Home Blog Page 5

Chronic Tendinopathy Solutions With Regenerative Orthopedics

Delve into the role of regenerative orthopedics in treating chronic tendinopathy and improving patient outcomes effectively.

Educational Abstract: Ultrasound-Guided Needle Fenestration for Tendinopathy with Integrative Chiropractic and Functional Medicine Care

In this educational post, I, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, present a comprehensive, first-person exploration of ultrasound-guided needle fenestration (also known as tendon fenestration or dry needling of tendons) as a modern, evidence-based intervention for chronic tendinopathy, particularly tennis elbow (extensor carpi radialis brevis, ECRB). I describe the technique, physiological rationale, ultrasound in-plane guidance, dosing (number of passes), and integration with orthobiologics such as dextrose prolotherapy and platelet-rich plasma (PRP). I also explain how we integrate this intervention into a chiropractic and functional medicine model that includes medical oversight, structured rehabilitation, and personal injury care.

I highlight our multidisciplinary framework at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933)—with over 40 years of clinical experience—serves as our Medical Director and Collaborative Physician, working closely with me, Dr. Alex Jimenez, DC. In this framework, we deliver patient-centered care that integrates medical diagnostics, interventional procedures, chiropractic neuromusculoskeletal optimization, functional medicine strategies, and graded rehabilitation. We emphasize outcomes tracking, ultrasound-based assessment, informed consent, and safety. The post synthesizes recent literature and leading researcher insights, translating them into practical, patient-focused steps.

Key topics include:

  • What needle fenestration is, why we use it, and how it triggers a controlled healing response
  • The ultrasound-guided technique: in-plane approach, bevel orientation, redirection strategy, and pass counts
  • The biological underpinnings: neovascular modulation, fibroblast activation, mechanotransduction, growth factor signaling, and nociceptive pathway recalibration
  • Integrative chiropractic care: spinal and regional joint biomechanics, kinetic-chain optimization, load management, and proprioceptive retraining
  • Medical oversight: patient selection, risk mitigation, anesthesia, sterile technique, and post-procedure pharmacologic considerations
  • Adjunctive therapies: prolotherapy (dextrose), PRP, shockwave, eccentrics and isometrics, BFR, and tendon-loading progressions
  • Clinical pathways for personal injury, workers’ compensation, and return-to-work/return-to-sport
  • Data-driven care: PROMs, ultrasound features, re-injury prevention, educational counseling, and psychosocial determinants

The goal is to empower patients and clinicians with a clear, evidence-based roadmap for diagnosing, treating, and rehabilitating tendinopathy using needle fenestration within a safe, integrated, and outcome-focused system of care.

Needle Fenestration for Tendinopathy: A Patient-Centered Journey

I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. In our clinic, we work every day to solve the puzzle of chronic tendon pain through evidence-based, integrative methods. Today, I will guide you through one of the most useful tools in our repertoire: ultrasound-guided needle fenestration, often called “tendon fenestration” or “dry needling of the tendon.” I will also explain how we integrate this interventional procedure with chiropractic care, functional medicine, and rehabilitative science to ensure patients receive complete, thoughtful care.

Before we proceed, I want to acknowledge our collaborative team. Our Medical Director and Collaborative Physician is Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine), who brings over 40 years of internal medicine expertise to our practice at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas. Her credentials include NPI #1164426749 and Texas MD License #J2933. She works in tandem with me, blending medical oversight, imaging, safety protocols, and pharmacologic guidance with musculoskeletal optimization through chiropractic and functional medicine.

When patients come to us with persistent tendon pain—tennis elbow, patellar tendinopathy, Achilles tendinopathy, rotator cuff tendinosis—we start by asking the right questions, reviewing the history carefully, performing a thorough physical and functional evaluation, and utilizing ultrasound imaging to pinpoint the degenerative areas. If conservative measures have failed or plateaued, needle fenestration can catalyze healing by converting the chronic degenerative state into a controlled acute phase—carefully and precisely—under ultrasound guidance.

Understanding Chronic Tendinopathy: Why Pain Persists

  • Key term: chronic tendinopathy
  • Key concept: degenerative-reparative mismatch

Chronic tendinopathy is not simply inflammation. In many cases, it is a degenerative process—a failed healing response characterized by disorganized collagen, increased ground substance, and in some cases neovascular ingrowth with accompanying nociceptive fiber ingrowth. Patients often describe pain with loading—gripping, lateral elbow stress, pushing, jumping or running, overhead activities—and the tendon exhibits hypoechoic changes on ultrasound, with loss of the crisp fibrillar pattern and focal thickening.

From a physiological standpoint, chronic tendinopathy can involve:

  • Collagen disarray and increased type III collagen replacing stronger type I
  • Tenocyte phenotype alteration, including disordered matrix production
  • Neovascularization and nerve ingrowth that sensitize the tendon region
  • Low-grade metabolic imbalance, where the tendon matrix is undernourished or subjected to loads it cannot adapt to
  • Mechanotransduction dysfunction, whereby appropriate loading stimuli fail to trigger robust, organized remodeling

This degenerative milieu has limited capacity to re-enter an acute, organized healing phase without a “reset.” That’s where needle fenestration fits—a targeted, ultrasound-guided intervention designed to induce microtrauma, encourage localized bleeding, and rekindle a healing cascade. We then pair this acute-phase trigger with smart load progressions, chiropractic joint optimization, and metabolic support to guide the tendon back to function.

What Is Needle Fenestration?

  • Key term: needle fenestration (tendon fenestration)
  • Key distinction: often performed without injectate; can be paired with prolotherapy or PRP

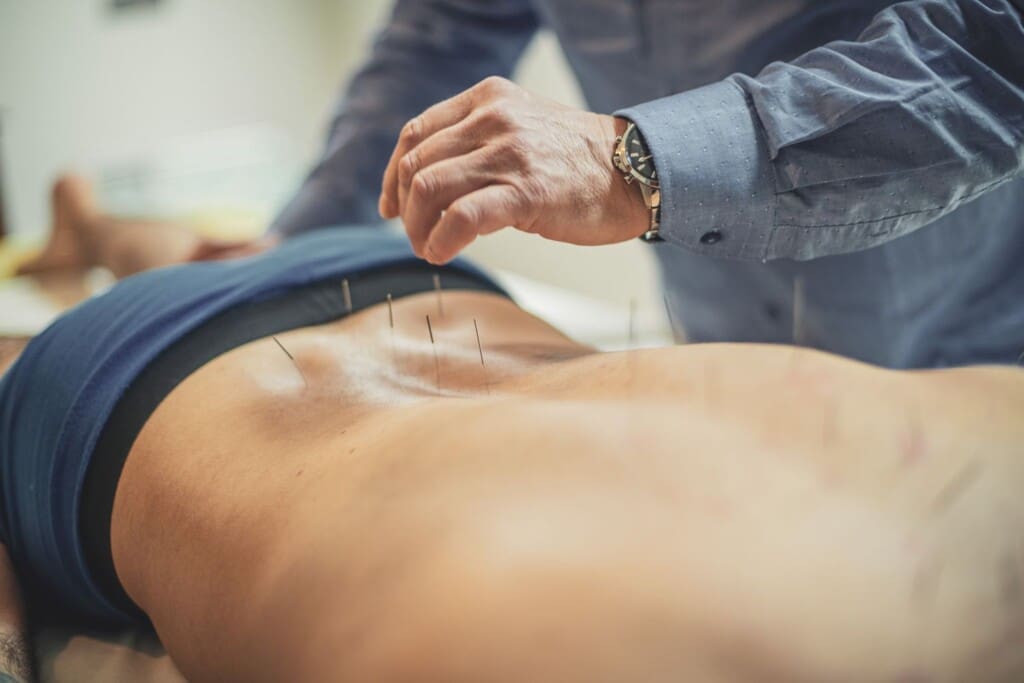
Needle fenestration is the deliberate creation of multiple, controlled micro-perforations within the pathologic region of a tendon using a fine needle under ultrasound guidance. The objective is to convert a chronic lesion into a managed, acute wound by initiating localized bleeding and an inflammatory milieu that can increase growth factor concentration and recruit reparative cells. By doing so, we aim to set the stage for proper collagen alignment through subsequent loading programs and rehabilitative strategies.

While the technique can be performed as a “dry” procedure (no injectate), it is commonly paired with:

  • Dextrose prolotherapy (typical concentrations 15–25% for peritendinous, sometimes higher for specific indications): a hyperosmolar solution designed to provoke a mild inflammatory response and promote healing
  • Platelet-rich plasma (PRP): a concentration of autologous platelets delivering growth factors like PDGF, TGF-β, VEGF, and IGF-1
  • Occasionally, other orthobiologics depending on patient-specific indications and evidence

Our approach is individualized. We choose between a purely fenestrative procedure, dextrose prolotherapy, or PRP based on ultrasound findings, chronicity, patient comorbidities, and prior responses to care. Dr. Cardenas oversees the medical aspects, including screening for contraindications, anticoagulation management, and anesthetic choices, while I focus on ultrasound-guided technique and functional rehabilitation.

Why Needle Fenestration Works: A Scientific Narrative
  • Key term: mechanobiology
  • Key mechanisms: microtrauma, inflammation cascade, growth factor activation, remodeling

The biological rationale for fenestration is straightforward but powerful:

  1. Microtrauma induces controlled bleeding in a chronic, relatively quiescent lesion.
  2. Platelet degranulation and local upregulation of growth factors (e.g., PDGF, TGF-β, VEGF) increase tenocyte activity and matrix synthesis.
  3. Inflammatory signaling recruits reparative cells and modulates extracellular matrix turnover.
  4. Collagen remodeling—especially if guided by proper loading—realigns fibers to functional orientation.
  5. Neovascular and nociceptive fiber modulation may downregulate pain signaling over time.

This combination facilitates a rebooting of the healing process. Without appropriate post-procedure care, however, the potential benefits can dissipate. Thus, the intervention is not isolated; it is integrated with load management, eccentric and isometric exercises, chiropractic joint optimization (to normalize regional kinematics), and functional medicine strategies that address recovery capacity (nutrition, sleep, systemic inflammation).

Our Multidisciplinary Model: MD Oversight + Chiropractic + Functional Medicine

  • Key roles:
    • Maria Guadalupe Cardenas, MD: Medical Director and Collaborative Physician (Internal Medicine; NPI #1164426749; Texas MD License #J2933)
    • Alex Jimenez, DC, APRN, FNP-BC: Chiropractic care, ultrasound-guided procedures, functional and rehabilitative pathways

Our clinic—Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic—functions as a multidisciplinary integrative system. This is common in injury care and integrative practices, where an MD provides medical direction alongside a chiropractor. Dr. Cardenas’ role is crucial for:

  • Medical screening and patient selection
  • Informed consent, anesthesia planning (e.g., 1% lidocaine for skin and subcutaneous local anesthesia)
  • Review of medications (e.g., anticoagulants, NSAIDs) and comorbidities (e.g., diabetes, autoimmune disease)
  • Infection prevention protocols and sterile technique
  • Selection of adjunct therapies (e.g., PRP vs. prolotherapy) and post-procedure pharmacology

My role focuses on:

  • Ultrasound-guided needle fenestration technique
  • Chiropractic evaluation and correction of kinetic-chain dysfunction (cervical-thoracic-shoulder-elbow-wrist-hand alignment, hip-knee-ankle linkages)
  • Rehabilitation programming—isometrics, eccentrics, heavy slow resistance, tempo work
  • Functional medicine—nutrition, anti-inflammatory strategies, sleep, stress management
  • Personal injury cases—documentation, causation analysis, return-to-work/sport plans

This synergy ensures safety, precision, and continuity of care.

Ultrasound-Guided Technique: Precision at Every Step

  • Key terms: in-plane approach, long-axis imaging, bevel orientation

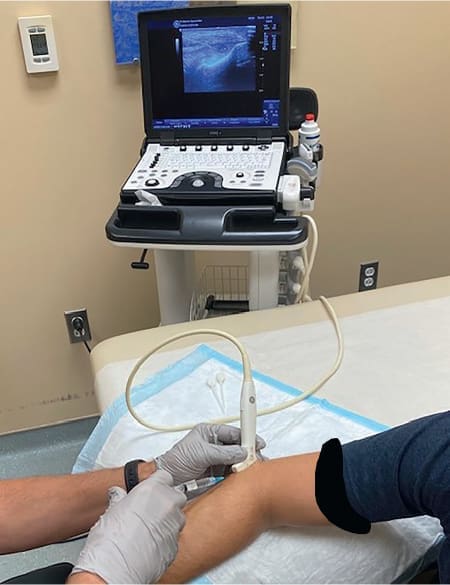
In our practice, ultrasound guidance is not optional—it is central. Visualization ensures that the needle path is precise, the lesion coverage is complete, and adjacent structures are respected. Here is how I execute the technique:

  1. Patient Positioning
    • For lateral epicondylalgia (tennis elbow), position the patient with the forearm supported and the elbow slightly flexed. We align the extensor tendon origin at the lateral epicondyle for optimal imaging.
    • Place the transducer to visualize the ECRB tendon in long axis, revealing fibrillar alignment and hypoechoic degenerative zones.
  • In-Plane Needle Alignment
    • I choose a needle gauge based on the tendon and intended injectate (if used). Commonly, a 22–25 gauge needle is selected for fenestration.
    • I approach in-plane to see the needle throughout its trajectory. This is non-negotiable for safety and precision.
    • The bevel-up orientation provides controlled entry and tactile feedback.
  • Anesthesia and Preparation
    • We often anesthetize the superficial tissues with 1% lidocaine using a 27-gauge needle. Dr. Cardenas oversees dosing and contraindications.
    • The field is prepped sterilely; sterile gel and probe covers are used.
  • Targeting the Hypoechoic Zone
    • I align the needle along the long axis of the tendon, entering the hypoechoic area that correlates with clinical pain and sonographic pathology.
    • With steady hand-eye coordination, I advance to the lesion, verifying continuous visualization of the needle tip.
  • Fenestration Pattern and Pass Counts
    • Once within the lesion, I perform controlled advancement and withdrawal, slightly redirecting to cover the lesion.
    • The number of passes varies by lesion size—typically between 15 and 5.0. This aligns with published ranges and clinical experience.
    • The tendon often feels “softer” as the passes proceed, indicating tissue disruption and microbleeding.
  • Transducer Reorientation
    • I may rotate the transducer 90 degrees (short-axis) to assess medial-lateral coverage.
    • Additional passes are directed to ensure we have comprehensively addressed the pathologic zone without over-penetration.
  • Adjunct Injection (If Planned)
    • If we have chosen prolotherapy (e.g., 15–25% dextrose for peritendinous support; higher concentrations based on protocol), I inject after fenestration with meticulous visualization.
    • For PRP, we coordinate timing and tendon state to optimize delivery into the fenestrated tissue.
  • Post-Procedure Protocols
    • A compressive wrap may be applied.
    • We counsel on relative rest for the initial window, followed by graded loading.

This structured, ultrasound-first approach allows me to ensure accuracy while minimizing risk. Visualization is everything.

Dextrose Prolotherapy: Why and When We Use It

  • Key terms: dextrose prolotherapy, hyperosmolar stimulus, proliferant

When I choose to integrate dextrose prolotherapy, it is to amplify the biologic signal toward healing. Dextrose functions as a hyperosmolar agent that can:

  • Stimulate local inflammatory mediators within a controlled range
  • Support fibroblast proliferation and matrix deposition
  • Complement the mechanical stimulus of fenestration

Concentration matters:

  • Peritendinous injections may use 15–25%
  • Intratendinous strategies and specific protocols may vary; patient selection and safety, overseen by Dr. Cardenas, are central.

In practice, dextrose is a cost-effective option with a favorable safety profile when executed by trained clinicians under sterile technique and ultrasound guidance. In our clinic, we choose dextrose when patients prefer a simpler, lower-cost adjunct to fenestration or when PRP is not indicated or desired.

Platelet-Rich Plasma (PRP): Biologic Synergy

  • Key terms: PRP, growth factors, autologous biologic

For select tendinopathies, PRP may complement fenestration by delivering a high concentration of platelets and growth factors directly to the lesion. Depending on the protocol and literature trends:

  • Leukocyte-rich PRP may be considered for certain chronic tendinopathies; others may favor leukocyte-poor depending on site and goals.
  • PRP is often chosen when patients have recurrent tendinopathy, large hypoechoic areas, or when prior conservative care failed.

The potential advantages include:

  • Enhanced growth factor milieu
  • Improved tenocyte activity
  • Possibly better mid-term outcomes in refractory cases

We counsel patients on evidence variability, cost, and expected timelines. Dr. Cardenas ensures appropriate screening (e.g., platelet disorders) and manages peri-procedural medications. I focus on precise delivery and rehabilitation coordination.

Safety, Contraindications, and Risk Mitigation

  • Key terms: sterile technique, anticoagulation management, neurovascular safety

Ultrasound guidance significantly improves the safety profile; however, vigilance is essential. Our safety strategies include:

  • Pre-procedure screening: anticoagulants, bleeding disorders, infection risks, uncontrolled diabetes, immune compromise
  • Sterile technique: skin prep, sterile probe cover, sterile gel, clean field
  • Anesthesia: appropriate dosing of lidocaine; avoid intratendinous anesthetic volume that might affect cellular function
  • Needle control: continuous visualization; avoid neurovascular structures
  • Post-procedure monitoring: immediate observation, clear instructions, emergency contact

We do not proceed if risk-benefit is unfavorable. With Dr. Cardenas’ oversight, we ensure medical alignment and informed consent.

Understanding Plantar Fasciitis- Video

Understanding Plantar Fasciitis | El Paso, Tx (2023)

Integrative Chiropractic Care: Aligning the Kinetic Chain

  • Key terms: kinetic-chain optimization, regional interdependence, spinal and peripheral joint biomechanics

Chronic tendon pain frequently reflects regional mechanical issues. For tennis elbow, for instance, the cervical-thoracic-shoulder-elbow-wrist-hand chain matters immensely. My chiropractic role is to:

  • Assess joint mobility—especially cervical and thoracic segments affecting scapular mechanics and distal stress
  • Correct segmental dysfunctions that perpetuate aberrant loading
  • Address shoulder girdle control, scapulothoracic rhythm, and proximal stability
  • Normalize wrist and hand biomechanics affecting extensor load

The reasoning is clear:

  • Tendons become symptomatic when loaded beyond their adaptive capacity
  • Joint restrictions or instability upstream or downstream can shift forces to vulnerable tendons
  • By restoring mobility and stability, we reduce aberrant loads and facilitate healing

I use precise joint adjustments, soft tissue mobilization, and neuromuscular re-education to recalibrate the system. This complements fenestration by ensuring the newly healing tendon experiences appropriate, not chaotic, stresses.

Rehabilitation: The Load Is the Medicine

  • Key terms: isometrics, eccentrics, heavy slow resistance, tempo control, BFR

After fenestration (with or without injectate), a structured rehab program is essential:

  • Phase 1: Acute Modulation
    • Relative rest for 48–72 hours based on procedure specifics
    • Gentle range-of-motion and isometrics to maintain neuromuscular activation
    • Pain target: mild discomfort allowed; avoid sharp pain
  • Phase 2: Early Loading
    • Isometric holds (e.g., wrist extension positions) to reduce pain and maintain tendon stiffness.
    • Transition to eccentrics—slow, controlled lowering phases
    • Mechanotransduction signals fibroblasts to align collagen along lines of stress
  • Phase 3: Progressive Overload
    • Heavy slow resistance (HSR) if appropriate—3–4 sets, 6–8 repetitions, controlled tempos
    • Tempo emphasis—3–5 seconds eccentric to enhance tendon remodeling
    • Blood flow restriction (BFR) as needed to stimulate adaptations with lower loads when pain or joint stress is a concern
  • Phase 4: Return to Function
    • Sport- or task-specific drills
    • Plyometric or elastic energy storage exercises if indicated (e.g., for Achilles)
    • Continuous monitoring of pain during and after sessions, aiming for acceptable ranges with steady progress

Why this works:

  • Tendons respond to tension more than to rest alone
  • Appropriate loading channels healing collagen into functional, aligned fibers
  • Isometrics can provide analgesia through cortical and spinal mechanisms
  • Eccentrics and HSR enhance tendon stiffness, resilience, and functional capacity

We tie this progression to patient goals, whether it is lifting children without pain, returning to tennis, or resuming manual work tasks.

Personal Injury and Occupational Care: Documentation and Function

  • Key terms: causation analysis, functional capacity, return-to-work

In personal injury contexts, clarity and documentation are critical:

  • Mechanism of injury analysis—acute overload vs. cumulative microtrauma
  • Baseline function and objective measures—grip strength, dynamometry, range of motion
  • Work task analysis—job demands, ergonomics
  • Return-to-work plans—graded transitions, accommodations, re-injury prevention

We collaborate with case managers, attorneys, and employers when appropriate, ensuring our evidence-backed interventions align with functional outcomes and legal documentation requirements. Needle fenestration can shorten downtime when paired with smart load progression and workplace modifications.

Patient Education: Shared Decision-Making

  • Key terms: informed consent, expectation setting, timelines

Patients must understand:

  • The goal: convert chronic tendon pathology into a healing phase
  • Expected discomfort during and after the procedure
  • Timelines: improvement may be gradual over weeks to months
  • The importance of rehab adherence and biomechanical corrections
  • The role of sleep, nutrition, and stress in healing

With this alignment, patients become active participants, not passive recipients.

A Closer Look at Tennis Elbow: ECRB Fenestration

Let’s walk through a procedure similar to what you might have seen in clinical demonstrations.

  • Setup: The lateral elbow is prepped; the ultrasound transducer is placed to visualize the extensor tendon origin with the hypoechoic area
  • Anesthesia: Anesthetize the superficial plane with 1% lidocaine via a 27-gauge needle.
  • Needle: Use a 22–25 gauge needle. We approach in-plane, long-axis, with bevel up.
  • Fenestration: Controlled passes are made—often 15–50—covering the lesion by minor redirections, both superficial and deep within the lesion. As passes progress, the tendon often feels softer.
  • Transducer rotation: Turning 90 degrees allows evaluation of medial-lateral coverage.
  • Adjunct: If planned, dextrose prolotherapy is injected to augment the inflammatory signal.
  • Completion: The needle is withdrawn; compressive measures may be applied; post-care instructions are provided.

We emphasize precise visualization: at all times, I keep the needle tip in view to ensure exact lesion targeting and safety.

Integrative Functional Medicine: Healing Capacity from Within

  • Key terms: anti-inflammatory nutrition, collagen substrates, sleep, stress resilience

Tendon healing is not only local—systemic factors matter. Our functional medicine approach includes:

  • Nutrition:
    • Adequate protein to support collagen synthesis
    • Vitamin C, copper, and zinc as cofactors for collagen crosslinking
    • Omega-3 fatty acids for inflammation modulation
    • Consider gelatin or collagen peptides pre-loaded before tendon exercises to improve collagen synthesis potentially
  • Glycemic control:
    • Hyperglycemia impairs collagen quality; we address insulin resistance if present
  • Sleep:
    • Growth hormone and tissue repair processes rely on robust sleep
  • Stress:
    • Excess cortisol can impede healing; we provide stress management strategies

This holistic layer ensures the local procedure has the systemic support needed for durable outcomes.

Clinical Observations: From the Field

Drawing from my clinical observations, which I discuss on our platforms, including Sciatica Clinic and my professional updates:

  • Patients with persistent lateral elbow pain often harbor proximal chain dysfunctions—thoracic hypomobility, scapular dyskinesis, cervical restrictions—that must be addressed.
  • Grip retraining and ergonomic coaching are essential adjuncts, especially for keyboard-intensive or tool-intensive occupations.
  • Early isometric interventions can reduce pain and facilitate adherence to later-stage eccentrics.
  • For athletes, return-to-play timelines improve with clear milestones that reflect objective metrics (e.g., pain-free grip strength benchmarks, functional tests).

These observations align with the broader literature and emphasize the need for a comprehensive plan rather than a single procedure.

For more of my insights and updates:

Evidence-Based Perspective: What the Research Suggests

  • Needle fenestration has been reported to improve pain and function in chronic tendinopathies when coupled with structured rehab.
  • Dextrose prolotherapy and PRP show variable results across studies; selection should be individualized.
  • Ultrasound guidance enhances accuracy and may improve outcomes by ensuring lesion coverage and minimizing risk.
  • Load management and progressive tendon loading are crucial determinants of success.
  • Integrative approaches that address biomechanics and systemic factors yield more durable results.

We stay current with leading researchers and evolving methodologies, applying what works in the clinic while respecting patient preferences and constraints.

Post-Procedure Care and Milestones

  • First 72 hours: swelling and soreness are common; use relative rest, cold packs as needed; avoid NSAIDs if we want to preserve the inflammatory signal (decision individualized by Dr. Cardenas).
  • Days 3–7: initiate isometrics; maintain gentle range.
  • Weeks 2–4: progress to eccentrics; monitor pain using a simple 0–10 scale; keep within tolerable ranges.
  • Weeks 4–8: transition to HSR; integrate functional patterns.
  • Beyond 8 weeks: return to sport/work tasks; continue preventive strategies.

We reassess at defined intervals using ultrasound, patient-reported outcomes, and functional tests to steer the plan.

Frequently Asked Questions

  • Will it hurt?
    • Some discomfort is expected during fenestration and in the days following. We mitigate this with local anesthesia and careful technique.
  • How many sessions?
    • Many patients respond to one procedure paired with rehab; some need repeat sessions depending on chronicity and lesion size.
  • Is PRP better than dextrose?
    • It depends—each has pros and cons, costs, and evidence variability. We discuss options transparently.
  • Can I work out?
    • Yes, but with planned progression. The right load at the right time is key.
  • Is it safe?
    • With ultrasound guidance, sterile technique, and medical oversight, we minimize risks. We screen carefully for contraindications.

Team Roles in Our Clinic

  • Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933)
    • Medical Director and Collaborative Physician
    • Oversees medical screening, contraindications, anesthesia, and sterile protocols
    • Guides pharmacologic decisions and co-manages comorbidities
  • Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST
    • Integrative chiropractic and functional medicine
    • Ultrasound-guided procedures (needle fenestration)
    • Rehabilitation design and kinetic-chain optimization
    • Personal injury care and functional outcomes

This blend reflects integrative and injury care clinics where collaboration drives quality.

Case Integration: From Assessment to Outcomes

  • Assessment
    • Detailed history, mechanism analysis, co-morbid assessment, medication review
    • Ultrasound mapping of tendon pathology
    • Biomechanical screening—regional interdependence emphasis
  • Intervention
    • Ultrasound-guided fenestration with or without injectate
    • Immediate post-procedure care with clear instructions
  • Rehabilitation
    • Staged loading with milestones and monitoring
    • Chiropractic adjustments and soft-tissue work to normalize mechanics
    • Functional medicine supports for healing capacity
  • Outcomes Tracking
    • Pain scores, function scales, ultrasound reassessment
    • Return-to-activity timelines and prevention strategies

Our integrated approach enhances predictability and reduces the chance of recurrence.

Why Integrative Chiropractic Care Matters Here

  • Chiropractic adjustments and neuromuscular re-education restore joint-centric contributions to tendon load management.
  • Tendons do not heal in isolation—joint angles, segmental motion, and motor control influence how force is transmitted.
  • With integrative chiropractic care, we reduce pathologic stress on the healing tendon and align the system for success.

This does not replace medical oversight; it complements it, reflecting the synergy of disciplines in modern musculoskeletal care.

Practical Tips for Patients

  • Follow the pain rules: mild is acceptable; sharp, persistent pain demands modification.
  • Trust the process: remodeling takes weeks to months, but each phase builds on the last.
  • Prioritize sleep and protein: your tendon is rebuilding—give it the tools.
  • Do your rehab: consistency trumps intensity early on.
  • Communicate: keep us informed about responses and barriers.

We are your team—MD, DC, rehab specialists—committed to your outcome.

Summary: Precision, Biology, and Integration

Needle fenestration is a precision tool that can rekindle healing in chronic tendinopathy. Its strength lies not just in the needle, but in the system that surrounds it: ultrasound visualization, medical oversight, integrative chiropractic optimization, rehabilitative science, and functional medicine. Together, these elements convert a stubborn tendon into a partner in healing—structured, supported, and guided by evidence and experience.

Our partnership—Dr. Maria Guadalupe Cardenas, MD, and me, Dr. Alex Jimenez, DC—reflects a contemporary, patient-centered model designed to maximize safety, efficacy, and durability. Whether you are an athlete, a clinician, or someone seeking relief from persistent tendon pain, this path offers a measurable, thoughtful way forward.

References

SEO tags: needle fenestration, tendon fenestration, ultrasound-guided fenestration, dextrose prolotherapy, PRP for tendinopathy, tennis elbow treatment, ECRB tendinopathy, integrative chiropractic care, functional medicine tendinopathy, elbow pain, Achilles tendinopathy, rotator cuff tendinopathy, heavy slow resistance, isometric analgesia, mechanotransduction, ultrasound musculoskeletal, internal medicine oversight, El Paso injury clinic, Dr. Alex Jimenez, Dr. Maria Cardenas

High-Volume Injections for Tendonopathy Techniques

High-Volume Injections for Tendonopathy Techniques

Understanding High-Volume Injections for Tendonopathy: A Modern Approach

By Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST

Medical Direction: Dr. Maria Guadalupe Cardenas, MD

Abstract

In this educational overview, I will be exploring an advanced, evidence-based technique for managing chronic tendonopathy known as brisement, or high-volume injection (HVI). Drawing on the latest findings from leading researchers like Dr. Fran O’Connor, we will explore the physiological basis of this procedure. Then, we’ll discuss its application in conditions like Achilles and patellar tendonopathy. Also, we will explain how it is performed under ultrasound guidance.

We will break down the mechanics of hydrostatic decompression and the disruption of problematic neovessels and neonerves. Importantly, you’ll learn why this approach differs from traditional treatments like fenestration. I will also explain how this cutting-edge modality integrates seamlessly into the comprehensive, multidisciplinary framework we use at Injury Medical Clinic. Our approach combines my expertise in chiropractic and functional medicine. Additionally, we include the invaluable medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD. As a result, we provide a holistic and effective path to recovery for our patients.

High-Volume Injections for Tendonopathy Techniques

Our Integrative and Collaborative Care Model

At Injury Medical Clinic, our philosophy is rooted in a patient-centered, integrative approach. This is made possible through our unique multidisciplinary structure. I, as a Doctor of Chiropractic and Advanced Practice Registered Nurse, work closely with Dr. Maria Guadalupe Cardenas. Dr. Cardenas is a Board-Certified Internist with over four decades of clinical experience. She serves as our Medical Director and Collaborative Physician. This partnership allows us to blend chiropractic care, functional medicine, rehabilitation, and conventional medical oversight. Notably, all of this happens under one roof.

Our model provides comprehensive solutions, particularly for complex musculoskeletal injuries and chronic pain conditions. While I focus on biomechanical alignment, neuromuscular function, and holistic wellness through chiropractic adjustments and functional medicine protocols, Dr. Cardenas provides essential medical diagnostics and oversight. Additionally, she can prescribe and manage treatments that fall within the scope of internal medicine. This synergy ensures our patients receive a well-rounded, robust treatment plan. It addresses their health from every angle. Procedures like the high-volume injections discussed here are prime examples of how we integrate advanced medical techniques with rehabilitative and chiropractic principles. As a result, our patients achieve superior outcomes.

What is Brisement, or High-Volume Injection (HVI)?

When we encounter persistent tendon pain, or tendonopathy, our goal is to address the underlying cause of the dysfunction. While some procedures focus on directly stimulating the tendon tissue itself, brisement (a French term for “breaking” or “disruption”) takes a different and innovative approach.

  • Distinct from Fenestration: It’s crucial to understand that brisement is not the same as tendon fenestration or tenotomy. In those procedures, a needle is used to repeatedly puncture the degenerated portion of the tendon to create micro-trauma and stimulate a healing response.
  • Targeting the Peritendinous Tissues: Brisement, in contrast, focuses on the space around the tendon. The primary target is the interface between the tendon and adjacent structures, such as the paratenon (the sheath-like covering of some tendons) or the nearby fat pad (like Kager’s fat pad behind the Achilles tendon).
  • Hydrostatic Decompression: The core mechanism of brisement is hydrostatic decompression. We inject a large volume of fluid—typically a mixture of a local anesthetic like lidocaine and sterile saline—into this space. This fluid mechanically and hydraulically separates soft tissues that have adhered to the tendon.

The Science Behind the Pain: Neovessels and Neonerves

To truly appreciate why brisement is effective, we must understand the pathophysiology of chronic tendonopathy. For a long time, we believed tendon pain was primarily an inflammatory condition (“tendinitis”). However, modern research has shown that chronic cases are more accurately described as tendinosis—a degenerative state characterized by disorganized collagen fibers, cellular changes, and a notable absence of inflammatory cells.

A key finding in the development of pain in tendinosis is the ingrowth of new, disorganized blood vessels (neovascularization) and accompanying nerve fibers (neoinnervation) into the tendon and surrounding tissues.

  • Neovessels and Neonerves: These new vessels and nerves, often found in the space anterior to the Achilles tendon or within Kager’s fat pad, are not part of the normal, healthy anatomy. They are believed to be a primary source of the persistent, nagging pain associated with the condition.
  • The Goal of Disruption: The high-volume injection aims to physically disrupt this delicate and problematic neurovascular network. By injecting a large fluid volume, we create a pressure wave that separates the adhered tissues and, in the process, breaks apart these tiny new vessels and nerves. This process effectively “resets” the local environment, reducing the primary pain generators and creating a better environment for healing.

How is the High-Volume Injection Procedure Performed?

The HVI procedure is a minimally invasive, office-based treatment performed with meticulous precision using ultrasound guidance. This ensures safety and accuracy by allowing us to visualize the target structures in real time. Here is a step-by-step breakdown of the process:

  1. Patient Positioning and Preparation: The patient is positioned comfortably to allow optimal access to the affected tendon. For an Achilles tendon, the patient typically lies face down. The area is then sterilized, and a sterile drape is applied.
  2. Ultrasound Examination: Using a high-frequency linear ultrasound probe, I conduct a thorough examination of the tendon in both long-axis (parallel to the tendon fibers) and short-axis (perpendicular) views. This allows me to identify the exact area of tendonopathy—often seen as tendon thickening, hypoechoic (darker) regions, and disorganized fiber patterns—and map out the precise injection path.
  3. Local Anesthesia: To ensure patient comfort, the skin and superficial tissues are first anesthetized using a very fine needle (25 or 27-gauge) to inject a small amount of lidocaine.
  4. The High-Volume Injection: Once the skin is numb, a slightly larger needle (21- or 22-gauge) is guided under direct ultrasound visualization into the target plane—for the Achilles, this is the space between the anterior border of the tendon and Kager’s fat pad.
  5. Real-Time Hydrodissection: As the fluid mixture (saline and lidocaine) is injected, we can watch on the ultrasound screen as it flows into the space, visibly lifting the tendon away from the underlying fat pad. This is the hydrodissection or hydrostatic decompression in action. You can literally see the fluid creating a new, clear space where adhesions once were. The volume of fluid injected can vary significantly, with literature reporting anywhere from 5 to 100 cc, depending on the tendon, the severity, and patient tolerance. We inject until we achieve adequate separation or meet resistance.

This mechanical separation is the key to the procedure’s success. It physically disrupts the adhesions and the pain-generating neovessels and neonerves. Consequently, it provides both immediate and long-term relief by altering the pathological environment.

The Role of Integrative Chiropractic Care in Recovery

Performing a procedure like a high-volume injection is only one part of a comprehensive recovery plan. True healing requires addressing the root biomechanical issues that led to the tendon overload in the first place. This is where integrating chiropractic care becomes essential.

Following an HVI procedure, my focus as a chiropractor and rehabilitation specialist shifts to restoring proper function and preventing recurrence.

  • Biomechanical Correction: I assess and correct underlying biomechanical faults in the kinetic chain. For Achilles tendinopathy, this often involves evaluating foot pronation, ankle mobility, pelvic alignment, and lumbar spine function. A misaligned pelvis or sacroiliac joint dysfunction can alter gait mechanics, placing excessive strain on the Achilles tendon. Chiropractic adjustments can restore proper joint motion and neurological function, which normalizes load distribution.
  • Soft Tissue Mobilization: We use techniques like Graston or Active Release Technique (ART) on the surrounding musculature (e.g., the gastrocnemius and soleus muscles) to break down scar tissue and improve muscle flexibility, further reducing tension on the treated tendon.
  • Personalized Rehabilitation: A structured and progressive loading program is critical. After the initial post-injection phase, we introduce specific eccentric exercises, which have been shown to stimulate collagen remodeling and strengthen the tendon. The program is carefully tailored to the patient’s progress, ensuring the tendon is strengthened without being re-injured.
  • Functional Medicine and Nutrition: We also look at systemic factors. Chronic inflammation, nutritional deficiencies (e.g., Vitamin C, zinc, and manganese), and poor metabolic health can all impair tissue healing. Through a functional medicine lens, we may recommend specific dietary modifications or supplements to support collagen synthesis and reduce systemic inflammation, creating an optimal internal environment for recovery.

This multifaceted approach ensures that we not only alleviate the immediate pain through the HVI procedure but also correct the underlying dysfunctions. In turn, this builds resilience and prevents the problem from returning. This synthesis of advanced medical intervention, expert chiropractic care, and holistic wellness strategies defines our commitment to our patients’ long-term health.

Revitalize and Rebuild with Chiropractic Care | El Paso, Tx (2023)

References

  1. Chan, O., O’Dowd, D., Padhiar, N., Morrissey, D., King, J., & Crisp, T. (2008). High volume image guided injections in chronic Achilles tendinopathy. Disability and Rehabilitation, 30(20–22), 1697–1708. https://doi.org/10.1080/09638280701785929
  2. Maffulli, N., Spiezia, F., Longo, U. G., Denaro, V., & Maffulli, G. D. (2013). High-volume image-guided injection for recalcitrant patellar tendinopathy in athletes. Clinical Journal of Sport Medicine, 23(2), 115–119. https://doi.org/10.1097/JSM.0b013e318269555b
  3. Morton, S., Williams, S., Valle, X., & de-la-Fuente, C. (2019). The new age of tendinopathy: new thoughts on the physiopathology and treatment. Current Sports Medicine Reports, 18(11), 385-391. https://doi.org/10.1249/JSR.0000000000000652

GLP-1 Antagonist Explained for Neuro-Immune Mechanisms

Dive into the science of the GLP-1 antagonist for the neuroimmune mechanism and its significance in disease management.

Abstract

As a clinician, I have watched many patients experience severe, burning skin sensitivity after starting retinoids or metabolic therapies that modulate GLP-1, GIP, and glucagon signaling. Patients often describe it as feeling like their skin was sandpapered or sunburned, with pain triggered by light touch from clothing or bed sheets. This constellation of sensations is consistent with drug-induced cutaneous allodynia and hyperesthesia, a neuroimmune phenomenon—not a classical allergy—driven by sensitized small-fiber peripheral nerves, mast cell hyperreactivity, and transient pro-inflammatory shifts associated with rapid adipose changes and electrolyte modulation.

In this educational post, I will explain, in accessible language, the underlying physiology of retinoid- and incretin-related skin sensitivity, including small-fiber nerve receptor distribution, mast cell thresholds, dorsal root ganglion (DRG) excitability, and renal electrolyte handling as relevant to nerve stability. I will also present how our integrative team at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas—led medically by Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749, Texas MD License #J2933), and clinically directed by me, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST—coordinates care across internal medicine, chiropractic, rehabilitation, and functional medicine to address this problem comprehensively.

This guide provides a detailed, evidence-aligned framework for evaluation and management, including dose modulation strategies, hydration and electrolyte planning, nutraceutical supports, neuromodulatory chiropractic methods, functional rehabilitation, stress regulation, and careful medical oversight. Throughout, I reference leading research and clinical insights to help you understand why each recommendation is used, how it fits within a modern integrative care model, and how to adapt treatment to individual needs. My goal is to empower patients and clinicians with a clear, science-forward pathway to relieve symptoms, prevent escalation, and restore function.

About Our Integrated Care Team and Clinic

  • Medical Director and Collaborative Physician: Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749; Texas MD License #J2933), with over 40 years of experience in internal medicine. She provides medical oversight, safety monitoring, medication management, and collaboration with our chiropractic and functional medicine services.
  • Clinical Director: Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. I integrate chiropractic care, functional medicine, small-fiber neurosensory assessments, and rehabilitative strategies within a multidisciplinary framework.
  • Clinic: Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic), El Paso, Texas. We offer integrative care for injury recovery, neurogenic and metabolic pain syndromes, and complex functional disorders.
  • Clinical observations and perspectives: My ongoing clinical notes and updates are accessible via sciatica.clinic and LinkedIn.

Why Your Skin Feels Like It’s On Fire: Understanding Drug-Induced Cutaneous Allodynia and Hyperesthesia

  • Key terms:
    • Allodynia: Pain provoked by stimuli that do not normally cause pain (e.g., clothing brushing the skin).
    • Hyperesthesia: Heightened sensitivity to sensory input, resulting in exaggerated pain responses.
    • Neuroimmune axis: The integrated communication network of the nervous and immune systems.
    • Incretin pathways: Hormonal networks that include glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon.

Patients often report that after starting certain therapies—especially retinoids or incretin-modulating agents—light touch feels like a burn, seams aggravate the skin, warm water stings, and even bed sheets hurt. These are hallmark features of a sensitized small-fiber system and mast cell hyperreactivity. This condition is not an allergy in the classical IgE sense. Rather, it is a dynamic, reversible neuroimmune adaptation in which peripheral nerves and immune sentinels become hyperexcitable, lowering the firing threshold for pain signals.

I emphasize this: your skin is not randomly malfunctioning; it is responding to biochemical signals that shift excitability thresholds. With appropriate care—adjusting dose, stabilizing electrolytes, calming mast cells, supporting nerve membranes, and restoring neuroimmune balance—most patients improve significantly.

The Neuroanatomy of Sensitivity: Small-Fiber Nociceptors and Their Receptors

  • Key structures:
    • C-fibers: Unmyelinated fibers that transmit slow, burning pain and warmth.
    • A-delta fibers: Thinly myelinated fibers that transmit sharp, fast pain and cold.
    • Dorsal root ganglia (DRG): Clusters of sensory neuron cell bodies at the spinal level, integrating peripheral inputs before they enter the spinal cord.
    • Keratinocytes and immune cells: Skin cells that communicate with nerves via cytokines, neuropeptides, and receptor-mediated signals.

Emerging research has shown that small-fiber nerves in the peripheral skin express receptors relevant to incretin signaling. This includes GLP-1 receptors on sensory fibers, with neuromodulatory roles in pain, temperature, and touch processing. When these receptors are repeatedly or intensely engaged, they can increase neural excitability. In clinical terms, that means previously neutral signals (a breeze, a shirt seam) now trigger discomfort.

Importantly, nociceptive neurons respond to signal patterns, not intentions. If a medication modulates receptors affecting neuronal excitability, the nervous system will adapt accordingly. That is what you are feeling—an adaptation that can be nudged back toward balance.

Mast Cells: The Immune “Border Patrol” of the Skin

  • Key concepts:
    • Mast cells reside in the skin, gut, and other tissues; they store histamine, prostaglandins, bradykinin, leukotrienes, and neuropeptides like substance P.
    • Mast cell activation releases these mediators, contributing to neurogenic inflammation, vasodilation, and pruritus or pain.
    • Lowered degranulation thresholds create a “hair trigger” response, leading to symptoms with minimal provocation such as heat, light pressure, or friction.

GIP receptors are present on mast cells. Chronic stimulation can modulate the threshold at which mast cells degranulate. When thresholds are lowered, normal micro-stimuli (fabric contact, mild temperature changes) can lead to local histamine and neuropeptide release, amplifying skin sensitivity. This is a key reason why antihistamines often only partially address symptoms—they may reduce histamine’s effects but do not fully normalize multi-mediator mast cell activity, nor do they recalibrate linked neural excitability.

An effective approach aims to stabilize mast cells, modulate neuropeptide signaling, and improve barrier integrity while simultaneously addressing nerve membrane stability and systemic inflammatory tone.

The Dorsal Root Ganglion and Sensory Gain: Why Everything Feels Louder

  • Key point:
    • DRG neurons function as “gain controllers” for sensory input. Their excitability determines whether a peripheral signal is amplified into pain.

Glucagon receptors have been implicated in modulating neuronal excitability within sensory pathways. If glucagon receptor activation increases the gain (amplification) on nociceptive circuits, then mechanoreceptive inputs might be “recoded” as painful. Clinically, patients describe this as a heightened “loudness” of touch signals. When this occurs alongside mast cell activation and small-fiber sensitization, the cumulative effect is the painful skin sensitivity pattern we see.

Integrative strategies aim to reduce the gain within the DRG and downstream spinal processing while quieting peripheral inputs from sensitized skin.

Rapid Fat Loss and Transient Inflammation: When Biology Needs Time to Adapt

  • Key insight:
    • Rapid adipose reduction can create a temporary pro-inflammatory milieu due to shifts in adipokines, free fatty acid flux, and cytokine expression.

This transient state can amplify neural sensitivity and immune reactivity. Patients sometimes assume that faster weight loss is always better; however, biology often needs time to adapt to new set points. When weight reduction outpaces adaptation, tissues may bathe in inflammatory signals that prime nociceptors and mast cells, increasing pain in response to minor stimuli.

Medical guidance that calibrates the pace of weight loss, supports anti-inflammatory signaling, and stabilizes nerves can alleviate this transient, adaptive pain pattern.

Electrolyte Physiology and Nerve Stability: Why Magnesium and Sodium Matter

  • Key concepts:
    • Sensory nerve stability depends on the resting membrane potential, which is influenced by ion gradients (sodium, potassium, calcium, magnesium).
    • Magnesium acts as a physiological stabilizer, modulating voltage-gated channels and NMDA receptor activity; low magnesium increases membrane excitability.
    • Alterations in renal electrolyte handling can shift sodium, water, and intracellular magnesium balance.

If renal effects of certain therapies increase sodium and water loss and reduce intracellular magnesium, nerve sheaths lose part of their stabilizing “electrolyte shield.” This leads to a depolarized resting membrane potential, making nerve fibers more likely to fire in response to trivial stimuli. Clinically, patients experience spontaneous tingling, burning, or hypersensitivity.

A thoughtfully designed hydration and electrolyte strategy helps reestablish stable membrane potentials and reduces the propensity for spontaneous firing.

What This Condition Is Not: Clarifying Misconceptions

  • Not a classical IgE-mediated allergy: While histamine may be involved, the primary driver is neuroimmune sensitization and lowered activation thresholds across multiple mediators and receptors.
  • Not nerve “damage”: The system is hyperresponsive, not necessarily structurally injured. This is important because the treatment target is recalibration, not repair of a lesion.
  • Not purely psychological: While stress can amplify pain pathways, the physiology discussed here is measurable and modifiable through targeted interventions.
  • Not solved by sedating antihistamines alone: These may reduce histamine symptoms but do not adequately address DRG gain, small-fiber excitability, membrane stability, or multi-mediator mast cell outputs.

Understanding these distinctions helps patients feel validated and guides clinicians toward more comprehensive, effective interventions.

Clinical Portrait: What Patients Tell Me

Patients commonly describe:

  • Burning, sunburn-like sensations at baseline.
  • Pain triggered by clothing seams, light touch, or bed sheets.
  • Intensified discomfort with warm water or heat exposure.
  • Flares during periods of rapid weight change, poor sleep, stress, or dehydration.
  • Partial relief from antihistamines, with persistent pain.
  • Symptom improvement when hydration and electrolytes are optimized, doses are adjusted, and nerve-calming supports are applied.

From my clinical observations across sciatica-centric patients and broader pain populations, these patterns are consistent with small-fiber sensitization and neuroimmune amplification. Outcomes improve with a stepwise, mechanistically informed approach under medical oversight.

Our Integrative Care Model: How We Coordinate Chiropractic, Internal Medicine, and Functional Care

  • Leadership:
    • Medical oversight by Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933).
    • Clinical direction and integrative case management by me, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST.
  • Multidisciplinary services:
    • Internal medicine evaluation and safety monitoring.
    • Chiropractic neuromusculoskeletal assessments and gentle neuromodulatory adjustments.
    • Functional medicine analysis of nutritional status, electrolytes, and inflammatory markers.
    • Small-fiber neuropathy screening and autonomic balance strategies.
    • Rehabilitation, graded sensory exposure, and posture/biomechanics support.
    • Personal injury care where relevant, addressing overlapping pain generators.
  • Workflow:
    1. Intake and medical review (medications, labs, comorbidities).
    2. Neuromusculoskeletal exam focusing on small-fiber signs and segmental facilitation.
    3. Functional and nutritional assessment (hydration, electrolytes, micronutrients).
    4. Tailored plan: dose modulation, electrolyte therapy, mast cell stabilization, chiropractic neuromodulation, rehabilitative sensory re-education.
    5. Regular follow-up, adjusting pace according to response and safety metrics.

This model ensures safety, adaptability, and comprehensive coverage of neural, immune, and metabolic contributors.

Stepwise Strategy to Calm Sensitized Skin and Nerves

  • Principles:
    • Reduce the driving signal (e.g., dose modulation).
    • Stabilize nerve membranes (electrolytes, magnesium).
    • Quiet mast cell outputs (diet, nutraceuticals, medications when appropriate).
    • Lower DRG gain (gentle neuromodulation, sleep, stress regulation).
    • Rebuild resilience (graded exposure, rehabilitation, nutrition).
  • Practical steps:
    1. Collaborative dose reevaluation: If an agent is likely contributing, our team discusses dose reduction or interval adjustments under Dr. Cardenas’s medical supervision.
    2. Hydration and electrolytes: Structured intake balancing water with sodium and potassium, plus magnesium support to stabilize nerve membranes.
    3. Anti-inflammatory nutrition: Emphasize omega-3s, polyphenols, and low-glycemic, mineral-rich foods.
    4. Mast cell support: Consider a low-histamine diet trial, quercetin, vitamin C, and other stabilizing supports under guidance.
    5. Nerve support: Alpha-lipoic acid, benfotiamine, and B-complex nutrients may support neural metabolism.
    6. Integrative chiropractic care: Gentle techniques to reduce segmental facilitation and improve autonomic tone.
    7. Rehabilitation: Graded sensory desensitization, skin care routines, and biomechanical support.
    8. Sleep and stress strategies: Improving restorative sleep and parasympathetic tone to reduce DRG excitability.
    9. Monitoring and adjustments: Regular check-ins to titrate supports and avoid overcorrection.

Dose Modulation: Why Slowing Down Can Speed Relief

When a medication or supplement is driving neuroimmune sensitivity, simply forcing through discomfort is not optimal. Dose modulation allows the nervous system to adapt while maintaining therapeutic goals. The key is individualized balance—reduce enough to alleviate neuroexcitation, but not so much that we lose the benefit. This is coordinated with Dr. Cardenas to ensure safety.

  • Indicators for dose review:
    • New-onset allodynia/hyperesthesia.
    • Rapid weight loss beyond planned targets.
    • Signs of electrolyte imbalance (cramps, palpitations, excessive thirst).
    • Sleep disruption or autonomic symptoms.
  • Clinical rationale:
    • Reducing receptor activation decreases excitability.
    • Allowing time for adipose and inflammatory adaptation reduces peripheral sensitization.
    • Mitigating renal electrolyte shifts stabilizes membranes and reduces firing.

Hydration and Electrolyte Strategy: Building a Stable Nerve Membrane

  • Hydration is not just water:
    • Overconsumption of plain water without electrolytes can dilute plasma sodium and lower extracellular osmolality, destabilizing nerve function in sensitive contexts.
  • Structured intake:
    • Individualize daily fluid targets for body size, environment, and medical status.
    • Tailor sodium and potassium balance to health status and labs.
    • Magnesium supplementation (e.g., glycinate or threonate forms) to support intracellular levels and neural stability.
  • Rationale:
    • Sodium helps maintain extracellular volume and stable nerve conduction.
    • Potassium supports proper membrane potential across excitable tissues.
    • Magnesium modulates calcium influx and NMDA receptor activity, reducing hyperexcitability.
  • Monitoring:
    • We consider medical conditions (hypertension, kidney disease) and medications (diuretics) before adjusting electrolytes.
    • Cardenas oversees labs and safety for individualized adjustments.

Mast Cell Stabilization: Multipronged Strategies

  • Dietary support:
    • Trial a low-histamine diet for 2–4 weeks to assess symptom responsiveness.
    • Avoid triggers (aged cheeses, cured meats, fermented products) if they exacerbate flares.
    • Emphasize anti-inflammatory foods: omega-3-rich fish, berries, green leafy vegetables.
  • Nutraceuticals:
    • Quercetin and luteolin as mast cell modulators.
    • Vitamin C as a cofactor for histamine degradation.
    • Consider DAO support if histamine intolerance is suspected.
  • Medications:
    • H1 and H2 blockers may help some patients.
    • Cromolyn sodium and ketotifen (where appropriate) can provide mast cell stabilization; coordinated through internal medicine.
  • Rationale:
    • Reduce mediator load while addressing upstream sensitizers.
    • Stabilize thresholds to prevent trivial stimuli from triggering disproportionate reactions.

Nerve Metabolic Support: Alpha-Lipoic Acid, Benfotiamine, and B-Complex

  • Alpha-lipoic acid (ALA):
    • Antioxidant and metabolic cofactor that supports nerve function and reduces oxidative stress.
    • Especially helpful in small-fiber neuropathic patterns.
  • Benfotiamine:
    • Lipid-soluble thiamine derivative aiding glucose metabolism and reducing advanced glycation end-products that can sensitize nerves.
  • B vitamins:
    • Adequate B1, B6 (in non-excessive, physiologic doses), and B12 support myelination and nerve metabolism.
  • Clinical rationale:
    • Improve nerve energy handling and reduce oxidative stress, lowering background excitability.

Integrative Chiropractic Care: Calming Segmental Facilitation and Restoring Autonomic Balance

In this context, chiropractic care is about gentle neuromodulation, not forceful adjustments. When nerves are sensitized, spinal segments can become facilitated: a low threshold for activation due to persistent afferent input. This contributes to hyperexcitability within the DRG and spinal cord.

  • Techniques:
    • Low-force mobilizations and instrument-assisted adjustments targeting facilitated segments.
    • Cranial-sacral and thoracic outlet soft tissue techniques to reduce sympathetic tone.
    • Myofascial release focusing on dermal and subdermal layers to improve cutaneous gliding without provoking flares.
    • Neurodynamic flossing adapted for hypersensitivity to prevent exacerbations.
  • Rationale:
    • Reduce aberrant afferent input to the DRG.
    • Encourage parasympathetic dominance and improve sleep quality.
    • Restore normal mechanoreceptor-to-nociceptor balance.
  • Outcome measures:
    • Reduction in allodynia zones.
    • Improved tolerance to clothing and light touch.
    • Enhanced heart rate variability (a marker of autonomic balance).

The Non-Surgical Approach to Wellness with Chiropractic Care- Video

The Non-Surgical Approach to Wellness with Chiropractic Care | El Paso, Tx (2024)

Functional Rehabilitation: Gradual Desensitization and Protective Biomechanics

  • Graded sensory exposure:
    • Start with non-irritating textures applied briefly, progressing to more challenging stimuli.
    • Pair exposure with diaphragmatic breathing to lower sympathetic arousal.
  • Skin barrier care:
    • Gentle, fragrance-free emollients to support stratum corneum integrity.
    • Avoid heat exposure and harsh soaps during flare phases.
  • Movement:
    • Controlled mobility and light resistance training to promote endogenous analgesia.
    • Posture and ergonomics to reduce mechanical stress on sensitized dermatomes.
  • Rationale:
    • Recalibrate cortical and spinal processing through safe, repeated non-threatening stimuli.
    • Minimize peripheral triggers while building tissue resilience.

Sleep, Stress, and Parasympathetic Tone: The Hidden Levers of DRG Gain

  • Sleep optimization:
    • Consistent schedule, cool/dark environment, and reducing evening stimulants.
    • Consider magnesium and behavioral strategies to enhance deep sleep.
  • Stress modulation:
    • Breathing exercises, mindfulness-based stress reduction, or biofeedback to raise vagal tone.
    • Gentle yoga or tai chi tailored to avoid cutaneous triggers.
  • Rationale:
    • DRG excitability is bidirectionally linked to autonomic state; enhancing parasympathetic tone reduces hyperexcitability.
    • Sleep consolidates neuroplastic changes toward normalization.

Safety Considerations and Red Flags

  • Seek medical evaluation for:
    • Rapidly progressive weakness, numbness, or motor deficits.
    • Signs of systemic allergic/anaphylactic reactions (rare but urgent).
    • Severe dehydration, palpitations, or syncope.
    • Underlying conditions like kidney disease or heart failure that influence hydration strategies.
  • Dr. Cardenas’s oversight:
    • Ensures that electrolyte and dose adjustments are safe.
    • Coordinates lab monitoring and medication management.
    • Screens for alternative diagnoses (e.g., small-fiber neuropathy due to diabetes, B12 deficiency, autoimmune etiologies).

Case Vignettes: Patterns and Progress

  • Case 1: Rapid weight loss with skin allodynia
    • Presentation: Severe burning with clothing contact; rapid adipose reduction in 6 weeks.
    • Intervention: Dose modulation, electrolyte repletion, low-histamine diet, ALA/benfotiamine, gentle chiropractic neuromodulation.
    • Outcome: Significant symptom reduction within 2–4 weeks; normalized tolerance to touch over 8–12 weeks.
  • Case 2: Heat-triggered flares with mast cell sensitivity
    • Presentation: Warm showers unbearable; flushing and pruritus.
    • Intervention: H1/H2 support, quercetin, vitamin C, graded cool-to-lukewarm desensitization, sleep optimization.
    • Outcome: Marked reduction in flares; improved quality of life and confidence in daily routines.

Note: These are representative patterns reflective of clinical observations and do not replace individualized care.

How We Evaluate You: An Integrative Intake

  • Medical history:
    • Current medications and supplements, timing of symptom onset relative to dose changes.
    • Comorbid conditions (metabolic, autoimmune, cardiovascular).
    • Hydration habits, diet, stress, and sleep.
  • Physical exam:
    • Small-fiber signs (pinprick, temperature, light touch, cotton swab testing).
    • Segmental facilitation and myofascial trigger patterns.
  • Labs and tests:
    • Basic metabolic panel, magnesium status (clinical inference and RBC magnesium where available).
    • Inflammatory markers as indicated.
    • Consider small-fiber assessments (QSART, skin biopsy) in refractory cases, with appropriate referral.
  • Plan:
    • Collaborative strategy emphasizing safety and incremental gains.

Why Antihistamines Alone Often Fall Short

  • Multimediator reality:
    • Mast cells release more than histamine; prostaglandins, leukotrienes, bradykinin, and substance P also contribute to pain and vasodilation.
    • Nerve sensitization is electrically mediated and requires membrane stabilization.
  • Integrative fix:
    • Combine mast cell stabilization with electrolyte support, nerve metabolism aids, dose modulation, and neuromodulation.
    • Address DRG gain through sleep, stress, and gentle chiropractic care.
  • Clinical outcome:
    • Comprehensive approaches yield durable relief by addressing root mechanisms.

Practical Daily Plan: A Sample Framework

  • Morning:
    • Electrolyte-balanced hydration.
    • Gentle movement and breathwork.
    • Nutraceutical support as personalized.
  • Midday:
    • Balanced meal emphasizing minerals and omega-3s.
    • Short graded sensory exposure session.
  • Afternoon:
    • Light resistance or mobility work.
    • Hydration check-in and magnesium timing based on tolerance.
  • Evening:
    • Warm-to-lukewarm shower; gentle emollients.
    • Wind-down routine; screen-light reduction.
    • Sleep support as needed.
  • Weekly:
    • Chiropractic neuromodulation session (as indicated).
    • Review symptoms and adjust graded exposure challenges.
  • Monthly:
    • Medical follow-up for dose and safety checks.
    • Labs as indicated.

This is illustrative; actual plans are tailored to individual needs and medical status.

Special Populations and Considerations

  • Cardiometabolic conditions:
    • Close oversight for sodium and fluid balance.
    • Adjust electrolyte strategies considering blood pressure and renal function.
  • Athletes:
    • Higher sweat losses may necessitate adjusted electrolyte targets.
    • Manage training load to avoid sensitization spikes.
  • Older adults:
    • Increased attention to polypharmacy and renal reserve.
    • Slower graded exposure and conservative chiropractic techniques.
  • Post-injury or post-surgical patients:
    • Integrate scar desensitization and mechanotherapy with caution.
    • Coordinate with surgical teams as needed.

What to Expect Over Time: A Healing Trajectory

  • Early phase (1–2 weeks):
    • Reduction in intensity of burning and improved tolerance to light touch.
    • Better sleep with consistent hydration and magnesium.
  • Intermediate phase (4–8 weeks):
    • Noticeable normalization of daily triggers (clothing seams, bed sheets).
    • Improved exercise tolerance and mood.
  • Longer term (3–6 months):
    • Stable set points with rare flares.
    • Confidence in self-management tools and resilience.

Individual timelines vary, especially with comorbidities or ongoing metabolic therapies. The key is steady progress and iterative adjustments.

Patient Education: Language That Empowers

  • Your nerves are not broken; they are responsive to signals we can change.
  • Your immune system is not your enemy; it is over-attentive and can be coached to calm down.
  • Faster is not always better; giving biology time to adapt prevents suffering.
  • Precision hydration and electrolytes are medicine for your nerves.
  • Gentle, consistent inputs teach the system safety and restore normal sensation.

In my experience, when patients understand the why, they follow through and achieve better outcomes.

Integrative Chiropractic In Practice: What I Do and Why

  • Low-force adjustments:
    • Reduce segmental facilitation, minimizing provocation.
    • Encourage mechanoreceptive input that competes with nociception in the dorsal horn.
  • Soft tissue and fascial glide:
    • Gentle, superficial techniques to restore cutaneous glide and reduce dermal mechanosensitivity.
  • Autonomic balancing:
    • Thoracic mobilization and rib mechanics to support respiration and vagal tone.
    • Cranial-sacral applications to promote parasympathetic dominance.
  • Education and pacing:
    • Teach patients to avoid overexposure.
    • Integrate movement literacy to prevent re-sensitization.

This is not “one-size-fits-all.” Adapt every session to the patient’s current state to ensure safety and incremental gains.

Coordinating With Internal Medicine: Dr. Cardenas’s Role

  • Medical review:
    • Medication reconciliation and dose evaluation.
    • Safety labs for electrolytes and renal function.
  • Pharmacologic options:
    • Considering non-sedating antihistamines, H2 blockers, mast cell stabilizers, or neuropathic pain agents where appropriate.
    • Monitoring interactions and contraindications.
  • Collaborative care:
    • Communicating changes and response patterns to align chiropractic and rehab pacing.
    • Addressing comorbidities that influence nerve stability (e.g., diabetes, thyroid disorders).

This synergy allows us to implement comprehensive strategies while ensuring medical safety and efficacy.

Functional Medicine Lens: Nutritional and Metabolic Foundations

  • Diet:
    • Emphasis on anti-inflammatory patterns: Mediterranean-style diet, rich in vegetables, olive oil, fish, and nuts.
    • Mineral-dense foods to support electrolyte balance.
  • Micronutrients:
    • Magnesium, B-complex, vitamin D (tailored to status), and omega-3s.
  • Gut-skin-nerve axis:
    • Address gut dysbiosis if suspected, as it can influence systemic inflammation and mast cell activity.
  • Personalized care:
    • Adjust based on labs, symptoms, and response.

Personal Injury Context: Overlapping Pain Generators

In personal injury cases, cutaneous hyperesthesia may overlap with myofascial pain, nerve entrapments, or central sensitization from trauma. Our clinic integrates:

  • Diagnostics to identify structural contributors.
  • Rehabilitation to correct biomechanics.
  • Neuromodulatory chiropractic care to reduce central sensitization.
  • Internal medicine oversight to adjust medications that may influence neuroimmune tone.

This approach enhances recovery trajectories and reduces chronic pain risk.

Real-World Tips: Reducing Daily Triggers

  • Clothing:
    • Soft, seamless fabrics; avoid tight elastics during flares.
    • Pre-wash new garments with hypoallergenic detergents.
  • Bathing:
    • Use lukewarm water; keep showers brief; pat dry gently rather than rubbing.
    • Apply emollients to slightly damp skin.
  • Environment:
    • Avoid overheating; maintain moderate humidity.
    • Gentle fans or airflow can help if they don’t trigger symptoms.
  • Work and activity:
    • Plan graded exposure; avoid long static positions.
    • Micro-breaks to reduce sustained cutaneous load.

Small, consistent changes add up to less frequent and less intense flares.

Frequently Asked Questions

  • Is this permanent?
    • Typically not. With appropriate care, most patients improve significantly. The key is addressing drivers and giving the system time.
  • Do I have to stop my medication?
    • Not necessarily. Many patients improve with dose modulation and supportive care. Decisions are individualized with medical oversight.
  • Can I exercise?
    • Yes, but adapt intensity and clothing to reduce triggers. Exercise can aid neuroimmune balance when paced.
  • Are supplements required?
    • They are tools, not mandates. Some patients benefit significantly; others gain relief from hydration and pacing alone.
  • What about antihistamines?
    • They can be part of the plan, especially for histamine-dominant flares, but are rarely sufficient as a sole therapy.

Outcome Tracking: Measuring What Matters

  • Symptom diaries:
    • Document triggers, intensity, and duration.
    • Track hydration and sleep patterns.
  • Functional goals:
    • Clothing tolerance, shower comfort, improved sleep, and return to activities.
  • Physiological markers:
    • Heart rate variability for autonomic balance (optional).
    • Labs as clinically indicated.

Tracking empowers shared decision-making and personalization.

My Clinical Observations and Reflections

From my practice and shared insights on sciatica. clinic and LinkedIn, I observe that:

  • The nervous system often responds quickly to electrolyte correction, particularly magnesium and balanced sodium/potassium intake.
  • Patients gain momentum when they understand the rationale behind dose modulation.
  • Gentle chiropractic neuromodulation accelerates normalization of segmental facilitation and autonomic tone.
  • Sleep is often the differentiator between partial and robust recovery.
  • Mast cell stabilization is most effective when combined with nerve membrane stabilization and autonomic balancing.

These patterns inform our protocols and the patient education we provide daily.

Implementation Checklists

  • Initial week:
    • Review dose with medical team.
    • Begin structured hydration with electrolytes.
    • Introduce magnesium if appropriate.
    • Start low-histamine trial and gentle desensitization.
    • Schedule chiropractic neuromodulation session.
  • Weeks 2–4:
    • Evaluate response; adjust supports.
    • Introduce ALA/benfotiamine if indicated.
    • Expand graded exposure; begin light strength training.
    • Reinforce sleep strategies.
  • Weeks 4–8:
    • Progress desensitization; normalize daily triggers.
    • Reassess medication dosing with Dr. Cardenas.
    • Consider scaling down supports as stability improves.
  • Ongoing:
    • Maintain hydration/electrolyte habits.
    • Use flare plans as needed.
    • Continue movement and recovery balance.

Ethical and Practical Considerations

  • Individualization:
    • Not all patients will need all steps; some will require more medical interventions.
  • Monitoring:
    • Avoid self-directed high-dose electrolyte strategies without medical guidance.
  • Communication:
    • Keep all providers aligned to prevent conflicting recommendations.
  • Safety:
    • Prioritize kidney, cardiovascular, and metabolic safety in all plans.

Integrative Medicine: Aligning Evidence With Compassion

Our goal is to translate complex physiology into clear, actionable steps while honoring patient experience. Drug-induced cutaneous allodynia and hyperesthesia can be frightening and disruptive. With a careful, collaborative approach, we alleviate suffering and restore normalcy.

At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), we combine internal medicine, chiropractic neuromodulation, functional strategies, and rehabilitation to address the multi-layered nature of this condition. Dr. Maria Guadalupe Cardenas, MD, ensures medical rigor and safety; I guide integrative implementation and neuromusculoskeletal care. Together, we help patients regain comfort and confidence.

Conclusion

Cutaneous allodynia and hyperesthesia in the context of retinoids or incretin-modulating therapies reflect a neuroimmune recalibration that can be improved by:

  • Dose modulation under medical supervision.
  • Precision hydration and electrolyte balance to stabilize nerve membranes.
  • Mast cell stabilization to raise degranulation thresholds.
  • Nerve metabolic support with targeted nutraceuticals.
  • Gentle integrative chiropractic neuromodulation to reduce segmental facilitation and enhance autonomic balance.
  • Functional rehabilitation with graded sensory exposure and movement.
  • Sleep and stress optimization to lower DRG gain.

By addressing biology at each level—peripheral, spinal, autonomic, and metabolic—we restore healthy set points and reduce discomfort. The integrative pathway is evidence-alignedandt patient-centered, ensuring relief is achieved safely and sustainably.

If you are experiencing these symptoms, reach out. Our team is ready to help you navigate a clear, compassionate, and scientifically grounded path forward.

References

Note: Citations are provided for educational anchoring. For precise article details, consult the linked journals and their latest publications relevant to incretin receptor expression in peripheral nerves, mast cell immunobiology, DRG excitability, electrolyte physiology, and neuropathic pain management.

SEO tags: retinoid-induced skin sensitivity, cutaneous allodynia, hyperesthesia, GLP-1 receptors, GIP receptors, glucagon receptors, dorsal root ganglion, DRG gain, mast cell stabilization, magnesium for nerves, electrolyte balance, integrative chiropractic, functional medicine, internal medicine oversight, El Paso Injury Medical Clinic, Dr. Maria Guadalupe Cardenas MD, Dr. Alex Jimenez DC, small fiber neuropathy, alpha-lipoic acid, benfotiamine, low histamine diet, graded exposure therapy, parasympathetic tone, autonomic balance, neuroimmune axis

Calcific Tendinopathy Relief: Innovative Barbotage Procedure

Calcific Tendinopathy Relief: Innovative Barbotage Procedure

Calcific Tendinopathy Relief with Ultrasound-Guided Barbotage

Hello, I’m Dr. Alex Jimenez, and I am honored to present this educational insight into an advanced, ultrasound-guided procedure for treating calcific tendinopathy, a condition that can cause significant shoulder pain and dysfunction. At Injury Medical Clinic, our multidisciplinary team integrates cutting-edge, evidence-based treatments to provide comprehensive, personalized care. Today, we will explore barbotage, a minimally invasive procedure that aligns with our philosophy of combining targeted medical interventions with rehabilitative and chiropractic care to restore function and improve quality of life.

Our clinic operates on a collaborative model that brings together diverse expertise for our patients’ benefit. I work alongside Dr. Maria Guadalupe Cardenas, MD, a highly experienced, board-certified internist who serves as our Medical Director and Collaborative Physician. With over 40 years in internal medicine, Dr. Cardenas provides invaluable medical oversight, ensuring that our integrative protocols are safe, effective, and grounded in sound medical principles. This partnership allows us to offer a seamless blend of chiropractic care, functional medicine, rehabilitation, and targeted medical procedures under one roof, creating a powerful synergy for healing, especially for complex cases like chronic pain and personal injuries.

Calcific Tendinopathy Relief: Innovative Barbotage Procedure

Abstract: Understanding and Treating Calcific Tendinopathy

This post will guide you through the complexities of calcific tendinopathy, a painful condition characterized by calcium deposits within a tendon, most commonly affecting the rotator cuff of the shoulder. We will explore ultrasound-guided barbotage, a sophisticated procedure designed to break down and remove these deposits. I will explain the physiological basis of this condition, detail the single-needle and double-needle barbotage techniques, and showcase a real-time video demonstration of the procedure. I will also connect this medical intervention to our integrative care model, explaining how chiropractic care and functional medicine support the body’s recovery process post-procedure and address both the structural and systemic factors contributing to inflammation and dysfunction. This comprehensive approach ensures we not only alleviate the immediate symptom but also promote long-term healing and resilience.

What is Calcific Tendinopathy? A Deeper Look

Calcific tendinopathy is a condition where deposits of calcium hydroxyapatite form within tendons. While it can occur in various parts of the body, such as the patellar tendon or the gluteus medius tendon, it is most frequently diagnosed in the supraspinatus tendon of the rotator cuff. These calcium deposits can trigger a significant inflammatory response, leading to intense pain, restricted range of motion, and impaired shoulder function.

The image to the right shows a clear example. You can see the layers of tissue: the skin, subcutaneous fat, the overlying deltoid muscle, and the supraspinatus tendon. Within the tendon, a bright white calcium deposit is clearly visible. Notice the dark “shadow” beneath it—this is known as acoustic shadowing, a key diagnostic marker in ultrasound imaging. The dense calcium deposit blocks the ultrasound waves from passing through, creating this shadow and confirming its presence. The pain associated with this condition can be debilitating, often disrupting sleep and daily activities.

Barbotage: A Targeted Solution for Pain Relief

To address the pain from calcific tendinopathy, we utilize a specialized, ultrasound-guided procedure called barbotage. The term “barbotage” comes from a French word meaning “to splash” or “to stir up,” which aptly describes the technique. It involves repeatedly injecting a solution (typically saline) and aspirating the softened calcium deposit. This method is a highly effective, minimally invasive alternative to surgery for many patients.

The primary goal of barbotage is to physically break down and wash out calcium deposits, relieving pressure and inflammation within the tendon. By using real-time ultrasound guidance, we can precisely target the deposit, ensuring the needle is placed accurately for maximum effectiveness while avoiding damage to surrounding healthy tissue.

The Barbotage Technique: Single vs. Double Needle

There are two primary methods for performing barbotage: a two-needle technique and a single-needle technique. While I will be showcasing a video of the single-needle approach, it’s important to understand both.

  • Two-Needle Technique:
    • Insert the first needle into the lower part of the calcium deposit, with the bevel (the angled tip) facing the ultrasound probe.
    • A second needle is then inserted parallel to and just above the first, but with its bevel facing the opposite direction.
    • This setup creates a “washing circuit.” Saline, often warmed to improve its ability to dissolve calcium, is injected through one needle.
    • The gentle pressure from the saline helps break down the deposit, and the resulting chalky, fluid-like calcium can then exit through the second needle into an empty syringe. This process is repeated until no more calcium can be aspirated.
  • Single-Needle Technique:
    • A single, larger-gauge needle is inserted directly into the calcium deposit.
    • Saline is repeatedly injected and aspirated through the same needle. The practitioner injects fluid to build pressure and break up the deposit, then pulls back on the plunger to aspirate the softened calcium slurry.
    • This method is often combined with fenestration, which involves using the needle tip to repeatedly puncture and mechanically break up the deposit.

The consistency of the deposit influences the outcome. Soft, paste-like calcifications are more likely to be aspirated, giving the satisfying visual of the milky fluid filling the syringe. Hard, rock-like deposits may not aspirate easily. In these cases, the primary therapeutic action comes from fenestration, which breaks the deposit into smaller fragments. This mechanical disruption, combined with the inflammatory response it triggers, stimulates the body’s own cells (macrophages) to clear away the debris over the following weeks.

A Step-by-Step Walkthrough of the Barbotage Procedure

Dr. Nate Nye expertly demonstrates the single-needle technique. Let’s walk through the process.

1. Preparation and Anesthesia

First, proper sterile technique is paramount. The patient’s shoulder is prepped with chlorhexidine, and the ultrasound probe is covered with a sterile sleeve. The patient is positioned to optimally expose the supraspinatus tendon.

Dr. Nye begins by anesthetizing the area. Using a small-gauge needle, he injects lidocaine (a local anesthetic) along the planned needle path, from the skin down to the surface of the tendon and into the subacromial bursa, the fluid-filled sac that sits above the rotator cuff. This ensures the patient’s comfort throughout the procedure.

2. Identifying the Target with Ultrasound

Using the linear ultrasound probe, he visualizes the anatomy in real-time. He identifies the deltoid muscle, the rotator cuff tendon, and the bright, hyperechoic calcium deposit with its characteristic acoustic shadowing. Precise alignment of the needle with the ultrasound probe is critical for maintaining an in-plane view, where the entire length of the needle is visible on the screen.

3. Fenestration and Lavage (Washing)

Next, a larger needle is introduced through the anesthetized tract. Dr. Nye carefully guides the needle directly into the calcium deposit. You can see the needle tip making contact and beginning the fenestration process—methodically puncturing the deposit from multiple angles.

As he fenestrates, he also injects normal saline. This does two things:

  • The hydraulic pressure helps to fracture the deposit.
  • It creates a fluid medium to “wash” the area and potentially suspend calcium particles for aspiration.

During the procedure, he skillfully manipulates the probe, viewing the deposit in both long-axis (along the length of the tendon fibers) and short-axis (a cross-section). This provides a three-dimensional understanding of the deposit’s size and shape, ensuring no part of it is missed.

4. Observing the Changes in Real-Time

As the procedure progresses, we can observe fascinating changes on the ultrasound screen. The once-solid, bright white deposit begins to lose its distinct borders. More importantly, the prominent acoustic shadowing starts to diminish. This is a crucial sign of success—as the calcium breaks up, the ultrasound beam can penetrate deeper into the tissue below, indicating that the dense blockage is being resolved.

5. Post-Procedure Corticosteroid Injection

After the barbotage is complete (which can take 5-10 minutes of meticulous work), a final step is often taken to manage post-procedural inflammation. Fenestration can trigger a temporary inflammatory flare-up. To mitigate this response, a small amount of corticosteroid (like Kenalog) mixed with lidocaine is injected into the subacromial bursa. This helps to control pain and inflammation in the days following the procedure, allowing the body’s natural healing process to take over more comfortably.

The Role of Integrative Chiropractic Care in Recovery

At our clinic, treatment doesn’t end when the procedure is over. This is where our integrative model truly shines. The barbotage procedure addresses the direct physical blockage, but comprehensive recovery requires addressing the biomechanical and physiological factors that may have contributed to the problem.

This is where my role as a chiropractor and functional medicine practitioner becomes essential. Here’s how we support recovery:

  • Restoring Biomechanics: Following the procedure, the shoulder joint and surrounding structures need to be retrained to function correctly. As a Doctor of Chiropractic, I focus on the biomechanics of the entire shoulder girdle, cervical spine, and thoracic spine. Misalignments or dysfunctional movement patterns in these areas can place undue stress on the rotator cuff, potentially contributing to the initial tendinopathy. Through gentle, specific chiropractic adjustments and mobilizations, we can:
    • Improve scapulohumeral rhythm (the coordinated movement of the shoulder blade and arm).
    • Restore proper joint mobility in the shoulder, clavicle, and spine.
    • Release tension in compensatory muscles that have become tight and overworked.
  • Functional Rehabilitation: We design a personalized rehabilitation program that begins with gentle range-of-motion exercises and progresses to strengthening the rotator cuff and scapular stabilizing muscles. The goal is to build a strong, stable, and resilient shoulder that is less susceptible to future injury.
  • Functional Medicine and Inflammation Control: Calcific tendinopathy is fundamentally an inflammatory condition. As a Certified Functional Medicine Practitioner, I look beyond the localized symptoms to understand the systemic drivers of inflammation in the body. We may use advanced testing to assess nutritional status, gut health, and inflammatory markers. Based on these findings, we create a personalized plan that may include:
    • Anti-inflammatory nutritional protocols to reduce systemic inflammation.
    • Targeted supplementation with nutrients like omega-3 fatty acids, vitamin C, and magnesium, which are crucial for tendon health and tissue repair.
    • Lifestyle recommendations to manage stress and improve sleep, both of which are critical for an optimal healing response.

This comprehensive approach, overseen by our medical director, Dr. Cardenas, ensures that we are not just chasing symptoms. We are addressing the root causes of dysfunction from multiple angles—medical, mechanical, and metabolic. By combining an advanced procedure like barbotage with foundational chiropractic and functional medicine care, we guide our patients on a complete journey from pain and limitation to restored function and lasting wellness.

Conclusion

Ultrasound-guided barbotage represents a significant advancement in treating calcific tendinopathy, offering a precise, minimally invasive, and highly effective way to relieve pain. However, true healing is rarely achieved with a single intervention. Our experience at Injury Medical Clinic demonstrates the profound value of an integrative, multidisciplinary approach. By blending the targeted precision of procedures like barbotage with the holistic, function-focused principles of chiropractic care and functional medicine, we can provide a more robust and sustainable path to recovery for our patients.

Is Motion Key to Healing? | El Paso, Tx (2023)

References

This post draws upon the principles and techniques discussed by leading researchers and clinicians in the field, including the work presented by Dr. Fran O’Connor, who describes these advanced techniques in detail.

  • O’Connor, F. (n.d.). Calcific Tendinopathy and Barbotage. [Educational Presentation]. The insights and video demonstration provided by Dr. Nate Nye are also gratefully acknowledged for their clarity and educational value.
  • McMahon, P. J. (Ed.). (2018). Current Diagnosis and Treatment in Orthopedics (6th ed.). McGraw-Hill Education. This textbook series provides comprehensive information on orthopedic conditions and treatments, including tendinopathies.
  • Jimenez, A. (2024). Clinical Observations in Chiropractic and Functional Medicine. Sciatica.clinic. Retrieved from https://sciatica.clinic/
  • Jimenez, A. (2024). Professional Profile and Clinical Focus. LinkedIn. Retrieved from https://www.linkedin.com/in/dralexjimenez/

Autoimmunity and Health Benefits With Integrative Chiropractic

Discover how integrative chiropractic methods target autoimmunity and play a role in minimizing systemic inflammation.

Abstract

In this educational post, I, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, explore a timely clinical question at the intersection of dermatology, immunology, and integrative care: when and how can chronic rosacea reflect systemic immune dysregulation, and what can we do to prevent progression to autoimmune disease? Drawing from modern, evidence-based research methods and the latest peer-reviewed findings, I unpack the physiology of skin barrier failure, vascular dynamics, innate and adaptive immune signaling, type I interferon activation, matrix metalloproteinase (MMP) activity, Demodex-associated inflammation, micronutrient dependencies (with an emphasis on riboflavin, vitamin B2), gastric acid physiology, small intestinal ecology, pancreatic enzyme sufficiency, and the spleen’s role as a dynamic immunologic filter.

I also detail how our multidisciplinary team at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas works: I provide integrative chiropractic and functional medicine care while our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), delivers medical oversight, internal medicine evaluation, and inter-specialty coordination. Together, we integrate chiropractic care with diagnostic medicine, functional nutrition, gut-immune restoration, personal injury care, rehabilitation, and longitudinal monitoring to detect early immune shifts and intervene before organ damage occurs.

Finally, I outline a practical, stepwise protocol—anchored to safety, physician oversight, and confirmed diagnostics—to close common gaps between dermatology and rheumatology, while emphasizing the role of integrative chiropractic care in neuromusculoskeletal, autonomic, lymphatic, and rehabilitative domains. Throughout, I cite leading research in dermatology, immunology, and gastroenterology to ground each step in evidence, and I highlight clinical observations from my practice and writings.

My Clinical Lens On Rosacea And Systemic Immunity

I have spent years seeing patients present with “just a red face” and leave with a plan that changes the trajectory of their health. When I examine rosacea through a systems lens, I see a dynamic interface: the skin as sentinel, the gut as gatekeeper, the spleen as filter, and the vascular-immune axis as amplifier. Modern research clarifies that rosacea is not simply “cosmetic.” It is an immunologically active state marked by barrier dysfunction, neurovascular reactivity, dysbiosis (including Demodex overgrowth), and cytokine signaling that can echo patterns seen in systemic autoimmunity.

I present this post to show how we can listen to biology’s early warning signs—and respond with evidence-based, integrative strategies that calm immune overdrive, restore barriers, and protect organs.

Our Team-Based Model In El Paso: Integrative Chiropractic Care With Internal Medicine Oversight

  • Maria Guadalupe Cardenas, MD (Board Certified, Internal Medicine; NPI #1164426749; Texas MD License #J2933) serves as Medical Director and Collaborative Physician at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic).
  • I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, lead integrative chiropractic care and functional medicine services, bridging neuromusculoskeletal rehabilitation with systemic, lifestyle-driven interventions.
  • Our clinic structure reflects an integrative, multidisciplinary model common in injury and functional care settings. Dr. Cardenas provides diagnostic evaluation, risk stratification, medical management, and specialty referral. I coordinate chiropractic, rehabilitative exercises, biomechanical corrections, autonomic balancing strategies, lifestyle and nutrition support, and functional testing where appropriate.

  • Together, we apply a shared-care approach: medical safety and oversight combined with hands-on, systems-oriented chiropractic care, rehabilitation, and functional therapeutics.

This structure allows us to catch trends early—especially in conditions like rosacea, where skin and vascular signs may foreshadow systemic immune activation.

Rosacea As A Systems Signal: What The Skin Is Telling Us

  • The skin’s primary mandate is clear: keep “bad” out and “good” in. It accomplishes this through:
    • Tight junctions and adherens junctions that maintain barrier integrity.
    • Lipid bilayers (ceramides, cholesterol, free fatty acids) that create water-impermeable layers.
    • Antimicrobial peptides (AMPs) such as cathelicidin (LL-37) and beta-defensins that patrol the interface.

    • Resident immune surveillance via Langerhans cells, dermal dendritic cells, macrophages, mast cells, and T cells.
  • In rosacea, the barrier weakens, blood vessels dilate chronically, and innate immunity becomes hyper-reactive. This convergence increases trans-epidermal water loss, raises skin pH, disrupts microbiome balance, and heightens sensitivity to environmental triggers (UV, heat, spicy foods, alcohol, and microbial antigens) (Linares-Gonzalez et al., 2024).

When barrier integrity falters, the immune system compensates by elevating inflammatory pathways and vascular responses. Over time, those signals can propagate beyond the skin.

The Vascular-Immune Loop: Why Persistent Flushing Matters

Rosacea is characterized by:

  • Chronic vasodilation due to neurovascular dysregulation and TRP channel activation.
  • Increased vascular permeability, allowing plasma proteins and fluid to leak into interstitial tissues, contributing to papules and pustules.
  • Endothelial activation, which recruits leukocytes to the skin and elevates inflammatory mediators including IL-8, TNF-α, IL-1β, and MMPs (Two et al., 2015; Woo et al., 2020).

This vascular-immune loop can become self-perpetuating: each flare primes the next. If systemic signals such as type I interferons rise and stay elevated, they can reshape adaptive immunity in ways that resemble autoimmune patterning.

Matrix Metalloproteinases: Collagen And Elastin Under Stress

  • Rosacea is associated with increased matrix metalloproteinases (MMPs)—especially MMP-1 and MMP-9—which degrade collagen and elastin in the dermal matrix (Woo et al., 2020).
  • Elevated MMPs contribute to telangiectasia, tissue laxity, and persistent inflammation by releasing matrix fragments that further stimulate immune pathways.

In clinical practice, I consider MMP activity a signpost of connective tissue stress. It prompts me to examine micronutrient status (zinc, copper balance), redox tone, sleep quality, thermal triggers, and ultraviolet exposure—all of which influence MMP expression.

Type I Interferons: The Immune System’s Emergency Broadcast

  • Type I interferons (IFN-α, IFN-β) coordinate antiviral defense and intensify antigen presentation. Persistently high signaling is characteristic of systemic autoimmunity such as SLE (Psarras et al., 2020; Rönnblom & Leonard, 2019).
  • Rosacea cohorts show innate immune activation, dysregulated AMPs (e.g., LL-37), and vascular changes. Some research highlights overlaps in interferon pathway signaling across inflammatory dermatoses and systemic autoimmunity, warranting vigilance in persistent or severe cases (Woo et al., 2020; Two et al., 2015).

Clinical translation:

  • I do not equate rosacea to lupus. They are distinct diagnoses with different criteria and prognoses.
  • However, if patients exhibit severe, treatment-resistant rosacea with systemic symptoms (fatigue, arthralgia, photosensitivity, rashes beyond the malar area, mucosal ulcers), I coordinate with Dr. Cardenas to evaluate for systemic inflammation and, when indicated, order targeted labs and rheumatology referrals.

Demodex, Innate Immunity, And The Riboflavin Connection

  • Demodex mites are commensals in humans. In rosacea, they may be more numerous or immunostimulatory, with mite-associated bacteria contributing to inflammation (Forton & De Maertelaer, 2017; Lazaridou et al., 2011).
  • The immune system attempts to control Demodex through neutrophil and macrophage activity. That effort relies on the respiratory burst—generation of reactive oxygen species (ROS) powered by NADPH oxidase.
  • Riboflavin (vitamin B2) is a precursor for FAD and FMN, cofactors in redox enzymes, including components relevant to ROS generation. Inadequate riboflavin may limit optimal immune oxidative killing capacity while permitting persistent, smoldering inflammation (Powers, 2003; Rucker et al., 2012).

Practical considerations:

  • I screen diet quality, alcohol intake, malabsorption risks, and medication interactions that might reduce riboflavin status.
  • In cases with signs of deficiency or high need, we consider riboflavin repletion alongside broader nutrient repletion under Dr. Cardenas’ medical oversight.

Gastric Acid Physiology: The First Antimicrobial Checkpoint

  • Adequate gastric hydrochloric acid (HCl) supports:
    • Protein denaturation and activation of pepsin.
    • Inactivation of ingested pathogens.
    • Triggering of pancreatic enzyme secretion and gallbladder contraction via secretin and cholecystokinin pathways.
  • Low stomach acid (hypochlorhydria) increases risk for microbial survival through the stomach, potentially promoting small intestinal bacterial overgrowth (SIBO) and dysbiosis (Duggan et al., 2023; Rezaie et al., 2017).

Why this matters in rosacea:

  • Multiple studies report associations between rosacea and SIBO, with some patients experiencing symptom relief after SIBO treatment (Weinstock & Steinhoff, 2013; Parodi et al., 2008).
  • Clinically, when I see refractory rosacea with bloating, postprandial fullness, or altered bowel habits, I coordinate gut evaluation with Dr. Cardenas and consider a SIBO workup.

Pancreatic Enzymes, Fat Digestion, And Immune Crosstalk

  • Suboptimal pancreatic enzyme output and bile flow can leave fats and proteins incompletely digested, providing substrates for microbial fermentation in the small intestine.
  • Fermentation byproducts can disrupt tight junctions, fueling a leaky-gut cycle that elevates systemic LPS and inflammatory cytokines (Bischoff et al., 2014; Camilleri, 2019).

Intervention rationale:

  • Restoring digestion reduces antigenic load, normalizes nutrient absorption, and lowers immune provocation.
  • Under medical oversight, we may support gastric acid, pancreatic enzymes, and bile flow as clinically indicated, always aligning with safety and diagnostics.

The Spleen: The Blood’s Immune Control Tower

  • The spleen screens blood approximately every 8–10 minutes, clearing senescent cells, opsonized microbes, and immune complexes.
  • In chronic immune activation, the spleen’s macrophages and dendritic cells can sustain type I interferon and cytokine signals, influencing B-cell activity and autoantibody production in susceptible individuals (Bronte & Pittet, 2013; Swirski & Nahrendorf, 2013).

Clinical implication:

  • Persistent systemic immune activation—reflected in CRP, ESR, interferon-stimulated gene signatures, or autoantibody panels—warrants careful evaluation. This is where Dr. Cardenas’ internal medicine guidance is essential, ensuring appropriate imaging, labs, and cross-specialty collaboration.

Why Integrative Chiropractic Care Belongs In This Conversation

Integrative chiropractic care is not limited to spinal adjustments. In our clinic, it encompasses:

  • Biomechanical optimization to reduce nociceptive drive and sympathetic overactivation.
  • Autonomic balancing via targeted manual therapies, breathing training, and graded movement to dampen neurogenic inflammation and vasodilatory flares.
  • Lymphatic and fascial techniques that can support tissue fluid dynamics and reduce edema.
  • Exercise rehabilitation to improve microvascular function, insulin sensitivity, mitochondrial efficiency, and antioxidant capacity.
  • Lifestyle and nutrition coaching that complements medical care and functional plans.

By relieving musculoskeletal stress, refining posture and breathing mechanics, and optimizing recovery, we help recalibrate autonomic tone and inflammatory set points. This complements Dr. Cardenas’ medical oversight and any dermatology/rheumatology care.

For deeper context on my clinical approach, see my observations and educational material:

The Research Landscape: Key Threads That Guide Clinical Decision-Making

  • Rosacea pathophysiology includes dysregulated innate immunity, neurovascular instability, and altered AMP processing (Two et al., 2015; Woo et al., 2020).
  • Type I interferon signatures are central in SLE and other autoimmune conditions; sustained interferon activity can shape adaptive responses (Rönnblom & Leonard, 2019; Psarras et al., 2020).
  • Rosacea-gut axis: SIBO and dyspepsia are enriched in rosacea cohorts; treating gut dysbiosis can attenuate cutaneous symptoms in subgroups (Weinstock & Steinhoff, 2013; Parodi et al., 2008; Holmes et al., 2018).
  • Demodex-associated inflammation correlates with severity in some patients; addressing cutaneous microbiome and barrier integrity is critical (Forton & De Maertelaer, 2017; Lazaridou et al., 2011).
  • MMP upregulation contributes to dermal matrix degradation and persistent inflammation (Woo et al., 2020).

I translate these threads into an actionable, stepwise evaluation and care plan under shared medical-chiropractic oversight.

Fighting Inflammation Naturally- Video

Fighting Inflammation Naturally | El Paso, Tx (2023)

A Practical, Stepwise Evaluation Strategy Under Medical-Chiropractic Collaboration

Step 1: Thorough History And Risk Stratification

  • Dermatologic features: subtype (erythematotelangiectatic, papulopustular, phymatous, ocular), triggers, severity, treatment history, photosensitivity.
  • Systemic clues: fatigue, arthralgia, mucosal ulcers, Raynaud phenomena, serositis symptoms, fevers, weight changes.
  • GI signals: reflux, bloating, postprandial fullness, altered bowel habits, food intolerances.
  • Nutritional and medication review: alcohol, PPIs/H2 blockers, metformin, isotretinoin history, antibiotics, supplements.
  • Autonomic and stress load: sleep, HRV surrogates (subjective), anxiety, heat intolerance.
  • Environmental: heat/UV exposure, occupation, climate, skincare products.

Step 2: Physical Exam

  • Dermatologic mapping, vascular reactivity, edema, telangiectasias.
  • Ocular assessment (dryness, blepharitis signs) and referral as needed.
  • Joint and connective tissue screen; oral/nasal mucosa exam.
  • Musculoskeletal posture, cervical mechanics, TMJ involvement, breathing pattern evaluation.

Step 3: Laboratory And Diagnostic Pathways (Tailored)

  • Baseline inflammation: hs-CRP, ESR.
  • Metabolic terrain: CBC, CMP, fasting insulin, lipid profile, HbA1c, ferritin, vitamin D.
  • Autoimmune screening (if clinically indicated): ANA with reflex panel, complement (C3/C4), ENA, dsDNA, urinalysis with microscopy for protein/hematuria.
  • Infectious and barrier-related: nasal/skin staph carriage in recurrent infections; stool tests in select cases.
  • Nutrient status: B2 (clinical assessment; plasma riboflavin is imperfect but can assist), B6, B12, folate, zinc, copper, selenium.
  • Gut evaluations: SIBO breath test (lactulose/glucose) when symptoms support; celiac serology if indicated.
  • Dermatology tools: dermoscopy; consider Demodex scraping in select cases.

Coordinate all diagnostics with Dr. Cardenas to ensure safety, relevance, and appropriate interpretation.

Step 4: Early Actions While Awaiting Results

  • Trigger mitigation: UV/heat, alcohol, capsaicin, hot beverages, and irritant skincare.
  • Skin barrier-first routine: gentle, non-alkaline cleansers; ceramide-rich emollients; niacinamide-containing formulations; mineral sunscreen.
  • Sleep and stress countermeasures: consistent schedule, wind-down routines, paced nasal breathing.
  • Nutrition foundations: anti-inflammatory dietary pattern emphasizing polyphenols, omega-3s, lean proteins, and low-glycemic plants; hydration; moderated alcohol.
  • Integrative chiropractic start: manual therapy to reduce cervical/thoracic tension, diaphragmatic training, lymphatic drainage techniques as appropriate.

Step 5: Targeted Interventions Based On Findings

  • If gut dysbiosis/SIBO: evidence-based antimicrobials (e.g., rifaximin or herbal protocols per guidelines) under physician oversight; low-fermentation diet short term; prokinetics; repletion of digestive support if indicated (HCl/enzymes under safety guardrails).
  • If nutrient gaps: riboflavin repletion, zinc, vitamin D, omega-3s, and individualized micronutrients with monitoring.
  • If high inflammatory tone: omega-3 fatty acids, curcumin phytosomes, green tea catechins, quercetin—selected for safety and interactions, coordinated with Dr. Cardenas.
  • If ocular rosacea: ophthalmology referral, lid hygiene, targeted therapies.
  • If autoimmune signals: rheumatology referral, closer monitoring, organ-protective strategies as guided by internal medicine.

Step 6: Rehabilitation And Autonomic Regulation

  • Structured, progressive exercise tailored to tolerance.
  • Breathing retraining to improve CO2 tolerance and autonomic balance.
  • Cervical-thoracic mobility, scapulothoracic coordination, and postural strength programming to decrease sympathetically mediated flushing triggers.
  • Sleep optimization strategies; HRV-informed recovery adjustments when available.

Why Each Technique Or Idea Is Used

  • Skin barrier repair reduces antigen ingress and transepidermal water loss, lowering innate immune activation and vascular reactivity (Linares-Gonzalez et al., 2024).
  • UV/heat trigger control decreases neurovascular flare frequency, reducing cumulative endothelial activation and MMP induction.
  • Gut-directed therapy reduces LPS translocation and systemic cytokine load, calming type I interferon–sensitizing contexts (Rezaie et al., 2017; Holmes et al., 2018).
  • Riboflavin and micronutrient repletion support enzymatic systems, redox balance, and immune competence, promoting resolution instead of chronic smoldering inflammation (Powers, 2003; Rucker et al., 2012).
  • Integrative chiropractic care reduces nociceptive stress and sympathetic arousal, improves lymphatic flow, and supports recovery physiology—shifting the inflammatory set point favorably.
  • Exercise and breathing retraining enhance endothelial function and vagal tone, dampening excessive vasodilatory cascades and stabilizing microcirculation.

Cases And Clinical Observations: Patterns I Watch For

From my clinical observations and published commentaries:

  • Patients with refractory facial flushing often show cervical and upper thoracic myofascial tension, mouth breathing, and low diaphragmatic engagement. Addressing biomechanics and breathing lowers flare frequency.
  • Those with prominent bloating, variable stools, and postprandial fatigue frequently benefit from SIBO evaluation; when treated appropriately, facial reactivity and pustules can soften.
  • Night-shift workers and those with irregular sleep schedules often need circadian repair to stabilize vascular tone and inflammatory rhythms.
  • In select cases, simple changes—mineral sunscreen, niacinamide moisturizers, and withdrawing irritant products—can significantly reduce daily flare burden.

For more of my clinical insights:

Safety Notes And Collaborative Guardrails

  • Persistent photosensitivity, malar rash beyond usual rosacea distribution, oral/nasal ulcers, serositis symptoms, hematuria/proteinuria, unexplained fevers, or systemic constitutional symptoms should prompt immediate medical evaluation. Dr. Cardenas leads this triage pathway.
  • The medical team coordinates and prescribes any pharmacologic therapy, including antibiotics for SIBO or systemic dermatologic medications.
  • Supplements can interact with medications; physicians reconcile all protocols.

Putting It Together: An Integrative Checklist

  • Assess skin barrier, vascular triggers, and routine skincare.
  • Screen for GI dysfunction when symptoms suggest—and treat if confirmed.
  • Evaluate nutrient status with a focus on riboflavin, zinc, vitamin D, and omega-3s.
  • Track inflammation, consider autoimmune screening when clinically indicated.
  • Employ integrative chiropractic care for autonomic balance, lymphatic support, and rehabilitation.
  • Coordinate across dermatology, internal medicine, gastroenterology, and rheumatology as appropriate.

Educational Takeaways

  • Rosacea is a skin-immune-vascular condition with systemic echoes. Listening early matters.
  • Type I interferon biology is relevant when inflammation persists, or systemic features emerge, but rosacea and lupus remain distinct conditions requiring distinct diagnostic criteria.
  • The gut-skin axis, micronutrient sufficiency, and autonomic balance are leverage points.
  • An integrative, multidisciplinary model—chiropractic plus internal medicine oversight—can detect and address risks sooner.

Our Clinic’s Commitment

At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933) and I collaborate on patient-centered, evidence-informed care. We connect dots between symptoms, systems, and science, aiming to reduce inflammatory burden, restore function, and protect long-term health.

If you are experiencing persistent rosacea or related systemic symptoms, our team can provide a comprehensive, integrated evaluation and care plan tailored to your needs.

References

SEO tags: rosacea, type I interferon, lupus, SLE, Demodex, riboflavin, vitamin B2, NADPH oxidase, small intestinal bacterial overgrowth, SIBO, leaky gut, gastric acid, pancreatic enzymes, MMPs, LL-37, cathelicidin, neurovascular dysregulation, integrative chiropractic, functional medicine, dermatology, internal medicine, spleen immunity, autonomic balance, lymphatic drainage, El Paso, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, Dr. Maria Guadalupe Cardenas MD, Dr. Alex Jimenez

Advanced Pain Management With Battlefield Acupuncture Protocol

Advanced Pain Management With Battlefield Acupuncture Protocol
Patient learning about ear points in auriculotherapy treatment.

Advanced Pain Management With Battlefield Acupuncture

Abstract

As a clinician dedicated to integrative and functional medicine, I am continually exploring evidence-based, minimally invasive therapies to alleviate pain and restore function for my patients. This post explores the innovative technique of Battlefield Acupuncture (BFA), a powerful auriculotherapy protocol developed for rapid, effective pain relief. We will explore the physiological basis of BFA, its specific application points, and the procedure itself. I will also share insights from my clinical practice at Injury Medical Clinic, showcasing how we integrate advanced techniques like BFA into our comprehensive care model. This model combines my expertise as a Doctor of Chiropractic and Advanced Practice Registered Nurse with the medical oversight of our esteemed Medical Director, Dr. Maria Guadalupe Cardenas, MD, an internist with over 40 years of experience. Together, we provide a multidisciplinary approach that merges chiropractic care, functional medicine, and traditional medical practices to achieve superior patient outcomes.

Advanced Pain Management With Battlefield Acupuncture Protocol


Hello, I’m Dr. Alex Jimenez. With a background spanning chiropractic, advanced practice nursing, and functional medicine, my mission is to bring the latest, most effective treatments to our patients in El Paso, Texas. Today, I want to share a fascinating, highly effective technique we use to manage acute and chronic pain: Battlefield Acupuncture (BFA). This isn’t just a traditional acupuncture method; it’s a specific, evidence-based protocol that has shown remarkable results, from the front lines of military medicine to our clinical setting.

Our Integrated Approach to Patient Care

At Injury Medical Clinic, we believe in a team-based, patient-centered approach. As a Doctor of Chiropractic (DC) and a board-certified Family Nurse Practitioner (APRN, FNP-BC), I can view health through multiple lenses. To ensure the highest standard of care, our practice operates under the medical direction of Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a board-certified internist (NPI #1164426749, Texas MD License #J2933) with more than four decades of experience. As our collaborative physician, she provides essential medical oversight to ensure our protocols are safe, effective, and well integrated.

This multidisciplinary setup is the cornerstone of modern integrative healthcare. It allows us to seamlessly blend:

  • Chiropractic Adjustments: To restore spinal alignment, improve nervous system function, and alleviate musculoskeletal pain.
  • Medical Oversight: Under Dr. Cardenas, ensuring comprehensive diagnosis and management of underlying health conditions.
  • Functional Medicine: To identify and address the root causes of disease through nutrition, lifestyle, and targeted supplementation.
  • Advanced Pain Therapies: Including cutting-edge techniques like Battlefield Acupuncture.
  • Rehabilitation and Personal Injury Care: To restore function and support recovery after an injury.

This collaborative model ensures that when we introduce a therapy like BFA, it is part of a holistic treatment plan supervised by both chiropractic and medical professionals.

Understanding Battlefield Acupuncture (BFA)

Battlefield Acupuncture is a specialized form of auriculotherapy, which is acupuncture performed on the external ear. Dr. Richard Niemtzow, a retired Air Force colonel and physician, developed it to provide rapid, potent pain relief in settings where traditional pain medications might be impractical or cause undesirable side effects—such as on the battlefield. However, its applications have expanded significantly and are now used in emergency rooms, post-operative recovery, and integrative pain clinics like ours.

The technique involves inserting minimal, semi-permanent needles, called ASP needles (Aiguille Semi-Permanente), into specific points on the ear. These needles are tiny, dart-like studs that are designed to stay in place for several days, providing continuous stimulation to the targeted points.

The Neurological Basis of BFA: How It Works

The ear is a fascinating microsystem that reflects the entire body. It is richly innervated by several major nerves, including branches of the vagus nerve, the trigeminal nerve, and cervical spinal nerves. When an ASP needle is inserted into a BFA point, it sends a powerful signal directly to the central nervous system—specifically to key pain-processing centers in the brain.

The five points used in the BFA protocol are strategically chosen to modulate the brain’s perception of pain. These points are thought to directly influence areas like the thalamus, the cingulate gyrus, and other regions involved in processing and filtering sensory information.

  • Cingulate Gyrus Point: This point is associated with the part of the brain that processes the emotional component of pain. By stimulating this point, we can help “un-link” the physical sensation of pain from the emotional suffering it often causes. This is crucial for chronic pain patients, where the emotional burden can be as debilitating as the physical sensation.
  • Thalamus Point: The thalamus acts as the brain’s primary relay station for sensory signals, including pain. Stimulating this point is believed to “gate” or block pain signals from reaching the cerebral cortex, where they would be consciously perceived. It effectively turns down the volume on pain.
  • Other Points (Point Zero, Shen Men, Omega 2): These points further support the central nervous system’s regulation. Shen Men, or “Spirit Gate,” is a master point for calming the mind and reducing stress and anxiety. Point Zero helps bring the entire body into homeostatic balance. Omega 2 is associated with musculoskeletal function.

By stimulating these points in a specific sequence, BFA aims to reset the central nervous system’s processing of pain, leading to significant, often immediate, relief.

The Battlefield Acupuncture Protocol: A Step-by-Step Guide

The BFA protocol is systematic and designed for clear decision-making. The process is straightforward, but precision is key.

The Five Key BFA Points

The protocol involves up to five specific points, typically addressed in a particular order:

  1. Cingulate Gyrus
  2. Thalamus
  3. Point Zero
  4. Shen Men
  5. Omega 2

The Procedure in Practice

Here is a look at how a typical BFA session unfolds in our clinic:

  1. Patient Assessment: We start by assessing the patient’s pain on a scale of 0-10. We also determine if the pain is localized to one side of the body (lateralized) or generalized.
  2. Ear Selection: If the pain is not lateralized, we typically begin with the ear on the patient’s non-dominant side. For example, for a right-handed person, we would start with the left ear. If pain is on one side of the body, we often start on the contralateral (opposite) ear.
  3. Site Preparation: Clean the ear thoroughly with an alcohol swab to ensure a sterile field. While some practitioners may not use gloves, I believe it is prudent to wear them to maintain the highest standards of hygiene.
  4. Needle Insertion: Using a three-finger technique for stability and precision, the first ASP needle is inserted into the Cingulate Gyrus point. The needle is housed in a small plastic inserter. With firm, direct pressure, the needle is deployed with a distinct “click.” Patients tolerate the process quickly and surprisingly well.
  5. Reassessment and Ambulation: This is a critical step. After inserting the first needle, we ask the patient to get up and walk around for a few minutes. We then reassess their pain level.
    • If the pain is significantly reduced (e.g., drops by 50% or more), we may decide to stop there. The goal is to use the minimum number of needles needed to achieve maximum effect.
    • If the pain is not sufficiently relieved, we proceed to the next point in the sequence, the Thalamus point, in the same ear. We repeat the process of insertion, ambulation, and reassessment.
  6. Progressing the Protocol: We continue this process through the five points on the first ear. If the patient has not achieved adequate pain relief after all five needles have been placed in the first ear, we then move to the other ear and repeat the entire sequence.

Clinical Observations

From my clinical experience, I’ve found that many patients achieve substantial relief with just the first one or two needles—most commonly the Cingulate Gyrus and Thalamus points. A patient I have treated for some time for chronic pain responds exceptionally well to bilateral needle insertions in just these two points. We perform this treatment for her every two to three weeks, and it provides consistent, lasting relief, allowing her to function with significantly less pain.

The ASP needles are designed to stay in place for approximately three to seven days. They often fall out on their own as the body naturally exfoliates skin cells. This provides a continuous, low-level stimulation that prolongs the pain-relieving effects of the treatment.

Integrating BFA with Chiropractic and Functional Medicine

Battlefield Acupuncture is a powerful tool, but its true potential is unlocked when it is part of a comprehensive, integrative treatment plan.

  • With Chiropractic Care: For a patient with sciatica, for example, I might perform a chiropractic adjustment to decompress the lumbar spine and relieve direct pressure on the sciatic nerve. I would then use BFA to immediately down-regulate the intense nerve pain signals being sent to the brain. The adjustment addresses the structural cause, while the BFA manages the acute neurological symptoms. This dual approach accelerates recovery and dramatically improves patient comfort.
  • With Functional Medicine: Chronic pain is almost always linked to chronic inflammation. As a certified functional medicine practitioner, I investigate the root causes of this inflammation—be it a pro-inflammatory diet, gut dysbiosis, or nutrient deficiencies. While BFA provides rapid symptom relief, a functional medicine plan involving dietary changes, anti-inflammatory supplements like curcumin and omega-3s, and stress management techniques works to resolve the underlying physiological imbalance. This combination treats both the symptom and the source, leading to long-term wellness.

With Dr. Cardenas as our collaborative physician, we can also co-manage patients who may require prescription medications or have complex medical histories, ensuring our integrative therapies complement and enhance their overall medical care.

Conclusion

Battlefield Acupuncture represents a significant advancement in non-pharmacological pain management. It is a testament to how ancient principles, when refined with modern, evidence-based research, can offer profound healing. Its ability to provide rapid, effective, and lasting pain relief with minimal side effects makes it an invaluable tool in our integrative practice.

At Injury Medical Clinic, our unique collaborative structure, combining the expertise of chiropractic, functional medicine, and internal medicine under Dr. Cardenas’s direction, allows us to leverage powerful therapies like BFA to their fullest potential. We don’t just treat symptoms; we treat the whole person, creating a personalized journey toward pain-free living and optimal health.

If you are struggling with acute or chronic pain, I encourage you to explore how an integrated approach can make a difference.

Chronic Body Pain Recovery | El Paso, Tx

References

Thyroid Health and Functional Medicine Approach for Everyone

Learn how the functional medicine approach to thyroid health can transform your journey to optimal well-being.

Abstract

For many individuals struggling with symptoms of hypothyroidism, such as weight gain, fatigue, depression, and brain fog, the conventional approach often involves a lifetime of medication like Synthroid or levothyroxine. While these medications can be essential, they frequently fail to address the root causes of thyroid dysfunction. This educational post, written from my perspective as Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, explores the intricate physiology of thyroid hormone conversion and highlights four primary mechanisms that account for over 90% of thyroid problems—none of which originate within the thyroid gland itself. We will delve into the roles of systemic inflammation, liver congestion, gut dysbiosis, and HPA axis dysregulation (chronic stress) in disrupting the crucial conversion of inactive T4 to active T3. Drawing upon the latest evidence-based research from leading experts, I will explain how these peripheral conversion issues can render thyroid medication ineffective and even counterproductive. This post will also detail how our multidisciplinary practice, Injury Medical Clinic PA, integrates my expertise in chiropractic and functional medicine with the invaluable medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD, to provide a comprehensive, patient-centered treatment model. We will discuss how this collaborative approach, combining chiropractic care, functional medicine diagnostics, nutritional strategies, and lifestyle modifications, offers a powerful alternative to restore metabolic function and resolve thyroid symptoms without solely relying on prescriptions.

Introduction: A Patient’s Story and a Common Misconception

My name is Dr. Alex Jimenez. With a background spanning chiropractic, advanced practice nursing as a Family Nurse Practitioner, and multiple certifications in functional and integrative medicine, I’ve dedicated my career to understanding the body as a complex, interconnected system. For over three decades, I’ve witnessed a recurring pattern in my practice: patients arrive, frustrated and disheartened, after years of being told their thyroid issues are “managed” with medication, yet their debilitating symptoms persist.

A recent case that deeply illustrates this is Jennifer, a 41-year-old woman who came to me in tears. Through a video message, she described a seven-year-long ordeal. Despite being prescribed both Synthroid and levothyroxine by five different doctors, she was gaining weight, battling depression, suffering from constant cold hands and feet, and living in a perpetual state of brain fog. She was, in her own words, “dragging herself through life.” Her story is not unique; it’s a narrative I hear time and time again.

The fundamental misunderstanding that traps patients like Jennifer lies in a simplified view of thyroid function. The common belief is that if thyroid-stimulating hormone (TSH) levels are high, the thyroid gland is failing, and providing synthetic hormone is the complete solution. However, this overlooks the most critical part of the story.

Our Collaborative Care Model: Integrating Medicine and Chiropractic

At Injury Medical Clinic PA, we’ve built a practice model designed to address these complex, multi-system issues. I work closely with Dr. Maria Guadalupe Cardenas, MD, our distinguished Medical Director and an internist with over 40 years of experience. Dr. Cardenas (NPI #1164426749, Texas MD License #J2933) provides essential medical oversight, ensuring our patient care protocols are safe, effective, and grounded in the highest standards of internal medicine.

This multidisciplinary setup allows us to bridge the gap between conventional and functional approaches. While Dr. Cardenas provides the medical perspective and diagnostic supervision, my role focuses on leveraging functional medicine principles and chiropractic care to uncover and address the underlying drivers of disease. We integrate:

  • Medical Oversight (Dr. Cardenas): Ensuring all treatment plans are medically sound and appropriate, especially for patients with comorbidities or those on prescription medications.
  • Chiropractic and Neuromusculoskeletal Care (Dr. Jimenez): Addressing structural imbalances, improving nervous system function through adjustments, and reducing physical stressors that contribute to systemic inflammation and HPA axis dysregulation.
  • Functional Medicine: Using advanced diagnostic testing to identify root causes related to inflammation, gut health, nutrient deficiencies, and hormonal imbalances.
  • Personalized Rehabilitation and Nutrition: Creating bespoke plans to restore physiological function, support detoxification, and optimize metabolic health.

This integrated team approach is particularly vital for conditions like hypothyroidism, where the problem is rarely confined to a single organ. By combining our expertise, we can create a truly holistic and effective treatment journey for our patients.

Understanding Thyroid Hormone 101: The Gland vs. The Body

To understand why Jennifer’s medication wasn’t working, we need to go back to basic biology. Think of the thyroid gland as a manufacturing plant. Its primary job is to produce thyroxine (T4), which is a relatively inactive prohormone. That’s essentially all the gland does—crank out T4.

The real magic happens elsewhere. The liver, gut, kidneys, muscles, and even the brain act as conversion engines. These peripheral tissues convert the inactive T4 into the powerhouse hormone: triiodothyronine (T3). T3 is the active form that binds to nuclear receptors in nearly every cell of your body, revving up your metabolism, regulating your body temperature, supporting cognitive function, and influencing your mood.

When this peripheral conversion process is broken, you are effectively running on an empty metabolic tank. It doesn’t matter how much T4—whether from your own gland or from medications like Synthroid, levothyroxine, or even Armor Thyroid—is circulating in your system. If your body cannot make that final, crucial conversion to T3, the T4 is metabolically useless.

Worse yet, when the body is under stress or inflamed, it has a defense mechanism. Instead of converting T4 to active T3, it shunts T4 down an alternative pathway, creating reverse T3 (rT3). Reverse T3 is a metabolic brake. It fits perfectly into the T3 receptor but doesn’t activate it. It’s like putting the wrong key into a lock: it doesn’t open the door, and it also blocks the right key from getting in. So, by flooding a dysfunctional system with more T4, you may simply be providing more raw material for the body to produce more rT3, actively making the problem worse. This is precisely what was happening to Jennifer.

Through my thirty years of clinical practice and a deep dive into the research, I’ve found four primary physiological mechanisms that account for over 90% of the thyroid problems I see. The best part? They are all detectable through proper testing, and none of them inherently require medication to fix. They require a functional, root-cause approach.

Image Caption: This diagram illustrates the conversion pathway of thyroid hormones, showing the thyroid gland’s production of T4 and its subsequent conversion to active T3 or inactive reverse T3 in peripheral tissues like the liver and gut. Various factors influence this process, including inflammation, stress, and nutrient availability.

1. Systemic Inflammation: The Body’s Saboteur

The first and most pervasive disruptor of thyroid function is systemic inflammation. This isn’t the acute, helpful inflammation you get from a cut or sprain; this is chronic, low-grade inflammation that simmers throughout the body, wreaking havoc on delicate biochemical processes. The sources are numerous: a latent viral infection like Epstein-Barr Virus (EBV), metabolic dysfunction associated with obesity, undiagnosed food sensitivities, environmental toxin exposure, or chronic stress.

The Cytokine Cascade and Deiodinase Enzymes

Regardless of the source, the biological result is the same: the immune system releases a flood of inflammatory messengers called cytokines. You can think of these cytokines, such as Tumor Necrosis Factor-alpha (TNF-α) and Interleukin-6 (IL-6), as biological grenades. They signal danger and mobilize a defense, but in a chronic state, they cause widespread collateral damage.

One of their primary targets is the deiodinase enzyme system, which governs thyroid hormone conversion.

  • Deiodinase 1 (D1) and Deiodinase 2 (D2) are the enzymes responsible for converting T4 into active T3. D1 is found primarily in the liver, kidneys, and thyroid, while D2 is crucial in the pituitary gland, brain, and brown adipose tissue.
  • Deiodinase 3 (D3) converts T4 into the inactive reverse T3.

Inflammatory cytokines activate a master inflammatory switch inside our cells called Nuclear Factor-kappa B (NF-κB). When NF-κB is turned on, it orchestrates a powerful pro-inflammatory response. In the context of thyroid health, this has a devastating two-pronged effect:

  1. NF-κB shuts down the expression and activity of D1 and D2 enzymes. This directly blocks the conversion of T4 to active T3, starving your cells of metabolic energy.
  2. NF-κB simultaneously cranks up the activity of the D3 enzyme. This shunts the available T4 toward the production of reverse T3, the metabolic brake.

So, in chronic inflammation, your body actively prevents the production of the “go” hormone (T3) and promotes the production of the “stop” hormone (rT3). This is a survival mechanism—the body interprets chronic inflammation as a state of crisis and dials down metabolism to conserve resources. However, in modern life, this leads to the classic symptoms of hypothyroidism: fatigue, weight gain, depression, and brain fog, even with “normal” TSH and T4 levels on a standard lab test.

How We Address Systemic Inflammation

In our clinic, the first step is to identify and eliminate the sources of inflammation. This involves:

  • Comprehensive Blood Panels: We look beyond TSH and T4. We test inflammatory markers like high-sensitivity C-reactive protein (hs-CRP), homocysteine, and ferritin. We also run a full thyroid panel that includes Free T3, Free T4, Reverse T3, and thyroid antibodies (TPO and TG) to calculate the T3/rT3 ratio, a key indicator of cellular thyroid function.
  • Identifying Triggers: We may test for underlying infections like EBV, screen for food sensitivities using IgG food panels, and assess for heavy metal or environmental toxin exposure.
  • Chiropractic Care and the Nervous System: Physical stress and spinal misalignments (subluxations) can be a significant source of low-grade inflammation. The nervous system modulates the immune response. By performing specific chiropractic adjustments, we can reduce mechanical stress, improve neurological signaling, and help downregulate the body’s inflammatory state. This helps break the feedback loop where physical stress contributes to systemic inflammation, which in turn worsens thyroid function.
  • Anti-Inflammatory Nutrition: We guide patients toward a whole-foods, nutrient-dense diet rich in omega-3 fatty acids, polyphenols, and antioxidants to naturally quell the inflammatory fire. We often start with an elimination diet to remove common inflammatory triggers like gluten, dairy, and processed sugar.

2. Liver Congestion and Impaired Detoxification: The Conversion Bottleneck

The liver is the undisputed champion of T4-to-T3 conversion. Approximately 80% of all active T3 is produced inside the liver cells (hepatocytes) via the D1 deiodinase enzyme. Therefore, the health of your liver is inextricably linked to the health of your thyroid metabolism. When the liver is overburdened and congested, this critical conversion process grinds to a halt.

From Fatty Liver to Endoplasmic Reticulum Stress

One of the most common conditions I see in my practice is Non-Alcoholic Fatty Liver Disease (NAFLD), a condition where hepatocytes accumulate excess lipid droplets. This is often driven by a diet high in processed carbohydrates, fructose, and industrial seed oils. This fat accumulation doesn’t just make the liver sluggish; it triggers a cellular stress response within hepatocytes, particularly in an organelle called the endoplasmic reticulum (ER).

The ER folds proteins into their correct three-dimensional shapes. The D1 deiodinase enzyme is a protein that must be properly folded to function. When the liver is fatty and the ER is under stress, protein folding becomes sloppy. ER stress directly shuts down D1 deiodinase activity. The liver loses its ability to convert T4 to T3, creating a major bottleneck in your metabolic pathway.

The Role of Bile and the Enterohepatic Loop

The liver’s role doesn’t end with conversion. It also plays a vital part in hormone clearance and recycling through a process called conjugation. The liver attaches molecules (like glucuronic acid or sulfate) to used hormones and other toxins, making them water-soluble so they can be excreted in bile. This bile is then released into the small intestine.

A portion of these conjugated hormones is meant to be reabsorbed back into the bloodstream through the enterohepatic circulation, effectively recycling them for reuse. However, when the liver is congested and inflamed, bile production becomes impaired. The bile grows thick and sludgy, a condition known as cholestasis.

When bile flow stalls, two negative things happen:

  1. The enterohepatic loop stalls: The recycling of thyroid hormones becomes inefficient.
  2. Hormone clearance tanks: The liver can’t effectively package and excrete excess hormones and toxins. This leads to a backup of metabolic waste, further increasing the inflammatory burden on the body and perpetuating the cycle of dysfunction.

Our Approach to Supporting Liver Health

Restoring liver function is paramount for anyone with thyroid symptoms. Our integrated approach with Dr. Cardenas’s medical oversight includes:

  • Liver Function Testing: We assess liver enzymes (ALT, AST, GGT), but we also look at functional markers that indicate detoxification capacity.
  • Nutritional Protocols: We implement a diet that removes the burden on the liver. This means eliminating high-fructose corn syrup, processed foods, and refined carbohydrates. We emphasize foods that support liver detoxification, such as cruciferous vegetables (broccoli, cauliflower), allium vegetables (garlic, onions), and high-quality protein for amino acids essential for conjugation pathways.
  • Targeted Supplementation: We may use nutrients and botanicals known to support liver health, such as N-acetylcysteine (NAC), milk thistle (silymarin), dandelion root, and taurine, to support both Phase I and Phase II detoxification pathways and promote healthy bile flow.
  • Chiropractic and Visceral Manipulation: The liver is innervated by the thoracic spine. Chiropractic adjustments can improve nerve supply to the liver and surrounding organs. Additionally, specific visceral manipulation techniques can improve liver mobility, reduce congestion, and enhance fluid dynamics (blood and lymph flow), supporting its detoxification capacity.
What is Thyroid Dysfunction? | El Paso, Tx (2021)

3. Gut Dysbiosis and Leaky Gut: The Gateway for Inflammation

While the liver does the heavy lifting, the gut contributes about 20% of the body’s active T3. That may sound modest, but the gut’s influence extends far beyond this direct conversion. The health of your gut microbiome can determine whether your liver can even function properly as a conversion organ.

The Microbiome’s Role in Hormone Recycling

In a healthy gut, beneficial bacteria produce an enzyme called intestinal sulfatase. Remember how the liver conjugates thyroid hormone for excretion? This enzyme does the opposite. In the gut, it “deconjugates” or snips the T3 free from its carrier molecule, allowing it to be reabsorbed through the portal circulation and sent back to the liver for reuse. This is a critical part of the hormone recycling system.

In a state of dysbiosis—an imbalance between beneficial and pathogenic bacteria—those helpful, sulfatase-producing bacteria are diminished. As a result, the conjugated T3 is not recycled. Instead, it remains bound and is flushed right down the toilet with your stool. You are literally losing active thyroid hormone with every bowel movement.

Leaky Gut and Lipopolysaccharides (LPS)

Dysbiosis often goes hand in hand with increased intestinal permeability, or “leaky gut.” The gut lining, which should be a tightly controlled barrier, becomes compromised. This allows large, undigested food particles and bacterial components to “leak” into the bloodstream where they don’t belong.

One of the most potent inflammatory triggers that leaks through is lipopolysaccharide (LPS). LPS is a component of the outer membrane of Gram-negative bacteria. When it enters the circulation, the immune system recognizes it as a sign of a major bacterial invasion and mounts a massive inflammatory response. This LPS-driven inflammation sends cytokine levels soaring, and as we discussed earlier, these cytokines annihilate D1 deiodinase activity in the liver, shutting down T4-to-T3 conversion at its primary source.

So, a dysfunctional gut sabotages your thyroid in two ways: it prevents the recycling of active T3 and triggers systemic inflammation that blocks new T3 production.

Restoring Gut Integrity in Our Clinic

Healing the gut is a non-negotiable step in restoring thyroid function. Our protocol, overseen by Dr. Cardenas and implemented by our functional medicine team, often follows the “5R” framework:

  • Remove: We eliminate inflammatory foods, pathogenic organisms (bacteria, yeast, or parasites) identified through stool testing, and other gut irritants.
  • Replace: We support digestion with digestive enzymes, hydrochloric acid (if needed), and bile acids to ensure food breaks down properly.
  • Reinoculate: We introduce beneficial bacteria through targeted probiotics and fermented foods to restore a healthy microbial balance.
  • Repair: We use specific nutrients to heal the gut lining, such as L-glutamine, zinc, collagen, and soothing herbs like marshmallow root and slippery elm.
  • Rebalance: This is where lifestyle factors and chiropractic care come in. The gut-brain axis is a two-way street. Chronic stress can degrade gut health, and poor gut health can send stress signals to the brain. Chiropractic adjustments help to balance the autonomic nervous system, shifting the body from a “fight-or-flight” (sympathetic) state to a “rest-and-digest” (parasympathetic) state, which is essential for proper digestion and gut healing.

4. HPA Axis Dysregulation: The Stress-Metabolism Connection

This is the area where so many well-intentioned people get it wrong. Your body has a sophisticated system for managing stress called the Hypothalamic-Pituitary-Adrenal (HPA) axis. This axis governs the release of cortisol, your primary stress hormone. The critical thing to understand is that from a biological perspective, your HPA axis cannot tell the difference between being chased by a predator, dealing with immense psychological stress, or being in a prolonged, severe caloric deficit. They all look identical. They all trigger cortisol release.

Cortisol is a catabolic hormone designed for short-term survival. In an acute crisis, it’s incredibly useful. But when cortisol is chronically elevated due to relentless stress, it becomes destructive. One of its primary actions is to crush the activity of the D1 deiodinase enzyme and promote the conversion of T4 to reverse T3. Again, this is a survival mechanism: in a perceived famine or crisis, the body conserves energy by slamming the brakes on metabolism.

The Caloric Deficit and Fasting Trap

Here’s the scenario I see constantly: A person struggling with weight gain and fatigue decides to “fix” their metabolism. They commit to a rigorous plan involving intermittent fasting and a huge caloric deficit, often combined with high-intensity exercise. Their commitment is commendable, but their timing is terrible.

T4-to-T3 conversion in the liver is a highly energy-dependent process. Specifically, it requires adequate insulin and glycogen (the stored form of glucose in the liver). When you adopt a low-carbohydrate, heavy caloric restriction diet:

  1. You rapidly deplete your hepatic glycogen stores.
  2. Your circulating insulin and leptin (the “satiety” hormone) levels crash.

The liver interprets this combination of low insulin, low leptin, and depleted glycogen as a clear and present danger: famine. In response, it immediately shuts down D1 deiodinase activity to conserve energy. Trying to force weight loss through severe restriction tells the body to shut down the metabolic engine. The person may lose some weight initially (mostly water and muscle), but their metabolic rate plummets, their thyroid symptoms worsen, and they inevitably hit a plateau, often regaining the weight and then some.

Rebalancing the HPA Axis: Our Integrated Method

Addressing HPA axis dysregulation requires a gentle, multifaceted approach, not a brute-force one.

  • Advanced Hormonal Testing: We use tests like the DUTCH (Dried Urine Test for Comprehensive Hormones) to map out a patient’s daily cortisol and cortisone rhythm, along with levels of sex hormones and their metabolites. This gives us a precise picture of their HPA axis function.
  • Chiropractic Care and the Autonomic Nervous System: The autonomic nervous system directly regulates the HPA axis. Spinal misalignments, particularly in the upper cervical and thoracic regions, can create neurological interference that keeps the body locked in a sympathetic “fight-or-flight” state. Chiropractic adjustments are a powerful tool for shifting the nervous system back toward a parasympathetic “rest, digest, and heal” state. My clinical observations at Sciatica.clinic consistently show that patients receiving regular adjustments report better sleep, reduced anxiety, and improved stress resilience, all of which are crucial for HPA axis recovery.
  • Stress Management and Mind-Body Therapies: We teach and encourage practices like meditation, deep breathing exercises, gentle yoga, and spending time in nature to manage stress actively.
  • Nutritional Support and Caloric Repletion: We often need to guide patients to eat more of the right foods, not less. We focus on nutrient-dense carbohydrates, adequate protein, and healthy fats to replenish glycogen stores and signal to the body that the “famine” is over.
  • Adaptogenic Herbs: We may use adaptogenic herbs like Ashwagandha, Rhodiola, and Holy Basil to help the body modulate its stress response and restore a healthy cortisol rhythm. Dr. Cardenas’s medical expertise ensures these are used safely and appropriately, especially for patients on other medications.

Conclusion: You Are Not Your Diagnosis

Jennifer’s story has a happy ending. By systematically identifying and addressing these four areas, we restored her body’s natural ability to convert thyroid hormone. We healed her gut, supported her liver, calmed the systemic inflammation, and rebalanced her HPA axis. Her energy returned, the brain fog lifted, her mood stabilized, and her body began to release the excess weight naturally. Eventually, under the supervision of her prescribing physician, she was able to wean off her medications because her body was finally doing the job it was designed to do.

What do all four of these cases—inflammation, liver congestion, gut dysbiosis, and HPA axis dysfunction—share? They are all detectable with the right functional lab testing. The scientific literature clearly explains their mechanisms. And most importantly, they are addressable without a single prescription being written. The entire playbook is in the research.

If you are struggling with thyroid symptoms despite being on medication, or if you’ve been told your labs are “normal,” but you feel anything but, I want you to know there is hope. The problem may not be in your thyroid gland at all. The solution lies in taking a comprehensive, whole-body approach to uncover and correct the underlying dysfunctions that are sabotaging your metabolism. By integrating the best of internal medicine, functional diagnostics, and chiropractic care, we can guide your body back to balance and vibrant health.

  • References

SEO Tags: thyroid health, functional medicine, hypothyroidism, Dr. Alex Jimenez, Dr. Maria Cardenas, integrative chiropractic, El Paso TX, systemic inflammation, liver health, gut dysbiosis, HPA axis, cortisol, T4 to T3 conversion, reverse T3, Synthroid, levothyroxine, autoimmune disease, Hashimoto’s, chronic fatigue, weight gain, brain fog, functional nutrition, chiropractic care, personal injury, Injury Medical Clinic, evidence-based research

Nutrition Support for Head and Neck Injury Recovery Guide

Nutrition Support for Head and Neck Injury Recovery Guide

Nutrition Support for Head and Neck Injury Recovery

Abstract

A concussion or whiplash injury may affect more than the head or neck. The nervous system, digestive system, immune system, metabolism, muscles, joints, and spine constantly communicate. Researchers increasingly describe an important gut-brain axis in which the brain and digestive system exchange signals through nerves, hormones, immune pathways, and the gut microbiome.

After a head or neck injury, inflammation, stress, changes in activity, poor sleep, pain, and altered nutrition may disturb this communication. A recovery plan may therefore need to look beyond the painful area.

A protein-forward, anti-inflammatory nutrition plan, healthy gut support, sleep, hydration, controlled movement, rehabilitation, and appropriate chiropractic care can work together to support recovery. In carefully selected patients, medical and regenerative procedures may also address specific damaged tissues. The goal is not simply to cover up symptoms. It is to identify the factors that may be slowing recovery and address them in a coordinated way.

Nutrition Support for Head and Neck Injury Recovery Guide


What Is the Gut-Brain-Spine Connection?

The gut-brain-spine connection is a useful way to describe how the digestive system, central nervous system, autonomic nervous system, immune system, and musculoskeletal system influence each other.

Scientists more commonly call part of this network the gut-brain axis.

The gut and brain communicate through several major pathways:

  • The vagus nerve
  • The autonomic nervous system
  • Immune signaling
  • Hormones
  • Neurotransmitters
  • The gut microbiome
  • Metabolic products created by intestinal bacteria

The gut contains its own extensive nervous system, called the enteric nervous system. Signals travel continuously between this system and the brain. The vagus nerve is one of the most important communication routes (Cleveland Clinic, 2023).

Gut bacteria also produce metabolites and participate in immune and metabolic processes that may influence brain function. In return, stress, injury, hormones, medications, and nervous-system activity can change digestion and the intestinal environment (Gwak & Chang, 2021).

The spine enters this picture because the brain and spinal cord form the central nervous system, while spinal nerves and autonomic pathways help regulate movement, sensation, pain, and many automatic body functions.

However, this does not mean that every digestive problem comes from a spinal problem or that a spinal adjustment directly treats intestinal disease. The relationship is more complex.


What Happens After a Concussion or Whiplash Injury?

A motor vehicle collision, sports injury, fall, or other traumatic event may place significant force on both the brain and cervical spine.

A concussion is a form of mild traumatic brain injury, or mTBI. Whiplash primarily affects the neck but may involve muscles, ligaments, joints, nerves, headaches, dizziness, and balance systems.

A patient may experience:

  • Neck pain and stiffness
  • Headaches
  • Dizziness
  • Brain fog
  • Problems concentrating
  • Fatigue
  • Sleep changes
  • Light or sound sensitivity
  • Nausea
  • Mood changes
  • Changes in appetite or digestion

The initial injury may also be followed by a series of metabolic and inflammatory changes.

Research suggests that traumatic brain injury can affect intestinal movement, gut-barrier function, immune activity, and the gut microbiome. Scientists are studying whether these changes contribute to continued systemic inflammation and neurological symptoms (Iftikhar et al., 2020; Ghaemi & Kheradmand, 2025).

A 2025 review described TBI-related changes involving dysbiosis, intestinal barrier dysfunction, immune signaling, and neuroinflammation. However, researchers also stress that many proposed microbiome treatments still require stronger human clinical trials (Ghaemi & Kheradmand, 2025).

This is why recovery should not be reduced to simply asking, “Where does it hurt?”

A better question may be:

What systems have been disturbed by the injury, and what does the body need to recover?


Why Nutrition Matters After a Head Injury

The brain requires large amounts of energy even when the body is resting.

After a concussion, its normal energy metabolism may temporarily change. At the same time, a patient may eat less because of nausea, headaches, fatigue, medication effects, or changes in appetite.

This creates an important problem:

The body may need additional nutritional support while the patient is eating less effectively.

A systematic review of nutritional interventions after mild traumatic brain injury found encouraging evidence for meeting appropriate calorie and protein requirements. Researchers also identified possible benefits associated with nutrients such as omega-3 fatty acids, vitamin D, magnesium, and N-acetylcysteine in selected studies.

However, the authors emphasized that available human studies were too different and too limited to establish a single proven concussion supplement program (Finnegan et al., 2022).

Nutrition should therefore support medical and rehabilitative care rather than replace it.


A Protein-Forward Approach to Injury Recovery

Protein provides amino acids that the body uses to maintain and repair tissues.

This is important after whiplash because the injury may affect:

  • Muscles
  • Tendons
  • Ligaments
  • Connective tissues
  • Supporting spinal structures

Protein is also needed for enzymes, immune processes, neurotransmitter pathways, and general recovery.

A protein-forward meal might include:

  • Eggs
  • Chicken
  • Turkey
  • Fish
  • Lean beef
  • Greek yogurt
  • Cottage cheese
  • Beans or lentils
  • Tofu or tempeh
  • A quality protein shake when appropriate

Rather than eating most of the day’s protein at dinner, patients can often benefit from spreading protein-containing foods throughout the day.

Individual needs vary with age, body size, kidney function, activity level, metabolic health, and injury severity. This is one reason nutritional recommendations should be individualized.


Feeding the Gut During Neurological Recovery

Protein is only one part of the strategy.

The intestinal microbiome also depends heavily on the foods a person regularly eats.

A whole-food eating pattern can include:

  • Vegetables of different colors
  • Berries and other fruits
  • Beans and lentils
  • Nuts and seeds
  • Oats and other whole grains
  • Olive oil
  • Fish
  • Fermented foods when tolerated
  • Adequate water

Many plant foods provide fiber, which beneficial gut organisms can use as fuel.

Some gut bacteria convert fiber into compounds called short-chain fatty acids. These metabolites participate in intestinal barrier health, metabolism, and immune regulation (Gwak & Chang, 2021).

Limiting large amounts of added sugar and heavily processed foods may also help create a more favorable nutritional environment (Hill, 2026).

This does not mean someone recovering from a concussion needs a restrictive “detox” diet.

The goal is usually much simpler:

Give the body enough protein, calories, fiber, healthy fats, vitamins, minerals, and fluids to support recovery.


Supplements for Concussion Recovery: What Does the Evidence Say?

Several nutritional compounds are being studied for concussion and traumatic brain injury.

Omega-3 fatty acids

EPA and DHA are found mainly in fatty fish and fish oil. DHA is particularly important in brain-cell membranes.

Human studies are encouraging, but researchers have not established one universally accepted dose or protocol for concussion recovery (Finnegan et al., 2022).

Vitamin D

Vitamin D supports immune, bone, muscle, and neurological functions. Correcting a documented deficiency may be important for overall health.

Taking excessive vitamin D without testing or clinical supervision is not recommended.

Magnesium

Magnesium participates in hundreds of biochemical reactions involving muscles, nerves, and energy metabolism. Research has explored magnesium following brain injury, but evidence is not strong enough to treat it as a stand-alone concussion therapy.

N-acetylcysteine

N-acetylcysteine, or NAC, is involved in antioxidant pathways and has also been studied after brain injury. Research remains developing.

The key lesson is simple:

Supplements should be selected because they fit the patient’s needs—not because they are popular online.

An appropriately licensed healthcare professional should review medication interactions, kidney or liver disease, anticoagulant use, pregnancy, laboratory findings, and other conditions.


Sleep, Stress, and Metabolic Health Matter Too

Food cannot compensate for poor recovery habits.

Sleep is especially important because neurological recovery depends on adequate rest and normal sleep-wake cycles.

An integrative recovery plan may address:

  • Consistent sleep schedules
  • Adequate hydration
  • Appropriate calorie intake
  • Blood-sugar stability
  • Gradual return to physical activity
  • Reduced alcohol intake
  • Stress management
  • Controlled screen exposure when symptoms require it
  • Progressive rehabilitation
  • Treatment of neck dysfunction

Prolonged complete rest is generally no longer viewed as the best answer for every concussion patient. Modern rehabilitation often progresses activity carefully according to symptoms and clinical findings.


Where Integrative Chiropractic Care Fits

Chiropractic care has a clearer evidence base for mechanical neck pain and selected whiplash-associated disorders than it does for directly changing the gut microbiome.

That distinction is important.

Clinical guidelines support multimodal approaches that may include manual therapy, mobilization or manipulation, exercise, education, and rehabilitation for appropriately screened patients with neck pain and whiplash-associated disorders (Bussières et al., 2016).

Care may target:

  • Restricted cervical joints
  • Reduced neck movement
  • Muscle guarding
  • Postural dysfunction
  • Cervicogenic headaches
  • Mechanical pain
  • Strength deficits
  • Abnormal movement patterns

For patients with persistent concussion symptoms involving dizziness, headache, and neck pain, research also supports appropriately selected cervical and vestibular rehabilitation approaches (Schneider et al., 2014).

Chiropractic treatment should therefore be viewed as one piece of a broader neurological and musculoskeletal rehabilitation plan, not as a treatment that independently “cures” concussion or digestive disease.


Advanced Regenerative and Interventional Treatment

Some head and neck injury patients continue to have pain because a specific physical structure remains damaged or irritated.

In carefully selected cases, advanced treatment may target these structural pain generators.

Options may include:

  • Platelet-rich plasma, or PRP
  • Other platelet-based procedures
  • Image-guided injections
  • Photobiomodulation or therapeutic laser
  • Shockwave therapy for selected soft-tissue conditions
  • Specialized rehabilitation

PRP has attracted particular interest for chronic cervical facet pain following whiplash.

A prospective study of 44 people with chronic whiplash-associated disorders found improvements in pain and disability after cervical facet PRP injections. However, this was a case series rather than a randomized controlled trial, so the results should be considered preliminary (Smith et al., 2022).

Longer follow-up from the same research group also showed encouraging results, while again calling for controlled trials (Smith et al., 2023).

A broader review has likewise described growing interest in PRP, platelet lysate, prolotherapy, and related regenerative injections for selected spinal pain conditions while emphasizing that evidence differs greatly by diagnosis and procedure (Williams et al., 2021).

These therapies should not be described as treatments that regenerate the injured brain after concussion.

Instead, their most reasonable role is to address carefully diagnosed musculoskeletal or spinal structures that may be contributing to continuing pain and disability.


Laser and Shockwave Therapy

Photobiomodulation uses specific wavelengths of light to influence cellular processes.

Research into photobiomodulation following traumatic brain injury is interesting, but much of the strongest experimental evidence remains preclinical. A systematic review found extensive animal research but very limited human evidence for acute TBI (Stevens et al., 2023).

Therefore, laser therapy should not be promoted as a proven cure for concussion.

For musculoskeletal neck pain, however, laser and extracorporeal shockwave therapies have been studied as physical medicine options. Recent evidence suggests some biophysical treatments may help selected patients with neck pain, and shockwave therapy has demonstrated benefits in studies of neck and shoulder myofascial pain (Jun et al., 2021).

The correct treatment depends on what tissue is actually injured.


Treating Both Ends of the Recovery Loop

An integrative head and neck injury program can be thought of as working from several directions at once.

From the structural side:

  • Restore safe movement
  • Reduce mechanical stress
  • Rehabilitate weakened muscles
  • Improve cervical function
  • Address persistent tissue injuries when medically indicated

Metabolic side:

  • Provide sufficient protein and calories
  • Correct nutritional deficiencies
  • Improve diet quality
  • Support healthy blood-sugar control
  • Maintain hydration

Gut and inflammatory side:

  • Increase whole foods and plant diversity
  • Provide adequate fiber
  • Support microbiome diversity
  • Reduce excessive highly processed foods
  • Address digestive problems when clinically present

Neurological side:

  • Restore sleep
  • Progress physical activity
  • Address dizziness and balance problems
  • Manage headaches
  • Monitor cognition
  • Reduce unnecessary stress on the recovering nervous system

This is the practical meaning of treating the gut-brain-spine connection.


Dr. Alex Jimenez’s Integrative Clinical Approach

Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, combines his chiropractic background with his training as a board-certified family nurse practitioner and functional medicine practitioner.

His published clinical educational materials emphasize looking at injury through several lenses at once: biomechanics, neurological function, nutrition, metabolic health, inflammation, sleep, rehabilitation, and lifestyle.

His earlier discussion of the gut-brain connection also emphasizes the two-way relationship among intestinal health, nervous-system activity, inflammation, lifestyle, and stress (Jimenez, n.d.).

In clinical practice, this means that a neck injury is not viewed only as a painful vertebra, and a concussion is not viewed only as a headache.

The broader question becomes:

What physical, neurological, nutritional, metabolic, and lifestyle factors may be preventing this person from moving toward recovery?

Dr. Jimenez’s published practice materials describe this root-cause and multidisciplinary approach across chiropractic care, functional medicine, personal injury management, and rehabilitation. These clinical observations help guide individualized care but should be distinguished from findings produced by controlled clinical trials.


Medical Oversight With Dr. Maria Guadalupe Cardenas, MD

The Injury Medical Clinic PA model also combines chiropractic and functional rehabilitation with medical oversight.

According to the practice’s published clinician information, Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine and has more than 40 years of clinical experience as an internist. The practice lists her as NPI #1164426749 and Texas MD License #J2933.

She serves as medical director and collaborative physician alongside Dr. Alex Jimenez at Injury Medical Clinic PA in El Paso, Texas.

This multidisciplinary structure allows different parts of recovery to be coordinated:

  • Dr. Jimenez: chiropractic evaluation, musculoskeletal care, functional medicine, rehabilitation, and injury management.
  • Dr. Cardenas: internal medicine perspective, medical oversight, systemic risk assessment, and coordination of medical issues.
  • Rehabilitation team: progressive movement, strengthening, mobility, and functional restoration.
  • Integrated services: nutrition, personal injury care, metabolic health support, diagnostic coordination, and related therapies.

The purpose is not to make chiropractic and medicine compete.

It is to allow them to work together when a complicated injury crosses several body systems.


A Root-Cause Recovery Strategy

The greatest lesson from the gut-brain-spine model is that recovery is rarely controlled by one factor.

A patient with persistent symptoms may have several problems occurring together:

  • Cervical joint injury
  • Muscle dysfunction
  • Poor sleep
  • Reduced activity
  • Nutritional deficiencies
  • Inadequate protein
  • Digestive problems
  • Metabolic dysfunction
  • Stress
  • Neurological symptoms

Treating only pain may overlook these contributors.

A functional and integrative approach asks what can safely be changed to improve the biological environment in which healing takes place.

That may mean combining protein-forward nutrition, whole-food eating, appropriate supplements, sleep restoration, chiropractic care, rehabilitation, medical oversight, and carefully selected advanced therapies.

No single treatment can guarantee faster neurological recovery.

But giving the body appropriate nutrition, restoring movement, managing mechanical injuries, protecting neurological health, and addressing medical problems together can create a much stronger foundation for healing.

Important Safety Note

Anyone with a suspected concussion should receive an appropriate medical evaluation. Emergency assessment is especially important for symptoms such as worsening severe headache, repeated vomiting, increasing confusion, seizures, weakness, loss of consciousness, slurred speech, or unusual behavior.

Regenerative procedures, supplements, spinal manipulation, laser therapy, and other treatments should be recommended only after an appropriate examination and diagnosis.

The Natural Way to Heal: Non-Surgical Chiropractic Care for Pain Relief | El Paso, Tx (2023)

References

Bussières, A. E., Stewart, G., Al-Zoubi, F., et al. (2016). The treatment of neck pain-associated disorders and whiplash-associated disorders: A clinical practice guideline. Journal of Manipulative and Physiological Therapeutics, 39(8), 523–564.e27. https://doi.org/10.1016/j.jmpt.2016.08.007

Cleveland Clinic. (2023). What is the gut-brain connection?

Finnegan, E., Daly, E., Pearce, A. J., & Ryan, L. (2022). Nutritional interventions to support acute mTBI recovery. Frontiers in Nutrition, 9, 977728. https://doi.org/10.3389/fnut.2022.977728

Ghaemi, M., & Kheradmand, D. (2025). The gut-brain axis in traumatic brain injury: Literature review. Journal of Clinical Neuroscience, 136, 111258. https://doi.org/10.1016/j.jocn.2025.111258

Gwak, M.-G., & Chang, S.-Y. (2021). Gut-brain connection: Microbiome, gut barrier, and environmental sensors. Immune Network, 21(3), e20. https://doi.org/10.4110/in.2021.21.e20

Hill, J. (2026). The gut-brain connection: How gut health impacts mental health. HelpGuide.org.

Iftikhar, P. M., Anwar, A., Saleem, S., Nasir, S., & Inayat, A. (2020). Traumatic brain injury causing intestinal dysfunction: A review. Journal of Clinical Neuroscience, 79, 237–240. https://doi.org/10.1016/j.jocn.2020.07.019

Jimenez, A. (n.d.). The gut-brain connection. DrAlexJimenez.com.

Jimenez, A. (2026). Integrative medical and diagnostic centers. DrAlexJimenez.com.

Jun, J. H., et al. (2021). The effect of extracorporeal shock wave therapy on pain intensity and neck disability for patients with myofascial pain syndrome in the neck and shoulder: A meta-analysis of randomized controlled trials. American Journal of Physical Medicine & Rehabilitation, 100(2), 120–129.

Schneider, K. J., Meeuwisse, W. H., Nettel-Aguirre, A., et al. (2014). Cervicovestibular rehabilitation in sport-related concussion: A randomised controlled trial. British Journal of Sports Medicine, 48(17), 1294–1298. https://doi.org/10.1136/bjsports-2013-093267

Smith, A., Andruski, B., Deng, G., & Burnham, R. (2022). Cervical facet joint platelet-rich plasma in people with chronic whiplash-associated disorders: A prospective case series of short-term outcomes. Interventional Pain Medicine, 1(2), 100078. https://doi.org/10.1016/j.inpm.2022.100078

Smith, A., Andruski, B., Deng, G., & Burnham, R. (2023). Cervical facet joint platelet-rich plasma in people with chronic whiplash-associated disorders: Longer-term 6- and 12-month outcomes. Interventional Pain Medicine, 2(1), 100237. https://doi.org/10.1016/j.inpm.2023.100237

Stevens, A. R., Hadis, M., Milward, M., Ahmed, Z., Belli, A., Palin, W., & Davies, D. J. (2023). Photobiomodulation in acute traumatic brain injury: A systematic review and meta-analysis. Journal of Neurotrauma, 40(3–4), 210–227. https://doi.org/10.1089/neu.2022.0140

Williams, C., et al. (2021). Regenerative injection treatments utilizing platelet products and prolotherapy for cervical spine pain: A functional spinal unit approach. Cureus, 13.

Nervous System Management With Non-Pharmacological Strategies

Explore non-pharmacological strategies to support nervous system health and wellness without medications to the body.

Abstract

In this educational post, I present a comprehensive, practical framework for understanding and managing panic attacks that arise during sauna sessions or high-intensity cardio, and I explain why these reactions occur from a neurophysiological standpoint. I discuss the role of the amygdala, vagus nerve, carbon dioxide tolerance, cardiorespiratory coupling, and autonomic dysregulation. I outline a stepwise plan that integrates breathwork (including the physiological sigh), nasal-only breathing during cardio, and graded exposure principles. I examine how magnesium glycinate, L-theanine, taurine, and select neuropeptides may modulate autonomic responses, while also reviewing the GI-brain axis and inflammatory signaling that influence panic thresholds.

I also describe our multidisciplinary model at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where I collaborate with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), who serves as our Medical Director and Collaborative Physician. Together, we integrate chiropractic care, internal medicine oversight, functional medicine, personal injury care, rehabilitation, and targeted lifestyle interventions to address both the triggers and the roots of autonomic imbalance. Throughout, I highlight how integrative chiropractic care supports neuromusculoskeletal resilience, autonomic regulation, and improved exercise tolerance, and I present evidence-based methods from leading researchers to support each step.

This post is designed to be easy to read, first-person, and journey-oriented, guiding you from physiological understanding to actionable protocols that you can implement with medical guidance. The material is informed by my clinical observations and case insights from my practice and educational platforms, including resources available at Sciatica. clinic and my professional updates on LinkedIn.

Understanding Panic During Sauna and Cardio: Why Your Brain Sounds the Alarm

When a patient tells me they used to enjoy sauna therapy and vigorous workouts but now panic during heat exposure or high-intensity cardio, my first message is simple and compassionate: you are not broken. What you are experiencing is a nervous system stuck on red alert. Your heart rate rises, your respiration shifts, your skin warms, and your amygdala—the brain’s alarm center—mislabels those signals as danger. It’s a false alarm, but the brain’s threat circuitry has become hardwired to interpret normal arousal as risk.

  • The core issue: the amygdala reads bodily arousal—heat, heart rate, breath—as threat rather than a fitness stimulus.
  • The result: panic surges during sauna or intense cardio.
  • The opportunity: we can retrain the circuitry using mechanical tools (breathwork), metabolic supports (nutrients and peptides under medical supervision), and graded exposure (structured, progressive practice) to re-label arousal as safe.

This is where modern integrative care excels. In our clinic, I coordinate with Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician, to clinically assess the autonomic system, cardiorespiratory function, and metabolic drivers of anxiety. I’m combining chiropractic neuro-musculoskeletal regulation with functional medicine principles and medical oversight to deliver a comprehensive approach that works with your brain-body systems.

Meet Our Multidisciplinary Team: Integrative Chiropractic Care with Internal Medicine Oversight

At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, I, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, partner with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933). Dr. Cardenas has over 40 years of experience as an internist and provides medical direction and collaborative physician leadership in our integrative model. This multidisciplinary setup is common in injury and functional clinics, where a medical doctor works alongside a chiropractor to ensure safety, evidence-based protocols, and continuity of care.

  • Dr. Cardenas (Internal Medicine):
    • Oversees medical safety, diagnostics, and pharmacologic considerations.
    • Evaluates cardiovascular, endocrine, and inflammatory contributors to panic.
    • Guides decisions around peptide use, nutrient dosing, and contraindications.
  • Dr. Jimenez (Chiropractic and Functional Medicine):
    • Provides integrative chiropractic care emphasizing neuro-musculoskeletal alignment, autonomic regulation, and movement pattern optimization.
    • Coordinates breathwork protocols, exercise pacing, and rehabilitation phases.
    • Integrates functional medicine assessments for gut-brain axis, micronutrients, and stress physiology.
  • The team:
    • Synchronizes treatment plans across personal injury care, rehabilitation, lifestyle medicine, and neurobehavioral retraining.
    • Uses evidence-based, modern research methods to monitor progress and refine interventions.

This collaboration ensures a patient’s panic-related exercise intolerance is approached safely and comprehensively.

The Physiology of Panic: From Amygdala Alarm to Autonomic Imbalance

To change your response to sauna heat or cardio, we must understand the physiology:

  • The amygdala’s role:
    • The amygdala surveys interoceptive signals (heart rate, temperature, breathing effort) for threat.
    • In sensitized states, the amygdala fires alarms to avoid perceived danger, producing panic and sympathetic surges (LeDoux & Pine, 2016).
  • Autonomic nervous system (ANS):
    • Sympathetic arousal increases heart rate, dilates pupils, and mobilizes energy for action.
    • Parasympathetic activity (vagus nerve) restores calm, lowers heart rate, and stabilizes breathing (Thayer & Lane, 2000).
    • Panic represents an imbalance: sympathetic dominance with reduced vagal brake (Park & Thayer, 2014).
  • Interoception and prediction:
    • The brain predicts whether arousal is “exercise” or “danger.”
    • Mislabeling occurs when prior experiences of distress tether arousal to threat, creating a conditioned fear of bodily signals (Paulus & Stein, 2006).
  • CO2 tolerance:
    • Hyperventilation lowers CO2 and can trigger panic through chemosensory pathways; mouth breathing during exertion often exacerbates this by promoting shallow, fast breaths (Nardi et al., 2009).
  • Heat stress:
    • Sauna increases core temperature and heart rate; a sensitized nervous system may interpret these as precursors to danger.
    • The key: graded exposure teaches the brain that heat-induced arousal is normal and safe when properly paced (Havenith et al., 2011).

Understanding this biology empowers you to use mechanical and behavioral tools to reset the threat circuitry.

Breathwork as a Mechanical Reset: The Physiological Sigh

You cannot outthink a panic attack; you must engage it mechanically. One powerful tool is the physiological sigh. This involves two sharp inhales through the nose followed by a long, slow exhale through the mouth. The double inhale helps reinflate alveoli, improve oxygenation, and increase CO2 tolerance; the prolonged exhale recruits the vagus nerve to downshift autonomic arousal (Huberman et al., 2021).

  • How to perform:
    • Two quick nasal inhales (the second slightly shorter).
    • One long, slow oral exhale.
  • Why it works:
    • The breath pattern optimizes gas exchange and stimulates parasympathetic tone.
    • The prolonged exhale enhances vagal influence on heart rate variability (HRV).
  • When to use:
    • Five cycles before sauna exposure.
    • Five cycles during the sauna if anxiety starts to rise.
    • Five cycles immediately after the sauna during cool-down.
    • Use as needed before cardio and during recovery periods.

This breathwork is an autonomic lever—fast, practical, and highly effective for many patients in our clinic.

Nasal-Only Breathing in Cardio: Building CO2 Tolerance and Calm

Mouth breathing during intense exercise often induces over-breathing, lowering CO2 and heightening panic susceptibility. Nasal breathing drives diaphragmatic mechanics, filters and humidifies air, and supports CO2 retention within a healthy range to prevent panic triggers (Courtney, 2009).

  • Protocol:
    • Engage in zone 2 cardio using nasal-only breathing for 2–3 weeks.
    • Avoid max effort sessions during retraining.
    • Focus on rhythm: steady nasal inhalation, relaxed exhalation, and a conversational pace.
  • Benefits:
    • Improves CO2 tolerance and reduces chemoreflex-driven anxiety.
    • Supports autonomic balance (better HRV).
    • Develops cardiorespiratory efficiency and lowers perceived stress.

I consistently observe improved exercise tolerance and decreased panic frequency when patients commit to nasal-only breathing during the early retraining phase.

Nutrient Anchors for Panic Modulation: Magnesium Glycinate, L-Theanine, and Taurine

Under medical guidance, certain nutrients can anchor the nervous system before panic-provoking activities:

  • Magnesium glycinate (approx. 400 mg):
    • Supports GABAergic tone and modulates NMDA receptor activity.
    • Helps stabilize cardiac rhythm and reduce neuromuscular hyperexcitability (Boyle et al., 2017).
  • L-theanine (approx. 200 mg):
    • Promotes alpha-wave activity and increases GABA, serotonin, and dopamine modulation without sedation (Williams et al., 2020).
  • Taurine (approx. 2 g):
    • Influences GABA and glycine receptors, stabilizes cardiac electrophysiology, and blunts adrenaline spikes (Schaffer et al., 2014).
  • Timing:
    • Take all three approximately 30 minutes before any activity that previously provoked panic (e.g., sauna or cardio), provided your physician agrees and no contraindications exist.

These nutrients, paired with breathwork and graded exposure, create a biochemical and behavioral platform for resilience. We screen for interactions, contraindications, and individualized dosing under Dr. Cardenas’s medical oversight.

Peptide Considerations and Medical Oversight: Select, BPC-157, and KPV

In carefully selected cases, and only with medical supervision, we may discuss peptides that modulate anxiety, gut-brain signaling, and inflammation thresholds. The goal is to support long-term resilience while ensuring safety.

  • Select (a GABAergic peptide; 500 mcg no later than 4:00 PM):
    • Intended to quiet anxiety without sedation and promote durable resilience.
    • Used as a tool to recalibrate anxiety circuitry during the retraining phase.
    • We avoid morning dosing to prevent daytime sluggishness and align with circadian modulation of arousal.
  • BPC-157 (500 mcg twice daily):
    • Supports GI mucosal integrity and angiogenesis, and may influence vagal signaling by improving gut barrier function.
    • We consider this when the gut-brain axis shows signs of distress (e.g., IBS-like symptoms, post-infectious GI issues).
  • KPV (1 mg daily):
    • A melanocortin-derived tripeptide associated with anti-inflammatory effects.
    • Considered when systemic inflammation appears to lower the nervous system’s panic threshold.

These discussions are always under Dr. Cardenas’s medical leadership. We evaluate cardiovascular status, psychiatric history, medication interactions, regulatory guidance, and ethical use. Evidence for peptides varies; we weigh mechanistic plausibility with emerging data and clinical outcomes to ensure patient safety and informed consent.

The Gut-Brain Axis: Why GI Signaling Can Trigger Amygdala Alarms

Patients are often surprised that gut distress can telegraph directly to the amygdala and shape anxiety responses. The gut houses extensive neural networks and communicates through vagal pathways, immune mediators, and endocrine signals. Dysbiosis, barrier dysfunction, and inflammation can elevate interoceptive “noise,” making the brain more likely to misinterpret arousal as threat (Mayer et al., 2015; Cryan et al., 2019).

  • Mechanisms:
    • Altered microbiota composition affects neurotransmitter precursors and inflammatory cytokines.
    • Leaky gut increases LPS and immune activation, lowering thresholds for autonomic instability.
    • Vagal afferents carry GI distress signals to brain regions including the amygdala and insula.
  • Clinical approach:
    • Assess GI symptoms, nutrition, stress load, and sleep.
    • Use targeted dietary protocols, probiotics/prebiotics (when appropriate), and barrier-supportive strategies.
    • Consider peptides like BPC-157 under medical supervision when barrier repair is prioritized.

We regularly find that stabilizing the gut environment reduces panic frequency and intensity during exercise and heat exposure.

Inflammation and Panic Threshold: Lowering the System’s Sensitivity

Systemic inflammation sensitizes neural circuits and the cardiorespiratory system, lowering the threshold at which normal arousal triggers panic. High-sensitivity CRP, cytokine patterns, and clinical signs of low-grade inflammation often correlate with anxiety and somatic hypervigilance (Dantzer et al., 2008).

  • Intervention targets:
    • Anti-inflammatory nutrition (e.g., omega-3s, polyphenols, balanced glycemic load).
    • Sleep optimization and circadian alignment.
    • Graded physical activity without exceeding panic thresholds.
    • Consideration of anti-inflammatory peptides (e.g., KPV) under medical oversight.
  • Chiropractic integration:
    • Reducing musculoskeletal strain and nociceptive input can decrease sympathetic tone.
    • Spinal and rib mechanics influence breathing efficiency and interoceptive clarity.
    • Pain reduction reduces the background “alarm” that can fuel panic.

By decreasing inflammatory signaling, the brain can more accurately label arousal as safe, supporting the retraining process.

Graded Exposure: Teaching the Brain That Arousal Is Not Danger

You do not go from zero to one hundred. We implement structured progression:

  • Sauna progression:
    • Start with 10 minutes.
    • Exit before panic arises; perform physiological sigh cycles.
    • Extend by small increments over weeks while maintaining calm breathing and focus.
  • Cardio progression:
    • Begin with zone 2 nasal-only breathing for 2–3 weeks.
    • Avoid max effort until panic episodes diminish and CO2 tolerance improves.
    • Use heart rate and perceived exertion to keep intensity within a calm range.
  • Rationale:
    • Graded exposure rewires amygdala circuits by pairing arousal cues with safety experiences.
    • Each calm session writes a new prediction: “heat and heart rate equal training, not danger.”

Patients often regain confidence rapidly when they follow this plan closely.

Beyond Adjustments: Chiropractic and Integrative Healthcare- Video

Beyond Adjustments: Chiropractic and Integrative Healthcare | El Paso, Tx (2024)

Integrative Chiropractic Care: Autonomic Regulation Through Musculoskeletal Alignment

From a chiropractic perspective, autonomic regulation is deeply connected to rib mechanics, diaphragm function, thoracic mobility, and cervical alignment. When rib motion is restricted, or the diaphragm is inhibited, breathing becomes shallow and erratic, increasing sympathetic tone and panic susceptibility. Correcting these mechanical constraints can be transformative.

  • Techniques:
    • Thoracic and rib mobilization to improve chest wall compliance.
    • Diaphragm release and motor control training for efficient respiration.
    • Cervical spine alignment to reduce nociception and sympathetic drive.
    • Soft tissue work to normalize respiratory accessory muscles (SCM, scalenes, intercostals).
  • Outcomes:
    • Smoother breathing mechanics support nasal-only cardio.
    • Reduced musculoskeletal pain lowers baseline arousal.
    • Improved interoception helps the brain assess exertion accurately.

I consistently observe that integrating breath-focused chiropractic sessions with sauna/cardio retraining accelerates recovery from panic-linked exercise intolerance.

Functional Medicine Integration: Nutrients, Sleep, Stress, and Rhythms

Functional medicine provides the lifestyle scaffolding that makes retraining stick.

  • Nutrition:
    • Magnesium-rich foods, balanced amino acids, anti-inflammatory fats, and stable glycemic control.
    • Hydration and electrolytes tailored to heat exposure and exercise demands.
  • Sleep and circadian rhythm:
    • Consistent sleep-wake cycles enhance autonomic stability and reduce the likelihood of anxiety (Walker, 2017).
    • Avoid late caffeine; align meal timing with training sessions.
  • Stress modulation:
    • Mindfulness, non-sleep deep rest (NSDR), and paced breathing augment vagal tone.
    • Social connection and structured recovery days support resilience.

In my practice, these pillars make the difference between short-term symptom relief and long-term rewiring.

Personal Injury Care and Rehabilitation: Managing Pain, Fear, and Return to Activity

In personal injury contexts, pain plus fear often coalesce into panic during exertion. Our rehabilitation team designs plans that gradually restore movement confidence:

  • Assessment:
    • Identify pain generators, instability, and avoidance patterns.
    • Screen for dizziness, dysautonomia, and hyperventilation tendencies.
  • Plan:
    • Low-threat movements with clear breathing cues.
    • Incremental loading, tracking heart rate and subjective anxiety.
    • Integration of chiropractic adjustments and soft tissue therapies to reduce nociceptive drive.

The goal is a safe, paced return to sauna and cardio, with reduced pain and disarmed panic.

Clinical Observations from My Practice

From sciatica-focused work to integrative anxiety care, I’ve seen how autonomic retraining transforms lives. On sciatica. clinic and my professional updates on LinkedIn, I discuss how breath-led movement, thoracic mechanics, and nervous system retraining improve not only pain but also tolerance for heat and exertion. Patients who initially panic in saunas or during sprints often regain enjoyment of these activities when we anchor their physiology with breathwork, nutrients, and graded exposure, all under proper medical oversight.

  • Common patterns:
    • Mouth breathing and poor rib mobility drive panic.
    • Inflammation and GI distress lower thresholds.
    • Sleep inconsistency magnifies sensitivity.
  • Common solutions:
    • Nasal breathing, physiological sigh, magnesium/theanine/taurine anchors.
    • GI support and anti-inflammatory strategies.
    • Autonomic-friendly chiropractic care.

These patterns are consistent and addressable.

Safety, Medical Screening, and Individualization

Every plan is individualized. With Dr. Cardenas’s internal medicine expertise, we screen for:

  • Cardiovascular disease, arrhythmias, and heat intolerance.
  • Endocrine issues (thyroid, adrenal) that affect autonomic balance.
  • Psychiatric comorbidities and medication interactions.
  • Contraindications for sauna, high-intensity cardio, nutrients, and peptides.

Individualization is the trademark of good care. We harmonize chiropractic interventions with medical oversight and functional strategies to keep patients safe and progressing.

Putting It All Together: The Stepwise Plan

Here is the concise blueprint we use, organized for clarity:

  • Before sauna or cardio:
    • Perform five cycles of the physiological sigh.
    • If medically appropriate: magnesium glycinate ~400 mg, L-theanine ~200 mg, taurine ~2 g about 30 minutes prior.
  • During sauna:
    • Start at 10 minutes; exit before panic.
    • Use physiological sigh if anxiety rises; cool down slowly.
  • Cardio retraining:
    • Zone 2 intensity; nasal-only breathing for 2–3 weeks.
    • Avoid max effort; build CO2 tolerance gradually.
  • Daily supports:
    • Sleep consistency; anti-inflammatory nutrition; hydration.
    • If medically approved: Select (500 mcg no later than 4:00 PM), BPC-157 (500 mcg twice daily), KPV (1 mg daily).
  • Chiropractic and rehab:
    • Thoracic mobility, diaphragm training, rib mechanics.
    • Soft tissue normalization; progressive movement confidence.
  • Functional medicine:
    • Gut-brain axis assessment; barrier support; microbiome care.
    • Stress management practices and non-sleep deep rest.

This plan has helped many patients re-enter sauna and vigorous exercise without panic, restoring health, confidence, and joy.

Evidence Base and Research Foundations

We draw from a broad literature:

  • Amygdala and anxiety circuitry: LeDoux & Pine (2016).
  • Autonomic balance and HRV: Thayer & Lane (2000); Park & Thayer (2014).
  • Interoceptive predictions and panic: Paulus & Stein (2006).
  • CO2, hyperventilation, and panic: Nardi et al. (2009); Courtney (2009).
  • Heat stress physiology: Havenith et al. (2011).
  • Breath and autonomic modulation: Huberman et al. (2021).
  • Nutrients: Boyle et al. (2017); Williams et al. (2020); Schaffer et al. (2014).
  • Gut-brain axis: Mayer et al. (2015); Cryan et al. (2019).
  • Inflammation and mood/anxiety: Dantzer et al. (2008).
  • Sleep and emotion regulation: Walker (2017).

We implement modern, evidence-based research methods and continually update protocols in response to emerging findings and clinical outcomes.

Closing Perspective

If panic has taken away your sauna time or your high-intensity cardio, there is a path back. With mechanical breath tools, paced progression, target nutrients, and integrative chiropractic care under internal medicine oversight, we can re-label arousal as safety and restore your capacity for vigorous, enjoyable activity. In our El Paso clinic, I work closely with Dr. Maria Guadalupe Cardenas, MD, to ensure that every step is medically sound and tailored to you.

Your nervous system can learn calm again. With structure, support, and practice, we can guide it there.

References

SEO tags: panic attacks, sauna anxiety, high-intensity cardio panic, physiological sigh, nasal breathing, CO2 tolerance, vagus nerve, autonomic nervous system, amygdala, chiropractic care, integrative medicine, internal medicine oversight, peptides, BPC-157, KPV, magnesium glycinate, L-theanine, taurine, gut-brain axis, inflammation, graded exposure, zone 2 cardio, heart rate variability, El Paso clinic, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, Dr. Alexander Jimenez, Dr. Maria Guadalupe Cardenas, personal injury care, rehabilitation, functional medicine, sciatica clinic, evidence-based protocols

Integrative Personal Injury Recovery Model and You

Integrative Personal Injury Recovery Model and You

Breaking the “Wait-and-See” Cycle After an Accident: An Integrative Personal Injury Recovery Model

Abstract

After a car accident, many people leave the emergency room with reassuring imaging, instructions to rest, and medications such as nonsteroidal anti-inflammatory drugs (NSAIDs) or muscle relaxants. These treatments may be appropriate for short-term symptom control, but emergency care is mainly designed to identify serious injuries and stabilize the patient. It is not always designed to provide months of musculoskeletal rehabilitation.

If patients continue to have neck pain, back pain, headaches, muscle spasms, numbness, weakness, or limited movement, they may need a more complete evaluation. An integrative personal injury model combines chiropractic care, medical assessment, functional rehabilitation, diagnostic testing, and careful documentation. At Injury Medical Clinic PA in El Paso, Texas, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, works within this multidisciplinary framework with internal medicine physician Dr. Maria Guadalupe Cardenas, MD.

The goal is to move the patient from acute symptom control toward restored movement, measurable function, rehabilitation, and, when possible, maximum medical improvement.

Integrative Personal Injury Recovery Model and You


Why “Wait and See” May Not Be Enough After an Accident

Emergency departments play a critical role after serious accidents. Their first job is to rule out problems such as fractures, internal bleeding, brain injury, spinal instability, or other medical emergencies.

Once the medical team has ruled out immediate danger, they may discharge the patient with medications, rest instructions, and follow-up recommendations.

That does not mean the person has no injury.

Muscles, ligaments, tendons, spinal joints, discs, and nerves can be injured even when there is no fracture. Some accident-related symptoms can also become more noticeable hours or days after the collision.

This is where the “wait-and-see” problem can begin.

A patient may take an NSAID or muscle relaxant, feel somewhat better, and assume that recovery is complete. These medicines can be useful when properly prescribed, but symptom reduction does not automatically mean that normal joint motion, strength, coordination, or soft-tissue function has returned.

Delayed evaluation can also create problems with medical documentation. Personal injury resources consistently note that long gaps between the accident and treatment can make it harder to establish a clear timeline showing when symptoms began and how the condition changed (Farahi Law Firm, 2025; Integrated Health & Injury Center, n.d.).

The better question is not simply:

“Does it still hurt?”

It is:

“Has the injured area returned to normal function?”


A Rapid Multimodal Personal Injury Examination

A more complete post-accident evaluation looks beyond a single pain score.

Dr. Jimenez describes an integrative examination as looking at several parts of the injury at the same time, including:

  • Range of motion
  • Spinal and extremity joint movement
  • Muscle guarding and spasm
  • Soft-tissue tenderness
  • Neurological findings
  • Strength
  • Balance
  • Posture
  • Numbness or tingling
  • Functional movement
  • Ability to sit, stand, walk, lift, drive, sleep, or work
  • Need for imaging or specialist referral

In his published clinical observations, Dr. Jimenez notes that accident injuries often involve several connected problems rather than one isolated painful structure. Joint restriction, muscle guarding, nerve irritation, inflammation, altered movement, stress, and poor sleep may occur together (Jimenez, 2026a).

These clinical observations should not be confused with controlled research studies. However, they help explain the reasoning behind a multimodal examination: treatment should be based on what is actually limiting the patient rather than simply treating the location where pain is felt.


Where Integrative Chiropractic Care Fits

Chiropractic care can provide an important mechanical part of the recovery plan.

Following trauma, the neck, lower back, pelvis, shoulders, and other joints may not move normally. Muscles may tighten to protect the injured area. Patients may also change the way they walk, sit, turn, or bend because movement hurts.

Integrative chiropractic care may include:

  • Chiropractic adjustments or joint mobilization
  • Soft-tissue treatment
  • Flexibility work
  • Corrective exercise
  • Neuromuscular retraining
  • Spinal decompression or traction when appropriate
  • Postural retraining
  • Progressive strengthening
  • Functional rehabilitation

Research supports active rehabilitation as an important part of whiplash recovery. A 2024 systematic review found that guided neck-specific exercise produced greater improvements in neck pain and disability than comparison programs, particularly when treatment continued for more than six weeks (Muñoz Lazcano et al., 2024).

A 2025 randomized clinical trial also reported that appropriately selected cervical manipulation produced outcomes comparable in several areas to a conventional rehabilitation program in patients with acute grade II whiplash (Parera-Turull et al., 2025).

The key is appropriate patient selection. Chiropractic treatment should follow examination and screening for fractures, instability, neurological emergencies, vascular concerns, or other red flags.


The Advantage of Dr. Jimenez’s DC and FNP-BC Background

Dr. Alexander Jimenez practices with credentials that include Doctor of Chiropractic and board-certified Family Nurse Practitioner qualifications.

Clinic information lists his NPI as 1205907805 and identifies active chiropractor and family nurse practitioner taxonomies.

This dual background allows an injury to be considered through two related viewpoints.

The chiropractic viewpoint asks:

  • How are the joints moving?
  • Is spinal motion restricted?
  • Are muscles guarding?
  • Is posture altered?
  • Is nerve irritation affecting function?
  • What movements need to be restored?

The advanced-practice medical viewpoint can consider:

  • General medical status
  • Medication use
  • Neurological symptoms
  • Metabolic conditions
  • Need for laboratory testing
  • Imaging
  • Medical referrals
  • Contraindications
  • Broader health problems that may affect recovery

Nurse practitioners also commonly perform physical examinations, develop treatment plans, coordinate care, order appropriate diagnostic testing within their scope, and refer patients to other medical specialists when needed (Jimenez, 2025).

Instead of one office managing musculoskeletal mechanics and another managing medical concerns, an integrated model can make communication easier.


Medical Direction From Dr. Maria Guadalupe Cardenas

Dr. Jimenez also works with Dr. Maria Guadalupe Cardenas, MD, at Injury Medical Clinic PA in El Paso.

Clinic materials identify Dr. Cardenas as a board-certified internal medicine physician with more than 40 years of medical experience who serves as medical director and collaborative physician. Her NPI number is 1164426749, and her Texas medical license number is J2933.

Within the clinic model, Dr. Cardenas provides internal medicine oversight alongside Dr. Jimenez’s chiropractic, rehabilitation, functional medicine, and injury-care work.

This multidisciplinary structure can help when a patient also has:

  • Diabetes
  • Hypertension
  • Cardiovascular concerns
  • Medication interactions
  • Chronic medical illnesses
  • Inflammatory disorders
  • Age-related risks
  • Abnormal laboratory findings
  • Symptoms requiring additional medical investigation

The goal is not for one discipline to replace another. Each professional should work within the appropriate scope while sharing information.


Looking Beyond Pain: Functional Impairment Mapping

One of the most valuable parts of personal injury treatment is measuring function.

Pain is important, but pain scores alone do not tell the whole story.

A patient may report that pain fell from an 8/10 to a 4/10 but still be unable to:

  • Turn the head safely while driving
  • Sit through a workday
  • Lift normal household objects
  • Sleep through the night
  • Bend forward
  • Walk normally
  • Exercise
  • Carry a child
  • Return to work

These limitations matter clinically.

They also create measurable treatment goals.

Thorough personal injury documentation commonly includes the initial examination, imaging when necessary, diagnosis, treatment plan, progress notes, objective measurements, and descriptions of how injuries affect work and everyday activities (Integrated Health & Injury Center, n.d.; Jimenez, 2026b).


Why SOAP Notes Matter After an Accident

Detailed SOAP notes can help organize the patient’s progress.

S — Subjective

What is the patient reporting?

Pain, headaches, stiffness, numbness, sleep problems, driving difficulty, work limitations, or other symptoms.

O — Objective

What can be measured?

Range of motion, orthopedic tests, neurological findings, strength, tenderness, posture, gait, imaging findings, and functional testing.

A — Assessment

What does the clinician believe is happening?

This includes diagnoses, clinical changes, response to care, new findings, and barriers to recovery.

P — Plan

What happens next?

Treatment, rehabilitation, imaging, referrals, exercise progression, additional testing, and changes in care may be needed.

Over time, these records create a medical timeline showing how the patient moved from the original injury toward recovery.

Thorough documentation should never exaggerate an injury simply because a legal claim exists. Treatment should be based on examination findings, diagnosis, medical necessity, patient response, and measurable progress (Jimenez, 2026a).


A Three-Phase Personal Injury Recovery Framework

A simple phase system can make complicated treatment easier to understand.

These time periods are guidelines, not guarantees. A mild strain and a major disc or neurological injury will not recover at the same speed.

Phase 1: Days 1–14 — Acute Pain and Protection

The early goals are to:

  • Identify serious injuries
  • Establish a baseline examination
  • Control pain and muscle guarding
  • Protect injured tissues
  • Maintain safe movement
  • Document functional losses
  • Decide whether imaging is needed
  • Begin gentle rehabilitation when appropriate

Treatment intensity depends on the diagnosis.

The goal is not aggressive treatment. It is safe evaluation, symptom control, and preservation of function.


Phase 2: Weeks 3–8 — Stabilization and Tissue Recovery

Once acute symptoms begin to settle, treatment can shift toward rebuilding function.

This stage may include:

  • Chiropractic mechanical care
  • Progressive mobility
  • Strengthening
  • Stability exercises
  • Soft-tissue rehabilitation
  • Laser or photobiomodulation therapy when appropriate
  • Functional medicine support
  • Nutrition and recovery strategies

Laser therapy has been studied for musculoskeletal neck pain. Reviews suggest that photobiomodulation and high-intensity laser treatment may reduce pain or disability in selected patients, although results depend on diagnosis, dosage, and treatment protocol (Cidral-Filho et al., 2024; de la Barra Ortiz et al., 2024).

What About Regenerative Therapies?

Selected patients may also be evaluated for therapies such as platelet-rich plasma or other orthobiologic procedures.

These treatments are not automatically appropriate for every accident injury. Their evidence varies greatly depending on the joint, tendon, ligament, diagnosis, severity, and technique used.

Consider them only after proper diagnosis and medical evaluation.


Peptide Therapy Requires Extra Caution

Peptides are sometimes promoted as “tissue-rebuilding” treatments.

This area needs careful medical language.

Some peptide products being marketed for musculoskeletal recovery remain experimental and do not have established FDA approval for treating accident-related soft-tissue injuries.

For example, the FDA currently identifies substances such as BPC-157 and CJC-1295 as having limited human safety information and potential safety concerns. The agency has also raised safety concerns about compounded injectable ipamorelin.

Therefore, peptide use should not be described as proven tissue regeneration.

When considered at all, it requires appropriate medical supervision, informed consent, careful sourcing, regulatory review, and discussion of the limits of current evidence.


Phase 3: Week 8 and Beyond — Functional Rehabilitation

Later-stage recovery focuses less on passive pain relief and more on performance.

Patients may work toward:

  • Full or improved range of motion
  • Better strength
  • Improved spinal stability
  • Normal walking patterns
  • Safer lifting
  • Better balance
  • Work conditioning
  • Return to exercise
  • Reduced dependence on passive treatments
  • Independence with home rehabilitation

Research on whiplash supports exercise-based rehabilitation as part of improving pain and disability, although the strength of evidence varies among programs (Teasell et al., 2021; Muñoz Lazcano et al., 2024).


Moving Toward Maximum Medical Improvement

Maximum medical improvement, or MMI, does not simply mean that eight weeks have passed.

MMI generally means the condition has recovered or stabilized to the point where major additional improvement is not expected with further treatment.

For some patients, this may happen relatively quickly.

For others, it may take months.

Patients with disc injury, neurological involvement, significant joint trauma, surgery, chronic pain, or multiple injuries may require much longer rehabilitation.

Functional restoration and objective measurement are important when deciding whether a patient has reached a stable endpoint (Gelfman & Hill, 2019).

That is why MMI should be based on the patient’s actual recovery, not an arbitrary calendar date.


The Goal: From Pain Relief to Measurable Recovery

The strongest personal injury healthcare model is not built around producing more treatment.

It is built around producing the right treatment.

A coordinated El Paso injury-care model can bring together:

  • Chiropractic care
  • Internal medicine oversight
  • Advanced practice nursing
  • Personal injury evaluation
  • Functional medicine
  • Rehabilitation
  • Diagnostic imaging
  • Objective functional testing
  • Carefully selected advanced therapies
  • Medical-legal documentation
  • Specialist referrals when needed

Dr. Jimenez’s clinical philosophy emphasizes looking at structure, movement, nervous-system function, rehabilitation, lifestyle, and systemic health together rather than treating them as unrelated problems (Jimenez, 2026a).

Working alongside Dr. Cardenas provides an additional internal medicine layer for medical oversight and complex health concerns.

For an injured patient, the central goal remains simple:

Find the injury, document it accurately, restore as much function as possible, and follow measurable progress until the patient reaches a stable recovery point.

That approach replaces passive “wait and see” care with a structured path from injury → assessment → stabilization → rehabilitation → functional recovery → MMI.

Why Choose Chiropractic? | El Paso, Tx (2023)

References

Cidral-Filho, F., et al. (2024). Photobiomodulation on shoulder and neck pain and disability: A comprehensive review. Lasers in Medical Science. Photobiomodulation on Shoulder and Neck Pain and Disability

de la Barra Ortiz, H. A., Arias, M., & Liebano, R. E. (2024). A systematic review and meta-analysis of randomized controlled trials on the effectiveness of high-intensity laser therapy in the management of neck pain. Lasers in Medical Science, 39, 124. High-Intensity Laser Therapy in the Management of Neck Pain

Farahi Law Firm. (2025, February 18). 5 ways a delay in treatment can devalue your injury case. 5 Ways a Delay in Treatment Can Devalue Your Injury Case

Gelfman, R., & Hill, J. J., III. (2019). Rehabilitating the injured/ill worker to maximum medical improvement (MMI). Physical Medicine and Rehabilitation Clinics of North America, 30(3), 657–669. Rehabilitating the Injured/Ill Worker to Maximum Medical Improvement

Integrated Health & Injury Center. (n.d.). How chiropractic documentation strengthens your personal injury case. How Chiropractic Documentation Strengthens Your Personal Injury Case

Jimenez, A. (2026a, May 5). Integrative chiropractic care for personal injury and work injury recovery in El Paso. LinkedIn. Integrative Chiropractic Care for Personal Injury and Work Injury Recovery in El Paso

Jimenez, A. (2026b, June 3). Why personal injury attorneys look for integrative chiropractic clinics after motor vehicle accidents. LinkedIn. Why Personal Injury Attorneys Look for Integrative Chiropractic Clinics After Motor Vehicle Accidents

Jimenez, A. (2026). Integrative chiropractic for personal injury recovery success. Personal Injury Doctor Group. Integrative Chiropractic for Personal Injury Recovery Success

Jimenez, A. (2026). Integrative chiropractic and regenerative therapies benefits. Personal Injury Doctor Group. Integrative Chiropractic and Regenerative Therapies Benefits

Jimenez, A. (n.d.). Chiropractic and nurse practitioner care after accidents. El Paso Back Clinic. Chiropractic and Nurse Practitioner Care After Accidents

Jimenez, A. (n.d.). Integrative chiropractic clinics help personal injury claims. El Paso Back Clinic. Integrative Chiropractic Clinics Help Personal Injury Claims

Muñoz Lazcano, P., Rojano Ortega, D., & Fernández López, I. (2024). Effects of a guided neck-specific exercise therapy on recovery after a whiplash: A systematic review and meta-analysis. American Journal of Physical Medicine & Rehabilitation. Effects of Guided Neck-Specific Exercise Therapy After Whiplash

Parera-Turull, J., et al. (2025). The effects of cervical manipulation compared with a conventional physiotherapy program for patients with acute whiplash injury: A randomized controlled trial. Healthcare, 13(7), 710. Cervical Manipulation Compared With Physiotherapy for Acute Whiplash

U.S. Food and Drug Administration. (2026). Certain bulk drug substances for use in compounding that may present significant safety risks. FDA: Certain Bulk Drug Substances That May Present Safety Risks

Women’s Hormonal Health: Testosterone Deficiency Explained

Explore the link between women’s hormonal health and testosterone deficiency. Find ways to manage and improve your wellness.

Abstract

This educational post explores the often-misunderstood and under-diagnosed issue of testosterone deficiency in women. For too long, symptoms like fatigue, depression, weight gain, and low libido have been dismissed as inevitable consequences of aging. However, a growing body of evidence, which we will explore in detail, reveals that these are often hallmark signs of hormonal imbalance, specifically low testosterone. I am Dr. Alex Jimenez, and in this comprehensive guide, I will walk you through the critical role testosterone plays in female health, drawing from the latest findings of leading researchers and my clinical experience. We will dissect the physiological pathways of testosterone production, differentiate between primary and secondary hypogonadism, and uncover the root causes—from ovarian failure to the intricate interplay of stress, thyroid function, and metabolic health. This journey will empower you to understand your body, advocate for proper testing, and explore effective, evidence-based treatment strategies.

At Injury Medical Clinic PA in El Paso, Texas, we champion an integrative, multidisciplinary approach. This post will also show how we deliver comprehensive patient care through the unique collaboration between me, Dr. Alexander Jimenez (DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST), and our esteemed Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas, a Board-Certified Internist with over four decades of experience (NPI #1164426749, Texas MD License #J2933), provides essential medical oversight, ensuring our diagnostic and treatment protocols meet the highest standards of care. Together, we integrate functional medicine, integrative chiropractic care, medical diagnostics, and personalized rehabilitation to address the whole person, not just their symptoms. We will discuss how this collaborative model is uniquely positioned to manage complex conditions like hormone deficiencies, providing a seamless blend of medical precision and holistic healing. By the end of this post, you will have a deep understanding of female testosterone deficiency and a clear roadmap toward reclaiming your vitality.

The Misunderstood Hormone: Debunking Myths About Testosterone in Women

As a clinician with dual credentials in chiropractic and advanced practice nursing, specializing in functional medicine, I have dedicated my career to uncovering the root causes of chronic symptoms that diminish quality of life. One of the most pervasive and damaging misconceptions I encounter daily in my practice revolves around testosterone and its role in women’s health. For far too long, the narrative has been that testosterone is exclusively a “male” hormone, and its presence in women is either insignificant or problematic. This could not be further from the truth.

It is a clinical reality that breaks my heart: countless women enter my office feeling utterly defeated. They describe a constellation of symptoms—crippling fatigue, a persistent low mood or depression, a complete loss of libido, unexplained weight gain despite their best efforts, and a noticeable decline in muscle mass and physical strength. They have often seen multiple doctors, only to be told this is just “part of getting older.” Many are handed a prescription for an antidepressant and advised to “age gracefully.” This advice is not only dismissive but also scientifically unsound. It is a profound disservice to women who are suffering not from a primary psychiatric disorder, but from a tangible, measurable, and, most importantly, treatable hormone deficiency.

The notion that women should accept a decline in vitality as an inevitable part of aging is a lie. My wife is 46 years old, and through a proactive, evidence-based approach to hormone optimization, she looks and functions with the energy and vitality of someone in her mid-twenties. I am not just her husband; I am her doctor, and I apply the same rigorous scientific principles to her care as I do for every patient who walks through my doors. The knowledge and tools to reverse this decline are not hidden; they are readily available in published research and clinical playbooks. My mission is to bring this information to light.

Women produce testosterone, and they always have. It is an essential biological component for optimal female health. The idea that hormones are “complicated” is often used as a shield to mask a lack of understanding or an unwillingness to investigate deeper. In reality, the physiology is elegant and comprehensible. By understanding how and why testosterone works in the female body, we can move from a place of passive acceptance to one of proactive empowerment. This post is your first step on that journey.

The Vital Roles of Testosterone in Female Physiology

Testosterone in women is not a biological accident; it is a cornerstone of health and well-being. Its influence extends far beyond the bedroom, touching nearly every system in the body. To truly grasp why its deficiency can be so devastating, we must first appreciate its multifaceted functions. The production of this vital hormone is a beautifully orchestrated process involving multiple organs working in concert.

Where Does Female Testosterone Come From?

The female body manufactures testosterone through a distributed network of endocrine tissues. This decentralized production system highlights its systemic importance. Here is the breakdown:

  • The Ovaries (50%): The primary producers of testosterone in premenopausal women are the theca cells of the ovaries. This production is closely linked to the menstrual cycle and regulated by signals from the brain.
  • The Adrenal Glands (25%): Situated atop the kidneys, the adrenal glands produce precursor hormones like dehydroepiandrosterone (DHEA) and androstenedione, which are then converted into testosterone. This pathway becomes increasingly important after menopause when ovarian function declines.
  • Peripheral Tissues (25%): The remaining portion of a woman’s testosterone is synthesized in what are known as peripheral tissues. This “local” production occurs in fat (adipose tissue), skin, and muscle cells, which convert adrenal androgens into active testosterone. This localized conversion allows tissues to fine-tune their own hormonal environment.

This distributed production model means that a disruption in any one of these areas—be it ovarian health, adrenal function, or metabolic status—can impact a woman’s overall testosterone levels.

Testosterone’s Systemic Impact: More Than Just Libido

While testosterone is most famous for its role in sexual desire, its job description is far more extensive. As confirmed in a pivotal 2021 publication in The Lancet Diabetes & Endocrinology, testosterone deficiency in women is not merely correlated with poor health outcomes; it is independently associated with them. This is a crucial distinction. A correlation means two things happen together; an association implies a direct, causal link. Let’s explore these critical functions in detail.

  • Sexual Health and Libido: This is perhaps the most well-known function. Testosterone is the primary driver of libido, or sex drive, in both men and women. It acts on neural circuits in the brain, particularly in the hypothalamus and limbic system, to promote sexual desire, arousal, and fantasy. Low testosterone is a leading cause of Hypoactive Sexual Desire Disorder (HSDD), a condition that can cause significant personal and relational distress.
  • Bone Density and Skeletal Health: Testosterone plays a crucial role in maintaining strong, healthy bones. It works in synergy with estrogen to regulate the continuous process of bone remodeling—the breakdown of old bone (resorption) and the formation of new bone (ossification). Testosterone directly stimulates osteoblasts, the cells responsible for building new bone matrix, and it inhibits the activity of osteoclasts, the cells that break bone down. The Lancet study unequivocally linked low testosterone to decreased bone mineral density, increasing a woman’s risk for osteopenia and osteoporosis, especially after menopause when both estrogen and testosterone levels plummet.
  • Lean Muscle Mass and Metabolic Rate: Testosterone is a powerful anabolic hormone, meaning it promotes tissue building, particularly muscle. It stimulates muscle protein synthesis, helping women build and maintain lean muscle mass. This is vital not only for physical strength and mobility but also for metabolic health. Muscle is a highly metabolically active tissue; the more lean muscle a person has, the higher their basal metabolic rate (BMR), which is the number of calories the body burns at rest. A decline in testosterone leads to sarcopenia (age-related muscle loss), which in turn lowers the BMR, making it easier to gain fat and harder to lose weight.
  • Cognitive Function and Mental Sharpness: The brain is rich in androgen receptors. Testosterone has profound neuroprotective and neurotrophic effects, meaning it protects brain cells and supports their growth and connectivity. It is particularly active in brain areas responsible for memory, spatial ability, and executive function. Women with low testosterone often report “brain fog,” difficulty concentrating, and memory lapses. Optimizing testosterone levels can enhance cognitive sharpness, focus, and verbal memory.
  • Mood Stability and Psychological Well-being: Testosterone modulates key neurotransmitters, including serotonin, dopamine, and GABA, which are critical for mood regulation. It has a natural mood-stabilizing and anti-anxiety effect. When levels are low, it can contribute to feelings of depression, irritability, and a general lack of motivation or “zest for life.” This is why misdiagnosing testosterone deficiency as simple depression and prescribing an SSRI (which can further suppress libido) is so problematic—it fails to address the underlying hormonal cause.
  • Energy and Vitality: Testosterone is fundamental to our sense of energy and drive. It supports the production of red blood cells (erythropoiesis), which carry oxygen to all our tissues, including our muscles and brain. Better oxygenation means better cellular energy production. Clinically, one of the first and most dramatic improvements patients report after starting testosterone therapy is a significant boost in energy and a reduction in chronic fatigue.
  • Cardiovascular Health: Emerging research suggests a protective role for testosterone in the cardiovascular system. It helps maintain blood vessel health by promoting vasodilation (the widening of arteries), which can help regulate blood pressure. It may also improve cholesterol profiles and reduce inflammation, a key driver of atherosclerotic plaque formation.

Understanding this wide-ranging impact is the first step. When a woman presents with depression, fatigue, and weight gain, a perceptive clinician should see these not as isolated issues, but as potential signals of a systemic hormonal imbalance rooted in testosterone deficiency.

Our Integrative Approach at Injury Medical Clinic PA

At Injury Medical Clinic PA, we have built a practice model founded on collaboration and a shared vision of patient-centered care. We recognize that the human body is a complex, interconnected system and that true healing requires a multidisciplinary approach that transcends the traditional silos of medicine. This philosophy is embodied in the professional partnership between me, Dr. Alex Jimenez, and our Medical Director, Dr. Maria Guadalupe Cardenas, MD.

The Synergy of Chiropractic, Functional Medicine, and Internal Medicine

My background provides a unique clinical lens. As a Doctor of Chiropractic (DC), my training is rooted in the body’s biomechanical and neurological integrity. As an Advanced Practice Registered Nurse (APRN) and Board-Certified Family Nurse Practitioner (FNP-BC), I have the diagnostic and prescriptive authority to manage a wide range of medical conditions. My certifications as a Certified Functional Medicine Practitioner (CFMP) and an Institute for Functional Medicine Certified Practitioner (IFMCP) also drive my commitment to identifying and treating the root causes of disease.

This multifaceted expertise is powerfully complemented by Dr. Maria Guadalupe Cardenas’s profound experience. As a Board-Certified Internist with over 40 years of practice, Dr. Cardenas brings an exhaustive knowledge of pathophysiology, pharmacology, and the complexities of internal medicine. Her role as our Medical Director and Collaborative Physician is not a mere formality; it is the cornerstone of our integrative model. This structure, where an MD provides medical direction and oversight for a clinic led by a chiropractor and nurse practitioner, is common in cutting-edge integrative and injury care settings. It ensures our patients receive the best of all worlds: holistic, root-cause-oriented care grounded in the rigorous standards and diagnostic precision of conventional medicine.

How Our Team Works Together for You

When a patient comes to us with symptoms suggestive of testosterone deficiency, our collaborative process begins immediately.

  1. Comprehensive Initial Assessment: The patient journey starts with a deep-dive consultation. This is not a 10-minute visit. We spend time listening to the patient’s story, mapping out their symptom timeline, and understanding their health history, lifestyle, and goals. I may conduct a detailed physical examination, assessing biomechanical function, neurological status, and functional movement patterns, while also considering the clinical signs of hormonal imbalance.
  2. Advanced Diagnostic Workup: Based on the initial assessment, we order comprehensive lab panels. This goes far beyond a simple “total testosterone” level. Under Dr. Cardenas’s medical oversight, we ensure the diagnostic workup is thorough and medically appropriate. This includes measuring total and free testosterone, SHBG, LH, FSH, a complete thyroid panel, adrenal markers like DHEA-S and cortisol, prolactin, and metabolic markers. Dr. Cardenas reviews the lab requisitions and results, providing her internist’s perspective on any confounding variables or comorbidities to consider.
  3. Integrative Diagnosis and Care Plan Development: Once the results are in, Dr. Cardenas and I confer. We synthesize the patient’s subjective story, my clinical findings, and the objective lab data. Is this a clear case of ovarian failure? Is it a secondary issue driven by stress or thyroid dysfunction? Does the patient also have underlying insulin resistance or gut inflammation that needs to be addressed? This collaborative diagnosis allows us to build a truly holistic and personalized treatment plan.
  4. Multimodal Treatment Implementation: The care plan leverages our combined expertise:
    • Medical Management (Overseen by Dr. Cardenas): If Hormone Replacement Therapy (HRT), including exogenous testosterone, is indicated, it is prescribed under the guidance and medical authority established by our collaborative practice agreement. Dr. Cardenas ensures the choice of therapy, dosing, and monitoring protocols meet the highest medical safety and efficacy standards.
    • Functional Medicine Interventions (Led by Dr. Jimenez): We simultaneously address the “why.” If lab work points to high stress, we support the HPA axis with adaptogenic herbs, targeted nutrients, and lifestyle coaching. If thyroid function is suboptimal, we use nutritional strategies and cofactors to support thyroid hormone production and conversion. We use dietary interventions, nutraceuticals, and gut-healing protocols to correct metabolic dysfunction or inflammation.
    • Integrative Chiropractic Care (Provided by Dr. Jimenez): The body’s structure and function are inextricably linked. Chronic stress and hormonal imbalances often manifest as musculoskeletal tension, spinal misalignments, and neurological interference. Chiropractic adjustments can help regulate the autonomic nervous system, moving the body from a “fight-or-flight” sympathetic state to a “rest-and-digest” parasympathetic state. This is crucial for lowering cortisol and supporting HPA axis function. By improving spinal alignment and nerve flow, we enhance the brain-body communication necessary for proper hormone regulation.
    • Rehabilitation and Lifestyle Coaching: Our team includes rehabilitation specialists who design personalized exercise programs. These focus not just on general fitness, but on building lean muscle to improve metabolic rate and insulin sensitivity, key components of hormonal health. We provide detailed guidance on nutrition, stress management techniques like meditation and breathwork, and sleep hygiene.

This seamless integration of medical oversight, functional medicine investigation, and chiropractic care allows us to provide a level of comprehensive treatment that isn’t possible in a conventional, single-specialty setting. We don’t just replace a hormone; we rebuild the foundations of health so the body can regulate itself more effectively.

Diagnosing the “Why”: Primary vs. Secondary Hypogonadism

When a woman’s testosterone is low, the diagnosis is broadly termed hypogonadism. However, labeling the condition is not enough. It is like saying a car won’t start without asking if the problem is a dead battery or an empty gas tank. To treat effectively, we must understand why the testosterone is low. In my clinical practice, I see a concerning trend where the term “hypogonadism” is used generically, leading to one-size-fits-all treatment that often fails. There are two distinct types of hypogonadism, each with a different cause and a different management strategy.

Primary Hypogonadism: A Factory Problem

Primary hypogonadism is a problem with the “factory” itself—the ovaries. In this scenario, the ovaries have lost their ability to produce hormones, including testosterone and estrogen, despite receiving the correct signals from the brain. Think of it as a factory with broken machinery. The management team (the brain) is shouting instructions, but no one on the factory floor can hear or respond.

The Hormonal Signature:

The brain, specifically the pituitary gland, senses the low levels of ovarian hormones in the blood. To stimulate the failing ovaries, it ramps up production of signaling hormones. The key hormonal markers for primary hypogonadism are:

  • Low Testosterone and Estrogen: The ovarian output is minimal.
  • High Luteinizing Hormone (LH) and Follicle-Stimulating Hormone (FSH): These are the pituitary’s signaling hormones. The brain is screaming at the ovaries to work, so LH and FSH levels will be sky-high.

Common Causes of Primary Hypogonadism:

  • Menopause: This is the most common cause. It is the natural, programmed cessation of ovarian function, typically occurring around age 51.
  • Surgical Menopause: The surgical removal of the ovaries (oophorectomy), often performed during a hysterectomy for conditions like endometriosis or cancer, induces immediate and severe primary hypogonadism.
  • Premature Ovarian Insufficiency (POI): Sometimes called premature ovarian failure, this is a condition where the ovaries stop functioning before the age of 40. It can have autoimmune, genetic, or unknown causes.
  • Ovarian Damage: Treatments like chemotherapy or radiation for cancer can damage ovarian tissue, leading to a loss of function.
  • Oophoritis: A rare condition involving inflammation of the ovaries, often due to an autoimmune attack, which can impair their ability to produce hormones.

The Treatment Solution for Primary Hypogonadism:

When the factory is permanently broken, there is no way to fix the machinery. The signal from the brain is fine, but the receiver is cooked. The only logical and effective solution is to provide the hormones that the body can no longer make. This is exogenous hormone replacement.

The treatment plan for primary hypogonadism is direct and clear:

Hormone Replacement Therapy (HRT): This involves replacing both estrogen and progesterone (if the woman has a uterus) to manage menopausal symptoms and protect long-term health. Crucially, it must also include testosterone replacement. Omitting testosterone ignores a huge piece of the puzzle.

Supportive Cofactors and Peptides: We also support this therapy with nutritional cofactors necessary for hormone metabolism and may use specific peptides (small protein signaling molecules) that can help improve cellular sensitivity to the hormones being administered.

For primary hypogonadism, attempting to “boost” the ovaries is futile. The focus must be on safe and effective replacement to restore physiological balance.

Secondary Hypogonadism: An Upstream Communication Breakdown

Secondary hypogonadism is a completely different beast. Here, the ovaries (the factory) are perfectly healthy and capable of producing hormones. The problem lies upstream, in the brain’s command-and-control centers: the hypothalamus and the pituitary gland. “Management” is essentially offline.

The hypothalamus fails to release Gonadotropin-Releasing Hormone (GnRH) in its normal, pulsatile fashion. Without this top-level command, the pituitary gland does not receive the signal to release its own hormones, LH and FSH. Consequently, the ovaries never get the message to produce estrogen and testosterone. It’s like a fully functional factory sitting idle because the head office never sent the day’s production orders.

The Hormonal Signature:

The lab results for secondary hypogonadism paint a very different picture from primary:

  • Low Testosterone and Estrogen: Like primary, the end product is low.
  • Low or Inappropriately Normal LH and FSH: This is the key differentiator. Instead of being high (as the brain would command if it sensed a problem), the pituitary signals are low or absent. The entire hormonal axis, from the top down, is suppressed.

The Critical Question: Why is the Brain Offline?

Herein lies the most important part of diagnosing secondary hypogonadism. Simply replacing testosterone without asking why the hypothalamus-pituitary axis has shut down is a clinical error. It’s like jump-starting the car every morning without ever checking why the alternator isn’t charging the battery. You are treating the symptom (low testosterone) but ignoring the root cause, which means you will never achieve true health and will likely continue to feel unwell.

As a functional medicine practitioner, this is where my investigation begins. We must peel back the layers to find the source of the upstream dysfunction. Here are the most common culprits I see in my clinical practice at Injury Medical Clinic.

Uncovering the Root Causes of Secondary Hypogonadism

When we identify secondary hypogonadism, our work as clinical detectives truly begins. The low hormone levels are merely the downstream effect of an upstream problem. At Injury Medical Clinic, our integrative team focuses on a systematic investigation to pinpoint and address these root causes. Treating the source is the only path to sustainable recovery. Here are the key areas we investigate.

1. Thyroid Dysfunction: The Metabolic Master Regulator

The first place I always look when I see a profile of secondary hypogonadism is thyroid function. The thyroid gland governs the body’s metabolic rate and energy production, and its influence on the reproductive axis is profound. The relationship is complex and bidirectional.

A common scenario is subclinical hypothyroidism, where the TSH (Thyroid-Stimulating Hormone) is elevated, but T4 and T3 levels may still be within the “normal” lab range. An elevated TSH signals that the brain is working harder to stimulate a sluggish thyroid. This elevated TSH has a direct and detrimental effect on testosterone availability.

The SHBG Connection:

Elevated TSH signals the liver to increase its production of Sex Hormone-Binding Globulin (SHBG). SHBG is a protein that circulates in the bloodstream and acts like a “hormone sponge.” Its primary job is to bind to sex hormones, including testosterone and estrogen, rendering them biologically inactive.

Think of it this way:

  • Total Testosterone: This lab value measures all the testosterone in your bloodstream—both the testosterone that is bound to SHBG and the small fraction that is “free.”
  • Free Testosterone: This is the unbound, biologically active testosterone that can actually enter cells, bind to androgen receptors, and carry out its functions (building muscle, enhancing libido, etc.).

When high TSH drives up SHBG levels, a large portion of the total testosterone gets “hoarded” by SHBG. A woman can have a perfectly normal total testosterone level on her lab report, leading an unsuspecting clinician to dismiss her symptoms. However, if her SHBG is sky-high, her free testosterone could be virtually zero. She is hormonally deficient at the cellular level, despite having normal total levels in her blood. Standard, superficial hormone panels miss this critical nuance.

Our Approach:

This is why a comprehensive thyroid panel is non-negotiable in our workup. We never look at TSH. Our panel includes:

  • TSH
  • Free T4 (the inactive storage hormone)
  • Free T3 (the active hormone)
  • Reverse T3 (an inactive metabolite that can block T3 function)
  • Thyroid Antibodies (TPO and TG) to screen for autoimmune thyroid disease (Hashimoto’s).

If we identify thyroid dysfunction, our treatment is multifactorial. We use targeted nutrients like iodine, selenium, zinc, and tyrosine to support thyroid hormone production. We may recommend specific dietary changes to reduce inflammation. Under Dr. Cardenas’s medical guidance, we may initiate prescription thyroid medication (like T4, T3, or desiccated thyroid) if necessary. By optimizing thyroid function, we can lower SHBG, which “un-cages” the free testosterone, often restoring hormonal balance without needing to add exogenous testosterone.

2. The HPA Axis and Chronic Stress: The Pregnenolone Steal

The second major area of investigation is the Hypothalamic-Pituitary-Adrenal (HPA) axis, our central stress response system. In our modern world, many people live in a state of chronic stress, whether from work pressure, relationship issues, financial worries, or even hidden physiological stressors like chronic infections or inflammation.

When the body perceives chronic stress, the HPA axis goes into overdrive, leading to sustained high levels of the stress hormone cortisol. This has a direct and damaging effect on sex hormone production through a phenomenon known as the “pregnenolone steal” or, more accurately, the “cortisol shunt.”

Understanding the Steroid Hormone Cascade:

To understand this, we need to look at the basic flowchart of steroid hormone synthesis. All steroid hormones—cortisol, DHEA, testosterone, estrogen, and progesterone—are made from cholesterol. The pathway looks something like this:

Cholesterol → Pregnenolone → (Multiple pathways)

Pregnenolone is the “mother hormone.” It sits at a critical crossroads. From pregnenolone, the body can go down one of two major pathways:

  1. The Progesterone Pathway: Pregnenolone → Progesterone → (then branches to Cortisol and Aldosterone)
  2. The DHEA Pathway: Pregnenolone → DHEA → (then branches to Testosterone and Estrogen)

Under normal conditions, the body allocates pregnenolone resources down both pathways in a balanced manner.

How the “Steal” Happens:

During chronic stress, survival becomes the body’s number one priority. The adrenal glands pump out large amounts of cortisol to manage the perceived threat. To do this, the enzymatic machinery in the adrenal glands is upregulated to preferentially shunt the available pregnenolone down the pathway toward cortisol production.

This means that the resources (pregnenolone) that would normally be used to produce DHEA—the direct precursor to testosterone—are “stolen” or diverted to make cortisol instead. The body will always prioritize immediate survival (cortisol production) over long-term functions like reproduction and vitality (sex hormone production).

The clinical result is a hormonal profile of:

  • High Cortisol (or dysregulated cortisol, e.g., high at night and low in the morning)
  • Low DHEA
  • Low Testosterone

Why You Can’t Supplement Your Way Out of a Cortisol Problem:

I see many patients who have been told to take DHEA or pregnenolone supplements to fix this. This is a misguided and often ineffective approach. If the underlying driver—chronic stress—isn’t addressed, the body will take the supplemental pregnenolone you provide and keep shunting it toward cortisol production. You are pouring more raw materials into a system that is programmed to divert them.

Our Approach:

The only real solution is to drop the HPA load. This requires a deep, functional medicine approach:

  • Identify and Mitigate Stressors: We work with patients to identify their primary stressors—be they psychological, physiological (like gut infections or food sensitivities), or environmental (like exposure to toxins).
  • Nervous System Regulation: This is where integrative chiropractic care becomes invaluable. Spinal adjustments have been shown to influence the autonomic nervous system directly, helping shift the body out of a sympathetically dominant “fight-or-flight” state and into a parasympathetically dominant “rest-digest-heal” state. This directly lowers the HPA axis burden.
  • Adrenal Support: We use adaptogenic herbs like Ashwagandha, Rhodiola, and Holy Basil, which help the body adapt to stress and modulate cortisol production. We also use targeted nutrients like Vitamin C, B vitamins, and magnesium, which are rapidly depleted during chronic stress.
  • Lifestyle Interventions: We provide coaching on stress-reduction techniques such as mindfulness meditation, breathwork (pranayama), yoga, and ensuring adequate sleep, as sleep deprivation is a massive HPA axis activator.

By restoring balance to the HPA axis, we allow the body to naturally redirect pregnenolone back towards the DHEA and testosterone pathway, restoring hormone levels from the inside out.

3. Severe Caloric Deficits and Overtraining: The Energy Availability Crisis

I am seeing this with increasing frequency in my clinic, particularly with the widespread use of GLP-1 agonist medications (like semaglutide and tirzepatide) for weight loss, as well as the prevalence of extreme dieting and exercise regimens. The underlying issue is one of energy availability.

The hypothalamus, the master gland of the endocrine system, is exquisitely sensitive to the body’s energy status. Its primary directive is to ensure survival. From a biological and evolutionary perspective, functions like reproduction (which includes maintaining a healthy libido and menstrual cycle) and performance (building muscle) are energy-expensive luxuries. The body will not invest in these “luxuries” if it perceives starvation or an energy crisis.

How It Happens:

When a woman is in a severe caloric deficit—either through extreme dieting, the appetite-crushing effects of GLP-1 drugs, or a combination of both—or when she is engaged in excessive exercise without adequate caloric intake (a condition known as Relative Energy Deficiency in Sport, or RED-S), the hypothalamus receives danger signals.

These signals indicate that there is not enough energy to sustain basic life functions and support reproduction. In response, the hypothalamus executes a protective shutdown protocol. It dramatically reduces or completely stops pulsatile GnRH release.

This shutdown has a cascading effect:

  • No GnRH from the hypothalamus means…
  • No LH and FSH from the pituitary, which means…
  • No stimulation of the ovaries, which means…
  • No production of testosterone and estrogen.

This is a classic presentation of hypothalamic amenorrhea in its extreme form. Still, even less severe energy deficits can significantly downregulate the entire HPG axis, leading to secondary hypogonadism. The body is intelligently putting a hold on reproduction and anabolism until the energy crisis is resolved.

Our Approach:

The solution here is not hormones; it is energy. You have to fix the energy issue first.

  • Nutritional Rehabilitation: We work with patients to gradually and safely increase their caloric intake, focusing on nutrient-dense whole foods. We must reassure the hypothalamus that the famine is over. This can be a psychologically challenging process for patients who are afraid of regaining weight, so it requires careful coaching and support.
  • Adjusting Medications: For patients on GLP-1 agonists, we work with their prescribing physician (or, as an APRN, I may manage this myself under Dr. Cardenas’s oversight) to adjust the dose to allow adequate nutritional intake while still leveraging the drug’s metabolic benefits.
  • Smart Training, Not Overtraining: We assess the patient’s exercise regimen. The goal is to move from a catabolic (breaking down) state to an anabolic (building up) state. This often means reducing excessive cardio and incorporating more resistance training to build metabolically active muscle, which itself improves insulin sensitivity and hormonal balance.
  • Chiropractic and Nervous System Support: By calming the sympathetic nervous system, chiropractic care can reduce the body’s overall stress load, making it more resilient to the physiological stress of exercise and caloric repletion.

Fixing secondary hypogonadism requires a thorough, patient, and methodical approach. It is about restoring the body’s fundamental systems—metabolism, stress response, and energy balance. Only then can the endocrine system come back online and function as it was designed.

The Essential Lab Workup: Your Diagnostic Toolkit

You cannot manage what you do not measure. Guesswork has no place in hormone optimization. To accurately diagnose the type of hypogonadism and identify its underlying cause, a specific and comprehensive set of laboratory tests is essential. Many patients come to me frustrated because their previous doctors only ran a “total testosterone” test, saw that it was “normal,” and dismissed their concerns. This is inadequate.

At Injury Medical Clinic, our approach, overseen by Dr. Cardenas, is to gather all the necessary data points to see the full picture of your hormonal symphony. Here is the bare minimum panel I recommend for any woman experiencing symptoms of hormonal imbalance. I will keep a list of these in my social media stories for your reference.

The Foundational Hormone Panel

This core set of tests evaluates the entire Hypothalamic-Pituitary-Gonadal (HPG) axis from top to bottom.

  • Total Testosterone: This measures the total amount of testosterone in the bloodstream, including both bound and free forms. While not the whole story, it is an important starting point.
  • Free Testosterone: This is the most critical marker for androgen status. It measures the unbound, biologically active testosterone that is available to your cells. A woman can have normal total testosterone but debilitating symptoms if her free testosterone is low.
  • Sex Hormone-Binding Globulin (SHBG): This is the “hormone sponge” we discussed earlier. Measuring SHBG is crucial for context. If SHBG is high, it will bind up more testosterone, leading to low free testosterone. We need to know this value to understand the relationship between total and free levels.
  • Luteinizing Hormone (LH) and Follicle-Stimulating Hormone (FSH): These are the signaling hormones from the pituitary gland. They are the key to differentiating between primary and secondary hypogonadism.
    • High LH/FSH + Low Testosterone = Primary Hypogonadism (Ovarian failure)
    • Low or Normal LH/FSH + Low Testosterone = Secondary Hypogonadism (Brain/Pituitary issue)
  • Prolactin: This hormone is produced by the pituitary gland. Elevated prolactin levels (hyperprolactinemia) can be caused by stress, certain medications, or a benign pituitary tumor (prolactinoma). High prolactin directly suppresses GnRH, leading to secondary hypogonadism. It is a critical and often-overlooked cause of low libido and hormonal dysfunction.
  • DHEA-Sulfate (DHEA-S): This is a stable marker of adrenal androgen production. Low DHEA-S often signals adrenal fatigue or the “pregnenolone steal” phenomenon, pointing to HPA axis dysfunction as a root cause.

The Comprehensive Thyroid Panel

As discussed, thyroid function is inextricably linked to sex hormone balance. A simple TSH test is not enough.

  • TSH (Thyroid-Stimulating Hormone): The pituitary’s signal to the thyroid. We look for the optimal range (typically 0.5-2.0 mIU/L), not just the broad “normal” lab range.
  • Free T4 (Thyroxine): The main storage form of thyroid hormone.
  • Free T3 (Triiodothyronine): The active thyroid hormone that drives metabolism. Low T3 is a common cause of persistent hypothyroid symptoms.
  • Reverse T3 (rT3): An inactive form of T3 that can block T3 receptors. High rT3 is often seen in states of chronic stress, inflammation, or caloric restriction, indicating a problem with the conversion of T4 to active T3.
  • Thyroid Peroxidase Antibodies (TPOAb) and Thyroglobulin Antibodies (TgAb): These markers help diagnose Hashimoto’s thyroiditis. This autoimmune condition is the most common cause of hypothyroidism in the United States.

Additional Metabolic and Inflammatory Markers

To complete the functional picture, we often include these markers to assess for other potential root causes.

  • Fasting Insulin and Glucose: To calculate HOMA-IR, a marker of insulin resistance. Insulin resistance is a major driver of hormonal imbalance, particularly Polycystic Ovary Syndrome (PCOS), which can present with high androgens. Still, it also creates systemic inflammation that can disrupt the HPG axis.
  • Hemoglobin A1c (HbA1c): A 3-month average of blood sugar control.
  • High-Sensitivity C-Reactive Protein (hs-CRP): A sensitive marker of systemic inflammation. Chronic inflammation is a physiological stressor that can dysregulate the HPA axis and suppress hormonal function.
  • Complete Blood Count (CBC) and Iron Panel (including Ferritin): To screen for anemia and iron deficiency. Low iron (ferritin) is a common non-hormonal cause of fatigue and hair loss and can stress the body in ways that affect the HPA axis.

By assembling this complete dataset, we move beyond guessing and into precision, evidence-based medicine. Interpreted in the context of your unique symptoms and history, the results of these tests give us a clear roadmap. They tell us not only what is wrong but why, allowing us to design a targeted, effective, and personalized treatment plan that addresses the root cause of your suffering.

Your Path to Reclaiming Vitality: A Call to Action

The message I want to leave you with is one of hope and empowerment. The symptoms you are experiencing—the fatigue, the depression, the weight gain, the lost libido—are not a personal failing or an inevitable sentence of aging. They are real, measurable physiological signals that something is out of balance in your body. That is a lie you no longer have to accept.

My wife, at 46, is a living testament to what is possible when you reject the dismissive narrative and embrace a proactive, scientific approach to health. She functions with the vitality of a 25-year-old because we apply the principles outlined in this post. The research is detailed, and the clinical playbook is written. Everything you need is available.

Your journey starts with knowledge. By understanding the critical role of testosterone, the difference between primary and secondary hypogonadism, and the web of interconnected factors like thyroid, stress, and metabolism, you are already taking the first step. The next step is action.

  1. Advocate for Yourself: Do not accept “this is normal for your age” as an answer. Take the lab list from this post to your doctor and insist on a comprehensive workup. If they refuse, find a provider who will listen—a functional medicine practitioner, an integrative doctor, or a knowledgeable nurse practitioner who understands the complexities of hormone health.
  2. Seek Integrative Care: Consider a model like ours at Injury Medical Clinic PA. The synergy between medical oversight from an experienced internist like Dr. Cardenas and the root-cause, holistic approach of functional and chiropractic medicine provides the most comprehensive framework for healing. We don’t just treat the numbers on a lab report; we treat the whole person. We use chiropractic care to balance your nervous system, functional medicine to repair your metabolic and adrenal health, and evidence-based medical treatments when necessary to restore balance.
  3. Embrace Lifestyle as Medicine: While diagnostics and treatments are crucial, remember that the foundations of health are built daily. Prioritize sleep. Learn to manage your stress through mindfulness or breathwork. Move your body in a way that builds strength, not exhaustion. Fuel your body with nutrient-dense whole foods. These are not “soft” recommendations; they are powerful levers that directly influence your hormonal health.

You do not have to navigate this journey alone. The science is on your side, and dedicated clinicians are here to help. It is time to move from being a passive recipient of dismissive advice to an active participant in your own recovery. It is time to reclaim your energy, your mood, your strength, and your vitality. It is time to feel like yourself again.

References

  • Davis, S. R., Baber, R., Panay, N., Bitzer, J., Perez, S. C., Islam, R. M., Kaunitz, A. M., Kingsberg, S. A., Lambrinoudaki, I., Liu, J., Parish, S. J., Pinkerton, J., Rymer, J., Simon, J. A., Vignozzi, L., & Wierman, M. E. (2019). Global Consensus Position Statement on the Use of Testosterone Therapy for Women. The Journal of Clinical Endocrinology & Metabolism, 104(10), 4660–4666. https://doi.org/10.1210/jc.2019-01603
  • Worsley, R., Nab-Hall, A. M., Bell, R. J., & Davis, S. R. (2021). Testosterone and cognitive function in women. The Lancet Diabetes & Endocrinology, 9(3), 174–184. https://doi.org/10.1016/S2213-8587(20)30409-X (Note: The original transcript references a 2021 Lancet Diabetes & Endocrinology article. This is a highly relevant publication from that journal and year. However, the specific point about “association” vs. “correlation” with bone density and sexual dysfunction summarizes the broader consensus, such as the one in the 2019 global statement).
  • Stepien, T., & Kujawska-Luczak, M. (2020). The role of stress and the HPA axis in the pathophysiology of polycystic ovary syndrome. Neuropsychiatric Disease and Treatment, 16, 2831–2841. https://doi.org/10.2147/NDT.S272995
  • Verma, M. K., Jaleel, A., & Kirmani, A. (2021). The importance of sex hormone-binding globulin in the management of testosterone deficiency syndrome. Cureus, 13(5), e14995. https://doi.org/10.7759/cureus.14995

SEO Tags: Testosterone for Women, Low Testosterone Symptoms Women, Female Hypogonadism, Integrative Chiropractic Care, Dr. Alex Jimenez, Functional Medicine El Paso, Hormone Replacement Therapy, Low Libido in Women, Chronic Fatigue Syndrome, Weight Gain Hormones, Primary Hypogonadism, Secondary Hypogonadism, HPA Axis Dysfunction, Pregnenolone Steal, Cortisol and Testosterone, Thyroid and Hormones, SHBG, Dr. Maria Guadalupe Cardenas, Integrative Medicine Texas, GLP-1 and Hormones, Caloric Deficit Hormones, Comprehensive Hormone Testing

El Paso Spine and Nerve Pain Second Opinion Options

El Paso Spine and Nerve Pain Second Opinion Options

El Paso Spine and Nerve Pain Second Opinion Guide

Abstract

Complex spinal joint and nerve pain can be difficult to treat because the discomfort may not come from just one structure. A person may have problems involving the vertebrae, facet joints, spinal disks, muscles, ligaments, and nerve roots at the same time. This overlap can cause back or neck pain, stiffness, burning, numbness, tingling, weakness, or pain that travels into an arm or leg.

For patients in El Paso and West Texas who have already tried medications, injections, physical therapy, or other treatments without enough improvement, a second opinion may provide a fresh look at the diagnosis and treatment plan. A multidisciplinary approach may combine integrative chiropractic care and rehabilitation with medical oversight and selected treatments such as shockwave therapy, MLS laser therapy, epidural spinal injections, platelet-rich plasma (PRP), platelet/fibrin preparations, microfragmented adipose tissue (MFAT), IV infusion therapy, and carefully considered peptide therapies.

The goal is not to use every treatment on every patient. The goal is to identify what is causing the pain and build the safest, most appropriate recovery plan.

El Paso Spine and Nerve Pain Second Opinion Options


What Is Complex Spinal Joint and Nerve Pain?

Complex spinal joint and nerve pain is chronic discomfort caused by overlapping damage, wear, inflammation, or pressure involving several parts of the spine.

These structures may include:

  • Vertebrae
  • Facet joints
  • Intervertebral disks
  • Spinal nerve roots
  • Ligaments
  • Tendons
  • Muscles
  • Connective tissues

The spine is not simply a stack of bones. It is a moving system in which joints, disks, muscles, and nerves must work together. Because these structures are close to one another, a problem in one area can affect another.

For example, an aging or injured disk may bulge and reduce the space available for a nerve. Arthritis may cause bone spurs around a facet joint. Swelling after an injury may further irritate the nerve. Muscles may then tighten to protect the painful region. The patient may experience both joint and nerve symptoms.

Kansas Pain Management (2026) explains that back pain may originate from muscles, spinal joints, discs, or nerves, and that identifying the source matters when choosing treatment.


Joint Pain and Nerve Pain Can Feel Different

Understanding the type of pain can provide important clues.

Joint-related spinal pain may feel like:

  • A deep ache
  • Localized neck or back pain
  • Stiffness
  • Tenderness
  • Pain during bending or twisting
  • Pain after prolonged sitting or standing
  • Decreased range of motion

The facet joints help guide movement between the vertebrae. Like other joints, they can become irritated or develop degenerative changes.

Nerve-related pain may feel like:

  • Burning
  • Electrical sensations
  • Sharp or shooting pain
  • Tingling
  • Pins and needles
  • Numbness
  • Weakness
  • Pain traveling into an arm or leg

Butler (2026) notes that nerve and joint pain can sometimes occur together, making the source of symptoms difficult to identify without a detailed evaluation.

Radiculopathy is one example. It occurs when a spinal nerve root becomes irritated or compressed. Common causes include disk herniation, bone spurs, arthritis, inflammation, and narrowing around the nerves (Advanced Orthopaedics & Sports Medicine, n.d.).


Complex Spinal Pain Is Not the Same as CRPS

It is also important to separate complex spinal joint and nerve pain from complex regional pain syndrome (CRPS).

CRPS is a specific neurological pain disorder. Cleveland Clinic (2022) explains that it commonly affects an arm, hand, leg, or foot and may involve severe pain, sensitivity, swelling, changes in skin color or temperature, and changes in movement. It involves abnormal processing within the nervous system.

A person with chronic spinal pain does not automatically have CRPS.

However, CRPS helps demonstrate an important principle: chronic pain can involve much more than the place where pain is felt. Nerves, inflammation, movement, circulation, and nervous-system signaling can all contribute to the problem.


When Should You Seek a Second Opinion for Spinal Pain?

Getting a second opinion does not mean the first doctor did something wrong.

Complex spinal conditions can change over time, and different specialists may view the same problem from different angles.

A second opinion may be worth considering when:

  • Pain has continued for weeks or months.
  • Treatment helped only briefly.
  • Pain keeps returning.
  • You have tried several medications without enough relief.
  • You have completed therapy but still cannot move normally.
  • An injection helped temporarily, but symptoms returned.
  • Your MRI findings do not seem to match your symptoms.
  • Your pain travels into an arm or leg.
  • Numbness or tingling continues.
  • You notice weakness or decreased coordination.
  • Several areas of the spine appear to be involved.
  • You were told that surgery is your only option, but you want to understand nonsurgical choices.
  • You have been given several different diagnoses.
  • You were injured in a car crash or workplace accident, and recovery has stalled.

Spinal nerve compression can develop from herniated disks, degenerative disk changes, spinal stenosis, bone spurs, or trauma. Persistent numbness, weakness, radiating pain, and mobility problems deserve careful evaluation (Dallas Spine Surgery, 2026).

Urgent symptoms are different. New loss of bowel or bladder control, saddle-area numbness, rapidly increasing weakness, major trauma, fever with severe spinal pain, or other serious neurological changes require prompt medical evaluation rather than simply scheduling a routine second opinion.


Why a New Evaluation Can Change the Treatment Plan

A second opinion should involve more than reviewing the old diagnosis.

A comprehensive examination may evaluate:

  • Where the pain begins
  • Where the pain travels
  • Muscle strength
  • Reflexes
  • Sensation
  • Spinal motion
  • Joint mobility
  • Posture
  • Balance
  • Gait
  • Muscle guarding
  • Previous injuries
  • MRI or CT findings
  • X-rays when appropriate
  • Previous procedures
  • Medications
  • Medical conditions that may affect recovery

MRI, CT, electrodiagnostic testing, and other studies can help identify nerve compression or other neurological problems (Advanced Orthopedics & Sports Medicine, n.d.).

The important question becomes:

Which structure is producing which symptom?

That question can help prevent a patient from repeatedly treating the wrong part of the problem.


Integrative Chiropractic Care for Complex Spinal Pain

Integrative chiropractic care can be one part of a larger treatment plan.

Chiropractic care focuses on the mechanical and functional side of the condition. Depending on the diagnosis and the patient’s safety needs, treatment may involve:

  • Chiropractic adjustments
  • Gentle spinal mobilization
  • Soft-tissue techniques
  • Flexibility work
  • Postural correction
  • Core stabilization
  • Corrective exercise
  • Neuromuscular rehabilitation
  • Movement retraining
  • Home exercise

Spinal manipulation is not a cure for every spinal condition. However, the National Center for Complementary and Integrative Health reports that spinal manipulation may provide small improvements in pain and function for some people with low-back pain (NCCIH, n.d.).

This is why chiropractic treatment works best when it matches the diagnosis rather than being automatically applied to every painful spinal segment.


Combining Chiropractic Care With Advanced Treatment Options

Complex conditions may require multiple layers of treatment. Select these therapies based on the actual pain generator, medical history, imaging, examination, and response to previous treatment.

Shockwave Therapy

Extracorporeal shockwave therapy uses mechanical acoustic waves directed into selected musculoskeletal tissues.

Research suggests that shockwave therapy may reduce pain and improve function in some patients with chronic low-back pain. However, evidence quality varies, and more high-quality research is needed (Ferdinandov, 2024; Wu et al., 2023).

Shockwave therapy may be considered when muscular, fascial, tendon, or other musculoskeletal components contribute to chronic pain.

It does not physically remove a large disk herniation or mechanically open a severely compressed spinal nerve.


MLS Laser Therapy

MLS, or Multiwave Locked System laser therapy, uses synchronized light wavelengths.

Research into MLS laser treatment for chronic low-back pain is growing. Arefi et al. (2025) reported reduced pain in a small randomized study involving patients with chronic low-back pain. Other randomized research has also examined its effects on pain, movement, and disability (Labanca et al., 2024).

MLS laser may therefore serve as a noninvasive supportive treatment, especially when pain and irritated soft tissues make rehabilitation difficult.

The goal is often to help the patient tolerate movement and rehabilitation—not to replace rehabilitation.


Epidural Spinal Injections

When an irritated or compressed nerve root is producing radiating pain, an epidural injection may sometimes be considered.

The American Academy of Neurology’s systematic review found that epidural steroid injections probably provide short-term improvement in pain and disability for some patients with cervical or lumbar radiculopathy. Long-term pain benefits are less certain (Armon et al., 2025).

An epidural injection may create a window of reduced inflammation that allows the patient to participate more effectively in rehabilitation.

It does not correct every underlying mechanical cause.


PRP and Platelet/Fibrin Therapies

Platelet-rich plasma (PRP) is prepared from the patient’s own blood. The platelets are concentrated and placed into a selected injured region.

Platelets contain proteins and growth factors involved in normal tissue repair.

Research into PRP for degenerative spinal pain is developing. A systematic review found encouraging results for some forms of low-back pain, but protocols and study quality vary, so PRP is not a guaranteed solution for spinal degeneration (Muthu et al., 2023).

Some clinics also use platelet-and-fibrin preparations, sometimes referred to as PFP or related platelet-rich fibrin products. Terminology and preparation methods are not standardized. Injectable platelet-rich fibrin is being studied in orthopedics, but researchers continue to call for better clinical evidence (Costa et al., 2025).

These treatments should therefore be viewed as selected orthobiologic options, not automatic treatments for every painful disk or joint.


MFAT: Microfragmented Adipose Tissue

Microfragmented adipose tissue, or MFAT, is prepared from a patient’s own adipose tissue and mechanically processed for use in selected orthopedic applications.

Most higher-quality MFAT research currently involves joints such as the knee rather than complex spinal nerve compression.

Recent systematic reviews suggest potential improvements in pain and function for knee osteoarthritis, but they also point out limitations in the amount and quality of evidence (Hohmann et al., 2025).

For spinal patients, MFAT should therefore be considered only after careful diagnosis and discussion of the evidence, alternatives, risks, and intended treatment target.


What About Peptide Therapy?

Peptide therapies have attracted attention because some peptides are being studied for tissue signaling, inflammation, metabolism, and repair.

However, patients should understand an important difference between research interest and established treatment.

Several peptides promoted online for musculoskeletal healing are not FDA-approved treatments for spinal disk, joint, or nerve repair.

The FDA has specifically reported limited human safety information and potential concerns involving compounded substances such as BPC-157, CJC-1295, ipamorelin, and several other peptides (U.S. Food and Drug Administration, 2026).

For that reason, peptide treatment should never be presented as a proven way to regenerate a spinal disk or heal a compressed nerve. Any peptide discussion should occur under qualified medical supervision with attention to legal status, evidence, medication interactions, and patient-specific risks.


IV Infusion Therapy as Medical Support

IV therapy is another tool that must match the patient’s actual medical needs.

An IV can provide fluids, medications, or specific nutrients when medically indicated. In specialized pain medicine, IV ketamine is one treatment sometimes considered for difficult conditions such as severe CRPS (Cleveland Clinic, 2022).

However, general vitamin or nutrient IV therapy should not be described as directly rebuilding a damaged disk or removing nerve compression.

Within an integrative program, medical evaluation may identify dehydration, nutritional deficiencies, medication issues, metabolic problems, or other factors that could influence overall recovery.

In that setting, IV therapy is supportive medical care, not a substitute for treating the structural cause of spinal pain.


A Multidisciplinary Model in El Paso, Texas

At Injury Medical Clinic PA in El Paso, the care model combines medical oversight with integrative chiropractic treatment.

Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, works in chiropractic care, advanced practice nursing, functional medicine, personal injury care, neuromusculoskeletal evaluation, and rehabilitation.

His published clinical observations emphasize looking beyond the place where the patient feels pain and evaluating spinal mechanics, nerve involvement, movement, inflammation, functional limitations, and the patient’s broader medical picture (Jimenez, n.d.).

Working with him is Dr. Maria Guadalupe Cardenas, MD, whom Injury Medical Clinic materials identify as board-certified in internal medicine and Medical Director and Collaborative Physician.

Independent public provider information shows that Dr. Cardenas has practiced medicine for more than 40 years and identifies her specialty as internal medicine. Current public provider records list:

  • NPI: 1164426749
  • Texas medical license: J2933
  • Specialty: Internal Medicine

This multidisciplinary structure enables the team to review different parts of a complicated case together.

Dr. Jimenez’s role may focus on:

  • Chiropractic evaluation
  • Joint and spinal mechanics
  • Functional medicine
  • Neuromusculoskeletal examination
  • Personal injury care
  • Rehabilitation
  • Movement restoration

Dr. Cardenas’s internal medicine role can add:

  • Medical oversight
  • Review of chronic health conditions
  • Medication review
  • Cardiovascular and metabolic risk assessment
  • Laboratory interpretation
  • Safety screening
  • Medical referrals
  • Coordination of more complex medical needs

The result is a broader approach than treating a painful spinal segment alone.


A More Complete Recovery Strategy

For some patients with complex spinal joint and nerve pain, a coordinated treatment plan may move through several stages.

Phase 1: Find the pain generators

Determine whether the major problem involves:

  • Disk injury
  • Facet joints
  • Nerve compression
  • Muscles
  • Ligaments
  • Inflammation
  • Scar tissue
  • Poor mechanics
  • Several of these together

Phase 2: Calm symptoms when needed

Selected patients may benefit from:

  • MLS laser
  • Shockwave therapy
  • Medication
  • Epidural treatment
  • Other pain-management approaches

Phase 3: Restore movement

Integrative chiropractic care and rehabilitation may address:

  • Mobility
  • Posture
  • Muscle balance
  • Stability
  • Strength
  • Movement patterns

Phase 4: Consider advanced biological options

When appropriate, the team may discuss:

  • PRP
  • Platelet/fibrin preparations
  • MFAT
  • Other evidence-based or investigational options

Phase 5: Address the whole patient’s health

Functional and medical evaluations may include:

  • Nutrition
  • Sleep
  • Blood sugar
  • Weight
  • Inflammation
  • Hydration
  • Medications
  • Chronic health conditions
  • Appropriate IV support when medically indicated

This is a more realistic meaning of integrative care. Treatments are coordinated around a diagnosis instead of simply adding more procedures.


When Traditional Treatment Has Not Worked

If you have been living with chronic neck pain, back pain, sciatica, numbness, tingling, weakness, or spinal joint pain in El Paso or West Texas, continued symptoms deserve another look.

A second opinion may reveal that the original problem is more complicated than one painful disk, one arthritic joint, or one irritated nerve.

The goal should be to answer three questions:

  1. What is causing the pain?
  2. Which problems can be treated conservatively?
  3. Which treatments offer reasonable benefits based on the patient’s diagnosis and current evidence?

Complex spinal joint and nerve pain often requires coordination rather than a single treatment.

For the right patient, integrative chiropractic care, rehabilitation, medical oversight, laser or shockwave therapy, targeted injections, and carefully selected regenerative approaches may work together as parts of a comprehensive plan.

But no procedure should be promised to provide complete healing.

The strongest treatment plan is the one built around an accurate diagnosis, measurable functional goals, careful safety screening, and regular re-evaluation.

Facet Syndrome Pain Treatment El Paso, TX

References

Advanced Orthopaedics & Sports Medicine. (n.d.). Radiculopathy.

Arefi, S., Saidian, S. R., Mokhtari, M., & Eliaspour, D. (2025). MLS laser reduce pain in patients with chronic low back pain. Anesthesiology and Pain Medicine, 15(1), e158778.

Armon, C., Narayanaswami, P., Potrebic, S., Gronseth, G., et al. (2025). Epidural steroids for cervical and lumbar radicular pain and spinal stenosis: Systematic review summary. Neurology, 104(5), e213361.

Butler, B. (2026, April 7). Nerve pain vs. joint pain: Understanding the differences and finding proper relief. Oakland Spine & Physical Therapy.

Cleveland Clinic. (2022, September 30). Complex regional pain syndrome (CRPS).

Costa, B. R., et al. (2025). The role of injectable platelet-rich fibrin in orthopedics: Where do we stand?.

Dallas Spine Surgery. (2026, April 3). What causes nerve compression in the spine?.

Ferdinandov, D. (2024). Focused extracorporeal shockwave therapy for the treatment of low back pain: A systematic review. Frontiers in Medicine, 11, 1435504.

Hohmann, E., Keough, N., Frank, R. M., & Rodeo, S. (2025). Micro-fragmented adipose tissue demonstrates comparable clinical efficacy to other orthobiologic injections in treating symptomatic knee osteoarthritis. Arthroscopy, 41(2), 418–441.e14.

Jimenez, A. (n.d.). Dr. Alex Jimenez—El Paso chiropractor, family nurse practitioner, functional and injury care.

Kansas Pain Management. (2026, March 18). Is your back pain coming from nerves, muscles, or joints?.

Labanca, L., Berti, L., Tedeschi, R., D’Auria, L., Platano, D., & Benedetti, M. G. (2024). Effects of MLS laser on pain, function, and disability in chronic non-specific low back pain: A double-blind placebo randomized-controlled trial. Journal of Back and Musculoskeletal Rehabilitation, 37(5), 1289–1298.

National Center for Complementary and Integrative Health. (n.d.). Spinal manipulation: What you need to know.

U.S. Food and Drug Administration. (2026). Certain bulk drug substances for use in compounding that may present significant safety risks.

Wu, Z., Zhou, T., & Ai, S. (2023). Extracorporeal shock wave therapy for low back pain: A systematic review and meta-analysis. Medicine, 102(52), e36596.

Supplemental Media Resources Provided for This Article

YouTube spinal-pain educational video—resource 1

YouTube spinal-pain educational video—resource 2

Manipal Hospitals—spine problems affecting vertebrae, disks, nerves, and surrounding muscles

Nerve Pain After Sports: Insights and Solutions

Nerve Pain After Sports: Insights and Solutions

Nerve Pain After Sports: An Integrative Path From Irritated Nerves to Stronger Movement

Abstract

Athletes and active adults can develop neuropathies. These nerve problems usually come from repeated small strains, sudden compression, or stretching during sport. This article explains how sports neuropathies start, how they feel, and why they are often mistaken for a simple sprain or tendon injury. It then guides the reader through an integrative plan that uses chiropractic care to restore motion, advanced tools such as laser and shockwave therapy to support local healing, and regenerative medicine or targeted injections when tissue repair needs extra help. The article also describes the team model at Injury Medical Clinic PA in El Paso, Texas, where chiropractic care, medical oversight, functional medicine, personal injury care, and rehabilitation work together.

Nerve Pain After Sports: Insights and Solutions

Are There Neuropathies in Sports?

Yes, neuropathies do occur in sports and typically result from repetitive microtrauma, acute compression, or stretching of the nerves during athletic activity.

A neuropathy means a peripheral nerve is irritated, compressed, or injured. Peripheral nerves carry messages that help a person feel the ground, grip a bar, lift an arm, or keep balance. When those messages are disrupted, the body may feel burning, tingling, numbness, weakness, or a sharp electric snap.

Sports nerve injuries are not the most common athletic injuries, but they are important. They can linger, change the way a person moves, and delay a safe return to activity. Sports-related peripheral neuropathies make up a small part of all nerve problems and more often involve the arms than the legs (Mitchell et al., 2014). Older clinical reports also show that many of these injuries come from repeated pressure rather than one dramatic tear (Hirasawa & Sakakida, 1983).

That is why a nerve problem can hide inside what looks like a shoulder strain, elbow ache, or stubborn foot pain.

A Simple Way to Understand the Injury

Think of a nerve as a cable that needs room, blood flow, and the ability to slide as the body moves. Sport can crowd that cable in three ways.

Repeated small strain
The same motion, done over and over, can rub a nerve against bone, fascia, or a tight muscle. Throwers often load the ulnar nerve at the elbow. Overhead athletes may stress nerves around the shoulder. Runners and dancers may load nerves in the ankle and foot (Izzi et al., 2001; Senk & Carlson, 2026).

Sudden compression
A hit, fall, swelling, tight shoe, or long time in one position can pinch a nerve. Cyclists may compress nerves in the hands or pelvic area. In contact sports, athletes can compress nerves in the neck and shoulder.

Stretching
A hard landing, awkward slide, or side-bending force can pull a nerve. Stingers and burners in football and wrestling are well-known examples of this stretch-and-compression pattern (Stokes et al., 2025).

Training errors add to the risk. A fast jump in mileage, poor technique, muscle imbalance, and extra swelling can all reduce the space a nerve needs (Tettenborn et al., 2016).

Common Sports Nerve Problems

Different sports tend to irritate different nerves.

Upper body

  • Stingers and burners after contact to the neck or shoulder
  • Suprascapular or axillary nerve irritation in throwing and overhead sports
  • Ulnar nerve pain at the elbow in baseball and other throwing sports
  • Median or ulnar nerve compression at the wrist in cycling, lifting, and gripping sports
  • Radial nerve irritation in racket sports

Lower body

  • Peroneal nerve injury near the outside of the knee
  • Tarsal tunnel syndrome at the inside of the ankle
  • Sural nerve pain along the outside of the ankle and heel
  • Medial plantar nerve irritation, sometimes called jogger’s foot
  • Morton’s neuroma between the toes

Ankle and foot neuropathies are easy to miss. They can look like plantar fasciitis, Achilles tendon pain, or a sprain that never fully settles (Senk & Carlson, 2026). Sural nerve irritation can also mimic Achilles problems. Neuropathic pain in sport may start as activity-related burning and later become sharper or more electric (Bastani, n.d.).

Signs That the Problem May Be a Nerve

Nerve pain does not always announce itself clearly. These clues deserve a closer look:

  • Burning, tingling, or pins-and-needles in a clear path
  • Numbness in part of the hand, foot, or skin
  • Weakness that does not match a simple muscle pull
  • Pain that returns with one grip, stride, throw, or shoe
  • Symptoms that fade with rest and come back as soon as training resumes
  • Heel, arch, or outside-ankle pain that does not fit a typical tendon story

Imaging and nerve tests can help when the picture is unclear. MRI may show nerve swelling or muscle changes (Mitchell et al., 2014). Ultrasound can look for compression. EMG and nerve conduction studies can confirm which nerve is involved and how severe the injury is (Stokes et al., 2025). Early diagnosis provides a person with a better chance of recovering without long-term changes in strength or movement.

How Integrative Chiropractic Care Fits In

Integrative chiropractic care looks at the nerve and the structures around it. A nerve can be irritated because a joint is stiff, a disc is taking up space, a muscle is crowding a tunnel, or a movement pattern keeps stretching the same spot.

Chiropractic care can help by:

  • Improving spinal and limb joint motion
  • Reducing mechanical pressure around an irritated nerve
  • Easing tight soft tissue that crowds a nerve path
  • Retraining posture, gait, and sport mechanics
  • Guiding a safer return to load

Integrative chiropractic therapy is a strong, multi-layered approach to treating sports neuropathies, especially when combined with advanced modalities, regenerative medicine, and targeted injections. This procedure combines structural and cellular healing by fixing mechanical misalignment, improving metabolic function, and restoring biological function all at once.

The practical meaning is simple. The joint needs to move. The local tissue needs blood flow. The nerve needs a calmer place to heal. Treating only one layer often leaves the problem half-solved.

Laser Therapy and Shockwave Therapy

Two advanced tools are often used alongside chiropractic care.

Laser therapy, also called photobiomodulation, uses focused light to support cell energy and calm irritated tissue. In chiropractic and rehabilitation settings, it reduces inflammation around nerves, supports local circulation, and eases neuropathic pain (ChiroEco, n.d.; Medray Laser, n.d.; Lazar Spinal Care, n.d.). Class IV and MLS-style lasers are common options when the goal is drug-free support for nerve-related pain (Attaman, n.d.; Harrington, n.d.).

Shockwave therapy sends acoustic waves into stubborn soft tissue. It can increase blood flow, help thick tissue remodel, and support healing in areas that have become tight or poorly nourished (Holistiq, n.d.; HealthWorks, n.d.; Integrated Physical Medicine, n.d.). That is useful when a nerve sits next to an overused tendon, scarred fascia, or a crowded tunnel.

Laser and shockwave are not the same tool. Laser is often used to calm cells and improve circulation. Shockwave is often used for thicker, more chronic soft-tissue restriction (MVMT Chiropractic, n.d.). Both work best when the mechanical problem is also treated.

Regenerative Medicine and Targeted Injections

Some sports neuropathies linger because nearby discs, ligaments, or tunnels heal slowly. Regenerative care aims to support repair, not only cover symptoms.

Common options include:

  • PRP (platelet-rich plasma): concentrated platelets from the person’s own blood
  • Platelet-fibrin products: a natural scaffold that can hold healing signals in place
  • MFAT (microfragmented adipose tissue): a person’s own fat tissue, processed and used to support cushioning, signaling, and inflammation control (Fu & Wang, 2025; Regen Axis Health, n.d.)
  • Image-guided injections: used when a joint, ligament, or nerve tunnel needs a more focused stimulus

These options are not right for every case. They work best when movement is also restored. If a nerve remains pinched by poor joint mechanics, the biological signal has a harder time lasting (Jimenez, n.d.-a; Jimenez, n.d.-b). Nutrition supports the same process. Protein, vitamin C, zinc, omega-3 fats, antioxidants, and hydration all help tissue repair and inflammation control (Chiropractic Scientist, n.d.).

Clinical Observations From Dr. Alexander Jimenez

Clinical observations from Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, return to one practical theme: treat the injured tissue and the movement pattern together. An injection, a laser visit, or an adjustment can help. It is rarely the whole plan. The person still needs better joint motion, better strength, and a smarter training load (https://dralexjimenez.com/; https://www.linkedin.com/in/dralexjimenez/).

That view is useful in sports neuropathies because the nerve injury is often linked to compensation. A stiff ankle can overload a foot nerve. A restricted thoracic spine can change throwing mechanics and stress a shoulder nerve. A guarded gait after a collision can keep a lower-limb nerve irritated long after the first bruise fades.

A Team Model in El Paso

At Injury Medical Clinic PA in El Paso, Texas, we build this layered plan as a team process.

Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, provides chiropractic care and integrative evaluation. Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), has more than 40 years of experience as an internist. She works with Dr. Jimenez and serves as medical director and collaborative physician at the practice. This multidisciplinary setup is common in integrative or injury care clinics, where an MD provides medical direction alongside a chiropractor.

The team integrates:

  • Chiropractic care for joint motion and nerve pressure
  • Medical oversight for safety, imaging decisions, and complex cases
  • Functional medicine for inflammation, nutrient status, and recovery capacity
  • Personal injury care when a crash, fall, or delayed sports injury needs clear documentation
  • Rehabilitation to restore strength, balance, and sport skill

That mix matters because a sports neuropathy is rarely just one problem. It may involve a spinal joint, a foot-strike pattern, swelling, old scar tissue, or a metabolic factor that slows healing.

What the Recovery Journey Can Look Like

A clear path helps people know what comes next:

  1. Tell the full story of the sport, the hit, the training change, and when symptoms started.
  2. Map the nerve path with a hands-on exam.
  3. Use imaging or nerve testing when the diagnosis is still unclear.
  4. Take pressure off the nerve with chiropractic care and movement changes.
  5. Support healing with laser, shockwave, nutrition, and, when needed, regenerative injections.
  6. Rebuild capacity before full return to sport or work.

Most sports nerve injuries can start with conservative care. Surgery is considered when symptoms persist, or testing shows a more severe structural problem (Stokes et al., 2025; Tettenborn et al., 2016).

The hopeful point is this: sports neuropathies are real, but they are also workable. When structural care and cellular repair work together, they aim for more than just less pain. The goal is a nerve that can send a clearer signal and a body that can move with more confidence.

El Paso, TX Chiropractic Alignment

References

Attaman, J. (n.d.). MLS laser therapy for joint, nerve, and spine pain.

Bastani, M. (n.d.). Neuropathic pain in sports injuries. Journal of Sports and Rehabilitation Sciences.

ChiroEco. (n.d.). Laser therapy for neuropathic pain.

Chiropractic Scientist. (n.d.). Nutrition supports regenerative therapies and recovery.

Fu, H., & Wang, C. (2025). Micro-fragmented adipose tissue—An innovative therapeutic approach: A narrative review.

Harrington, P. (n.d.). Comparing Class 4 laser therapy, PEMF, and shockwave treatments in chiropractic care.

HealthWorks. (n.d.). Combining shockwave therapy and chiropractic: A powerful duo for chronic back pain.

Hirasawa, Y., & Sakakida, K. (1983). Sports and peripheral nerve injury. The American Journal of Sports Medicine, 11(6), 420–426.

Holistiq. (n.d.). The power of combining chiropractic treatment and shockwave therapy.

Integrated Physical Medicine. (n.d.). The benefits of integrating shockwave therapy.

Izzi, J., Dennison, D., Noerdlinger, M., Dasilva, M., & Akelman, E. (2001). Nerve injuries of the elbow, wrist, and hand in athletes. Clinics in Sports Medicine.

Jimenez, A. (n.d.-a). How regenerative medicine and chiropractic care work together.

Jimenez, A. (n.d.-b). Regenerative and integrative care for sciatica: PRP, PFP, mFAT, epidurals, and chiropractic support.

Lazar Spinal Care. (n.d.). Chiropractor laser therapy for neuropathy.

Medray Laser. (n.d.). Peripheral neuropathy: A chiropractic opportunity.

Mitchell, C. H., Brushart, T. M., Ahlawat, S., Belzberg, A. J., Carrino, J. A., & Fayad, L. M. (2014). MRI of sports-related peripheral nerve injuries. American Journal of Roentgenology, 203(5), 1075–1084.

MVMT Chiropractic. (n.d.). Shockwave therapy vs. laser therapy.

Regen Axis Health. (n.d.). Adipose-derived cell therapy: MFAT.

Senk, A. M., & Carlson, A. (2026). Ankle and foot neuropathies and entrapments. PM&R KnowledgeNow.

Stokes, D. C., Toole, K., & Cushman, D. M. (2025). Upper extremity neuropathies in athletes. Current Sports Medicine Reports, 24(11), 356–365.

Tettenborn, B., Mehnert, S., & Reuter, I. (2016). Peripheral nerve lesions due to sports.

Integrative Obesity Care and Cardiometabolic Wellness

Discover the benefits of integrative obesity and cardiometabolic care for comprehensive health improvement and obesity management.

Abstract

As a clinician practicing at the intersection of chiropractic care, advanced practice nursing, and functional medicine, I have seen how obesity and its cardiometabolic comorbidities reshape health trajectories for adults aged 40 to 60. In this educational post, I synthesize the latest findings from leading researchers and landmark trials to present a comprehensive, integrative roadmap for assessing and treating obesity-driven conditions, including insulin resistance, type 2 diabetes, hypertension, dyslipidemia, heart failure with preserved ejection fraction, metabolic dysfunction-associated steatotic liver disease, obstructive sleep apnea, osteoarthritis, chronic pain, depression, stress, and the complex physiology of menopause and sarcopenic obesity.

I lead Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, a multidisciplinary practice where I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, integrate chiropractic care, functional medicine, rehabilitation, and personal injury services with the medical direction of our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), who brings over 40 years of internal medicine experience. Our integrative model aligns medical oversight, precise diagnostics, functional and rehabilitative interventions, and evidence-based pharmacotherapy to reduce adiposity, improve metabolic function, preserve muscle, protect joints, and elevate quality of life.

You will find clear explanations of physiological mechanisms, stepwise protocols, clinical reasoning for each technique, in-depth case studies, and practical strategies for patients and clinicians. Throughout, I include my clinical observations from sciatica.clinic and professional updates on LinkedIn to illustrate how integrative chiropractic care supports neuromusculoskeletal function, autonomic balance, pain control, and adherence to cardiometabolic treatments. The collective research foundation includes the SELECT trial (semaglutide and cardiovascular outcomes), STEP-HFpEF (semaglutide for HFpEF), SURMOUNT-1 (tirzepatide and diabetes progression), SURMOUNT-OSA (tirzepatide and sleep apnea), STEP trials (weight reduction and osteoarthritis), the Look AHEAD trial (long-term lifestyle outcomes in diabetes), MAESTRO-NASH (resmetirom for MASH), and core guideline statements from the ADA, AACE/ACE, NAMS, ACOG, AHA/ACC, and AASM.

Our Integrative Clinic in El Paso: A Multidisciplinary Care Model Led by Medical Direction and Chiropractic Integration

I lead Injury Medical Clinic PA—also known as Mission Plaza Injury Medical Clinic—in El Paso, Texas, where our team integrates multiple disciplines to provide comprehensive, patient-centered care. At the core of our model is a collaborative partnership between my roles in chiropractic and advanced nursing practice, and the medical direction of our internal medicine physician.

  • My credentials and roles
    • Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST
    • Chiropractic care: neuromusculoskeletal assessment, spinal and extremity adjustments, soft tissue therapies, movement re-education
    • Functional medicine: systems-biology diagnostics, metabolic root-cause analysis, nutritional therapeutics, stress and sleep integration
    • Rehabilitation: graded loading, movement quality, joint protection
    • Personal injury care: documentation, impairment analysis, coordinated rehabilitative pathways
  • Medical direction and collaborative oversight
    • Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933)
    • Over 40 years as an internist, supervising diagnostics, pharmacotherapy, and complex case management
    • Provides medical direction typical of integrative and injury clinics and safeguards evidence-based standards and patient safety
  • How our team integrates care
    • Medical oversight ensures safe, effective protocols and precision in diagnostics (labs, imaging, risk stratification)
    • Chiropractic care reduces pain, restores joint mechanics, modulates autonomic tone, and enables activity.
    • Functional medicine identifies root causes across hormonal, inflammatory, metabolic, gastrointestinal, and stress domains.
    • Rehabilitation builds capacity: strength, flexibility, balance, proprioception, and graded exposure to movement.
    • Personal injury services align recovery with metabolic and musculoskeletal health goals.
    • Continuous outcome tracking: weight, waist circumference, body composition, blood pressure, A1c, lipids, pain scales, mobility, and sleep metrics

This multidisciplinary setup allows us to treat cardiometabolic disease and biomechanical dysfunction synergistically, ensuring each intervention supports the others.

Integrative Care Philosophy: Why Treating Obesity Is Treating Cardiometabolic Disease

Our guiding principle is simple and profoundly evidence-based: treating obesity is treating its downstream cardiometabolic disorders. Excess adiposity, especially visceral fat, drives inflammation, insulin resistance, dyslipidemia, hypertension, endothelial injury, sleep apnea, musculoskeletal pain, and neurohormonal imbalance. We aim not merely to reduce weight but to reduce adipose tissue—protecting and increasing lean muscle, restoring metabolic flexibility, and improving function and quality of life.

  • Our core goals
    • Reduce adiposity, especially visceral fat
    • Preserve and increase lean muscle mass and strength
    • Lower cardiometabolic risk (ASCVD, heart failure, diabetes, MASLD/MASH, OSA)
    • Improve functional capacity: walking, stairs, daily activities, sport return
    • Elevate quality of life: energy, mood, sleep, pain reduction, confidence
  • Clinically meaningful weight loss thresholds (Ryan & Yockey, 2017)
    • 5–5%: quality of life improvements; early glycemic gains; mobility relief
    • 5–10%: dyslipidemia improvements, knee osteoarthritis pain reduction, sleep apnea severity reduction
    • 10–15%+: hypertension improvements, diabetes remission potential, MASLD resolution potential, significant cardiovascular risk reduction
  • Why percent targets matter
    • They create achievable milestones that compound toward larger health gains
    • They provide dose-response clarity for risk reduction and motivate adherence

Deconstructing Cardiometabolic Syndrome: Diagnostic Criteria and Pathophysiology

Cardiometabolic syndrome is a cluster of metabolic abnormalities that amplify risk for type 2 diabetes, stroke, and cardiovascular events. At its core is a bidirectional loop between obesity and insulin resistance, fueled by chronic low-grade inflammation from adipose tissue cytokines and adipokines.

  • Diagnostic criteria (must have 3 of 5) (Grundy et al., 2005)
    • Central obesity: waist circumference > 40 inches (men) or > 35 inches (women)
    • Triglycerides ≥ 150 mg/dL or on therapy
    • Low HDL: < 40 mg/dL (men) or < 50 mg/dL (women)
    • Blood pressure ≥ 130/85 mmHg or on antihypertensives
    • Fasting glucose ≥ 100 mg/dL or dysglycemia diagnosis
  • Pathophysiology
    • Adipose inflammation: TNF-alpha, IL-6, resistin, and leptin signaling derangements (Powell-Wiley et al., 2021)
    • Insulin resistance: impaired receptor signaling in muscle, liver, and fat; compensatory hyperinsulinemia
    • Neurohormonal activation: sympathetic drive, renin-angiotensin-aldosterone system, vasoconstriction, sodium retention
    • Atherogenic dyslipidemia: elevated triglycerides, suppressed HDL, ApoB particle elevation.
    • Endothelial dysfunction: reduced nitric oxide bioavailability, vascular stiffness
  • Building a clinical risk profile
    • Vital signs: standardized blood pressure measurements after rest; accurate waist circumference
    • Body composition: InBody or DEXA scan to differentiate fat mass, lean mass, water, and estimate visceral adipose tissue
    • Laboratory evaluation
      • Fasting lipid panel: TC, LDL, HDL, triglycerides
      • Advanced lipids: ApoB particle count; Lipoprotein(a) [Lp(a)] for genetic risk
      • Glycemic markers: fasting glucose, HbA1c, fasting insulin (for insulin resistance), HOMA-IR calculation
    • Cardiovascular imaging: selective Coronary Artery Calcium (CAC) scoring
    • Psychosocial evaluation: PHQ-9, GAD-7, stress assessment, sleep quality, social support, and food relationship

Our integrative framework leverages these data to tailor interventions, calibrate pharmacotherapy, and track progress longitudinally.

Obesity and Cardiovascular Disease: Inflammation, Epicardial Fat, and Atherosclerosis

Obesity harms the cardiovascular system through mechanical burden, hemodynamic stress, inflammatory signaling, and neurohormonal activation. Of particular concern is epicardial and pericardial fat—locally pro-inflammatory tissue that shares blood supply with the coronary arteries and directly accelerates atherosclerosis.

  • Mechanisms of cardiovascular injury (Powell-Wiley et al., 2021)
    • Mechanical load: increased cardiac output demands; left ventricular hypertrophy risk
    • Hemodynamic changes: diastolic dysfunction; filling pressure abnormalities
    • Inflammation: endothelial damage; plaque initiation and progression
    • Neurohormonal derangement: RAAS activation; sympathetic tone; leptin resistance
  • Epicardial fat (“sick fat disease”)
    • Bathes myocardium and coronary arteries with inflammatory mediators
    • Promotes atherosclerosis, atrial fibrillation via electrical remodeling and fibrosis
    • Contributes to diastolic dysfunction and HFpEF through stiffness and local inflammation
  • Landmark cardiovascular evidence: SELECT trial (Ryan, Ling, & Bray, 2022)
    • Over 17,000 patients; age > 45; BMI ≥ 27; established ASCVD; no diabetes
    • Weekly semaglutide 2.4 mg vs placebo; ~40 months follow-up
    • 20% reduction in major adverse cardiovascular events (MACE)
    • Proof that treating obesity reduces heart attack and stroke risk

This is a seminal shift confirming that effective obesity pharmacotherapy confers hard cardiovascular event reduction independent of diabetes status.

Heart Failure Prevention and Treatment: Stage A Risk Modification and HFpEF

Heart failure risk is elevated in obesity through epicardial fat effects, hypertension, and diabetes. Stage A heart failure—risk factors present without structural disease or symptoms—is common in midlife and is our window for prevention.

  • Stage A heart failure strategy.
    • Target weight loss: ≥ 10–15% for vascular and hemodynamic improvements
    • Four pillars
      • Nutrition: DASH and Mediterranean patterns emphasizing fruits, vegetables, lean protein, healthy fats, and reduced sodium
      • Physical activity: ≥ 150 minutes per week of moderate-intensity activity, plus resistance training
      • Sleep optimization: 7–8 hours nightly; screening and treatment for OSA
      • Pharmacological support: GLP-1 receptor agonists (e.g., semaglutide) to achieve meaningful weight loss; off-label application guided by risk profile
  • Symptomatic HFpEF: STEP-HFpEF trial (Kosiborod et al., 2023)
    • Semaglutide improved symptoms, physical function, quality of life, and weight
    • Supports GLP-1 therapy as a primary option for HFpEF management in obesity
  • Emerging evidence: tirzepatide (SUMMIT trial preliminary results)
    • Dual GIP/GLP-1 agonism shows impressive benefits for HFpEF, including reduced risk of death or worsening heart failure
    • Reinforces the metabolic-cardio synergy from incretin-based therapies

Dyslipidemia Management: ApoB, HDL, Triglycerides, and Weight-Driven Improvements

Obesity-related dyslipidemia includes high triglycerides, low HDL, and often a rise in small, dense LDL particles. Reducing adiposity transforms lipid profiles—lowering ApoB particle load and elevating HDL—particularly when combined with heart-healthy nutrition and exercise.

  • Clinical approach to dyslipidemia
    • Evaluate: fasting panels, ApoB, Lp(a), ASCVD risk calculator
    • Weight reduction: 5–15% reductions dramatically improve lipid metrics (Ryan & Yockey, 2017)
    • Nutrition: low-fat Mediterranean-style diet, very high in soluble fiber (oats, barley, beans, apples, psyllium) to bind and reduce cholesterol reabsorption (Freeman et al., 2017)
    • Physical activity: ≥ 150 minutes/week moderate intensity to improve HDL and insulin sensitivity
    • Pharmacotherapy: statins remain cornerstone; anti-obesity medications synergize lipid improvements by reducing adiposity

Hypertension in Obesity: Mechanisms and Dose-Response to Weight Loss

Hypertension risk rises with age and is strongly tied to excess weight. Obesity is responsible for a significant proportion of essential hypertension—approximately 78% in men and 65% in women.

  • Mechanisms (Hall et al., 2015)
    • Physical compression: visceral fat compresses kidneys; microvascular expansion is limited; peripheral resistance increases
    • Inflammation and vasoconstriction: adipose-derived cytokines inflame vessels and promote narrowing
    • Hormonal activation: RAAS upregulation leads to sodium and water retention
    • Increased cardiac output: greater force against arterial walls
  • Impact of weight loss
    • Framingham data: systolic pressure increased ~ 4 mmHg per 10 lbs gained; weight loss reverses trend
    • Meta-analysis: 3–9% weight loss reduces systolic and diastolic pressures by ~ 3 mmHg
    • Clinical goal: 10–15% weight reduction for significant blood pressure effects
    • DASH diet: cornerstone nutritional strategy; potassium, magnesium, calcium support; low sodium
  • Coordinated medication management
    • As blood pressure improves, deprescribing under medical direction prevents hypotension and adverse events.
    • Home monitoring enhances safety during weight-driven medication adjustments.

Insulin Resistance: Central Metabolic Dysfunction Driving Obesity, Diabetes, and Hypertension

Insulin resistance sits at the epicenter of obesity’s cardiometabolic cascade. Elevated free fatty acids, adipokine dysregulation, and chronic inflammation disrupt insulin signaling in muscle and liver, leading to hyperinsulinemia—the biochemical environment of constant storage.

  • Physiologic underpinnings (Lin & Li, 2021)
    • Enlarged adipocytes leak free fatty acids, exacerbating hepatic triglyceride synthesis.
    • Hyperinsulinemia promotes lipogenesis and inhibits lipolysis
    • High insulin increases hunger (reactive hypoglycemia), cravings, and reduces metabolic rate
    • Elevated insulin drives renal sodium retention and vascular smooth muscle proliferation
  • Evaluation and early identification
    • Fasting insulin with glucose; HOMA-IR calculation
    • METS-IR and related indices; mortality associations highlight risk even before diabetes diagnosis (Li et al., 2023)
  • Therapeutic strategies
    • Lower-carbohydrate nutrition: reduces glycemic load, insulin demand, hepatic glucose output; shifts metabolism from storage to oxidation
    • Resistance training: increases GLUT4 translocation; enhances insulin sensitivity; preserves muscle
    • Chiropractic integration: autonomic modulation; pain reduction facilitating activity; movement quality and function
    • Pharmacotherapy: metformin (hepatic glucose production reduction); incretin-based therapies (GLP-1, dual GIP/GLP-1) for weight loss and insulin sensitivity

Understanding insulin resistance explains why “eat less, move more” often fails without hormonal recalibration; integrative strategies restore physiologic balance.

MASLD and MASH: Modern Liver Disease Nomenclature and Treatment

The shift to Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD) and Metabolic Dysfunction-Associated Steatohepatitis (MASH) emphasizes metabolic drivers over exclusion of alcohol. Obesity and insulin resistance are central to these liver conditions.

  • Prevalence and risk progression
    • Over two-thirds of MASLD patients have obesity.
    • MASH involves inflammation and hepatocyte injury; fibrosis progression increases risks for cirrhosis and hepatocellular carcinoma
  • Screening and evaluation (AASLD guidance reflected across practice)
    • Liver enzymes: ALT greater than AST is a common pattern
    • Imaging: review for hepatic steatosis on prior studies
    • FIB-4 score: age, AST, ALT, platelets; stratifies risk; high-risk thresholds prompt FibroScan referral
  • Treatment strategy
    • Weight reduction: ≥ 10% weight loss can resolve steatohepatitis and improve fibrosis.
    • Nutrition: Mediterranean-style, lower-carbohydrate, lower-fat pattern emphasizing whole foods
    • Physical activity: aerobic and resistance training; muscle mass improves insulin sensitivity
    • Supplementation: vitamin E in selected biopsy-proven MASH without diabetes
    • Pharmacotherapy: GLP-1 and dual GIP/GLP-1 agonists reduce liver fat via weight loss; ongoing trials
    • New FDA-approved therapy: resmetirom (Rezdiffra) for MASH with F2–F3 fibrosis (MAESTRO-NASH trial evidence)

Our approach addresses the metabolic roots—weight loss and insulin sensitivity are central levers in liver recovery.

Chronic Stress, Depression, and Obesity: Neurobiology of Eating Behavior and Adherence

Stress and depression profoundly influence obesity through neurohormonal, cognitive, and behavioral pathways. Chronic stress alters hunger and satiety, impairs executive function, and increases the brain’s reward response to palatable foods; cortisol promotes visceral adiposity and insulin resistance.

  • Overlapping epidemics
    • CDC data: 43% of adults with depression are obese (Pratt & Brody, 2014)
    • Bidirectional relationship; mood disorders increase risk for obesity and vice versa
  • Screening and holistic support
    • PHQ-9 for depression; GAD-7 for anxiety; PSS for stress
    • Sleep optimization: improved architecture reduces insulin resistance and cortisol
    • Nutrition and movement: whole-food patterns and gentle exercise improve mood and cognition
    • Therapy and social support: counseling for coping skills; reduce weight bias traumas
    • Pharmacotherapy: careful use with mental health providers; avoid weight-promoting agents when possible
  • Weight bias in medicine
    • Patients commonly report stigma and dismissal; we create safe, empathetic environments.
    • Validating experiences and listening deeply builds trust and improves adherence.

Chiropractic care reduces pain, improves mobility, and modulates autonomic tone—loosening stress’s grip and enabling consistent engagement with health behaviors.

Musculoskeletal Pain and Mobility: Biomechanics, Inflammation, and Integrative Rehabilitation

Chronic pain and mobility loss in midlife often stem from the dual burden of mechanical overload and metabolic inflammation. Obesity multiplies joint forces and inflames cartilage through cytokines.

  • Joint loading mechanics
    • Walking: knee force ~ 3x body weight
    • Stairs: ~ 6x body weight
    • Jumping: ~ 10x body weight
    • A 250-pound person experiences ~ 750 lbs across the knees while walking; ~ 1,500 lbs on stairs; ~ 2,500 lbs when jumping
  • Clinical evaluation
    • Mobility, strength, balance testing
    • Timed Get-Up-and-Go test for functional capacity and fall risk
    • Pain scales; imaging as indicated
  • Integrative chiropractic and physical therapy
    • Adjustments: restore joint mechanics; reduce nociception; improve spinal alignment
    • Physical therapy: strengthen musculature; improve range; teach body mechanics
    • Non-weight-bearing exercise: swimming, water aerobics, cycling to protect joints while improving cardiovascular health
  • Osteoarthritis and weight loss: STEP 9 trial (Lundsgaard et al., 2023)
    • Semaglutide reduced weight and significantly lowered knee osteoarthritis pain compared to placebo
    • Supports pharmacotherapy as a pain-reduction strategy via adiposity reduction and decreased inflammatory signaling

In my clinical work, combining manual therapy, graded rehabilitation, and weight loss produces rapid improvements in mobility and pain that empower long-term adherence.

Obstructive Sleep Apnea: A “Fat Mass Disease” with Systemic Metabolic Consequences

Obstructive sleep apnea (OSA) is prevalent in obesity due to fat deposits around the upper airway, reduced muscle tone, and external compression of the chest and lungs. Repeated apneas fragment sleep, lower oxygen saturation, and drive sympathetic activation and insulin resistance.

  • Screening and diagnosis
    • STOP-BANG questionnaire; Epworth Sleepiness Scale
    • Referral for polysomnography (PSG); Apnea-Hypopnea Index (AHI) staging: mild (5–15), moderate (15–30), severe (> 30)
  • Treatment strategies
    • Weight reduction: 5–15% weight loss lowers AHI; mild OSA may resolve
    • CPAP compliance: mask fit, humidification, pressure titration; device usage tracking
    • Pharmacotherapy: tirzepatide FDA indication for moderate-to-severe OSA in adults with obesity (SURMOUNT-OSA trials) (Malhotra et al., 2024)
  • Chiropractic considerations
    • Cervical and thoracic mobility; soft tissue techniques ease CPAP comfort
    • Breathing mechanics and rib cage mobility exercises improve respiratory function and sleep posture tolerance

Improving sleep restores metabolic regulation—leptin, ghrelin, cortisol, and insulin sensitivity—and dramatically elevates daytime energy for exercise and meal preparation.

Landmark Trials Overview: Evidence Backbone of Modern Obesity Medicine

A brief synthesis of key trials guiding our protocols:

  • Cardiovascular outcomes
    • SELECT: Semaglutide reduced MACE by 20% in overweight/obesity patients with established ASCVD and no diabetes (Ryan, Ling, & Bray, 2022)
  • Heart failure
    • STEP-HFpEF: Semaglutide improved symptoms, function, quality of life, and weight in HFpEF with obesity (Kosiborod et al., 2023)
  • Prediabetes and diabetes progression
    • SURMOUNT-1: Tirzepatide reduced progression to type 2 diabetes by ~ 94% over three years in prediabetes and produced ~ 22.9% average weight loss (Wharton et al., 2023)
  • Obesity treatment without diabetes
    • STEP 1: Semaglutide achieved ~ 14.9% average weight loss; 86.4% of prediabetes cases returned to normoglycemia (Wilding et al., 2021)
  • Sleep apnea
    • SURMOUNT-OSA: Tirzepatide significantly reduced AHI in OSA with obesity; led to FDA indication (Malhotra et al., 2024)
  • Osteoarthritis
    • STEP 9: Semaglutide improved weight and reduced knee osteoarthritis pain (Lundsgaard et al., 2023)
  • Liver disease
    • MAESTRO-NASH: Resmetirom approved for MASH with F2–F3 fibrosis, initiating a specialized pathway for true liver pharmacotherapy

These trials show that effective obesity treatment is disease-modifying across cardiometabolic and functional domains.

Case Study: “Robert” — Integrated Management of Type 2 Diabetes, Obesity, Sleep Apnea, Hyperlipidemia, Hypertension, Knee Osteoarthritis, and Low Libido

Robert is a 55-year-old Mexican American male and data analyst with Class III obesity, type 2 diabetes, hyperlipidemia, hypertension, knee osteoarthritis, and obstructive sleep apnea with poor CPAP adherence. He reported daytime fatigue, joint pain limiting exercise, and low libido. His weight gain began in his thirties with decreasing activity due to knee pain and a sedentary job. He often skipped breakfast, ate large portions, and had intense evening sweet cravings.

  • Initial medications
    • Metformin 1000 mg twice daily
    • Glipizide 10 mg daily
    • Lisinopril 20 mg daily
    • Rosuvastatin 20 mg daily
  • Baseline findings
    • Weight: 275 lbs; BMI: 40.6 kg/m²
    • Waist circumference: 43 inches
    • Blood pressure: 148/92 mmHg
    • HbA1c: 8.5%; fasting glucose: 180 mg/dL
    • Lipids: triglycerides 250 mg/dL; HDL 35 mg/dL; LDL 140 mg/dL
    • Liver enzymes: AST 55 U/L, ALT 65 U/L
    • Total testosterone: 250 ng/dL
    • STOP-BANG: 6 (high risk)
    • PHQ-9: 7 (mild depression)
    • FIB-4: indeterminate
    • Stage A heart failure risk
  • Integrated four-pillar plan
    • CPAP optimization: mask fit, humidification, pressure titration, device usage monitoring
    • Nutrition: low-carbohydrate, higher-protein, high-fiber whole-food pattern; eliminate ultra-processed foods
    • Physical activity: low-impact cardio (cycling, swimming), graded strengthening, joint-protective movement patterns
    • Medication management under Dr. Cardenas
      • Discontinue glipizide to avoid hypoglycemia with incretin therapy
      • Initiate tirzepatide; continue metformin, statin, and lisinopril
      • Monitor side effects; gradual titration toward effective dose
  • Sexual health approach
    • Address microvascular endothelial dysfunction with improved glycemic control and blood pressure
    • Lower inflammation via adiposity reduction; improve mood and energy through sleep optimization and movement
    • Provide mental health support; set realistic expectations
  • Three-year outcomes
    • 3% total body weight reduction; waist circumference markedly improved
    • Blood pressure decreased; A1c lowered from 8.7% with early improvements within the first year
    • Triglycerides lowered; lipid profile improved
    • Knee pain reduced with weight loss; greater exercise adherence
    • Substantial quality of life improvements

My chiropractic interventions supported Robert’s adherence by reducing pain and improving movement mechanics, while medical oversight ensured safe deprescribing and titration. Robert’s case exemplifies the synergy between mechanical and metabolic care.

Sarcopenic Obesity: Hidden Epidemic Driving Frailty, Diabetes, and Functional Decline

Sarcopenic obesity combines reduced muscle mass and strength with increased fat mass, especially visceral adipose tissue. Chronic inflammation from adipose tissue catabolizes muscle, reducing resting metabolic rate and accelerating fat accumulation. Weight cycling history worsens this phenotype.

  • Prevalence
    • Nearly 16% across all adults; 8% among ages 20–60; over 28% in those > 60
    • Elevated rates in prediabetes (~ 20%), type 2 diabetes (~ 35%), MASLD (~ 25%), and post-bariatric surgery (~ 22%)
    • Stark disparities: Mexican American women > 60 have reported rates as high as ~ 66.6%
  • Symptoms
    • Exhaustion, weakness, “hard to move,” perceived limitation in function
  • Assessment
    • Muscle function tests: grip strength, sit-to-stand
    • Body composition: BIA or DEXA for precise measurement; VAT quantification; motivational benchmarks for patients
  • Treatment plan
    • Physical activity: cardiometabolic targets; resistance training ≥ 2 times/week; PT referral using sarcopenia diagnosis codes
    • Nutrition: 1.0–1.5 g/kg ideal body weight protein; space protein every 3–4 hours; emphasize animal proteins; leucine and vitamin D whey shakes
    • Inflammation reduction: whole-food patterns, micronutrient assessment
    • Pharmacotherapy: anti-obesity medications when indicated; prioritize muscle-preserving strategies

Chiropractic supports movement quality and pain reduction, enabling consistent resistance training critical for reversing sarcopenic obesity.

Case Study: “Maggie” — Perimenopausal Insulin Resistance, Prediabetes, and Abdominal Adiposity

Maggie is a 53-year-old CPA experiencing perimenopausal symptoms, gradual weight gain, and increasing abdominal adiposity. She is part of the sandwich generation and reports daily wine intake to cope with stress. Her labs and biometrics show a progressive trajectory from optimal to prediabetes over three years.

  • Data trajectory (50 to 53 years)
    • Weight: 135 → 157 lbs; BMI: 23.2 → 27.5
    • Waist circumference: 33 → 36.5 inches (> 35 cutoff for women)
    • HbA1c: 5.2% → 5.8% (prediabetes)
    • Fasting glucose: 88 → 104 mg/dL
    • LDL-C: 95 → 130 mg/dL
    • Fasting insulin: increased to 11.7 μU/mL (> 7 is concerning for insulin resistance)
  • Diagnoses
    • Overweight/Early Class I Obesity; abdominal adiposity
    • Prediabetes with significant insulin resistance
    • Hyperlipidemia
    • Well-controlled hypothyroidism
  • Stepwise plan
    • Nutrition: lower carbohydrates; 90–100 g protein/day; high intake of vegetables and fruits; reduce nightly wine
    • Physical activity: increase intensity beyond dog-walking; begin resistance training 1–2 sessions weekly
    • Medical strategies
      • Metformin ER: start 500 mg with evening meal; gentle titration after tolerance
      • Re-evaluate gabapentin for VMS; consider taper if ineffective or contributing to weight gain.
      • Consider menopausal hormone therapy for VMS and insulin sensitivity
      • Sleep hygiene; potential CBT-I referral
      • Anti-obesity medications if insufficient progress at 3–6 months
  • Key clinical insight
    • Do not ignore progressive metabolic decline; intervene early with integrated nutrition, movement, sleep, and pharmacologic supports.

Chiropractic care prepares the musculoskeletal system for safe exercise, reducing injury risk and speeding functional gains.

Case Study: “Maria” — Post-MI, Type 2 Diabetes on Insulin, MASLD, Severe Knee Osteoarthritis, Sarcopenic Obesity

Maria is a 59-year-old health executive with a myocardial infarction history, uncontrolled type 2 diabetes, hypertension, dyslipidemia, MASLD, and severe bilateral knee osteoarthritis. She is on insulin therapy without GLP-1 therapy, and her body composition reveals extremely high fat mass and low muscle mass.

  • Baseline metrics
    • BMI: 35.7 (Class II Obesity)
    • HbA1c: 7.4%
    • Triglycerides: 256 mg/dL; HDL: 37 mg/dL
    • Elevated ALT/AST consistent with MASLD
    • DEXA: body fat 57.8%; muscle mass in 4th percentile; VAT 3.4 liters; waist 43.5 inches
  • Diagnoses
    • Class II Obesity with sarcopenic obesity
    • Uncontrolled type 2 diabetes
    • Hypertension; dyslipidemia, hypertriglyceridemia
    • MASLD
    • Severe knee osteoarthritis
  • Integrated plan
    • Nutrition: significant carbohydrate reduction; protein elevation; anti-inflammatory whole-foods pattern
    • Physical therapy: sarcopenia and osteoarthritis program; strengthen supporting musculature; pain-mitigating modalities
    • Orthopedic referral: injections or total knee replacement candidacy assessment; advocate against bias
    • Chiropractic and rehabilitation: gentle adjustments; peripheral soft tissue therapies; adjunct modalities for pain relief; graded loading
    • Medication management
      • Start GLP-1 receptor agonist (semaglutide): indicated for ASCVD risk reduction post-MI
      • Taper and discontinue insulin as glycemic control improves to avoid weight-promoting effects
      • Maintain statin and antihypertensives under medical oversight
    • Physical activity: non-impact cardio (swimming, water aerobics, stationary cycling); PT-guided resistance training
  • Advocacy against bias
    • Older women with obesity often face dismissal or minimized options
    • Our team communicates expectations to specialists and supports the patient through decisions, ensuring equitable, evidence-based care

For Maria, aligning pharmacotherapy, PT, and chiropractic care accelerates weight loss, reduces VAT, lowers triglycerides, and restores mobility.

Menopause and Metabolic Health: Vasomotor Symptoms, Central Adiposity, Insulin Resistance, and Bone-Muscle Changes

Menopause introduces systemic shifts that elevate cardiometabolic risk: rising LDL-C, insulin resistance, central fat accumulation, muscle loss, and bone remodeling changes that predispose to osteoporosis. Vasomotor symptoms correlate with weight gain and increased waist circumference, and sleep disruption worsens metabolic dysfunction.

  • Observed patterns
    • Weight gain across menopausal stages even without lifestyle change; maintenance requires adjustments.
    • Shift toward android fat distribution; reduced lean mass
    • Declines in moderate-to-vigorous activity due to pain, fatigue, stress
  • Clinical priorities
    • Prevent additional weight gain
    • Reduce visceral adiposity; preserve or increase muscle; protect bone density.
    • Improve sleep, mood, and VMS; enhance functional capacity
  • Strategy principle: treat obesity first
    • Lifestyle interventions: nutrition, activity, behavioral counseling, sleep and stress management
    • Pharmacotherapy: select anti-obesity medications (GLP-1 or dual GIP/GLP-1) per eligibility; avoid weight-promoting medications when viable; consider menopausal hormone therapy (NAMS, ACOG guidance)
    • Monitor cardiometabolic metrics and body composition
  • Protein and anabolic resistance
    • Higher protein intake needed to overcome anabolic resistance and support muscle synthesis
    • Distribute protein across meals; combine with resistance training for maximal effect.

Chiropractic integration reduces musculoskeletal barriers, optimizes posture and movement, and may modulate autonomic balance contributing to VMS and sleep improvements.

Exercise Prescription: Low-Impact Cardiovascular Training, Resistance Sessions, and Movement Quality

Exercise is medicine for obesity, diabetes, sarcopenic obesity, and menopause-related changes. Our prescriptions emphasize safety, progression, and neuromuscular quality.

  • Aerobic targets (Piercy et al., 2018)
    • 150–300 minutes per week moderate intensity or 75–150 minutes vigorous intensity
    • Spread sessions across the week; exceeding 300 minutes yields additional benefit
  • Resistance training
    • At least two sessions per week
    • Focus on posterior chain strength, core stability, and upper-body compound movements.
    • Closed-chain lower extremity exercises to reduce patellofemoral stress
  • Chiropractic role
    • Spinal and extremity adjustments optimize joint mechanics and motor control.
    • Myofascial techniques reduce pain and improve tissue pliability
    • Kinesiology taping and bracing for kinesthetic cues and offloading
    • Breathing mechanics training supports CPAP tolerance and exercise capacity
  • Mechanistic rationale
    • Resistance work stimulates mechanotransduction in cartilage and bone; improves insulin sensitivity via GLUT4
    • Graded exposure reduces fear-avoidance and central sensitization; improves resilience and adherence.

Nutrition Therapy: Lower Carbohydrates, Higher Protein, High Fiber, Whole-Food Emphasis

We prioritize dietary strategies that reduce insulin demand, improve satiety, preserve muscle, and lower inflammation.

  • Core principles
    • Lower-carbohydrate approach: mitigate postprandial hyperglycemia and hepatic glucose output
    • Higher protein: increase thermic effect; support muscle protein synthesis; counter anabolic resistance
    • High fiber: slow gastric emptying; blunt glycemic excursions; improve gut microbiota; enhance satiety
    • Whole-foods foundation: vegetables, fruits, lean proteins, healthy fats, legumes as tolerated
    • Limit ultra-processed foods: reduce emulsifiers and additives linked to hyperphagia and metabolic disruption.
  • Whey protein supplementation
    • Practical tool for busy patients; leucine-enriched shakes with vitamin D to potentiate muscle synthesis
  • Functional medicine integration
    • Assess micronutrient status (magnesium, vitamin D) and inflammatory markers.
    • Tailor nutrition to individual biochemistry and preferences; build sustainable patterns.

Sleep Optimization and Stress Management: Foundations of Metabolic Control

Sleep quality and stress resilience are indispensable for glycemic control, appetite regulation, and mood. We coach practical sleep hygiene and stress-downregulation methods.

  • Sleep strategies (St-Onge et al., 2017)
    • CPAP adherence for OSA; mask fit adjustments; humidification; pressure optimization
    • Sleep hygiene: consistent schedules; light management; cool temperatures; minimize stimulants
    • CBT-I referral for insomnia; leverage non-pharmacological gold-standard therapy
  • Stress reduction
    • Breathing exercises and biofeedback to reduce sympathetic dominance
    • Gentle mobility practices to relieve muscle tension
    • Chiropractic care reduces nociceptive stress; improves autonomic balance; supports restorative sleep

These foundations stabilize hormones (cortisol, ghrelin, leptin), restore appetite regulation, and improve energy for activity and self-care.

Pharmacotherapy Integration: Incretin-Based Therapies, Metformin, Statins, Antihypertensives, and MHT

We align pharmacotherapy with clinical goals and minimize weight-promoting effects.

  • Anti-obesity medications
    • GLP-1 receptor agonists (semaglutide): significant weight loss; cardiovascular risk reduction (SELECT)
    • Dual GIP/GLP-1 receptor agonists (tirzepatide): profound weight loss; reduced diabetes progression (SURMOUNT-1); OSA indication (SURMOUNT-OSA)
    • Titration schedules and side effect monitoring; hydration and gallbladder considerations
  • Diabetes management
    • Metformin ER: reduces hepatic glucose output; improves insulin sensitivity
    • Deprescribing sulfonylureas (e.g., glipizide) when starting incretins to avoid hypoglycemia
    • Careful tapering of insulin when initiating GLP-1 therapy in obesity to avoid weight promotion
  • Cardiovascular risk
    • Statins: LDL lowering and ASCVD risk reduction remain foundational
    • Antihypertensives: RAAS inhibitors (e.g., lisinopril) protect kidneys and lower blood pressure; adjust dosing as weight reduces
  • Menopausal hormone therapy (NAMS, ACOG)
    • Consider for VMS relief and insulin sensitivity improvements when indicated.
    • Balance risks and benefits with shared decision-making

Our medical oversight ensures safety through lab monitoring, side-effect management, and logical sequencing of agents to maximize efficacy.

Monitoring and Outcomes: Data-Driven Care Pathways

We continuously track objective metrics to demonstrate progress and guide adjustments.

  • Metabolic and cardiovascular measures
    • Weight, BMI, waist circumference
    • Blood pressure; lipids (LDL, HDL, triglycerides); ApoB; Lp(a) when indicated
    • A1c; fasting glucose; fasting insulin; HOMA-IR
    • Liver enzymes; FIB-4 score; imaging for MASLD/MASH when needed
    • CAC scoring in select high-risk cases
  • Functional and sleep metrics
    • Pain scales; mobility tests; Get-Up-and-Go timing
    • Exercise session logs; steps; heart rate recovery
    • CPAP usage duration and residual AHI from device reports
    • Quality of life indices and symptom checklists (including VMS)
  • Behavioral tracking
    • Nutrition adherence; sleep duration; stress scores
    • Motivational interviewing and habit scaffolding to maintain momentum

Collaborative Workflow: Roles of Dr. Cardenas and Dr. Jimenez

Our clinic operates through a coordinated, patient-centered workflow ensuring safety, efficacy, and alignment across modalities.

  • Dr. Cardenas
    • Internal medicine diagnostics; lab interpretation; pharmacotherapy guidance
    • Cardiometabolic risk management; deprescribing; complex case oversight
  • Dr. Jimenez
    • Chiropractic neuromusculoskeletal assessments; adjustments; manual therapies
    • Rehabilitation planning; movement re-education; pain science integration
    • Functional medicine evaluation; nutrition planning; sleep and stress coaching
  • Joint case reviews
    • Align priorities; refine interventions; co-manage specialist referrals
    • Support patient advocacy across disciplines and address healthcare bias

Clinical Observations from Practice: Movement Quality Enables Metabolic Success

Across sciatica.clinic and my professional updates on LinkedIn, I’ve documented how integrative chiropractic care creates the scaffold for consistent application of nutrition, sleep, and pharmacotherapy:

  • Pain reduction and joint mechanics restore confidence and capacity for daily activities and structured exercise
  • Autonomic modulation reduces sympathetic drive, supporting improved sleep, reduced stress, and better appetite regulation.
  • Movement control training improves efficiency and reduces compensatory patterns, enhancing adherence and outcomes.
  • Patients report earlier improvements in energy and mood when pain is addressed, reinforcing healthy habits.

When mobility improves, patients can prepare meals, attend therapy sessions, adhere to CPAP, and maintain exercise routines—converting clinical plans into durable health gains.

Practical Tips for Patients: Start Today, Build Momentum

  • Improve CPAP use
    • Check mask fit; humidification; nightly duration; device-reported AHI
  • Focus meals on protein and plants
    • Build plates around lean protein, vegetables, and high-fiber foods
  • Start low-impact activity
    • Daily movement; gradually add resistance training
  • Track progress
    • Sleep, exercise, meals; celebrate milestones (5%, 10%, 15% weight loss)
  • Ask for help
    • Share challenges early; our team adapts plans quickly and safely

Integrative Pearls for Clinicians: Align Musculoskeletal and Metabolic Care

  • Treat obesity first in menopausal care—benefits ripple across vasomotor symptoms, sleep, and mood
  • Avoid weight-promoting medications where possible; transition thoughtfully to metabolic-friendly regimens
  • Use objective metrics and share progress visually to reinforce patient motivation
  • Collaborate across disciplines—chiropractic, internal medicine, PT, sleep medicine—to ensure safety and comprehensive care
  • Address weight bias proactively—validate patient experiences and champion equitable treatment options

Conclusion: Evidence-Based Integration Transforms Midlife Health

Integrating chiropractic care, internal medicine oversight, functional medicine, rehabilitation, and targeted pharmacotherapy creates durable improvements for complex conditions in midlife—type 2 diabetes, sleep apnea, obesity, knee osteoarthritis, MASLD/MASH, hypertension, dyslipidemia, HFpEF, depression, stress, and menopausal changes. With clear goals, consistent support, and patient advocacy, we restore metabolic flexibility, reduce adiposity, preserve muscle, protect joints, and profoundly improve quality of life.

References

SEO tags: integrative chiropractic care, internal medicine oversight, El Paso injury medical clinic, Dr Alex Jimenez, Dr Maria Guadalupe Cardenas MD, obesity treatment, insulin resistance, type 2 diabetes, hypertension, dyslipidemia, cardiometabolic syndrome, epicardial fat, HFpEF, semaglutide, tirzepatide, SURMOUNT-1, SURMOUNT-OSA, SELECT trial, STEP trials, MAESTRO-NASH, MASLD, MASH, resmetirom, sleep apnea CPAP optimization, osteoarthritis pain reduction, knee OA, resistance training, low carbohydrate diet, high protein nutrition, functional medicine, personal injury care, rehabilitation, sciatica clinic, menopause weight gain, vasomotor symptoms, central adiposity, sarcopenic obesity, DEXA body composition, ApoB, Lp(a), CAC scoring, DASH diet, Mediterranean diet, stress and depression screening, PHQ-9, GAD-7, CBT-I, autonomic modulation

Regenerative Therapies for Gut Health and Healing

Regenerative Therapies for Gut Health and Healing

Regenerative Therapies for Gut Health: BPC-157, Leaky Gut, and Integrative Chiropractic Care

Abstract

Can regenerative therapies help improve gut health? Emerging research suggests that regenerative medicine may eventually offer new ways to support the repair of damaged intestinal tissue, restore the mucosal lining, regulate inflammation, and improve the environment in which intestinal stem cells function. Researchers are studying stem cells, organoids, microbiome-based treatments, immune therapies, and specialized peptides for these purposes.

One peptide receiving attention is BPC-157, or Body Protection Compound-157. Laboratory and animal studies suggest that BPC-157 may support cytoprotection, blood vessel formation, epithelial repair, and control of excessive inflammation. These effects have created interest in BPC-157 for increased intestinal permeability, commonly called “leaky gut.” However, most evidence for BPC-157 remains preclinical, human research is limited, and BPC-157 is not currently an FDA-approved drug.

At Injury Medical Clinic PA in El Paso, Texas, a multidisciplinary model combines the clinical perspectives of Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, and Dr. Maria Guadalupe Cardenas, MD, a physician with more than 40 years of internal medicine experience. This approach brings together medical oversight, integrative chiropractic care, functional medicine, rehabilitation, personal injury care, and other appropriate services while keeping experimental regenerative treatments within proper medical and regulatory boundaries.

Regenerative Therapies for Gut Health and Healing

Can Regenerative Medicine Help the Gut Heal?

The short answer is possibly, but much of the science is still developing.

The intestinal lining is not a passive wall. It is an active layer of cells that helps:

  • Absorb nutrients.
  • Keep harmful substances out of the bloodstream.
  • Communicate with the immune system.
  • Interact with trillions of microorganisms.
  • Replace damaged intestinal cells.
  • Regulate inflammation.

The intestinal epithelium normally renews itself rapidly. Intestinal stem cells help produce the new cells needed to maintain this barrier. Research funded by the California Institute for Regenerative Medicine has explored stem cells and stem-cell-derived intestinal organoids as possible ways to restore damaged epithelial tissue in inflammatory bowel disease (California Institute for Regenerative Medicine [CIRM], n.d.).

This does not mean stem-cell therapy is currently a routine treatment for “leaky gut.” It means scientists are learning how regenerative biology may eventually help restore injured intestinal tissue.

The Gut Lining Is a Regenerative Organ

Every day, the digestive tract faces stomach acid, digestive enzymes, food particles, bacteria, medications, alcohol, inflammatory chemicals, and mechanical stress.

Fortunately, the intestine has its own repair system.

Intestinal stem cells continuously produce new epithelial cells. Newer research also shows that the gut microbiome may influence how well these stem cells work.

A 2026 report from the International Society for Stem Cell Research described animal research showing that age-related changes in gut bacteria reduced intestinal stem-cell activity. When researchers restored a more youthful microbial environment in older mice, intestinal stem-cell activity and tissue regeneration improved (International Society for Stem Cell Research [ISSCR], 2026).

Other research has found that metabolites produced by gut bacteria may stimulate intestinal stem cells and strengthen the intestinal barrier after major medical treatments such as radiation and stem-cell transplantation (Leibniz Institute for Immunotherapy, 2025).

Together, these findings suggest that regeneration, the microbiome, immune function, and the intestinal barrier are closely connected.

What Is “Leaky Gut”?

The term leaky gut is commonly used to describe increased intestinal permeability.

Normally, cells lining the intestine form a carefully controlled barrier. Tight junctions between these cells help determine what passes through the intestinal wall.

When this barrier is injured, or its regulation changes, substances from the intestinal contents may cross the barrier more easily.

Possible contributors include:

  • Intestinal inflammation.
  • Certain infections.
  • Alcohol exposure.
  • Some medications, including NSAIDs.
  • Changes in gut bacteria.
  • Poor nutrition.
  • Chronic gastrointestinal disease.
  • Severe illness or medical treatment.

Increased permeability has been studied in inflammatory and gastrointestinal disorders, but “leaky gut syndrome” should not be treated as a stand-alone diagnosis without determining why the intestinal barrier may be abnormal.

This is where a proper medical evaluation becomes important.

BPC-157: A Gastric-Protective Peptide Undergoing Research

BPC-157 is a synthetic peptide made from a sequence of 15 amino acids related to compounds studied in gastric tissues.

The peptide has attracted attention because preclinical research suggests that it may influence several healing pathways.

These include:

  • Cytoprotection: helping cells tolerate injury.
  • Angiogenesis: supporting formation of new blood vessels.
  • Fibroblast activity: helping cells involved in repair.
  • Collagen production: supporting tissue structure.
  • Nitric oxide signaling: influencing blood vessels and tissue protection.
  • Inflammatory signaling: potentially controlling excessive inflammatory activity.
  • Epithelial healing: supporting repair of surface tissues.

A 2020 review by Park et al. examined experimental evidence suggesting that BPC-157 could protect gastrointestinal tissues from NSAID-related injury and stabilize intestinal permeability. The authors discussed BPC-157 as a possible cytoprotective compound for gastrointestinal injury, but much of the evidence came from experimental models rather than large human clinical trials (Park et al., 2020).

A broader 2026 review also reported that animal studies have shown BPC-157 activity involving gastrointestinal healing, angiogenesis, collagen production, cell migration, and inflammatory pathways. Importantly, the authors stressed that human data remain very limited and that many proposed benefits are not yet clinically proven (Yuan et al., 2026).

How Might BPC-157 Affect the Intestinal Epithelium?

Think of the intestinal lining like a tightly connected tile floor.

If the tiles become damaged and the connections between them weaken, the barrier becomes less effective.

Experimental BPC-157 research suggests several possible ways the peptide could influence this repair process.

Supporting epithelial cell repair

Experimental studies have associated BPC-157 with pathways involved in cell migration and tissue rebuilding.

Supporting blood flow

Healing tissue needs oxygen and nutrients. BPC-157 appears to influence VEGF-related signaling and blood-vessel development in preclinical models (Yuan et al., 2026).

Modulating inflammation

A damaged intestinal barrier can activate immune responses. Experimental studies suggest BPC-157 may influence inflammatory cytokines rather than functioning simply as a traditional anti-inflammatory medication.

Protecting the gastrointestinal lining

Animal studies have reported protective effects in the stomach, esophagus, small intestine, and other gastrointestinal tissues.

These findings help explain why BPC-157 is being investigated for intestinal permeability. They do not, however, establish that BPC-157 is a proven treatment for human leaky gut, Crohn’s disease, ulcerative colitis, IBS, ulcers, or other gastrointestinal diseases.

Patient-education sources discussing BPC-157 appropriately describe the peptide as promising but unproven, since large controlled human studies are still lacking (Ubie Health, n.d.; Tucson Wellness MD, n.d.).

Regenerative Medicine Goes Beyond BPC-157

BPC-157 is only one small part of the larger regenerative-medicine field.

Researchers are investigating several ways to help damaged digestive tissue repair itself.

Intestinal stem cells and organoids

Scientists can grow miniature intestinal structures called organoids from stem cells. These models allow researchers to study epithelial repair and may one day contribute to treatments designed to replace severely damaged intestinal tissue (CIRM, n.d.).

Microbiome-based regeneration

The microbiome produces metabolites that interact with immune cells and intestinal stem cells. Williams et al. (2023) described the microbiome as a possible regenerative medicine target because microbial changes can affect inflammatory, metabolic, immune, and neurological pathways throughout the body.

Cellular therapies

Mesenchymal stromal or stem cells are being studied for their ability to influence inflammatory signaling, immune regulation, blood-vessel growth, and tissue repair. Research into disorders such as gastroparesis remains experimental, and commercial descriptions should not be mistaken for proof of effectiveness (Stemwell, 2025).

Emerging immune-based regeneration

Researchers have even used CAR T-cell technology experimentally to remove aging cells that interfere with intestinal regeneration. In mice, the approach improved epithelial healing, nutrient absorption, and inflammation. Early laboratory findings in human intestinal cells were also encouraging, but this remains research rather than routine gastrointestinal treatment (Cold Spring Harbor Laboratory, 2026).

Could Better Gut Integrity Reduce Whole-Body Inflammation?

Possibly.

The gut interacts continuously with the immune system. When the intestinal barrier, microbiome, and immune response become disturbed, inflammatory signaling may extend beyond the digestive tract.

Gut dysbiosis has been associated with inflammatory and autoimmune conditions, and diets high in processed foods and added sugars may contribute to microbiome changes and systemic inflammation (Williams et al., 2023).

This creates an important goal for integrative care: do not focus only on a peptide.

A broader program may examine:

  • Food quality and dietary patterns.
  • Protein and micronutrient intake.
  • Fiber tolerance.
  • Hydration.
  • Sleep.
  • Stress.
  • Medication use.
  • Metabolic health.
  • Physical activity.
  • Gastrointestinal disease.
  • Infection or dysbiosis when clinically appropriate.

The goal is to improve the environment in which normal tissue repair takes place.

Where Integrative Chiropractic Care Fits

Chiropractic treatment should not be described as directly sealing intestinal tight junctions or curing intestinal disease.

Its role is different.

Dr. Alex Jimenez’s published clinical observations emphasize combining the biological side of healing with the mechanical side of recovery. Regenerative strategies may address tissue biology, while chiropractic care and rehabilitation focus on mobility, joint mechanics, posture, strength, and movement patterns (Jimenez, 2026a, 2026b).

For someone experiencing both musculoskeletal problems and gastrointestinal concerns, integrative chiropractic care may therefore be one part of a broader plan that includes:

  • Improving spinal and joint mobility.
  • Reducing musculoskeletal limitations to physical activity.
  • Correcting movement problems after injury.
  • Progressive rehabilitation and exercise.
  • Nutritional and functional medicine evaluation.
  • Medical review of medications and chronic disease.
  • Appropriate laboratory testing.
  • Gastroenterology referral when needed.
  • Monitoring for warning signs requiring conventional medical treatment.

Dr. Jimenez describes this multidisciplinary approach as treating the patient from more than one clinical angle rather than expecting one treatment to solve every problem.

Medical Oversight: Dr. Maria Guadalupe Cardenas and Dr. Alex Jimenez

At Injury Medical Clinic PA in El Paso, Texas, Dr. Maria Guadalupe Cardenas, MD, works alongside Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN.

Dr. Cardenas has more than 40 years of medical experience and practices in internal medicine. Clinic materials identify her as the Medical Director and Collaborative Physician, while Dr. Jimenez serves in integrative chiropractic, advanced-practice nursing, functional medicine, injury care, and rehabilitation.

This type of multidisciplinary arrangement can provide several layers of care:

  • Internal medicine oversight: medical diagnosis, medication review, risk assessment, chronic-disease management, and referral.
  • Integrative chiropractic care: spinal and joint evaluation, mobility, biomechanics, and musculoskeletal treatment.
  • Functional medicine: investigation of nutrition, metabolism, lifestyle factors, and possible contributors to inflammation.
  • Personal injury care: evaluation and documentation of injuries after automobile, workplace, or other traumatic events.
  • Rehabilitation: progressive movement, strengthening, stability, and return to activity.
  • Regenerative-care review: careful consideration of emerging treatments based on evidence, regulation, medical need, and patient safety.

This teamwork is especially important when patients are asking about experimental treatments.

Important BPC-157 Safety and FDA Information

BPC-157 needs to be discussed carefully.

As of August 2026, BPC-157 is not an FDA-approved medication.

In July 2026, the FDA’s Pharmacy Compounding Advisory Committee voted to recommend BPC-157-related substances for possible inclusion on the Section 503A Bulks List. However, that vote was advisory, and it did not constitute final FDA approval or prove that BPC-157 is safe or effective for treating intestinal disease.

FDA scientific reviewers also concluded that there was insufficient clinical information to characterize BPC-157’s safety profile. FDA noted a lack of adequate human studies using proposed oral, subcutaneous, nasal, and transdermal routes and raised concerns about immunogenicity and peptide-related impurities.

Therefore:

  • BPC-157 should not be advertised as a proven cure for leaky gut.
  • Patients should not purchase injectable research peptides from unknown internet sources.
  • Human dosing and long-term safety remain uncertain.
  • Serious gastrointestinal symptoms require proper medical evaluation.
  • Patients should not abandon FDA-approved treatments in favor of experimental peptides without appropriate medical guidance.

The Future of Regenerative Gut Care

The science of intestinal regeneration is advancing quickly.

Researchers are learning that the intestinal barrier depends on far more than one drug or peptide. Stem cells, epithelial cells, blood vessels, immune pathways, the microbiome, nutrition, metabolism, and lifestyle all interact.

BPC-157 is interesting because experimental research suggests cytoprotective, regenerative, vascular, and anti-inflammatory effects. But its most convincing evidence remains laboratory and animal research.

The safest message today is therefore:

BPC-157 may represent a future tool for intestinal repair, but it remains an investigational therapy rather than an established treatment for leaky gut or gastrointestinal disease.

A comprehensive approach combines sound medical diagnosis, evidence-based treatment, nutrition, functional health strategies, movement, rehabilitation, and appropriate specialty care. At Injury Medical Clinic PA, the collaboration between Dr. Jimenez and Dr. Cardenas reflects this broader philosophy: combining medical oversight with integrative chiropractic and rehabilitative care while allowing emerging regenerative science to develop through careful research rather than unsupported promises.

***ESSENTIAL FATTY ACIDS*** & their therapeutic uses | El Paso, Tx (2021)

References

California Institute for Regenerative Medicine. (n.d.). Stem cell therapy for inflammatory bowel disease.

Cold Spring Harbor Laboratory. (2026, January 3). Scientists found a way to help aging guts heal themselves. ScienceDaily.

International Society for Stem Cell Research. (2026, January 22). New study shows gut microbiota directly regulates intestinal stem cell aging.

Jimenez, A. (2026a). Regenerative medicine and integrative chiropractic approaches.

Jimenez, A. (2026b). Regenerative therapies for fitness and recovery insights.

Jimenez, A. (n.d.). Dr. Alex Jimenez—Clinical and integrative health information.

Leibniz Institute for Immunotherapy. (2025, October 28). Protecting the gut after stem cell transplantation: New evidence for the potential of microbiome-based therapies.

Park, J. M., Lee, H. J., Sikiric, P., & Hahm, K. B. (2020). BPC 157 rescued NSAID-cytotoxicity via stabilizing intestinal permeability and enhancing cytoprotection. Current Pharmaceutical Design, 26(25), 2971–2981.

Ruggeri, C. (2026, January 26). What are peptides? Peptide benefits for skin and more. Dr. Axe.

Stemwell. (2025, August 15). Healing gastroparesis with stem cells: A new path to digestive health.

U.S. Food and Drug Administration. (2026). Certain bulk drug substances for use in compounding that may present significant safety risks.

U.S. Food and Drug Administration. (2026, July). Pharmacy Compounding Advisory Committee meeting: BPC-157-related bulk drug substances.

Ubie Health. (n.d.). Gut won’t heal? BPC-157 medical guide.

Williams, K. L., Enslow, R., Suresh, S., Beaton, C., Hodge, M., & Brooks, A. E. (2023). Using the microbiome as a regenerative medicine strategy for autoimmune diseases. Biomedicines, 11(6), 1582.

Yoo Direct Health. (2026). FDA peptide update: What the recent BPC-157, KPV, and TB-500 news means.

Yoo Direct Health. (n.d.). Best peptides for gut health: BPC-157, KPV, larazotide and more.

Yuan, C., Demers, A., Silva-Ortiz, V., Hasoon, J. J., Lee, W., Dave, K., Amirdelfan, K., Burke, H. W., Christo, P. J., & Robinson, C. L. (2026). From regeneration to analgesia: The role of BPC-157 in tissue repair and pain management. International Journal of Molecular Sciences, 27(6), 2876.