Home Blog Page 5

Anti-Inflammatory Nutrition: Support After Injections

Anti-Inflammatory Nutrition: Support After Injections

Anti-Inflammatory Nutrition After PRP, PFP, MFAT, and Epidural Injections

Abstract

Regenerative medicine injections are designed to support tissue repair or improve the environment around an injured area. However, an injection cannot provide every nutrient the body needs to rebuild muscles, tendons, ligaments, cartilage, and other tissues. An anti-inflammatory diet can support recovery by providing protein, vitamins, minerals, antioxidants, healthy fats, and adequate hydration. It may also help control chronic background inflammation, support stable blood sugar, and improve the body’s internal healing environment. This article explains how nutrition may support recovery after platelet-rich plasma (PRP), platelet-fibrin products (PFP), microfragmented adipose tissue (MFAT), and epidural spinal injections. It also covers supplements that may need to be paused and how chiropractic care and active rehabilitation can fit into a coordinated recovery plan.

Anti-Inflammatory Nutrition: Support After Injections

Creating a Better Internal Environment for Healing

Healing is not controlled by one treatment alone. It is a series of steps involving inflammation, immune activity, new cell growth, collagen production, blood flow, and tissue remodeling.

A short inflammatory response is a normal and necessary part of healing. The goal of an anti-inflammatory diet is not to completely shut down this response. Instead, the goal is to reduce excessive, long-lasting inflammation that may interfere with healthy tissue repair.

A diet built around whole foods can provide the raw materials cells need to complete their work. Sonoran University’s Regenerative Health Diet, for example, emphasizes quality protein, colorful fruits and vegetables, micronutrients, healthy fats, and hydration to support connective tissue health (Sonoran University of Health Sciences, 2025).

Nutrition should be viewed as supportive care. There is not enough evidence to claim that one food or supplement will guarantee a better injection result. Clinical guidelines also show that regenerative procedures have different levels of evidence depending on the condition, injection product, preparation method, and patient being treated (D’Souza et al., 2024).

Understanding the Different Injection Procedures

Although the same treatment discussion may include PRP, PFP, MFAT, and epidural injections, these procedures do not perform the same job.

Platelet-Rich Plasma

PRP is prepared from the patient’s own blood. The blood is processed to concentrate platelets, which contain proteins and growth factors involved in clotting, cell communication, and tissue repair. PRP may be considered for selected tendon, ligament, muscle, and joint problems.

Platelet-Fibrin Products

PFP refers to platelet-fibrin products, which may include forms of platelet-rich fibrin. These products contain platelets within a fibrin network. The fibrin may act as a temporary framework that keeps platelets and repair signals near the treatment area.

Microfragmented Adipose Tissue

MFAT is made from a small amount of the patient’s own fat tissue. The tissue is mechanically processed into smaller fragments while keeping portions of its natural structural matrix. MFAT may be considered for certain joint, cartilage, or soft-tissue conditions. PRP and MFAT are sometimes combined, although results vary and proper patient selection remains important (Active Pain Relief & Wellness, n.d.).

Epidural Spinal Injections

A traditional epidural spinal injection usually contains a corticosteroid and local anesthetic. Its main purpose is to reduce inflammation around an irritated spinal nerve. It is an anti-inflammatory pain procedure, not a regenerative injection.

An epidural injection may reduce radiating pain enough for a patient to walk, sleep, and participate in rehabilitation. It does not rebuild a damaged spinal disc or repair a torn ligament. Any epidural use of platelet products or other biologics should be clearly explained because these applications may be investigational.

How an Anti-Inflammatory Diet Supports Cellular Repair

1. Protein Supplies Repair Materials

Protein provides amino acids that the body uses to build muscle, collagen, enzymes, immune proteins, and connective tissue. A patient who does not eat enough protein may have fewer resources available for tissue repair.

Helpful protein choices include:

  • Chicken, turkey, eggs, fish, and lean meat
  • Beans, lentils, chickpeas, and tofu
  • Yogurt or dairy-free high-protein alternatives
  • Nuts and seeds
  • Protein shakes when approved by the medical team

Protein needs depend on body size, activity level, age, kidney function, and the type of injury. Very high-protein plans should not be started without guidance, especially when kidney disease or another medical condition is present. Reviews of wound healing research support correcting protein and nutrient shortages, but they do not show that unlimited supplementation produces unlimited healing (Barchitta et al., 2019).

2. Vitamin C Supports Collagen Formation

Collagen is a major structural protein in tendons, ligaments, skin, cartilage, and other connective tissues. Vitamin C is needed for normal collagen production.

Food sources include:

  • Bell peppers
  • Broccoli
  • Strawberries and other berries
  • Kiwi
  • Oranges
  • Tomatoes

Research suggests that vitamin C is important for tissue healing, especially when a deficiency is present. However, evidence for large supplement doses in people without a deficiency is less certain (Bechara et al., 2022).

3. Minerals Support Cells and Enzymes

Zinc, copper, iron, and magnesium support many processes involved in cell growth, oxygen delivery, immune function, and tissue repair.

Useful food sources include beef, poultry, seafood, beans, lentils, pumpkin seeds, leafy vegetables, whole grains, mushrooms, and nuts. Zinc deficiency can interfere with healing, but excessive zinc intake may create new problems, including copper deficiency. Food-first nutrition is usually safer than taking high doses without laboratory testing or medical guidance.

4. Colorful Plants Help Control Oxidative Stress

Fruits, vegetables, herbs, beans, and whole grains contain antioxidants and plant compounds. These nutrients help cells manage oxidative stress, which may increase during injury and inflammation.

A simple goal is to include several colors each day:

  • Green leafy vegetables
  • Blue or purple berries
  • Red peppers and tomatoes
  • Orange carrots or sweet potatoes
  • White onions, garlic, or cauliflower

No single “superfood” controls healing. Variety matters more than relying on one fruit, vegetable, or supplement.

5. Hydration Supports Circulation

Water helps move nutrients through the bloodstream and supports normal circulation, digestion, joint lubrication, temperature control, and waste removal. Dehydration may also increase fatigue and make rehabilitation more difficult.

Water needs are different for each patient. Heart disease, kidney disease, medications, outdoor work, exercise, and El Paso’s hot, dry climate may all change fluid needs. Patients with fluid restrictions should follow their medical provider’s instructions.

Foods That May Work Against Recovery

A patient does not need a perfect diet, but limiting certain products may improve the overall healing environment.

Try to reduce:

  • Sugary drinks, candy, and frequent desserts
  • Deep-fried foods
  • Highly processed snack foods
  • Processed meats
  • Excessive alcohol
  • Large portions of refined flour products
  • Foods that repeatedly cause digestive symptoms
  • Very low-calorie crash diets

These choices may contribute to unstable blood sugar, poor nutrient intake, excessive calorie intake, or chronic inflammation when eaten frequently. Regenerative nutrition resources commonly recommend whole foods, quality protein, vegetables, berries, healthy fats, and reduced intake of refined sugar and heavily processed food (Leiber, 2025; Krasnick Regenerative Medicine, n.d.).

Smoking and poor sleep may also interfere with recovery. Nutrition works best when it is combined with enough sleep, appropriate movement, stress control, and treatment of conditions such as diabetes or anemia.

Supplements to Review After PRP or a Regenerative Injection

Food and supplements are not always equal. Eating salmon or adding a small amount of turmeric to food is different from taking a concentrated fish oil or curcumin capsule.

Some clinicians ask patients to temporarily pause products that may affect platelet activity, bleeding, or the controlled inflammatory response after PRP. These may include:

  • High-dose turmeric or curcumin capsules
  • High-dose fish oil or omega-3 supplements
  • High-dose vitamin E
  • Concentrated garlic, ginger, or ginkgo supplements
  • Combination “anti-inflammatory” herbal products
  • Nonsteroidal anti-inflammatory drugs when directed by the injector

The research is not completely consistent. High omega-3 doses may reduce platelet aggregation and increase bleeding time, yet clinical reviews have generally not found a major increase in bleeding from standard fish oil use. High-dose purified EPA may present a different risk (National Institutes of Health, n.d.).

For this reason, patients should not create their own stop-and-start schedule. The injection provider should decide which supplements to pause and when to restart them.

Never stop aspirin, anticoagulants, prescription omega-3 products, or another prescribed medicine without approval from the prescribing clinician. Stopping these drugs without guidance may be more dangerous than continuing them.

Normal food portions are often treated differently from concentrated supplements. Patients should bring a complete list of medications, vitamins, powders, herbal products, and injections to the medical team before the procedure.

A Simple Recovery Plate

A practical meal after the procedure could include:

  • One serving of chicken, fish, eggs, beans, or another protein
  • Half a plate of vegetables
  • A moderate portion of brown rice, potatoes, oats, corn, or whole grains
  • A small amount of olive oil, avocado, nuts, or seeds
  • Water or another unsweetened drink
  • Fruit for a snack or dessert

This approach provides protein, fiber, vitamins, minerals, carbohydrates, and healthy fats without requiring an extreme diet.

How Chiropractic Care and Rehabilitation Fit In

A regenerative injection may support biological repair, but it does not automatically correct restricted joint motion, muscle weakness, poor posture, an unsafe lifting pattern, or loss of balance.

Integrative chiropractic care can address the mechanical side of recovery. Depending on the diagnosis and stage of healing, care may include:

  • Gentle joint mobilization
  • Chiropractic adjustments away from a protected injection site
  • Soft-tissue treatment
  • Spinal decompression when appropriate
  • Corrective exercise
  • Posture and movement training
  • Progressive strengthening
  • Balance and coordination work

Treatment should be coordinated with the injection provider. Aggressive manipulation or heavy exercise immediately after a procedure may not be appropriate. The early phase may require protection and relative rest. Controlled movement and progressive loading can then be added as the tissue becomes ready.

Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, has described a clinical approach that combines biological support with mechanical correction. His clinical observations emphasize that an injection may begin a healing process, while chiropractic care and rehabilitation help the patient restore movement, strength, and safer body mechanics (Jimenez, 2026a, 2026b).

Multidisciplinary Injury Care in El Paso, Texas

At Injury Medical Clinic PA in El Paso, the clinic’s published materials identify Dr. Maria Guadalupe Cardenas, MD, as a board-certified Internal Medicine physician, Medical Director, and Collaborative Physician. The clinic lists NPI #1164426749 and Texas Medical License #J2933 and reports that she has more than 40 years of internal medicine experience.

  • Dr. Cardenas works alongside Dr. Jimenez within a multidisciplinary model.
  • Dr. Jimenez focuses on chiropractic care, musculoskeletal evaluation, functional medicine, personal injury care, and rehabilitation within his professional scope.
  • Dr. Cardenas provides medical direction and internal medicine experience for medical services.

This coordinated model may help the team review health factors that can affect recovery, including:

  • Diabetes or unstable blood sugar
  • High blood pressure
  • Kidney or heart disease
  • Anemia and nutritional deficiencies
  • Medication and supplement interactions
  • Bleeding concerns
  • Chronic inflammatory conditions

The goal is to connect the patient’s structural health, medical health, nutrition, and physical function rather than treating each concern in isolation.

Supporting Healing From the Inside Out

An anti-inflammatory diet cannot guarantee that PRP, PFP, MFAT, or an epidural injection will be successful. It can, however, give the body a stronger nutritional foundation.

Adequate protein, colorful produce, minerals, healthy fats, fiber, hydration, sleep, and stable blood sugar may help create a more supportive internal environment for cellular repair. Limiting alcohol, added sugar, heavily processed food, smoking, and unnecessary high-dose supplements may also support recovery.

The safest plan is individualized. Patients should follow the specific aftercare instructions provided by the clinician performing the procedure and coordinate nutrition, medication, chiropractic care, and rehabilitation with the full treatment team.

From Inflammation to Healing | El Paso, Tx (2023)

References

Active Pain Relief & Wellness. (n.d.). PRP and MFAT combination therapy.

Barchitta, M., Maugeri, A., Favara, G., Magnano San Lio, R., Evola, G., Agodi, A., & Basile, G. (2019). Nutrition and wound healing: An overview focusing on the beneficial effects of curcumin. International Journal of Molecular Sciences, 20(5), 1119.

Beso Wellness & Beauty. (n.d.). How nutrition and lifestyle influence PRP results.

D’Souza, R. S., Her, Y. F., Hussain, N., et al. (2024). Evidence-based clinical practice guidelines on regenerative medicine treatment for chronic pain. Journal of Pain Research, 17, 2951–3001.

Dr. Lissa Plastic Surgery. (n.d.). The importance of an anti-inflammatory diet during post-op recovery.

Jimenez, A. (2026a). Anti-inflammatory nutrition supports regenerative healing.

Jimenez, A. (2026b). El Paso injury regenerative wellness treatments available.

Jimenez, A. (n.d.-a). Clinical observations and professional resources.

Jimenez, A. (n.d.-b). Professional profile.

Krasnick Regenerative Medicine. (n.d.). The role of nutrition in enhancing regenerative medicine outcomes.

Leiber, J. (2025, April 4). Optimizing recovery: Why nutrition and supplements matter after PRP and bone marrow concentrate procedures.

National Institutes of Health, Office of Dietary Supplements. (n.d.). Omega-3 fatty acids: Fact sheet for health professionals.

Sonoran University of Health Sciences. (2025, March 24). A regenerative health diet: Heal, reduce inflammation, and thrive.

Total Spine Wellness. (2025). Exosome therapy explained.

Ubie Health. (2026a, May 6). How to fix slow healing: PRP and diet for best results.

Ubie Health. (2026b, May 6). What to eat before PRP to maximize your growth factors.

West Texas Pain Institute. (n.d.). Regenerative medicine.

Cardiometabolic Care: Understanding the Connection with Obesity

Understanding cardiometabolic care for obesity is crucial for better health. Discover effective strategies and insights.

Integrative Approach to Weight Management and Metabolic Health

Disclaimer: The information presented in this post is intended for educational purposes only and should not be considered medical advice. It is not a substitute for professional medical consultation, diagnosis, or treatment. Always seek the advice of your physician or another qualified health provider with any questions you may have regarding a medical condition. Never disregard professional medical advice or delay in seeking it because of something you have read here. The case studies presented are illustrative and individual results will vary. The treatments and medications discussed may not be suitable for everyone and should only be used under the supervision of a licensed healthcare professional.

Abstract: A Modern, Integrative Approach to Weight Management and Metabolic Health

In this educational post, I, Dr. Alex Jimenez, will guide you through the complexities of modern obesity management, drawing upon the latest evidence-based research and our clinical experience at Injury Medical Clinic. I will guide you through a comprehensive, first-person exploration of our integrative care pathways for a diverse group of patients, each presenting with unique but interconnected challenges: a 25-year-old woman with obesity, PCOS, and binge-eating disorder; a 35-year-old man with insulin resistance and male infertility; a 42-year-old perimenopausal woman with metabolic dysfunction; a 57-year-old man with type 2 diabetes and advanced cardiometabolic disease; and a 72-year-old woman with severe osteoarthritis and sarcopenia. Through their journeys, we will delve into the physiological underpinnings of obesity, including insulin resistance, hormonal dysregulation, and sarcopenia (age-related muscle loss). I will discuss advanced diagnostic tools like HOMA-IR and body composition analysis, and explain how we develop personalized, multimodal treatment plans. These plans integrate targeted nutrition, progressive physical activity, and advanced pharmacotherapy, including GLP-1/GIP receptor agonists like semaglutide and tirzepatide, as well as other medications like phentermine, naltrexone-bupropion, and lisdexamfetamine. A significant focus will be placed on the importance of our integrative care model, showcasing how the team—including myself and our Medical Director, Dr. Maria Guadalupe Cardenas, MD—collaborates to provide comprehensive care. We will also address the critical and often overlooked issues of weight bias in healthcare and the psychological barriers patients face, offering strategies to foster a supportive, patient-centered environment. This comprehensive discussion aims to illuminate a path toward sustainable health improvements, enhanced mobility, and a better quality of life for individuals with complex health challenges.

Note: This post is presented as an educational article for our clinic website; it is not a lecture. It synthesizes contemporary research using rigorous, modern, evidence-based methods and showcases the collaborative model our patients experience. For background on my clinical observations and practice philosophy, see my sciatica resource at https://sciatica.clinic/ and my professional profile at https://www.linkedin.com/in/dralexjimenez/.

The Integrative Clinical Team: Dr. Alex Jimenez and Dr. Maria Guadalupe Cardenas

Building a Multidisciplinary Foundation for Complex Metabolic Care in El Paso, Texas

At Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, located in El Paso, Texas, the clinical philosophy is rooted in a simple but powerful truth: complex patients deserve complex, coordinated care. No single discipline, whether chiropractic, internal medicine, nutrition, or rehabilitation, can address the full spectrum of metabolic, musculoskeletal, hormonal, and psychological challenges that patients bring to the clinic. It is precisely this recognition that drives the multidisciplinary model we practice here every day.

I am Dr. Alexander Jimenez, and my professional journey has led me to earn a series of credentials—DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST—that reflect my deep commitment to an integrative and holistic approach to patient care. My training spans chiropractic medicine, advanced practice nursing (family nurse practitioner), and functional and integrative cardiometabolic care. My clinical work focuses on metabolic optimization, spine and neuromusculoskeletal health, and injury rehabilitation within a systems-biology framework. With decades of clinical experience and a commitment to evidence-based, integrative practice, I have become a recognized voice in chronic pain management, metabolic dysfunction, hormonal imbalance, and musculoskeletal rehabilitation. My clinical observations and educational resources are publicly available at sciatica.clinic and through my professional profile at LinkedIn.

A cornerstone of our practice is my professional collaboration with Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a highly respected physician, board-certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933), with over 40 years of invaluable experience as an internist. She serves as our clinic’s Medical Director and Collaborative Physician, providing essential medical oversight and direction. This partnership between a Doctor of Chiropractic (DC) and a Medical Doctor (MD) is a powerful model for integrative healthcare. It allows us to seamlessly blend the principles of chiropractic care—focusing on musculoskeletal integrity, nervous system function, and biomechanics—with the diagnostic and pharmacological expertise of internal medicine. Her role as Medical Director ensures that the clinic operates at the highest standard of medical care while providing the legal, ethical, and clinical framework for collaborative practice.

How the Collaborative Model Works

This type of multidisciplinary setup is increasingly recognized as the gold standard for integrative and injury care clinics, where patients often present with overlapping diagnoses that require simultaneous management from multiple clinical perspectives. At Injury Medical Clinic PA, the model works as follows:

  • Dr. Jimenez (Chiropractic, APRN, Functional Medicine): I provide chiropractic care, functional medicine evaluation, advanced practice nursing services, musculoskeletal assessment, movement prescriptions, nutrition patterning, behavioral strategies, care coordination, and outcome tracking. My training as an APRN and FNP-BC allows me to diagnose, prescribe, order diagnostic studies, and manage patients across a broad spectrum of conditions.
  • Dr. Cardenas (Internal Medicine): She provides comprehensive medical oversight, risk stratification, lab and imaging interpretation, medication selection and titration, contraceptive strategy, pregnancy planning and drug washouts, monitoring for adverse effects and drug–drug interactions, and specialist-level evaluation of complex cardiometabolic, endocrine, and systemic conditions.
  • Together, the team integrates services including:
  • Chiropractic spinal manipulation and soft tissue care
  • Functional medicine evaluation and nutritional biochemistry
  • Obesity medicine and metabolic health management
  • Hormone optimization and menopausal care
  • Personal injury care and rehabilitation
  • Cardiometabolic risk reduction programs
  • Collaborative referral to dietitians, physical therapists, and mental health professionals

This collaborative framework ensures that our patients receive a holistic and robust treatment plan that is both safe and effective, addressing all facets of their health. The clinical observations shared in this post reflect the kind of real-world, patient-centered thinking that defines our work and that has made our team trusted providers in the El Paso community for many years.

Patient Journey Case Introduction: A 25-Year-Old With Obesity, Insulin Resistance, and Probable PCOS

I first met a 25-year-old woman who works as a fitness director and lives an active lifestyle. Despite her high activity, she reported lifelong weight struggles with cycles of loss and regain, escalating to her highest weight at presentation. She reported:

  • BMI of 37.5 with central adiposity (elevated waist circumference, apple-shaped pattern).
  • Clinical signs of insulin resistance: acanthosis nigricans, skin tags.
  • Hyperandrogenism indicators: cystic acne, hirsutism (upper lip hair).
  • Ovulatory dysfunction: infrequent, irregular menses since adolescence.
  • Metabolic labs: fasting insulin 36.1 µIU/mL, fasting glucose 107 mg/dL, A1c 6.0%, elevated triglycerides, low HDL, elevated LDL, and elevated liver enzymes; HOMA-IR 9.5 (marked insulin resistance).
  • Eating pattern: highly restrictive caloric targets (~1200 kcal), anxiety when exceeding this, evening cravings, and intermittent binge episodes 1–2 evenings per week.
  • Reproductive context: sexually active for 5 years without contraception, believes she “can’t get pregnant,” and wishes for future fertility.

In my examination and review with Dr. Cardenas, she met 2 of the 3 Rotterdam criteria for PCOS (hyperandrogenism and ovulatory dysfunction). She had cardiometabolic risk amplification consistent with insulin resistance and prediabetes. She also presented with binge-eating disorder features.

Why this matters

  • PCOS is a chronic, lifelong syndrome with persistent cardiometabolic risk beyond menopause, driven by insulin resistance and hyperandrogenism (Legro et al., 2013; Fauser et al., 2012).
  • Insulin resistance impairs weight loss, increases hepatic lipogenesis, fuels dyslipidemia, and worsens ovulatory dysfunction (Dunaif, 1997; Taylor, 2021).
  • Restrictive eating and binge cycles heighten stress reactivity, dysregulate appetite signals (ghrelin/leptin), and perpetuate weight cycling with preferential fat regain and muscle loss (Montani et al., 2015; Dulloo & Montani, 2015).

Diagnostic Framing: Insulin Resistance, PCOS, Dyslipidemia, and Binge-Eating Disorder

Key clinical impressions at baseline:

  • Class II obesity with central adiposity and metabolic syndrome features.
  • Probable PCOS by clinical criteria (no need to delay treatment with exhaustive imaging when clinical criteria are satisfied and symptoms are significant).
  • Prediabetes (A1c 6.0%) with hyperinsulinemia (fasting insulin 36.1 µIU/mL) and HOMA-IR 9.5.
  • Atherogenic dyslipidemia typical of insulin resistance: elevated triglycerides, low HDL, elevated LDL.
  • Elevated liver enzymes consistent with metabolic dysfunction-associated steatotic liver disease risk (MASLD; formerly NAFLD).
  • Binge-eating disorder by symptoms and validated screening.

How I screen for binge eating in practice

  • I incorporate the BEDS-7 (Binge Eating Disorder Screener-7) to assess frequency of unusually large food intake, perceived loss of control, and associated distress (Herman et al., 2016). Scores >5 suggest binge-eating disorder and prompt structured intervention and, when appropriate, pharmacotherapy.

Physiological linkages

  • Hyperinsulinemia and androgen excess create a feed-forward loop: insulin stimulates ovarian theca cells, increasing androgen production; androgens worsen visceral adiposity and insulin resistance (Dunaif, 1997; Azziz et al., 2016).
  • Central adiposity produces proinflammatory adipokines (e.g., TNF-α, IL-6) and reduces adiponectin, reducing insulin sensitivity and impairing ovulatory signaling (Kershaw & Flier, 2004).
  • Restrictive eating raises cortisol, disrupts HPA axis tone, and primes reward-seeking circuits, amplifying binge risk (Adam & Epel, 2007; Berthoud, 2011).

Case Study 1: George – Unraveling the Links Between Stress, Hormones, and Male Fertility

Let’s begin by meeting George. His story is one that I see with increasing frequency in my practice—a story where the pressures of modern life manifest as complex physiological problems.

George is a 35-year-old man who works as a project manager for a tech company. He doesn’t smoke, which is a positive starting point. He and his spouse are trying to have a second child, but they are facing challenges, much like they did with their first. This is a significant source of emotional strain for both of them. When he first came to see me, he reported several concerning symptoms:

  • Feelings of depression and anxiety.
  • A recent diagnosis of low sperm count, which is a primary driver of his current distress.
  • Elevated blood pressure
  • Significant stress, stemming from both his demanding job and his personal life.

As we delved deeper into his daily life, a more detailed picture emerged. He’s aiming for a promotion, which adds a layer of professional pressure. His commute is long, eating into his personal time and adding to his daily stress load. At his tech company, free food and drinks are abundant, a common perk that often leads to unintentional overconsumption of processed foods and sugary beverages. On top of this, he and his spouse are navigating the stressful process of buying a new home in a better school district for their family.

The news of his low sperm count was particularly distressing for him. Compounding this worry is his concern over his elevated blood pressure, a fear magnified by his family history—his father was diagnosed with heart failure, which George correctly understands is linked to untreated hypertension. He also shared, with some hesitation, that he experiences occasional erectile dysfunction, which he attributes to stress. This constellation of symptoms paints a picture of a man whose body is struggling under the weight of chronic physiological and psychological stress.

Initial Clinical Assessment and Lab Findings

About three months before our consultation, George had a complete physical with another practitioner. The findings from that visit, combined with our own initial assessment, were revealing.

Concerning Trends and Vital Signs:

  • Weight Gain: There was a noticeable upward trend in his weight.
  • Waist Circumference: His waist measured at an elevated level, a key indicator of visceral adiposity (fat stored around the internal organs), which is a major risk factor for metabolic disease.
  • Blood Pressure: His readings were consistently in the elevated range, confirming his concerns about hypertension.
  • Poor Sleep: He reported not sleeping well, feeling unrested upon waking.
  • Increased Hunger: He was feeling hungry frequently and expressed shame about his inability to control his appetite. This feeling of lost control is a common and powerful psychological barrier for many patients.

He shared that he and his spouse are trying to adopt healthier habits together, but he worries about how she perceives the fertility issues, adding another layer of emotional complexity.

Laboratory Results:

Here is where the objective data began to connect the dots of his symptomatic complaints:

  • Fasting Glucose & Fasting Insulin: Both were significantly increased. This is a classic sign that the body is struggling to manage blood sugar.
  • HOMA-IR (Homeostasis Model Assessment for Insulin Resistance): We calculated his HOMA-IR score, which came out to 1.

To put this in perspective, a HOMA-IR score is a calculation using fasting glucose and fasting insulin levels to quantify the degree of insulin resistance. A score above 1.9 is generally considered indicative of early insulin resistance, while a score above 2.9 is a stronger indicator. George’s score of 3.1 firmly places him in the insulin resistance category. This means his cells are becoming “numb” to the effects of insulin, forcing his pancreas to pump out more and more of the hormone to keep blood sugar in check. This state of hyperinsulinemia is a major driver of fat storage, inflammation, and further hormonal chaos.

  • Lipid Panel: His cholesterol levels were slightly elevated, pointing towards dyslipidemia, another hallmark of metabolic syndrome.
  • Kidney and Electrolyte Function: These were within normal limits, which was reassuring.

However, I noted some critical missing pieces in his previous lab work. There was no Hemoglobin A1c (HbA1c) to assess his average blood sugar over the past three months, no thyroid panel to rule out thyroid dysfunction as a cause for his fatigue and weight gain, and no liver panel to check for signs of fatty liver disease, a common consequence of insulin resistance. We needed to order these to get a complete picture of his metabolic health.

Identifying Health Risks and Patient-Centered Goals

Based on this initial information, we identified several key areas of concern:

  • Cardiometabolic Risk: His elevated blood pressure, insulin resistance, dyslipidemia, and visceral adiposity put him at high risk for developing type 2 diabetes and cardiovascular disease.
  • Hormonal Imbalance: The interplay between stress, obesity, and insulin resistance was clearly impacting his endocrine system.
  • Mental and Emotional Health: His reported depression, anxiety, and stress were not just symptoms but also drivers of his physiological condition.
  • Substance Use/Coping Mechanisms: We needed to explore how he was managing his stress. Was he turning to food, alcohol, or other substances?
  • Lifestyle Factors: A deep dive into his nutrition, physical activity, and sleep habits was necessary.

Most importantly, we needed to understand what mattered to the patient. A treatment plan is only effective if it aligns with the patient’s own goals. When we asked him, his priorities were clear, and notably, “losing weight” was not his primary stated goal. Instead, he wanted to:

  1. Improve his heart health and prevent the fate his father faced.
  2. Prevent the onset of diabetes.
  3. Improve his fertility.
  4. Manage his stress more effectively.
  5. Have enough energy to be an active and engaged father.

This is a crucial distinction. By focusing on his intrinsic motivations, we could frame our interventions in a way that resonated with him, moving beyond the simple and often stigmatizing focus on the number on the scale. For a young woman like the PCOS patient, a key goal was future fertility, while for George, it was also fertility, alongside preventing the chronic diseases that afflicted his father. This highlights the need to align on patient-centered and measurable goals. For instance, even a 5–10% weight loss meaningfully improves insulin sensitivity, triglycerides, HDL, blood pressure, and A1c and can restore ovulation in PCOS (Knowler et al., 2002; Wilding et al., 2021; Moran et al., 2011).

The Vicious Cycle: Chemical vs. Character

One of the first and most important conversations I had with George was about the concept of “Chemical versus Character.” He had expressed deep shame about his inability to control his hunger. This is a story I hear every day. Patients internalize their body’s physiological signals as a personal or moral failing. They believe if they just had more willpower, more discipline, or a stronger character, they could overcome their cravings and weight gain.

I explained to George that what he was experiencing was not a failure of character, but a result of powerful chemical signals being driven by his underlying physiology. This understanding is profoundly liberating. It helps to release the internal bias, stigma, shame, and guilt that so many people carry, which in itself is a major source of stress.

We walked through the positive feedback cycle of obesity and hormone changes. In this context, “positive” doesn’t mean good; it means amplifying. The obesity drives the hormone changes, and the hormone changes, in turn, drive more obesity. Here’s how it works:

The Hormonal Cascade of Obesity and Stress

  • Increased Adipose Tissue and Its Endocrine Role: As a person accumulates excess adipose (fat) tissue, especially visceral fat, it doesn’t just sit there passively. Adipose tissue is a highly active endocrine organ. One of its key functions is producing an enzyme called aromatase.
  • Aromatase and Hormone Conversion: Aromatase converts androgens, like testosterone, into estrogens. In men, this leads to a dangerous imbalance: testosterone levels decrease while estrogen levels increase. Low testosterone contributes to fatigue, low mood, decreased muscle mass, and, critically for George, impaired sperm production (Katib, 2015). High estrogen can further promote fat storage, creating a self-perpetuating cycle.
  • Cortisol, Insulin, and Appetite: Chronic stress—from his job, commute, and personal worries—keeps his cortisol levels chronically elevated. Cortisol is our primary stress hormone. In short bursts, it’s essential for survival. But when it’s high all the time, it wreaks havoc.
  • Chronically high cortisol signals the body to store energy, particularly as visceral fat around the abdomen.
  • It also directly drives up appetite and cravings, especially for high-sugar, high-fat “comfort foods.”
  • Simultaneously, the underlying insulin resistance means that even though his body is flooded with insulin, it can’t use glucose effectively for energy. This state of perceived cellular starvation sends powerful hunger signals to the brain.
  • The Dysregulation of Hunger and Satiety Hormones: This process throws the delicate balance of our main appetite-regulating hormones into disarray.
  • Ghrelin: Known as the “hunger hormone,” ghrelin is produced in the stomach and signals the brain that it’s time to eat. In George’s state, his ghrelin levels are chronically elevated, making him feel constantly hungry.
  • Leptin: This is the “satiety hormone,” produced by fat cells to tell the brain, “We have enough energy stored; you can stop eating.” However, in a state of obesity and inflammation, the brain can become leptin resistant. Similar to insulin resistance, the signal is being sent, but the brain isn’t receiving it. So, despite having ample energy stores, his brain thinks he’s starving.
  • GLP-1 (Glucagon-Like Peptide-1): This is another crucial satiety hormone, released from the gut after eating. It slows stomach emptying, reduces appetite, and improves insulin sensitivity. In states of metabolic dysfunction, GLP-1 signaling is often impaired.
  • The result of this hormonal storm is a dramatic increase in appetite and a sharp decrease in satiety. This is a chemical reality, not a character flaw.
  • Inflammation and Self-Blame: The excess adipose tissue also releases inflammatory molecules called adipokines. This chronic, low-grade inflammation further worsens insulin resistance and contributes to a feeling of malaise and fatigue. The inability to control cravings leads to more self-blame and a negative internal dialogue, which further increases stress and elevates cortisol. And so, the vicious cycle continues to spin, gaining momentum with each rotation.

Understanding this complex interplay was a breakthrough for George. It shifted his perspective from self-blame to curiosity and empowered him to become an active participant in his own recovery.

Transform Your Body!- Video

Transform your Body! | El Paso, Tx (2023)

Case Study 2: Lynn – Navigating Perimenopause, Grief, and Metabolic Health

Now, let’s turn our attention to Lynn. Her case highlights a different but equally common set of challenges, centered around the hormonal transition of perimenopause.

Lynn is a 42-year-old non-smoker who works full-time as an event planner. She came to our clinic with a cluster of symptoms that I’m sure many practitioners will find familiar:

  • Fatigue and “Brain Fog”: A profound sense of mental cloudiness and difficulty concentrating.
  • Poor Sleep: Difficulty falling or staying asleep.
  • Mood Swings: Increased irritability and emotional lability.
  • Hot Flashes: Sudden feelings of intense heat, a classic vasomotor symptom of perimenopause.
  • A 20-pound weight gain that she was very concerned about.

Her history revealed several important details. She had her first child at age 35, but it was after a difficult time conceiving, which may suggest a pre-existing hormonal imbalance. She reported that her periods had been irregular for most of her adult life, often heavy and accompanied by severe mood changes and worsened depression, pointing towards a possible history of PMDD (Premenstrual Dysphoric Disorder) or other underlying issues.

The Weight of Grief and Medical Distrust

A significant life event was casting a long shadow over her health: she had lost her father to heart disease just six months ago. We needed to be acutely aware of the grief she was processing. Furthermore, her trust in the medical system was frayed. We were her third primary care provider in the last 18 months due to provider turnover at her previous clinic. This lack of continuity of care is a major barrier to effective treatment.

She felt her previous concerns had been dismissed. When she brought up her perimenopausal symptoms, she felt they were brushed aside. When she expressed concern about her weight gain, she was told she just needed to pay more attention to her diet and exercise. This dismissive advice left her feeling lonely and unheard, a common experience for many women in this life stage.

Clinical and Laboratory Findings for Lynn

Vital Signs and Lab Work:

  • Blood Pressure: Her blood pressure was slightly elevated.
  • Waist Circumference: Her waist circumference was elevated (above the 35-inch threshold for women), indicating increased visceral adiposity and metabolic risk.
  • Lab Results:
  • Cholesterol Panel and HbA1c: Both indicated emerging metabolic issues, consistent with her weight gain and elevated waist circumference.
  • Thyroid and Kidney Function: Both were normal.
  • Liver Enzymes: Her liver enzymes were slightly elevated, which, like with George, raises concern for nonalcoholic fatty liver disease (NAFLD).
  • Screenings: She was up to date on all her age-appropriate health screenings, which was excellent.

Health Risks and Considerations:

  • Cardiovascular Disease: Her elevated blood pressure, dyslipidemia, visceral adiposity, and family history (father with heart disease) put her at increased risk.
  • Type 2 Diabetes: Her HbA1c results indicated she was on the path towards metabolic syndrome and diabetes.
  • Perimenopausal Transition: Her symptoms were classic for this hormonal shift.
  • Grief and Mental Health: The recent loss of her father was a significant psychological stressor.

Lynn’s Health Goals: Reclaiming Her Mind and Body

When we discussed her goals, Lynn was clear and articulate. She was tired of “feeling like she’s lost her mind,” a powerful description many women use for the cognitive effects of perimenopause. Her priorities were:

  1. Alleviate her perimenopausal symptoms, especially the brain fog, mood swings, and poor sleep.
  2. Reduce her blood pressure.
  3. Prevent further weight gain and reduce her visceral fat.
  4. Decrease her long-term risk for cardiovascular disease.

The Physiology of Perimenopause and Metabolic Dysfunction

How Declining Estrogen Reshapes the Metabolic Landscape

Perimenopause is the transitional phase preceding menopause, typically beginning in a woman’s mid-to-late forties, during which ovarian function begins to decline and estrogen and progesterone levels fluctuate erratically before ultimately falling. This phase can last anywhere from two to ten years and is associated with a constellation of symptoms and physiological changes that have profound implications for metabolic health, cardiovascular function, body composition, cognitive clarity, and overall quality of life (Santoro et al., 2021).

To fully appreciate why perimenopause demands serious clinical attention in the context of obesity and cardiometabolic risk, it is essential to understand estrogen’s role as a metabolic hormone. This role extends far beyond its reproductive functions.

Estrogen as a Metabolic Regulator

Estradiol (E2), the predominant form of estrogen during the reproductive years, exerts its effects through estrogen receptors (ERα and ERβ) that are distributed throughout virtually every tissue in the body, including adipose tissue, skeletal muscle, liver, pancreas, brain, and the cardiovascular system. Through these receptors, estrogen:

  • Regulates insulin sensitivity. Estradiol enhances insulin receptor signaling and promotes glucose uptake in peripheral tissues. As estrogen levels decline during perimenopause, insulin resistance increases, raising the risk of type 2 diabetes and metabolic syndrome (Mauvais-Jarvis et al., 2013).
  • Governs fat distribution. Estrogen promotes the preferential storage of fat in the gluteofemoral (hip and thigh) region—the so-called “android” fat pattern, which is metabolically less harmful than visceral fat. As estrogen declines, fat redistribution shifts toward the visceral compartment, dramatically increasing cardiometabolic risk. This is why many women notice a significant increase in belly fat during perimenopause even without significant changes in their eating or exercise habits (Davis et al., 2012).
  • Supports energy expenditure and mitochondrial function. Estrogen promotes mitochondrial biogenesis and oxidative phosphorylation, meaning that as estrogen declines, cellular energy production becomes less efficient, resting metabolic rate decreases, and fatigue increases. This partially explains the profound fatigue that Lynn and many perimenopausal women experience.
  • Protects lean muscle mass. Estrogen has anabolic effects on skeletal muscle, promoting muscle protein synthesis and reducing muscle protein breakdown. The perimenopausal decline in estrogen accelerates sarcopenia (age-related muscle loss) at a time when it is already beginning due to the natural aging process after age thirty (Sipila et al., 2021).
  • Modulates appetite and food reward. Estrogen receptors in the hypothalamus regulate hunger-signaling pathways, including those involving leptin and neuropeptide Y. Declining estrogen can dysregulate these pathways, increasing appetite and reducing the rewarding sensation of food—contributing to increased caloric intake and weight gain (Asarian & Geary, 2013).
  • Supports cardiovascular health. Estrogen promotes endothelial function, reduces LDL oxidation, supports HDL production, and has anti-inflammatory effects on the vascular wall. The decline in estrogen during perimenopause is associated with accelerated cardiovascular risk, which is why women’s cardiovascular disease incidence rises sharply after the menopausal transition (Mendelsohn & Karas, 1999).

Case Study 3: Dolores’s Battle with Osteoarthritis and Sarcopenia

Now, let’s shift our focus to another patient, Dolores. Her case highlights a different but equally common set of challenges, particularly those faced by older women.

Dolores is a 72-year-old retired wealth advisor who is eager to begin a new chapter of her life: traveling. However, her plans are severely hampered by her health.

Presenting Clinical Picture

  • Primary Complaint: Severe osteoarthritis (OA) in both knees. The pain and joint damage have significantly limited her mobility.
  • Immediate Goal: She desires a total knee replacement for both knees to regain her freedom of movement. However, she has been told she must first reduce her weight to achieve a Body Mass Index (BMI) below 40 to qualify for the surgery.
  • Medical History: Her pertinent history includes hyperlipidemia (high cholesterol, for which she takes rosuvastatin), insomnia (managed with trazodone), and her knee OA (for which she uses diclofenac, an NSAID).
  • Weight History: Dolores reports a very common pattern. She maintained a stable weight until she entered perimenopause. At that point, she began to gain weight, particularly central adiposity (fat around her midsection), and has been on an upward trajectory ever since. Past attempts at weight loss through portion control, eliminating sweets, and increasing activity have been short-lived, always ending in weight regain. This yo-yo pattern is typical and speaks to the powerful biological and hormonal forces at play.

Baseline Health Behaviors and Labs

  • Nutrition: She eats three meals a day but consumes very little protein. She enjoys fruits and vegetables but also loves sweets, finding them especially difficult to resist in the evening. This combination—low protein, high sugar—is a recipe for muscle loss and fat gain.
  • Physical Activity: Her severe knee pain restricts her activity. She can swim for 20 minutes, three times a week, which is excellent as it is a non-weight-bearing exercise.
  • Sleep: She has a long-standing history of insomnia, which is now much improved with trazodone. Quality sleep is crucial for hormonal regulation, muscle repair, and appetite control, so managing this is a key part of her overall plan.
  • Social Habits: She is a non-smoker and drinks alcohol only occasionally.

When we look at her initial labs and measurements, she appears, on the surface, to be “metabolically healthier” than other patients at baseline.

  • Fasting Insulin: Her fasting insulin is 8.4 µU/mL. This is slightly elevated but not nearly as high as others, suggesting a lesser degree of insulin resistance.
  • BMI and Body Composition:
  • Her BMI is 41.5, just over the surgical cutoff.
  • Her body fat percentage is 56.8%, which is extremely high.
  • Her skeletal muscle mass is a mere 15.1%, placing her in the 2nd percentile for women her age. This is a critical finding: Dolores has severe sarcopenia.
  • Visceral Fat and Body Shape: Her visceral fat is 2.3 liters. She has a gynoid (“pear-shaped”) fat distribution pattern, but with the added central adiposity common after menopause.
  • Metabolic Markers: Because she has maintained some level of physical activity (swimming) and has a healthier diet in some respects (high fruit and vegetable intake), her lipids and A1c are currently in a good range.

Identifying the Health Risks and Inequities

Our primary concern is preventing her from tipping over into full-blown metabolic disease. But just as important is recognizing the unique challenges and health inequities she faces.

  1. Systemic Health Inequities: Dolores is at the intersection of three factors that often lead to suboptimal care: she is female, she is older, and she has obesity. Research and my own clinical observations confirm that patients with these characteristics are frequently dismissed by the healthcare system (Puhl & Heuer, 2009). Their concerns are minimized, their symptoms are attributed solely to their weight, and they are often not offered the full range of evidence-based treatments. Many of these women come to expect this treatment and, as a result, don’t advocate for themselves. It is my responsibility as her clinician to be acutely aware of this and to be her proactive advocate.
  2. Progressive Immobility and Sarcopenia: The vicious cycle is clear: her knee pain prevents her from exercising, which worsens her sarcopenia and contributes to weight gain. The increased weight, in turn, puts more stress on her knees, worsening the pain and accelerating the joint damage. We must break this cycle.
  3. Deteriorating Quality of Life: Her immobility and pain are robbing her of her retirement dreams. This is not a cosmetic issue; it’s about function, independence, and joy.
  4. Future Cardiometabolic Risk: While her labs look relatively good now, her high body fat percentage, central adiposity, and sarcopenia put her on a direct path toward developing type 2 diabetes, worsening hypertension, and cardiovascular disease if left unaddressed.

Introducing Amit: A Case Study in Sarcopenic Obesity and Cardiometabolic Disease

The case of Amit—a fifty-seven-year-old male of North African ancestry, married, with two college-aged children, working as a manager at a tire factory—offers a profoundly different but equally instructive clinical portrait. Where Lynn’s case illustrated the hormonal and metabolic consequences of perimenopause, Amit’s case illustrates the convergence of multiple advanced cardiometabolic conditions in a patient whose obesity has been present since early adulthood and whose disease burden reflects both genetic predisposition and decades of metabolic dysregulation.

Amit’s Medical History: A Constellation of Interconnected Diagnoses

Amit’s pertinent medical history includes:

  • Type 2 diabetes mellitus—treated with both basal and bolus insulin plus metformin
  • Myocardial infarction (MI) three years prior—the single most significant event in his health history, prompting smoking cessation
  • Stage 2A peripheral artery disease (PAD) with intermittent claudication—indicating established atherosclerotic disease in the lower extremities
  • Obstructive sleep apnea (OSA)—managed with CPAP
  • Hypertension—on lisinopril
  • Hyperlipidemia—on rosuvastatin
  • Stage 2 Metabolic-Associated Steatotic Liver Disease (MASLD)—formerly called NAFLD/NASH, representing significant hepatic fat accumulation and inflammation.
  • Low testosterone (hypogonadism)—on testosterone therapy
  • Erectile dysfunction—on tadalafil
  • Former smoker—quit after his MI

Each of these diagnoses is individually significant. Together, they form a metabolically devastating picture in which each condition both results from and perpetuates the others. Insulin resistance drives visceral fat accumulation, which drives inflammation, which drives atherosclerosis, which caused the MI and drives PAD. Sleep apnea worsens insulin resistance and hypertension. Low testosterone accelerates muscle loss and fat gain. MASLD reflects and contributes to systemic dyslipidemia and insulin resistance. Every condition feeds every other.

Body Composition Analysis in Sarcopenic Obesity

The body composition data obtained for Amit tells a story that the BMI alone cannot tell:

  • BMI 38.4—Class 2 obesity, significant but not the most clinically informative metric
  • 7% body fat—the majority of his body weight is fat mass; this is extremely elevated
  • Skeletal muscle mass 20.7%—placing him in the fourth percentile compared to age-, weight-, and height-matched peers; a profoundly low level of muscle mass
  • Visceral fat 4.4 liters (measured by bioimpedance)—significantly elevated; visceral fat is the metabolically active, inflammatory fat depot most strongly associated with cardiometabolic disease
  • Waist circumference 51.25 inches—far exceeding the clinical threshold (greater than 40 inches in men) associated with metabolic syndrome

The combination of high fat mass and low muscle mass is the definition of sarcopenic obesity—a condition that carries significantly higher health risks than either obesity or sarcopenia alone. The fact that Amit ranks in the fourth percentile for skeletal muscle mass relative to his peers is a striking clinical finding. It means that 96% of men his age, with his weight and height, have more muscle mass than he does.

The Acanthosis Nigricans, Skin Tags, and Physical Examination Findings

The physical examination findings reported for Amit include:

  • Acanthosis nigricans—a velvety, hyperpigmented thickening of the skin in the neck folds, axillae, and groin, which is a cutaneous marker of severe insulin resistance.
  • Skin tags (acrochordons)—also associated with insulin resistance and hyperinsulinemia.
  • Enlarged liver (hepatomegaly)—consistent with his diagnosis of stage 2 MASLD.
  • 1+ pitting edema in lower extremities—indicating impaired venous return.

Each of these physical findings is not isolated—together they form a coherent clinical narrative of advanced metabolic syndrome with multi-organ involvement.

Stepwise Care Plan: Nutrition, Movement, Medication, and Behavioral Stability

I prefer sequential rollouts to stabilize each pillar of a patient’s care plan. This allows us to attribute effects and avoid overwhelming the patient. This strategy applies to George, Lynn, Dolores, Amit, and our 25-year-old with PCOS.

Shared Decision-Making: Why the Sequence of Treatment Matters

One of the most instructive questions in clinical weight management is not simply what to treat, but in what order to treat it. When considering a perimenopausal woman like Lynn, the decision to initiate menopausal hormone therapy (MHT) before an obesity medication was made for several well-grounded reasons:

  • Perimenopause was her primary concern. Shared decision-making begins with listening. Addressing her most pressing concern first builds therapeutic trust and adherence.
  • She met clinical criteria for MHT. She was within the “window of opportunity” for hormone therapy, where benefits are most robust (Manson et al., 2017).
  • Starting one medication at a time allows for cleaner attribution of adverse effects.
  • Hormonal optimization may itself support metabolic improvement. Correcting the hormonal deficit can create a more receptive physiological environment for subsequent weight management interventions.

1. Nutrition Recalibration

For all our patients, the first step is a nutritional intervention. We shift from calorie-obsession to pattern-based, protein-forward, carbohydrate-restricted eating tailored for insulin resistance.

  • Target 4–5 small meals/day, spaced every 3–4 hours, minimizing long fasting windows that can provoke evening hyperphagia and binges.
  • Protein: 90–100 g/day (at least 1.2–1.6 g/kg ideal body weight), anchored at breakfast to blunt diurnal hunger curves and improve glycemic responses (Leidy et al., 2015). This is crucial for both Amin’s and Dolores’s sarcopenia.
  • Fiber: Emphasize non-starchy vegetables and whole fruit to 50–100 g/day total carbohydrate (net carbs individualized).
  • Minimize ultra-processed foods, refined starches, sweets, and limit alcohol.
  • Rationale: Lower glycemic load reduces postprandial insulin excursions; protein supports GLP-1/PYY responses, stabilizes appetite, and protects lean mass during weight loss (Hall & Guo, 2017). For Amit, we specifically recommend a Mediterranean dietary pattern, which aligns with his North African heritage and has strong evidence for cardiovascular benefit (Estruch et al., 2018).

2. Movement Dosing and Autonomic Support

Physical activity is a cornerstone, but it must be tailored to the patient’s ability.

  • For active patients, like our 25-year-old with PCOS, we maintain their robust routine.
  • For sedentary or pained patients, like George, Dolores, and Amit, we start small. We encouraged George to take the stairs at work. For Dolores and Amit, with significant mobility limitations, a referral to Physical Therapy (PT) is key.
  • A PT can design programs for strengthening supportive muscles (as in Dolores’s knee OA) and supervised exercise for conditions like Amit’s claudication. Cycling (stationary bike) is often a great option.
  • Add insulin-sensitizing micro-bouts: 10-minute brisk walks daily (postprandial preferred), progressing as tolerated (DiPietro et al., 2013).
  • Strength Training: All patients are encouraged to add resistance training at least twice weekly to preserve and build metabolically active muscle mass.

3. Medical Therapy with Internal Medicine Oversight

After setting nutrition and movement foundations, we introduce medical therapy under Dr. Cardenas’s supervision.

  • Metformin: For patients like our 25-year-old with PCOS/prediabetes, we initiate Metformin ER, titrating as tolerated. Metformin reduces hepatic gluconeogenesis, improves peripheral insulin sensitivity, and can aid weight stabilization in PCOS (Morley et al., 2017).
  • Hypertension Management: For George and Amit, controlling blood pressure with appropriate medication (like lisinopril for Amit) is an immediate priority.
  • Hormone Replacement: For Lynn, we started transdermal estrogen and progesterone to address her primary perimenopausal symptoms. Transdermal delivery is preferred to avoid first-pass hepatic metabolism and reduce VTE risk (Canonico et al., 2007).
  • Obesity Pharmacotherapy: Based on the patient’s profile and needs, we introduce powerful medications to assist with weight management.
  • Bupropion-Naltrexone: A good choice for George’s cravings and depression and Dolores’s evening sweet cravings (Guerin & Billes, 2016).
  • GLP-1/GIP Agonists (Semaglutide/Tirzepatide): These are game-changers. For Amit, semaglutide 2.4 mg (Wegovy) was chosen due to the SELECT trial, which demonstrated a 20% reduction in major adverse cardiovascular events in patients with pre-existing cardiovascular disease (Lincoff et al., 2023). For our PCOS patient and Lynn, tirzepatide was chosen for its potent dual-agonist effects on weight and metabolism (Frias et al., 2021).
  • Lisdexamfetamine: If binge-eating persists despite GLP-1/GIP stabilization, as in the case of our 25-year-old, we consider this FDA-approved medication with careful monitoring (McElroy et al., 2015).
  • Deprescribing Insulin: For Amit, a crucial step was tapering and stopping his exogenous insulin as the semaglutide improved his glycemic control. Continuing insulin would have risked hypoglycemia and perpetuated weight gain.

4. Behavioral Stability, Sleep, and Mental Health

  • Sleep Optimization: For all patients, but especially George and our PCOS patient, we emphasize 7-9 hours of consistent, high-quality sleep to normalize leptin/ghrelin signaling (Taheri et al., 2004). For patients like George and Amit with suspected sleep apnea, a sleep study is essential.
  • Stress Management: We made meditation accessible for George by suggesting a three-minute guided app in his car.
  • Mental Health Support: We referred Lynn to a therapist for grief counseling and encouraged ongoing therapy for all patients to address emotional eating, anxiety, and the psychological burden of chronic disease.

Addressing the Barriers: A Patient-Centered and Trauma-Informed Approach

A plan is only as good as a patient’s ability to implement it. Dolores, in particular, faced a significant barrier: a deep-seated fear of going to PT because she believed she would be judged for her weight, as she had been by healthcare providers in the past. Her fear is valid and born of negative experiences with weight bias.

My response to this must be one of empathy, validation, and empowerment.

  • Validate and Listen: The first step is to listen without judgment. I say things like, “Thank you for telling me that. I can completely understand why you would feel that way. Your experiences are real, and your feelings are valid.”
  • Advocate for the Patient: I explicitly tell her, “I am on your side. We are a team. I will advocate for you.” This might involve me personally calling the physical therapy clinic or the orthopedic surgeon’s office to reframe the conversation from one of patient blame to one of collaborative problem-solving.
  • Coach and Role-Play: We work together to prepare her for these appointments. We role-play conversations, transforming her from a passive recipient of judgment into an empowered partner in her own care.

My colleague’s point about BMI requirements for surgery is critically important. These blanket cutoffs are often not patient-centered and can feel so discouraging that patients give up. Advocating against these rigid, non-evidence-based protocols is part of our job as clinicians.

Why Integrative Chiropractic Care Belongs in Metabolic Care

Integrative chiropractic care is not a standalone weight-loss tool; it is a movement, pain, and autonomic optimization modality that elevates adherence to the core metabolic interventions. Within this comprehensive plan, my role as a chiropractor is to address the crucial connection between the nervous system and the body’s overall function.

  • Pain and Mobility: Chronic pain and limited mobility impose energetic and psychological barriers to consistent activity. For patients like Dolores with severe OA or Amit with claudication, musculoskeletal pain is the primary obstacle. By addressing lumbopelvic, thoracic, and rib biomechanics, I reduce mechanical load and pain. Patients walk more, lift more, and sit less, multiplying daily energy expenditure and insulin sensitivity gains. My clinical observations over decades, including reflections shared across my resources (see sciatica.clinic), suggest that reducing mechanical pain and improving segmental motion enhances patients’ capacity to sustain regular, insulin-sensitizing activity.
  • Autonomic Nervous System (ANS) Balance: Chronic stress, like George was experiencing, places an immense load on the ANS, leaving patients stuck in a state of sympathetic dominance (“fight or flight”). Chiropractic adjustments, particularly in the upper cervical and thoracic regions, can help modulate the ANS, promoting a shift to parasympathetic activity (“rest and digest”). This can lead to a reduction in resting heart rate and blood pressure, improved heart rate variability (HRV), enhanced digestive function, and a subjective feeling of calmness and well-being.
  • Neuromuscular Re-education: For patients with sarcopenic obesity like Amit and Dolores, chiropractic rehabilitation is critical. We address joint misalignments and compensatory movement patterns, making their physical therapy and strength training safer and more effective. Graded exposure and neuromuscular re-education build confidence and reduce fear-avoidance, stabilizing the actionable lifestyle domain where medications exert their greatest synergistic benefits.

In multidisciplinary care, the chiropractor’s role is a movement and function specialist, complementing the internist’s medical management. With Dr. Cardenas coordinating safety and metabolic pharmacology, I ensure our patient can physically and neurologically engage the program at a high level—and keep doing so over months and years.

Clinical Outcomes: The Power of an Integrated Approach

The journeys of our patients demonstrate what is possible with a comprehensive, patient-centered, and integrative approach.

The 25-Year-Old with PCOS: Two-Year Outcomes

  • Total weight reduction: 24.1% from baseline.
  • Fasting insulin: 8.4 µIU/mL (normalized from 36.1).
  • HOMA-IR: normalized.
  • A1c: 5.2% (normoglycemic range, down from 6.0%).
  • Binge-eating: effectively resolved with the addition of lisdexamfetamine.
  • Fertility Planning: The patient is now well-positioned to contemplate pregnancy with lower cardiometabolic risk and improved ovulatory potential.

George (Male Infertility): One-Year Outcomes

  • A New Baby on the Way: His spouse was pregnant, a direct result of improving his metabolic and hormonal health.
  • HOMA-IR: Dropped from 3.1 to 64 (insulin sensitive).
  • HbA1c: Moved from 9% (prediabetic) to the normal range.
  • Blood Pressure: Well-controlled.
  • Medication: Found his “sweet spot” on semaglutide 1.7 mg weekly, sufficient to control appetite without needing the maximum dose.

Amit (Cardiometabolic Syndrome): One-Year Outcomes

  • Weight Loss: Achieved a 3% reduction in total body weight.
  • Insulin: Successfully tapered off all exogenous insulin.
  • Fasting Insulin: Dropped to 1 µU/mL from a much higher baseline on insulin.
  • HbA1c: Decreased to 0% (from uncontrolled diabetes).
  • Body Composition: Body fat decreased from 56.7% to 1%, while skeletal muscle mass percentile increased from 4th to 25th.
  • Function: Claudication pain is minimal, and he enjoys daily exercise.

Dolores (Osteoarthritis): One-Year Outcomes

  • Surgery and Recovery: Successfully had her first knee replacement with no complications and is planning her second.
  • Body Composition: Achieved a 7% body weight reduction while increasing her muscle mass percentile from 2nd to 10th.
  • Labs: Fasting insulin is now in the normal range.
  • Quality of Life: Her ultimate goal is within reach: she is planning her trip to Europe.

What Success Looks Like in Our Clinic

  • Biomarkers: Fasting insulin trending to single digits, HOMA-IR into normal range, A1c into the low 5s, triglycerides down, HDL up, ALT/AST normalization.
  • Symptoms: Acne and hirsutism reduced, cycles become more regular, energy improves, and sleep stabilizes.
  • Behavior: Binge episodes diminish or resolve; anxiety around calories subsides; movement becomes routine and enjoyable.
  • Structure: Chiropractic sessions reduce pain barriers; internal medicine oversight ensures safe and effective pharmacotherapy; functional supports keep the system resilient.

Conclusion: The Power of Integrative and Compassionate Care

The cases of these patients powerfully illustrate that obesity is a complex, chronic disease that requires a sophisticated, multifaceted, and deeply compassionate approach. At Injury Medical Clinic, our integrative model—combining chiropractic care for musculoskeletal function, medical oversight from Dr. Cardenas for complex disease management and pharmacotherapy, and a functional medicine lens to seek root causes—allows us to create these kinds of life-changing outcomes.

By treating obesity with the seriousness and scientific rigor it deserves, we can help our patients not just lose weight, but regain their health, their function, and their lives. I appreciate your commitment to this important work.

Disclosures, Safety, and Individualization

  • Some medications discussed (e.g., metformin for prediabetes/PCOS without diabetes) may be off-label; we follow current guidelines and evidence, discuss risks/benefits, and obtain informed consent.
  • GLP-1/GIP therapies require contraceptive planning; we advise barrier methods during initiation and titration if using oral contraceptives due to delayed gastric emptying considerations referenced in product information.
  • Lisdexamfetamine is FDA-approved for binge-eating disorder but demands careful cardiovascular and psychiatric monitoring.

References

SEO Tags: perimenopause hormone therapy, menopausal hormone therapy El Paso, tirzepatide weight loss, semaglutide cardiovascular outcomes, GLP-1 receptor agonist, sarcopenic obesity treatment, type 2 diabetes insulin deprescribing, integrative chiropractic care metabolic disease, functional medicine El Paso Texas, body composition monitoring obesity, obesity medicine shared decision making, incretin based therapy mechanism of action, Dr Alex Jimenez DC APRN, Injury Medical Clinic PA El Paso, Dr Maria Cardenas MD internal medicine El Paso, peripheral artery disease exercise therapy, MASLD treatment semaglutide, muscle mass preservation GLP-1 therapy, food noise GLP-1, Mediterranean diet type 2 diabetes, sarcopenia resistance training protein intake, dual incretin agonist tirzepatide mechanism, SELECT trial semaglutide cardiovascular, chiropractic autonomic nervous system, weight management multidisciplinary care, integrative medicine obesity, cardiometabolic risk reduction El Paso, perimenopausal weight gain estrogen, transdermal estradiol perimenopause, obesity hormonal disease biology, PCOS treatment, insulin resistance, GLP-1 therapy, metformin, binge eating disorder, lisdexamfetamine, women’s health, fertility and PCOS, HOMA-IR, A1c improvement, dyslipidemia, metabolic syndrome, postprandial walking, protein-forward diet, sciatica clinic, El Paso chiropractor, Mission Plaza Injury Medical Clinic, Male Infertility, Prediabetes, Hypertension, Low Testosterone, Bupropion-Naltrexone, Stress Management, Visceral Fat, Osteoarthritis, Knee Replacement, Weight Bias in Healthcare, Patient-Centered Care, Phentermine, Cardiometabolic Syndrome, Musculoskeletal Health, Personal Injury Clinic

Regenerative Medicine for Auto and Work Accidents

Regenerative Medicine for Auto and Work Accidents

Regenerative Medicine for Auto and Work Accident Joint Injuries

Abstract

Automobile crashes and work accidents can damage joints, tendons, ligaments, muscles, spinal discs, and nearby nerves. Pain medicine may help provide short-term comfort, but it does not always improve the injured tissue or correct movement problems that continue to stress it.

Regenerative and targeted injection treatments may offer another option for selected patients. Platelet-rich plasma (PRP), platelet-fibrin products (PFP), and microfragmented adipose tissue (MFAT) use materials taken from the patient’s own body to support healing. Epidural spinal injections work differently because they mainly reduce inflammation around irritated spinal nerves.

Peptide therapies are also being studied, but they require caution because human research and long-term safety information remain limited. A complete treatment plan may combine medical oversight, integrative chiropractic care, functional medicine, rehabilitation, and a gradual return to work or daily activity.

Regenerative Medicine for Auto and Work Accidents

Why Joint Pain Can Continue After an Accident

A car crash, fall, lifting injury, or repeated work strain can affect more than one part of the body. A knee may twist, a shoulder may be pulled, or the spine may be compressed. The injury may involve:

  • Joint cartilage
  • The joint capsule
  • Tendons and ligaments
  • Muscles and connective tissue
  • Spinal discs
  • Spinal nerve roots

Swelling and muscle guarding may then limit movement. The body often protects the painful area by changing how it moves. A person with knee pain may limp. Someone with a shoulder injury may use the neck and upper back to lift the arm. A worker with lower back pain may avoid bending and place more pressure on the hips.

Over time, these changes may create weakness, stiffness, poor balance, and added strain on nearby joints. Treatment should therefore look beyond the pain score. The care team should identify the injured tissue, check for nerve irritation, study how the patient moves, and determine whether the joint is stable enough for daily activity and work.

PRP: Concentrated Healing Signals From the Blood

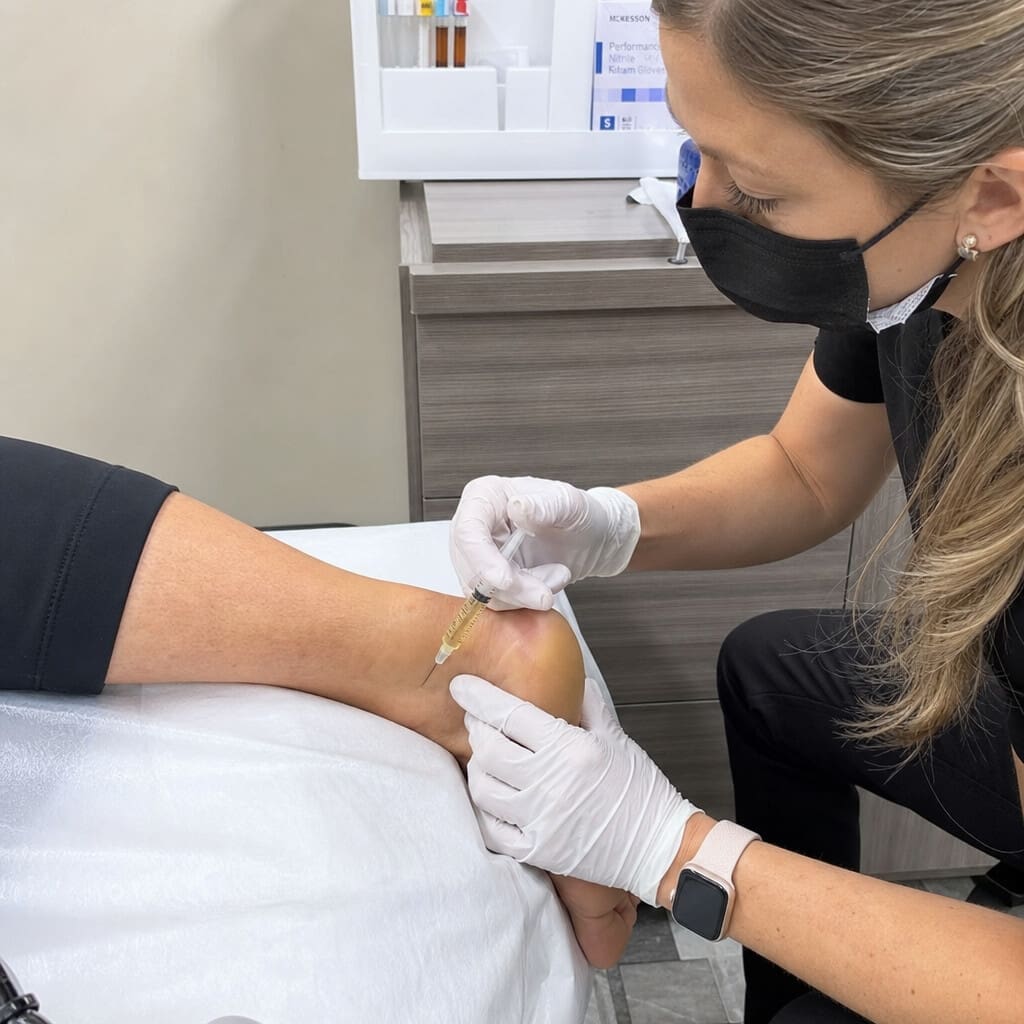
Platelet-rich plasma treatment begins with a blood draw. The blood is placed in a centrifuge, which separates and concentrates the platelets. The prepared PRP is then injected into a selected joint, tendon, ligament, or muscle. Ultrasound or another imaging method may be used to guide the injection.

Platelets are best known for helping the blood clot. However, they also release growth factors and chemical signals involved in tissue repair. These signals may help manage inflammation, support collagen production, improve blood flow, and create a better local healing response (UPMC, n.d.).

PRP may be considered for:

  • Knee, hip, shoulder, or ankle joint pain
  • Tendon injuries
  • Ligament sprains
  • Partial soft-tissue tears
  • Early or moderate osteoarthritis
  • Pain that continues after conservative care

PRP has more human research than many other regenerative treatments. A meta-analysis of randomized trials found meaningful improvements in pain and function for many patients with knee osteoarthritis. However, results may depend on the condition, platelet concentration, preparation method, number of injections, and the patient’s overall health (Bensa et al., 2025).

PRP should not be described as a guaranteed cure or as a method that can rebuild a completely damaged joint. It is better understood as a treatment that may improve the healing environment around selected injuries. Temporary soreness may occur, and improvement often develops over several weeks or months rather than overnight.

PFP: A Fibrin Framework for Repair

Platelet-fibrin products are sometimes called platelet-rich fibrin (PRF). Like PRP, they are made from the patient’s own blood. The main difference is the fibrin framework.

Fibrin is a natural protein involved in clot formation. It may create a soft scaffold that holds platelets, white blood cells, and healing signals near the treatment area. This framework may allow some growth factors to be released over a longer period than with certain liquid PRP preparations (Farshidfar et al., 2025).

Possible goals of PFP treatment include:

  • Supporting slow-healing soft tissue
  • Holding platelets near the injured area
  • Providing a temporary repair framework
  • Supporting tendons and ligaments
  • Working alongside controlled rehabilitation

PFP products are not all prepared in the same way. The research is also less standardized than the evidence for PRP. Patients should ask which platelet-fibrin product is being used, how it is prepared, why it is being recommended, and what research supports that specific use.

MFAT: Support From the Patient’s Own Fat

Microfragmented adipose tissue is prepared from a small amount of the patient’s own fat. The fat is collected through a minimally invasive procedure, washed, and mechanically processed into smaller sections.

MFAT keeps much of the fat tissue’s natural support structure. Adipose tissue contains signaling cells, blood-vessel support cells, and other components that may help manage inflammation and support tissue repair.

MFAT has been studied most often for joint conditions such as knee osteoarthritis. Research comparing MFAT with PRP has found that both treatments may improve pain and function in selected patients. However, MFAT is not automatically better than PRP, and the right choice depends on the diagnosis and the severity of the damage.

MFAT may be considered when:

  • Joint pain is more advanced
  • Cartilage wear is present
  • Earlier conservative care has not provided enough relief
  • The patient wants to delay joint surgery
  • A larger tissue-based product may be appropriate

MFAT is more involved than a blood draw. It requires fat collection, sterile processing, and careful placement into the treatment area. It also cannot guarantee that damaged cartilage will completely regrow. A medical evaluation is needed to review infection risk, bleeding risk, medications, medical conditions, and whether surgery may be the safer choice.

Academic medical centers commonly include MFAT as one possible part of an evidence-based regenerative medicine program rather than as a stand-alone cure for every joint problem (University of Iowa Health Care, n.d.).

Epidural Spinal Injections Calm Inflamed Nerves

Epidural spinal injections are sometimes grouped with regenerative treatments, but they are not regenerative in the same way as PRP, PFP, or MFAT.

Most epidural injections place a corticosteroid, sometimes with a local anesthetic, into the space around the spinal nerves. The medication is intended to reduce inflammation around an irritated or compressed nerve root.

Epidural spinal injections may be considered when an automobile or work-accident causes:

  • A herniated or bulging spinal disc
  • Sciatica
  • Cervical radiculopathy
  • Lumbar radiculopathy
  • Pain traveling into an arm or leg
  • Numbness or tingling caused by nerve irritation

The goal is to create a period of lower pain and better movement. This treatment window may help the patient participate more comfortably in chiropractic care, walking, physical rehabilitation, and strengthening exercises.

The benefits are often short-term. A 2025 American Academy of Neurology review found that epidural steroid injections may provide modest short-term pain or disability improvement for some people with radiculopathy. Long-term benefits were less certain (American Academy of Neurology, 2025).

Possible risks include:

  • Temporary blood sugar changes
  • Bleeding
  • Infection
  • Headache
  • Temporary numbness
  • Reactions to the medication
  • Rare nerve injury

Careful patient selection, sterile technique, and image guidance are important.

Peptide Therapies: Promising but Still Emerging

Peptides are short chains of amino acids that act as signals in the body. Some clinics discuss peptides such as BPC-157 or thymosin-related products for tendon, ligament, muscle, or joint recovery.

Animal and laboratory studies have raised interest in their possible effects on inflammation, blood-vessel growth, and tissue repair. However, strong human evidence remains limited. Large randomized clinical trials are lacking for many peptides promoted for musculoskeletal injuries (Levo Health, 2025).

The U.S. Food and Drug Administration has identified important concerns involving compounded BPC-157 and several other peptides. These concerns include possible immune reactions, peptide-related impurities, product-quality problems, and limited safety information. The FDA states that it lacks enough information to know whether compounded BPC-157 may cause harm when given to humans.

Peptide therapy should not be presented as equal to PRP or as a proven treatment for accident-related joint damage. A medical discussion should cover:

  • FDA approval and regulatory status
  • The quality of available human studies
  • Known and unknown risks
  • The source of the product
  • Possible medication interactions
  • Medical conditions that may increase risk
  • Better-studied treatment choices

Peptide therapy should never replace a correct diagnosis, rehabilitation, or necessary surgery.

How Integrative Chiropractic Care Fits In

An injection may support the tissue or reduce inflammation, but the patient still has to move, work, lift, walk, and regain strength. Integrative chiropractic care addresses the mechanical side of recovery.

Depending on the diagnosis and stage of healing, chiropractic care may include:

  • Gentle joint mobilization
  • Spinal manipulation when appropriate
  • Soft-tissue treatment
  • Posture education
  • Safe lifting instruction
  • Corrective exercises
  • Balance and walking training
  • Spinal decompression for selected conditions
  • A gradual return-to-work plan

The goal is not simply to “put a joint back in place.” A better goal is to improve safe movement, reduce stiffness, decrease repeated stress, and help the patient use the healing tissue correctly.

Recent clinical guidelines for lower back pain commonly include exercise, remaining active, and spinal manipulation among the non-drug options that may be considered for selected patients (Zhou et al., 2024).

Rehabilitation is also important because muscles protect joints by controlling movement. A combined care plan may follow these steps:

  1. Reduce severe pain and inflammation.
  2. Restore comfortable joint and spinal motion.
  3. Rebuild strength, balance, and endurance.
  4. Practice work and daily-life movements.
  5. Return to normal activity in safe stages.

Dr. Jimenez’s published clinical observations emphasize that regenerative treatment, chiropractic care, and rehabilitation have different but connected jobs. Biological treatments may support the healing environment. Chiropractic care may improve joint movement and reduce harmful compensation. Rehabilitation helps the patient rebuild strength and use the treated tissue properly (Jimenez, 2026).

A Multidisciplinary Treatment Model in El Paso

Clinic materials identify Dr. Maria Guadalupe Cardenas, MD, as board-certified in internal medicine and as the medical director and collaborative physician at Injury Medical Clinic PA in El Paso, Texas.

The clinic lists:

  • NPI: 1164426749
  • Texas medical license: J2933
  • Experience: More than 40 years in internal medicine

In this multidisciplinary model, Dr. Cardenas provides medical direction and internal-medicine oversight. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, focuses on chiropractic care, musculoskeletal evaluation, functional medicine, personal injury care, and rehabilitation.

The team may coordinate:

  • Medical screening
  • Diagnostic imaging
  • Medication review
  • Regenerative treatment decisions
  • Chiropractic treatment
  • Functional medicine services
  • Personal injury documentation
  • Exercise progression
  • Nutrition support
  • Return-to-work planning

This type of coordinated care addresses both biological healing and physical movement. Medical oversight helps identify health risks and determine whether an injection is appropriate. Chiropractic care works on joint mobility, spinal function, and movement patterns. Rehabilitation rebuilds strength, balance, and work ability.

Clinical observations from Dr. Jimenez are useful for explaining this coordinated approach, but they do not replace controlled medical research or an individual examination.

Choosing the Right Treatment

No regenerative treatment is right for every automobile or work injury. A complete evaluation should consider:

  • The exact diagnosis
  • Imaging findings
  • Joint stability
  • Range of motion
  • Nerve symptoms
  • Previous treatments
  • Current medications
  • Diabetes or immune conditions
  • Work duties
  • Recovery goals
  • The quality of evidence

A responsible treatment plan should use realistic language. It should not promise a cure, complete cartilage regrowth, or guaranteed avoidance of surgery.

Patients should receive clear information about treatment costs, alternatives, risks, expected recovery time, and how progress will be measured. Evidence-based guidelines also stress that regenerative treatment decisions should be based on the diagnosis, available research, patient preferences, and professional medical judgment (D’Souza et al., 2024).

Conclusion

PRP, PFP, and MFAT may support healing for selected joint, tendon, and ligament injuries after automobile or work accidents. Epidural spinal injections may reduce inflammation around irritated spinal nerves, but they are mainly pain and inflammation treatments rather than regenerative procedures.

Peptide therapies remain experimental for many musculoskeletal uses and require careful medical review. They should not be promoted as proven replacements for PRP, rehabilitation, or standard medical care.

The strongest treatment plan addresses both biology and movement. Medical oversight guides safety and treatment choices. Integrative chiropractic care improves mobility and body mechanics. Rehabilitation rebuilds strength and function.

Together, these services may help selected patients move beyond temporary symptom control and work toward a safer and more complete recovery.

El Paso, TX Chiropractic Care For Auto Accidents

References

American Academy of Neurology. (2025). Epidural steroids for cervical and lumbar radicular pain and spinal stenosis.

Bensa, A., Previtali, D., Sangiorgio, A., Boffa, A., Salerno, M., & Filardo, G. (2025). PRP injections for the treatment of knee osteoarthritis: The improvement is clinically significant and influenced by platelet concentration. The American Journal of Sports Medicine.

D’Souza, R. S., Her, Y. F., Hussain, N., Karri, J., Schatman, M. E., Calodney, A. K., et al. (2024). Evidence-based clinical practice guidelines on regenerative medicine treatment for chronic pain. Journal of Pain Research, 17.

Farshidfar, N., et al. (2025). Platelet-rich plasma versus injectable platelet-rich fibrin: A systematic review across all fields of medicine. Periodontology 2000.

FoRM Health. (2025). Understanding regenerative injection therapies: PRP, MFAT, and prolotherapy.

Goulian, A. J., Goldstein, B., & Saad, M. A. (2025). Advancements in regenerative therapies for orthopedics. Journal of Clinical Medicine, 14(6), 2061.

Health Coach Clinic. (n.d.). Regenerative options for personal injury recovery.

Jimenez, A. (2026, July 27). How regenerative medicine and chiropractic care work together. LinkedIn.

Jimenez, A. (n.d.). Dr. Maria Cardenas, MD: Board-certified internal medicine specialist.

Levo Health. (2025, June 16). Peptide injections versus platelet-rich plasma therapy for musculoskeletal injuries.

University of Iowa Health Care. (n.d.). Regenerative medicine.

UPMC. (n.d.). Regenerative injection therapy.

U.S. Food and Drug Administration. (n.d.). Certain bulk drug substances for use in compounding that may present significant safety risks.

Zhou, T., et al. (2024). Recent clinical practice guidelines for the management of low back pain.

Telemedicine: Benefits and Insights in Regenerative Therapy

Revolutionize your health journey with regenerative therapy via telemedicine for personalized, effective treatment.

Abstract

In this educational post, I share how we at Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, integrate advanced, evidence-based methods to support patients after personal injury. Drawing on my roles as DC, APRN, FNP-BC, CFMP, IFMCP, ATN, and CCST, I detail our multidisciplinary collaboration with our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), who brings over 40 years of clinical experience. I walk through our modern digital outreach and qualification processes, the clinical physiology behind integrative chiropractic care, functional medicine diagnostics, rehabilitation strategies, and medically supervised adjunctive therapies such as PRP and IV nutrition. I also present how AI-enabled intake, SEO, and ethical advertising connect patients to care, and I summarize relevant findings from leading researchers to ground our protocols in modern, evidence-based practice. Clinical observations from my ongoing publications and case narratives illustrate real-world outcomes.

A Multidisciplinary, Medically Directed Model of Care

I am Dr. Alex Jimenez, and for more than three decades I have committed my practice to an integrated approach that unites chiropractic care, internal medicine oversight, functional medicine, rehabilitation, and personal injury management. Our clinical engine is a collaborative MD–DC model:

  • Medical Oversight by Dr. Maria Guadalupe Cardenas, MD: Board Certified in Internal Medicine (NPI #1164426749; Texas MD License #J2933), Dr. Cardenas serves as our Medical Director and Collaborative Physician. Her four decades of internal medicine experience ensure comprehensive differential diagnosis, safe pharmacologic management when needed, and medico-legal rigor.
  • Integrative Chiropractic Care by Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST: I focus on neuromusculoskeletal biomechanics, spinal alignment, neurodynamics, pain modulation, and rehabilitation integration.
  • Functional Medicine: We evaluate systems biology drivers—immune, endocrine, gut–brain axis, mitochondrial function—and personalize protocols to address root causes.
  • Rehabilitation and Reconditioning: We employ graduated loading, neuromotor retraining, mobility restoration, and strength scaffolding in a full gym and rehab environment.
  • Personal Injury Protocols: We aggregate diagnostics, clinical documentation, and coordinated care plans aligned with legal and insurance frameworks.

This integrated setup—a medically directed, multidisciplinary clinic—has become a best-practice structure in both integrative and injury care, blending the strengths of internal medicine and chiropractic to improve diagnostic completeness, treatment safety, and outcomes (Whedon & Bezdjian, 2021).

Modern, Ethical Patient Outreach and AI-Enabled Intake

On 2026-07-13, I reflected on how technology has transformed ethical patient outreach. We designed a value-first, compliant strategy that places patients in control.

  • Targeted, Value-Driven Messaging: We use Meta platforms to present simple, educational content that helps people within 12–72 hours post-accident find safe, accurate guidance. These messages are not sales pitches; they are practical, evidence-informed steps.
  • Consent-Based Language Pattern Recognition: Platforms can detect user-initiated accident-related discussions and deliver helpful materials to people actively seeking answers—without violating privacy.
  • Patient-Initiated Contact: Individuals choose to click through, read, and complete a detailed questionnaire. The connection begins with the patient, making this pathway ethical and compliant.

Once a person engages, GoHighLevel CRM and tools like ReviewWave orchestrate intake and scheduling while our on-site and remote teams qualify cases and ensure no patient is lost in the transition from interest to appointment (Salesforce, 2023; GoHighLevel, n.d.). We also integrate an AI assistant—”Charlie AI”—to guide questions, route intake forms, and book visits, creating multiple managed, controlled pathways that minimize friction and maximize clarity.

The Patient Journey: Lead to Contact to Care

We distinguish between leads and contacts to focus resources on patient care:

  • Leads: Individuals who express interest but have not yet visited. They receive educational support, follow-ups, and clear scheduling pathways.
  • Contacts: People who have physically arrived. At this stage, the relationship deepens, and the clinical journey starts.

Once a patient becomes a contact, our attrition rate drops dramatically because care shifts from transactional to relationship-based healthcare—a core principle supported by outcomes research in clinician–patient alliance (Ventres & Frankel, 2015). My clinical experience confirms that the most important step is crossing the threshold into our clinic; face-to-face, trust can be established, and we can begin a structured plan toward relief and recovery.

Comprehensive Qualification for Personal Injury Patients

To steward resources and ensure fit, we perform a meticulous, PI-focused screening:

  • Accident Details: Mechanism, vector forces, time since injury.
  • Role and Fault Status: Driver/passenger, liability context.
  • Immediate Care: ER visits, imaging, prior interventions.
  • Symptomatology: Neck pain, back pain, headaches, radicular symptoms, paresthesias.
  • Insurance: PIP/MedPay status, claim numbers.
  • Legal Representation: Coordination with attorneys for documentation integrity.

This pre-qualification builds an actionable case file before the first appointment, enabling us to enter patients directly into the EHR and schedule diagnostic and treatment steps without delay. In a high-volume, 20,000-square-foot facility seeing nearly 400 patients per week, efficiency ensures quality does not suffer.

Integrative Chiropractic Care: Physiological Foundations and Clinical Rationale

Integrative chiropractic care is central to our PI model. The physiology drives the plan:

  • Biomechanical Restoration: Acceleration–deceleration forces can precipitate segmental dysfunction and joint position errors, producing nociceptive bombardment and reflexogenic spasm. Chiropractic adjustments apply precise, graded forces to facilitate joint cavitation, reduce facilitated segments, and restore arthrokinematics, which lowers aberrant afferent signaling and normalizes reflex tone.
  • Neurodynamic Recovery: Segmental malalignment and disc–facet pathology alter nerve root mechanosensitivity, provoking radiculopathy. Adjustments and spinal decompression reduce compressive and shear loads, optimize foraminal patency, and modulate dorsal horn excitability, improving pain transmission and motor unit recruitment.
  • Soft Tissue Remodeling: Post-injury, microtrauma and ligamentous sprain generate inflammatory cascades (e.g., elevated cytokines). Myofascial release, instrument-assisted soft tissue mobilization, and therapeutic exercise promote collagen realignment, improve interstitial fluid dynamics, and reduce fibroblast-driven maladaptive scar remodeling.
  • Foundation for Adjunct Therapies: Proper spinal alignment and neuromuscular normalization improve the response to PRP injections, IV nutrition, and progressive rehabilitation by reducing local inflammatory load, optimizing perfusion, and facilitating programmed motor relearning.

Evidence-based guidelines support multimodal care in whiplash-associated disorders and neck pain, endorsing mobilization/manipulation, therapeutic exercise, and education within an integrated framework (Côté et al., 2016). Meta-analyses demonstrate the utility of manipulation/mobilization for non-specific low back pain in select populations (Salehi et al., 2020). Biomarker studies suggest manual therapy can modulate pain pathway mediators (Goertz et al., 2018), aligning with observed reductions in pain and disability in our clinic.

Internal Medicine Oversight: Risk Management and Diagnostic Depth

Under Dr. Cardenas’s medical direction:

  • Systemic Screening: We evaluate for occult cardiometabolic disease, rheumatologic conditions, neuropathies, and endocrine contributors that can amplify pain and delay healing.
  • Medication Safety: Where necessary, we manage analgesics, anti-inflammatories, and co-morbidity treatments within best-practice standards, minimizing polypharmacy and adverse interactions.
  • Medico-Legal Integrity: MD oversight strengthens case documentation, ensuring alignment with insurer and legal requirements, particularly in contested liability scenarios.

This co-management model augments chiropractic diagnostics with internal medicine’s systemic lens, producing a more complete characterization of patient health and lowering risk across the arc of care (Whedon & Bezdjian, 2021).

Functional Medicine: Investigating the “Why” Behind Persistent Pain

Functional medicine complements structural care by identifying multi-system drivers:

  • Inflammation and Immune Modulation: We assess CRP, IL-6, oxidative stress markers, micronutrient status, and gut permeability indicators. Tailored nutrition plans, elimination diets, and professional-grade supplementation target dysregulated immune responses that perpetuate central sensitization and myofascial pain.
  • Endocrine and Stress Axes: Chronic stress and sleep disruption dysregulate the HPA axis, elevating cortisol and impairing tissue repair. We implement sleep hygiene, stress modulation techniques, and, when appropriate, adaptogenic support to restore physiologic rhythms.
  • Gut–Brain–Muscle Axis: Dysbiosis can alter short-chain fatty acid profiles, influencing pain perception and muscular endurance. Microbiome support and dietary strategy enhance systemic resilience and reduce neuroinflammation.

By lowering systemic inflammatory tone and improving metabolic readiness, patients respond more robustly to spinal adjustments and rehab strategies, accelerating recovery and reducing relapse risk (Haffner, 2021).

Rehabilitation: From Pain Control to Performance

We progress rehabilitation through phases:

  • Phase 1: Pain Modulation and Mobility Restoration: Gentle mobility work, segmental stabilization, and breath mechanics reduce hypertonicity and facilitate parasympathetic engagement, improving pain thresholds and range of motion.
  • Phase 2: Motor Control and Endurance: We focus on local stabilizers (e.g., multifidus, transverse abdominis), proprioceptive training, and graded loading to reestablish spinal stiffness profiles and coordination patterns.
  • Phase 3: Strength and Resilience: Kinetic chain integration, anti-rotation drills, and hip–spine coupling patterns prevent recurrence by correcting mechanical faults and building load tolerance.
  • Phase 4: Return to Life/Work/Sport: We perform task-specific conditioning and stress inoculation, scaling impact and complexity to match real-world demands.

This scaffolded approach recognizes that pain relief without neuromotor reprogramming risks recurrence; durable outcomes require restoring normalized movement strategies and tissue capacity.

Advanced Therapies: PRP, IV Nutrition, and Adjunct Modalities

For select cases, we add medically supervised adjuncts:

  • Platelet-Rich Plasma (PRP): Concentrated autologous platelets deliver growth factors that stimulate tenocyte activity and collagen synthesis, useful in chronic tendinopathy or ligament sprain. Proper alignment and tissue mobility improve PRP efficacy by enhancing microcirculatory flow and reducing competing inflammatory signals.
  • IV Nutritional Therapies: Targeted infusions mitigate deficiencies and support mitochondrial function in patients with poor gut absorption or high metabolic demand. These are integrated after medical assessment by Dr. Cardenas.
  • Decompression and Neuromodulation: Spinal decompression modifies axial loading and diffusion dynamics in discs; neuromodulation strategies (e.g., TENS for gate control) may complement pain management programs.

These therapies are employed selectively, grounded in physiologic plausibility, patient-specific indicators, and monitored outcomes.

The Chiropractic Approach for Pain Relief- Video

The Chiropractic Approach for Pain Relief | El Paso, Tx (2023)

Digital Discovery: SEO, AI Search, and Ethical Advertising

In the modern web ecosystem, discoverability ensures access to care:

  • SEO Foundations: We maintain content-rich websites, including my ongoing clinical observations on sciatica and related disorders (https://sciatica.clinic/) and my professional portfolio (https://www.linkedin.com/in/dralexjimenez/), to educate and guide patients and clinicians. Detailed, expert-driven writing supports high-quality information retrieval by search engines and AI models (Sterling, 2023).
  • AI-Driven Search: As conversational queries rise, comprehensive educational content helps AI systems identify authoritative clinical answers, directing patients to multidisciplinary care.
  • Specialized Campaigns: We partner with PI-focused teams to ensure compliant, precise messaging. Platforms such as GoHighLevel streamline tracking and communication; we favor performance-linked partnerships that prioritize quality and retention (Saleh & Biba, 2022).

Our ethics remain unwavering: we do not solicit patients under active care elsewhere, and we avoid superlative claims. Our outcomes and patient relationships speak for themselves.

Economics of Sustainable Care: Cost Per Case and Lifetime Value

We monitor acquisition economics to sustain access:

  • Cost Per Case: Effective PI acquisition typically ranges from $175 to $350; our blended average is about $300 across patient types. Performance billing with partners (e.g., $150 per shown and qualified appointment after a grace cohort) aligns incentives for patient quality and continuity.
  • Lifetime Value (LTV): The patient relationship extends beyond initial visits—ongoing wellness, functional medicine consultations, and family referrals compound value. Long-term trust returns both health and economic dividends.

Our practice has served El Paso since the early 1990s, with more than 150,000 patients treated. Community trust, paired with data-driven systems and compassionate care, fuels sustained growth.

Telehealth Horizons: Compliance-First Weight Management and Peptide Care

As an APRN licensed in seven states (with planned expansions), I evaluate telehealth platforms that integrate intake, prescribing, and pharmacy workflows:

  • Compliance Imperatives: We require sourcing from 503A/503B compounding pharmacies for sterile solutions—never research-grade powders. The risk profile and regulatory environment demand impeccable standards (U.S. FDA, 2023).
  • Platform Vetting: We assessed solutions including DoctorWell, Ember, LegitRX, WhiteLabelMD, and CareValidate for integration with GoHighLevel, ensuring vertical alignment from telehealth to brick-and-mortar (CareValidate, n.d.).
  • GLP-1 and Peptides: Demand is high for weight management therapies (e.g., semaglutide). Our stance remains strict: only compliant, medically justified prescriptions with verified sourcing and MD oversight.

Success built on non-compliant foundations is a liability; we choose sustainable, ethically sound models that protect patients and licensure.

Clinical Observations and Practical Outcomes

Across my clinical documentation and case observations (https://sciatica.clinic/), recurring themes emerge:

  • Patients with post-accident neck pain and headaches respond best to a triad of gentle mobilization/manipulation, education, and progressive exercise—consistent with guideline-based care (Côté et al., 2016).
  • In lumbar radiculopathy, combining decompression and targeted adjustments with core retraining reduces flare cycles, likely by normalizing disc hydration dynamics and reducing dorsal root ganglion mechanosensitivity.
  • Functional medicine interventions that lower systemic inflammation frequently reduce pain amplification, improving the responsiveness to manual therapy and rehabilitation load progressions.
  • Medically supervised adjuncts (PRP, IV nutrition) help select refractory cases when structural alignment and soft tissue dynamics are optimized first, reiterating the importance of sequencing.

Our integrated protocols are not one-size-fits-all; they are precision pathways that reflect each patient’s physiology, stressors, and life demands.

References

SEO Tags

Dr. Alex Jimenez, integrative chiropractic care, multidisciplinary clinic, Dr. Maria Guadalupe Cardenas, personal injury treatment, El Paso chiropractor, functional medicine, patient acquisition, lead management, relationship-based healthcare, advanced AI in healthcare, search engine optimization for doctors, cost per case, lifetime patient value, GoHighLevel, Texas chiropractic board rules, injury medical clinic, collaborative physician, internal medicine and chiropractic, whiplash treatment, back pain relief, sciatica, PRP therapy, spinal rehabilitation, ethical digital healthcare marketing, PI Docs, ReviewWave, CareValidate, 503A pharmacy compliance, telehealth weight management, GLP-1 therapy


Peptides for Sciatica Relief: How They Work

Peptides for Sciatica Relief: How They Work

Peptides for Sciatica Relief: How Targeted Peptide Support and Integrative Chiropractic Care Work Together for Nerve Recovery

Sciatica causes sharp, shooting pain that travels from the lower back down one leg. It often brings numbness, tingling, or weakness. The problem usually starts when a disc, tight muscle, or spinal misalignment presses on the sciatic nerve or nearby roots. Inflammation then adds chemical irritation on top of the physical pressure. Standard care can ease symptoms, yet many people still search for ways that address both the mechanical squeeze and the cellular damage.

Research and clinical practice now point to specific peptides that support nerve repair and pain control. When these peptides are paired with integrative chiropractic care, the combination offers mechanical relief plus cellular regeneration. This approach is used at practices such as Injury Medical Clinic PA in El Paso, Texas.

Peptides for Sciatica Relief: How They Work

Understanding Sciatica and Why Dual Support Matters

The sciatic nerve is the longest nerve in the body. Pressure from a herniated disc, spinal stenosis, or piriformis muscle can compress it. At the same time, local inflammation sensitizes the nerve and slows healing. Purely structural treatments free the nerve but leave residual tissue damage. Purely chemical treatments calm inflammation but leave ongoing mechanical stress. Combining both creates a clearer path to recovery.

Specific Peptides Studied for Nerve Repair and Pain Modulation

Several peptides have been examined for their effects on nerve tissue and neuropathic pain.

BPC-157 (Body Protection Compound-157): This stable gastric peptide supports systemic and local tissue healing. In animal models of transected sciatic nerve, BPC-157 improved axonal regeneration, increased the density and size of regenerative fibers, enhanced myelination, and restored motor function as measured by electromyography and walking scores. It also reduced inflammation and promoted new blood vessel growth around injured tissue. Clinically, it is often considered when chemical irritation of the nerve root contributes to leg pain.

ARA-290 (also called cibinetide): This peptide is derived from erythropoietin and activates the innate repair receptor. It reduces neuropathic pain and supports nerve fiber recovery without raising red blood cell counts. Studies show it inhibits the NLRP3 inflammasome in Schwann cells after sciatic nerve injury, lowers neuroinflammation, and improves functional recovery in crush models. Human trials in small-fiber neuropathy demonstrated reduced pain scores and measurable increases in corneal and skin nerve fiber density.

Structural extracellular matrix sequences: IKVAV and YIGSR: These short peptides come from laminin, a major component of the extracellular matrix that guides nerve growth. IKVAV promotes neurite outgrowth and neural adhesion and reduces fibrous scar formation after injury. YIGSR supports Schwann cell attachment, proliferation, and axonal guidance. Both have been incorporated into experimental scaffolds and hydrogels that improve regeneration across gaps in the sciatic nerve in animal studies.

These peptides do not replace structural correction. They support the body’s own repair processes once mechanical pressure is reduced.

How Integrative Chiropractic Care Provides Mechanical Relief

Chiropractic care focuses on the physical causes of nerve compression. Gentle spinal adjustments restore proper joint motion in the lumbar spine and pelvis. Flexion-distraction and spinal decompression techniques create space around the nerve roots and improve disc hydration. Soft-tissue work releases tight muscles, such as the piriformis, that can compress the sciatic nerve. Therapeutic exercises then strengthen supporting muscles so the relief lasts.

Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, has observed that restoring spinal alignment and nerve glide reduces ongoing irritation. This creates a more favorable environment for tissue healing. His clinical work at Injury Medical Clinic PA emphasizes non-surgical recovery for personal injury, chronic low-back pain, and sciatica through precise biomechanical correction combined with regenerative support.

The Power of Combining Peptides with Chiropractic Care

Mechanical relief and cellular regeneration work best together. Chiropractic adjustments remove or lessen the physical pressure that keeps the nerve inflamed and poorly nourished. Peptides then help the nerve axons regrow, calm residual inflammation, improve local blood flow, and support the extracellular matrix that guides new fibers. The result is often faster functional improvement and reduced risk of lingering symptoms.

At Injury Medical Clinic PA in El Paso, Texas, this combination is delivered in a multidisciplinary setting. Dr. Alex Jimenez provides chiropractic care focused on alignment, decompression, and rehabilitation. Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933), serves as Medical Director and Collaborative Physician. With more than 40 years of experience as an internist, she oversees medical aspects of care, ensuring protocols remain safe and compliant. The team also integrates functional medicine testing, personal injury documentation, and structured rehabilitation. This model is common in integrative injury clinics: the chiropractor addresses the neuromusculoskeletal system while the medical director provides overall clinical direction.

Patients typically begin with a thorough evaluation that includes history, examination, and imaging when needed. Care plans may then layer spinal adjustments and decompression with carefully supervised peptide protocols. Functional medicine addresses contributing factors such as inflammation, nutrient status, and metabolic health. The goal is lasting nerve recovery rather than temporary symptom control.

What a Clear Recovery Journey Looks Like

  • Assessment identifies the exact sources of compression and inflammation.
  • Chiropractic care restores motion and reduces mechanical stress.
  • Peptide support (when appropriate under medical oversight) aids axonal repair and pain modulation.
  • Rehabilitation rebuilds strength and movement patterns.
  • Ongoing monitoring adjusts the plan as function returns.

Dr. Jimenez’s clinical observations highlight that patients often notice reduced leg pain and improved walking once the mechanical component is corrected and cellular support is added. The approach stays conservative and patient-centered.

Moving Forward with Informed Care

Sciatica does not have to mean long-term limitation. Specific peptides such as BPC-157, ARA-290, and matrix sequences like IKVAV and YIGSR offer targeted support for nerve repair and pain control in research settings. When these are combined with skilled integrative chiropractic care that relieves nerve compression, patients gain both mechanical freedom and cellular recovery tools. In El Paso, the collaborative model at Injury Medical Clinic PA—led by Dr. Alex Jimenez with medical direction from Dr. Maria Guadalupe Cardenas—illustrates how this dual approach can be delivered safely within a multidisciplinary practice focused on functional outcomes.

Always work with qualified licensed providers who can evaluate your individual situation, order appropriate testing, and supervise any regenerative therapies. Personalized care that pairs structural correction with cellular support offers a practical path toward lasting relief.

Sciatica Secrets Revealed! | El Paso, Tx (2023)

References

Gjurasin, M., et al. (2010). Peptide therapy with pentadecapeptide BPC 157 in traumatic nerve injury. Regulatory Peptides.

Core Medical Wellness. (n.d.). Peptide therapy for pain management.

Jimenez, A. (n.d.). Integrative peptide therapy with chiropractic care explained.

Swartjes, M., et al. (2014). ARA 290, a peptide derived from the tertiary structure of erythropoietin, produces long-term relief of neuropathic pain. Molecular Pain.

Bamapain. (n.d.). Sciatica and peptide approaches.

Neu Life Chiropractic. (n.d.). Treating back pain and sciatica with spinal adjustments.

Frisco Rehab. (n.d.). Can BPC-157 heal a herniated disc?.

Nava Center. (n.d.). Recovery and healing peptides.

Ina Chicago. (n.d.). Nerve pain peptides.

Jimenez, A. (n.d.). Clinical observations and practice information. DrAlexJimenez.com and LinkedIn profile.

Chiropractic and Regenerative Medicine for Injury Recovery

Chiropractic and Regenerative Medicine for Injury Recovery

How Integrative Chiropractic Care and Regenerative Medicine Work Together for Stronger Recovery

Many people struggle with ongoing joint pain, soft tissue injuries, or back problems that do not fully resolve with rest alone. Integrative chiropractic care and regenerative medicine collaborate by fusing mechanical alignment with cellular tissue restoration. Chiropractic care restores normal joint motion and releases strained structures. At the same time, platelet-rich plasma (PRP), platelet-fibrin products (PFP), microfragmented adipose tissue (MFAT), and epidural injections target inflammation and rebuild weak soft tissues. This partnership creates a more complete path to healing.

The combination is useful for sports injuries, personal injury cases from auto accidents, and long-term wear on joints and soft tissues. It supports the body’s natural ability to repair rather than simply covering symptoms.

Chiropractic and Regenerative Medicine for Injury Recovery

Regenerative Treatments That Rebuild Tissue

Regenerative medicine uses materials from a person’s own body to encourage repair at the cellular level. These options deliver concentrated growth factors or signaling cells directly where damage exists. The goal is to calm inflammation and support the formation of stronger tissue.

Platelet-rich plasma (PRP) starts with a blood draw. The sample is spun to concentrate platelets. These platelets release growth factors that help form new blood vessels, support collagen production, and move the area from chronic inflammation toward active healing. Athletes and active adults often turn to PRP for tendon problems, ligament sprains, muscle strains, and mild joint wear because it can improve tissue quality without surgery (Nortex Spine and Joint, n.d.; OrthoRepair, n.d.).

Platelet-fibrin products (PFP) build on similar principles. They form a natural fibrin scaffold that holds growth factors longer. This slower release can help tissues that heal slowly, such as certain ligaments or spinal structures.

Microfragmented adipose tissue (MFAT) comes from a small sample of the patient’s own fat. The fat is processed into tiny fragments that keep regenerative cells and their supporting environment intact. MFAT provides both cushioning and biological signals. It is often chosen for more advanced joint issues, partial tears, or areas that need structural support along with repair (Form Health PDX, 2025).

Epidural injections place anti-inflammatory or regenerative material into the space around spinal nerves. These can reduce irritation from disc problems or stenosis. Regenerative versions may include platelet products to support longer calming of nerves and better participation in rehabilitation (El Paso Chiropractor Blog, 2026).

These treatments focus on the biological side. They help rebuild weak soft tissues and lower the inflammation that keeps pain going.

How Chiropractic Care Restores Motion and Reduces Strain

Chiropractic care handles the mechanical side of the problem. Joints that do not move well create extra stress on nearby muscles, ligaments, and discs. Over time, this stress can slow healing or lead to new issues.

Precise adjustments restore normal joint motion. Soft-tissue work reduces muscle tension. Spinal decompression and posture training help unload compressed or strained structures. Movement retraining and simple exercises teach the body better patterns so the same injury is less likely to return.

When joints move freely again, the regenerative treatments have a better environment in which to work. Healthy alignment means less repeated strain on the tissues that are trying to heal (NewRegen Ortho, 2021).

Why the Two Approaches Support Each Other

Think of the body as needing both strong building materials and a stable frame. Regenerative injections supply the materials for cellular repair. Chiropractic care straightens the frame and reduces load on damaged areas.

Supporting literature and clinical experience show that biologics alone are rarely enough. Structured rehabilitation and mechanical correction improve long-term results. When tissues receive growth factors while the joints above and below them move correctly, recovery tends to be more complete and lasting (Nortex Spine and Joint, n.d.; The Osteo Center, n.d.).

This layered approach is especially beneficial after personal injury. Auto accidents often create both soft-tissue damage and joint dysfunction. Treating only one side leaves the other problem unaddressed. Combining the two helps patients regain strength, reduce medication needs, and return to daily activities with more confidence (Health Coach Clinic, n.d.).

A Multidisciplinary Team in El Paso

At Injury Medical Clinic PA in El Paso, Texas, this integrated model is put into practice every day. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, provides chiropractic care, functional medicine insights, rehabilitation guidance, and personal injury documentation. His clinical observations, shared through his practice sites, emphasize that mechanical alignment prepares the body for biological repair and that both must be addressed for lasting results (Jimenez, n.d.).

Working alongside him is Dr. Maria Guadalupe Cardenas, MD. She is board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933) and brings more than 40 years of experience as an internist. Dr. Cardenas serves as medical director and collaborative physician. She provides medical oversight, reviews complex health histories, and helps ensure safety protocols are followed. This partnership is common in integrative injury clinics: the chiropractor handles musculoskeletal and functional care while the medical director supplies internal-medicine expertise and collaborative guidance.

The clinic also weaves in functional medicine. This looks at nutrition, sleep, inflammation, gut health, hormones, and metabolic factors that influence how well tissues heal. Rehabilitation services, personal injury care coordination, and related therapies round out the plan. Patients receive detailed evaluations and personalized steps that move from reducing inflammation to rebuilding tissue to restoring full function.

Practical Benefits Patients Notice

People who use this combined approach often report several advantages:

  • Faster progress in reducing pain and swelling
  • Improved joint motion that feels more stable
  • Better ability to take part in physical therapy
  • Lower chance of the same injury returning
  • Clearer documentation for injury claims when needed

Athletes appreciate the support for return-to-activity timelines when regenerative treatments are paired with proper loading and alignment work. People with chronic joint or spine problems value the chance to avoid repeated steroid injections or surgery when appropriate (OrthoRepair, n.d.; Form Health PDX, 2025).

What to Expect on the Care Journey

Care usually begins with a thorough exam, imaging when needed, and a clear discussion of goals. Regenerative injections are performed with guidance such as ultrasound for accuracy. Chiropractic sessions focus on restoring motion and reducing mechanical stress. Functional medicine recommendations may include nutrition and lifestyle steps that support healing from the inside. Rehabilitation progresses from gentle movement to strength and activity-specific tasks.

Results build over weeks rather than overnight. Early progress often shows as less pain and better daily function. Longer-term gains include stronger tissue and more reliable joint performance.

Moving Forward with a Complete Plan

Integrative chiropractic care and regenerative medicine form a practical partnership. One side restores normal joint motion and releases strained structures. The other targets inflammation and rebuilds weak soft tissues at the cellular level. When guided by an experienced multidisciplinary team—like the collaboration between Dr. Alexander Jimenez and Dr. Maria Guadalupe Cardenas at Injury Medical Clinic PA—patients receive coordinated support that addresses both biomechanics and biology.

This approach offers a clear path for those seeking lasting recovery. It respects the body’s ability to heal while giving it the right conditions to do so. Anyone dealing with soft-tissue injuries, joint problems, or personal-injury recovery can explore whether this combined model fits their needs through a careful evaluation with a qualified team.

From Injury to Recovery with Chiropractic Care | El Paso, Tx (2023)

References

El Paso Chiropractor Blog. (2026, June). Integrative chiropractic and regenerative medicine in El Paso: A modern path for spine, joint, and injury recovery. https://www.elpasochiropractorblog.com/2026/06/integrative-chiropractic-and.html

Form Health PDX. (2025). Understanding regenerative injection therapy. https://formhealthpdx.com/understanding-regenerative-injection-therapy/

Health Coach Clinic. (n.d.). Regenerative options for personal injury recovery. https://healthcoach.clinic/regenerative-options-for-personal-injury-recovery/

Jimenez, A. (n.d.). Clinical observations and regenerative approaches. https://dralexjimenez.com/

NewRegen Ortho. (2021). Chiropractors: How to integrate regenerative medicine into your practice the right way. https://newregenortho.com/chiropractors-how-to-integrate-regenerative-medicine-into-your-practice-the-right-way/

Nortex Spine and Joint. (n.d.). Why athletes use regenerative medicine. https://www.nortexspineandjoint.com/blog/why-athletes-use-regenerative-medicine/

OrthoRepair. (n.d.). PRP therapy for athletes: How professional sports medicine uses regenerative treatments. https://orthorepair.com/blog/prp-therapy-for-athletes-how-professional-sports-medicine-uses-regenerative-treatments/

The Osteo Center. (n.d.). Accelerating athletic recovery: The role of regenerative and integrative medicine. https://theosteocenter.com/accelerating-athletic-recovery-the-role-of-regenerative-and-integrative-medicine/

Trigger Point Injections: A Solution for Myofascial Pain

Explore trigger point injections as a treatment for myofascial pain. Learn how they can provide effective relief.

Abstract

In this educational post, I will take you on a journey into the world of integrative musculoskeletal care, focusing on a powerful and effective technique for managing chronic pain: trigger point injections. We will explore the physiological underpinnings of muscle spasms, adhesions, and the resulting pain patterns that affect so many individuals. I will share insights from my clinical practice at Injury Medical Clinic PA in El Paso, Texas, where we blend cutting-edge techniques with a deep understanding of human anatomy and physiology. This post will detail the “how” and “why” behind trigger point injections, comparing different approaches like dry needling versus injections with therapeutic agents such as lidocaine and Sarapin. We will discuss the science behind these treatments, including the mechanisms of action, appropriate dosages, needle depths, and patient safety considerations.

Furthermore, I will explain our unique multidisciplinary model, where my expertise in chiropractic and functional medicine is complemented by the medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, an esteemed internist. Together, we provide a comprehensive treatment paradigm that addresses the root cause of pain, from structural misalignments corrected by chiropractic adjustments to the muscular dysfunction treated with targeted injections. Join me as we unravel the complexities of chronic muscle pain and discover how this integrated approach can offer profound and lasting relief.

A Collaborative Vision for Comprehensive Patient Care

Before we delve into the specifics of trigger point therapy, I believe it’s essential to provide context on our practice’s philosophy. At Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, our mission has always been to offer patients a truly holistic and integrated path to wellness. My journey as a Doctor of Chiropractic (DC) and a board-certified Family Nurse Practitioner (APRN, FNP-BC) has been driven by the understanding that the human body is an interconnected system. A problem in one area, such as the musculoskeletal system, can have far-reaching effects on overall health.

This understanding is the foundation of our multidisciplinary setup. I am honored to work alongside Dr. Maria Guadalupe Cardenas, MD, a highly respected physician board-certified in Internal Medicine with over four decades of clinical experience. Dr. Cardenas serves as our Medical Director and Collaborative Physician, providing invaluable medical oversight and a depth of knowledge that enriches our patient care protocols. Her NPI is #1164426749, and she is licensed in Texas under #J2933. This collaborative structure is common and highly effective in modern integrative and injury care settings. It allows us to seamlessly merge the principles of chiropractic care—focusing on spinal alignment and nervous system function—with the diagnostic and prescriptive authority of conventional medicine.

Our team integrates:

  • Chiropractic Care (Dr. Jimenez): Focused on spinal adjustments, biomechanical correction, and restoring proper nervous system communication.
  • Medical Oversight (Dr. Cardenas): Ensuring all procedures meet the highest medical standards, managing complex patient cases, and providing a conventional medical perspective.
  • Functional Medicine: Investigating the root causes of disease by looking at lifestyle, genetics, and environmental factors.
  • Personal Injury Care & Rehabilitation: Providing comprehensive programs for recovery from accidents and injuries.
  • Advanced Therapies: Including the trigger point injections we will discuss in detail today.

This synergistic approach ensures that our patients receive a well-rounded and personalized treatment plan that addresses their health from every angle.

Understanding Muscle Spasms and Trigger Points

To appreciate the effectiveness of trigger point injections, we first need to understand the problem they are designed to solve. When a muscle is injured, overused, or subjected to chronic stress—be it physical or emotional—it can enter a state of sustained contraction known as a muscle spasm. This is a protective mechanism, but when it becomes chronic, it creates a vicious cycle of pain and dysfunction.

Inside that chronically contracted muscle, several things happen at a microscopic level:

  1. Reduced Blood Flow (Ischemia): The tightened muscle fibers constrict the tiny blood vessels (capillaries) that run through them. This starves the muscle tissue of oxygen and essential nutrients.
  2. Metabolic Waste Buildup: Without adequate blood flow to flush them out, metabolic byproducts like lactic acid accumulate in the tissue. This creates a toxic, acidic environment that further irritates the muscle and its nerve endings.
  3. The Energy Crisis: A muscle requires energy (ATP) not only to contract but also to relax. The persistent contraction depletes energy reserves, and the lack of oxygen prevents the muscle from producing more. The muscle becomes “stuck” in a contracted state because it lacks the energy to release.
  4. Formation of Scar Tissue (Adhesions): The body’s response to this chronic injury and inflammation is to lay down fibrous scar tissue, or adhesions, within the muscle. These adhesions are like internal glue, sticking muscle fibers together that should be gliding freely. This creates a palpable, ropey band of tissue with a highly sensitive nodule at its center—what we call a trigger point.

This trigger point is not just a local problem. It can refer pain to other parts of the body in predictable patterns. For example, a trigger point in the upper trapezius muscle in your shoulder can cause a tension-type headache that wraps around your ear to your temple. This is why a patient might complain of pain in one area, while the actual source of the problem is located elsewhere.

The Evolution of Treatment: From Dry Needling to Advanced Injections

In my years of practice, I’ve seen treatment modalities evolve significantly. Initially, a common and effective technique was dry needling. This involves inserting a thin, solid filiform needle (the same kind used in acupuncture) directly into the trigger point without injecting any substance.

The Mechanics of Dry Needling

The therapeutic effect of dry needling comes from several physiological responses:

  • Mechanical Disruption: The simple act of inserting and manipulating the needle breaks up the microscopic scar tissue and adhesions within the muscle. Imagine untangling a knotted rope by physically poking and separating the fibers.
  • Local Twitch Response: When the needle accurately hits the center of a trigger point, it often elicits an involuntary “twitch” or contraction of the muscle band. This response is a spinal cord reflex that is believed to reset the chemistry in the area, helping to break the pain-spasm cycle.
  • Neurophysiological Effects: The needle stimulates nerve receptors in the muscle (A-delta fibers), which send signals up the spinal cord to the brain. This can activate the body’s own pain-relieving mechanisms, such as the release of endorphins and enkephalins, and modulate how the brain perceives pain signals from the trigger point.

Many practitioners, including acupuncturists and physical therapists, still use dry needling with great success. It’s a valuable tool, especially for patients who may have allergies to injectable substances. However, we’ve found that we can achieve a more profound and faster result by introducing therapeutic agents directly into the dysfunctional tissue.

Enhancing Efficacy with Trigger Point Injections

This brings us to our current methodology: trigger point injections. Instead of just mechanically disrupting the tissue, we are now also delivering medication directly to the site of the problem. This allows us to address the biochemical and inflammatory components of the trigger point more directly.

In my practice, I have found a particularly effective combination: Lidocaine and Sarapin.

  • Lidocaine: This is a well-known local anesthetic. When injected into the trigger point, it blocks the sodium channels in the nerve endings. Nerves rely on the flow of sodium ions to transmit pain signals. By blocking these channels, lidocaine effectively “numbs” the area, providing immediate and significant pain relief. This breaks the immediate pain-spasm-pain cycle. It allows the patient to experience relief, which in turn helps the central nervous system to “calm down” and stop perpetuating the chronic pain signals.
  • Sarapin (Ceraferm): This is where our approach diverges from many conventional pain management practices that might use corticosteroids. Sarapin is a biological medicine, a sterile aqueous solution derived from the pitcher plant (Sarracenia purpurea). It acts as a powerful, all-natural anti-inflammatory. Its mechanism is fascinating; it is believed to work by selectively inhibiting nerve conduction in C-type sensory nerve fibers, the small, unmyelinated fibers responsible for transmitting dull, aching, chronic pain signals. It does not affect motor nerves, so it doesn’t cause muscle weakness, nor does it affect the larger nerves responsible for sensation and touch.

I prefer Sarapin over corticosteroids for trigger point injections for several critical reasons. While steroids are potent anti-inflammatories, they can have significant side effects, especially with repeated use. These can include tissue atrophy (thinning of the muscle and skin), weakening of tendons, and systemic effects like elevated blood sugar and suppression of the adrenal system. Sarapin, being a biological agent, works with the body’s physiology and does not carry these risks. It provides potent anti-inflammatory effects right where they are needed without the collateral damage associated with steroids.

The Art and Science of the Injection Technique

Performing trigger point injections is as much an art as it is a science. It requires a deep, three-dimensional understanding of anatomy, a well-honed sense of palpation to locate these elusive nodules, and a precise technique to deliver the medicine effectively and safely.

The “Star Pattern” Technique

One of the techniques we employ is often referred to as a “star pattern” or fanning technique. This is an evolution of the pistoning method used in dry needling. Here is how it works:

  1. Initial Insertion: After identifying the trigger point through careful palpation, the needle is inserted through the skin and into the heart of the taut muscle band.
  2. Fanning Out: Instead of just moving the needle in and out in one spot, we withdraw it to just beneath the skin without fully removing it. Then, we redirect it at a slightly different angle and advance it again into the trigger point complex. We repeat this process multiple times, moving in a radial or “star” pattern around the central point.
  3. Injecting the Solution: As we perform this fanning motion, we are slowly and simultaneously injecting our one-to-one mixture of lidocaine and Sarapin.

The purpose of this technique is multifaceted:

  • Maximizing Mechanical Breakup: The multi-directional movement of the needle is far more effective at mechanically breaking up the fibrous adhesions and scar tissue than a single in-and-out motion.
  • Wider Distribution of Medication: This technique ensures that the therapeutic solution is distributed throughout a larger volume of the dysfunctional tissue, not just in a single pocket. This allows the anesthetic and anti-inflammatory to reach more of the affected muscle fibers and nerve endings.
  • Eliciting Multiple Twitch Responses: By probing different areas within the trigger point complex, we are more likely to elicit the therapeutic local twitch responses that help to reset the muscle’s neurological feedback loop.

Patient Comfort and Strategy

From a clinical perspective, managing the patient’s experience is paramount to a successful treatment. These injections can be uncomfortable, especially when the needle hits an active trigger point. The sensation is often described as a deep ache or a brief, sharp “zing” that may replicate their familiar pain pattern.

I’ve learned over many years that the order in which I address the trigger points matters. I always save the most sensitive, most active trigger point for last. If I were to start with the most painful one, the patient’s apprehension and pain response would be heightened for the remainder of the procedure. They might tense up, making it harder to work on the remaining areas, or even want to stop the treatment altogether. By starting with the less sensitive points, we build trust and allow the patient to acclimate to the sensation. By the time we get to the “worst one,” they are more relaxed and understand what to expect. It’s a small psychological detail, but it makes a world of difference in patient compliance and overall experience.

Dosage and Needle Selection: Tailoring to Anatomy

The human body is not uniform. The muscles and overlying tissues vary greatly in thickness from one region to another, and from one person to another. Therefore, our equipment and dosage must be tailored accordingly.

  • Cervical (Neck) and Upper Thoracic (Upper Back) Regions: In these areas, the muscles are generally more superficial, and they lie closer to sensitive structures. For these regions, I typically use:
    • Dosage: Approximately 1 mL of the solution per injection site. The smaller muscle bellies in this area cannot accommodate a larger volume without causing excessive pressure and discomfort.
    • Needle: A 30-gauge, 1-inch needle. The 30-gauge is very fine, which minimizes patient discomfort upon insertion. The 1-inch length is sufficient to reach the target muscles (like the trapezius, levator scapulae, or rhomboids) without risking injury to deeper structures.
  • Lower Thoracic and Lumbar (Mid to Lower Back) Regions: The muscles here, such as the quadratus lumborum and the large erector spinae group, are much thicker and more robust.
    • Dosage: These larger muscles can safely and effectively accommodate up to 2 mL of solution per site.
    • Needle: We often use a slightly larger needle, perhaps a 25-gauge, 1.5-inch needle. The 1.5-inch length is necessary to penetrate the thick fascia and muscle belly to reach the deep trigger points common in this area.

Critical Safety Concern: Pneumothorax

A crucial safety consideration, particularly when working in the thoracic region, is the risk of pneumothorax (a punctured lung). This is a question I am often asked by clinicians learning this technique. The lung lies deep to the rib cage and the intercostal muscles.

My clinical rule of thumb is this:

  • A 1-inch needle, when used properly over the thoracic musculature (e.g., the rhomboids or mid-trapezius), does not pose a significant risk of pneumothorax, even in a very thin, elderly individual. The needle must pass through the skin, subcutaneous fat, fascia, and the target muscle itself. In most individuals, this combined thickness is greater than one inch.
  • When you start using a 5-inch needle, especially in smaller or frail individuals, you must be much more mindful of your anatomy and needle depth. This length is generally reserved for the thick lumbar muscles or for larger individuals where you are confident in the tissue depth.

This is why a profound knowledge of anatomy isn’t just academic—it’s a matter of patient safety. I constantly urge students and colleagues: “Go back and review your anatomy.” It’s a subject many of us struggled with in school, but in a hands-on practice like this, it is the bedrock of safe and effective care. You must be able to mentally visualize the layers of tissue your needle is passing through.

The Role of Chiropractic Care in a Comprehensive Treatment Plan

Now, you might be wondering, “How does this all fit in with chiropractic care?” This is the core of our integrative model. Trigger point injections are a powerful tool for addressing the muscular component of a patient’s pain. Still, they do not, in isolation, correct the underlying structural and biomechanical issues that often cause those muscles to become dysfunctional in the first place.

Imagine a car with a misaligned frame. The tires will wear out unevenly. You can keep replacing the tires (treating the symptom), but until you fix the frame’s alignment (treating the cause), the tires will continue to wear out prematurely.

In the human body:

  • The Misaligned Frame: This is equivalent to vertebral subluxations or spinal misalignments. A vertebra that is out of its proper position can irritate the spinal nerves exiting at that level. This nerve irritation can cause the muscles innervated by that nerve to become hypertonic, spastic, and prone to developing trigger points.
  • The Unevenly Worn Tires: These are the painful, spastic muscles with trigger points.

Our integrated treatment protocol works on both aspects simultaneously:

  1. Chiropractic Adjustments: I use specific, gentle adjustments to correct the vertebral subluxations. This restores proper motion to the spinal joints and, most importantly, removes the interference to the nervous system. This addresses the root cause of why the muscles are being sent signals to chronically tighten.
  2. Trigger Point Injections: We use the injections to directly address the downstream consequences—the painful, knotted muscles. The injections provide rapid pain relief, reduce inflammation, and break up the fibrous adhesions that the adjustment alone cannot resolve.

This dual approach creates a positive feedback loop. The trigger point injections make the patient more comfortable and relax the muscles, which in turn makes the chiropractic adjustment more effective and easier to perform. The adjustment, by correcting the underlying neurological issue, helps prevent the trigger points from reforming. This combination is far more powerful than either therapy used in isolation and is fundamental to achieving long-term, sustainable results for our patients.

The Root Causes of Pain- Video

The Root Causes of Pain | El Paso, Tx (2023)

Addressing Common Questions and Considerations

In my educational presentations, several questions frequently arise. Let’s address some of the most common ones here.

“What about patients allergic to ‘caines’?”

Allergies to lidocaine, Marcaine, or other local anesthetics in the “-caine” family are rare but do exist. It’s estimated that true IgE-mediated allergies occur in less than 1% of the population. However, it is a critical part of our patient screening process. For a patient with a confirmed allergy, we have two excellent options:

  1. Dry Needling: We can revert to the classic dry needling technique. By using the star pattern with just the needle, we can still achieve the mechanical breakup of adhesions and elicit the therapeutic local twitch response. The results may be less immediate without the anesthetic, but the treatment is still highly effective at breaking the pain-spasm cycle over a series of sessions.
  2. Sarapin-Only Injections: Since Sarapin works on sensory nerves without being a “-caine” anesthetic, it can often be used alone. The patient won’t get the immediate numbing effect, but they will still benefit from the powerful anti-inflammatory action and the mechanical effects of the needling.

“What is the difference between this and Prolotherapy or PRP?”

This is an excellent question that touches on the broader field of regenerative medicine.

  • Trigger Point Injections (as described): The goal is primarily neuromodulation and inflammation reduction. We are aiming to “reboot” a dysfunctional muscle and nerve pattern and calm local inflammation.
  • Prolotherapy: This is short for “proliferative therapy.” The goal is to stimulate tissue repair, specifically in lax or injured ligaments and tendons. It involves injecting a mild irritant solution (often containing dextrose, a form of sugar) into the attachment points of these structures. This creates a mild, controlled inflammatory response, which in turn signals the body to send growth factors and repair cells to the area, strengthening and tightening the weakened connective tissue. Sometimes ozone is added to enhance this effect.
  • Platelet-Rich Plasma (PRP): This is a more advanced form of regenerative therapy. We draw the patient’s own blood, spin it in a centrifuge to separate the components, and extract a concentrated solution of platelets. This platelet-rich plasma is then injected into the injured area. Platelets are the body’s first responders to injury; they are packed with a multitude of powerful growth factors that orchestrate the entire healing cascade. PRP is used to heal torn tendons, damaged ligaments, arthritic joints, and even severe muscle tears.

While you could inject PRP into trigger points, in my clinical opinion, it would be overkill for most cases. The primary issue in a trigger point is neurological and inflammatory, not a significant tissue tear requiring massive regeneration. Using the right tool for the right job is key. Trigger point injections with lidocaine and Sarapin are the precise tool for muscular trigger points, while Prolotherapy and PRP are the tools for ligamentous laxity and significant tissue damage.

Conclusion: A Patient-Centered Path Forward

The journey from chronic pain to lasting wellness is often complex, requiring more than a single-minded approach. At our clinic, under the collaborative guidance of Dr. Maria Guadalupe Cardenas and me, we have built a model that honors the intricate, interconnected nature of the human body. By integrating the structural precision of chiropractic care with the targeted, science-based application of trigger point injections, we can address both the root cause and the painful symptoms of musculoskeletal dysfunction.

Understanding the “why” behind your pain—the cycle of muscle spasm, ischemia, and scar tissue formation—is the first step toward taking control of your health. Therapies like the ones described here are not just about masking pain; they are about resetting physiology, restoring function, and empowering the body to heal itself. With a deep respect for anatomy, a commitment to patient safety, and a collaborative spirit, we can unlock new levels of health and vitality for our patients.

As I reflect on my clinical observations, which I regularly share on platforms like my Sciatica Clinic website and LinkedIn profile, the recurring theme is the power of this integrated approach. The synthesis of chiropractic, functional medicine, and targeted medical procedures provides a comprehensive framework for tackling even the most stubborn chronic pain conditions. It is a privilege to guide patients on this journey, offering them hope and tangible results grounded in modern, evidence-based care.

References

  • Dommerholt, J., & Fernández-de-las-Peñas, C. (Eds.). (2018). Trigger point dry needling: An evidence- and clinical-based approach (2nd ed.). Elsevier.
  • Manchikanti, L., Singh, V., Falco, F. J., Cash, K. A., & Fellows, B. (2010). Cervical erector spinae plane block: a novel analgesic technique for management of acute and chronic pain. Pain Physician, 13(5), E315-E321. [Note: This reference provides context on injection techniques in the spinal region, though not specific to Sarapin.]
  • Shah, J. P., Thaker, N., Heimur, J., Aredo, J. V., Sikdar, S., & Gerber, L. (2015). Myofascial trigger points then and now: A historical and scientific perspective. PM & R: The Journal of Injury, Function, and Rehabilitation, 7(7), 746–761. https://doi.org/10.1016/j.pmrj.2015.01.024
  • Simons, D. G., Travell, J. G., & Simons, L. S. (1999). Travell &Simons’’ myofascial pain and dysfunction: The trigger point manual (Vol. 1, 2nd ed.). Williams & Wilkins.
  • Wancura-Kampik, I. (2018). Sarapin in Pain Therapy. In Pain Therapy (pp. 531-536). Springer, Cham. https://doi.org/10.1007/978-3-319-58359-1_53

SEO Tags: Trigger Point Injections, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, Integrative Chiropractic Care, El Paso Chiropractor, Functional Medicine, Chronic Pain Management, Muscle Spasm Treatment, Dry Needling, Lidocaine Injection, Sarapin, Natural Anti-inflammatory, Pneumothorax Risk, Star Pattern Injection, Musculoskeletal Health, Chiropractic Adjustment, Personal Injury Clinic, Back Pain Relief, Neck Pain Relief, Myofascial Pain Syndrome


Regenerative Therapies for Personal Injury Recovery Strategies

Regenerative Therapies for Personal Injury Recovery Strategies

Regenerative Therapies for Personal Injury Recovery in El Paso

A personal injury can damage more than one part of the body. A car accident may cause whiplash, a shoulder tendon injury, lower back pain, and an irritated spinal nerve. A workplace accident may strain a ligament while also changing how a person walks, lifts, or moves.

For this reason, personal injury recovery may require more than one type of care. Platelet-rich plasma (PRP), platelet-fibrin products (PFP), micro-fragmented adipose tissue (MFAT), and epidural spinal injections may each serve a different purpose.

Some treatments support tissue repair. Others mainly reduce inflammation so the patient can move, sleep, and participate in rehabilitation. These procedures may be combined with chiropractic care, functional medicine, corrective exercise, and medical oversight.

Regenerative Therapies for Personal Injury Recovery Strategies

Why Tissue-Level Recovery Matters

Pain is an important warning signal, but it does not always explain the full extent of the injury. Pain after an accident may come from:

  • A torn or strained muscle
  • A sprained ligament
  • A damaged tendon
  • An irritated joint
  • A herniated spinal disc
  • An inflamed or compressed nerve root
  • Scar tissue from an older injury

These problems can reduce range of motion, strength, balance, coordination, sleep, and the ability to work.

A tissue-focused personal injury treatment plan aims to do more than cover pain. Its goals may include:

  • Reducing harmful inflammation
  • Supporting natural repair signals
  • Restoring joint and spinal movement
  • Improving strength and stability
  • Helping the patient return to normal activities
  • Tracking changes through examinations and imaging

Accurate medical records may also show the diagnosis, treatment plan, response to care, and changes in function over time. This information may help explain the clinical recovery process in an injury claim.

However, treatment must always be based on medical need. A procedure should not be performed only to support a legal case. Medical documentation also does not guarantee a legal outcome or prove that one treatment caused a specific result.

PRP Uses Concentrated Platelets to Support Healing

Platelet-rich plasma is made from the patient’s own blood. A small blood sample is drawn and placed into a centrifuge. The centrifuge spins the blood to separate and concentrate the platelets.

The prepared PRP is then injected into the injured area. Ultrasound or fluoroscopic imaging may be used to guide the needle to the correct location.

Platelets are commonly known for helping the blood clot. They also contain proteins and growth factors involved in inflammation, cell communication, blood vessel activity, and tissue repair.

When concentrated platelets are placed near damaged tissue, they release signals that may encourage local cells to respond to the injury.

PRP may be considered for selected cases involving:

  • Tendon injuries
  • Muscle strains
  • Ligament sprains
  • Partial soft-tissue tears
  • Joint injuries
  • Mild or moderate degenerative changes
  • Injuries that have not improved with basic conservative care

Research suggests that PRP may support muscle and soft-tissue recovery in certain cases. However, results are not the same for every injury.

A review by Setayesh et al. (2018) found possible improvements in healing, swelling, and return to activity in some studies. The authors also noted that there were not enough high-quality randomized trials to prove a consistent benefit for every muscle injury. PRP products may also differ in platelet concentration, white blood cell content, dose, and preparation method.

In simple terms, PRP brings a higher concentration of the patient’s platelets to a carefully selected target. It cannot reconnect a complete tendon rupture or replace missing tissue. Its purpose is to improve the healing environment while rehabilitation restores movement and strength.

PFP Creates a Fibrin Scaffold

The term platelet-fibrin product, or PFP, is sometimes used by clinics to describe blood-derived products that contain platelets and a fibrin network.

In scientific studies, related preparations may be called:

  • Platelet-rich fibrin, or PRF
  • Injectable platelet-rich fibrin, or i-PRF
  • Platelet-rich fibrin matrix, or PRFM
  • Advanced platelet-rich fibrin

Fibrin is a natural protein involved in blood clot formation. In a platelet-fibrin product, fibrin forms a soft, three-dimensional network. This network may hold platelets, signaling proteins, and other blood components close to the treatment site.

The fibrin network works like a temporary scaffold. It may help keep biological signals in the injured area while the product slowly breaks down.

Laboratory research found that injectable platelet-rich fibrin released certain growth factors over a longer period than traditional liquid PRP. It also supported fibroblast movement and collagen-related activity. Fibroblasts are cells involved in building and repairing connective tissue (Miron et al., 2017).

PFP or PRF-type products may be considered when the clinician wants:

  • A treatment made from the patient’s own blood
  • A fibrin structure that remains near the target
  • Longer exposure to certain repair signals
  • Support for chronic tendon or ligament problems
  • A biological scaffold for damaged soft tissue

A simple way to understand the difference is that PRP provides a concentrated biological signal, while a platelet-fibrin product holds that signal within a temporary mesh.

This comparison is simplified. The actual effects depend on how the product is prepared, the tissue being treated, and the patient’s overall health. Clinical evidence also varies, and more research is needed to determine which platelet-fibrin methods work best for specific injuries.

MFAT Provides Structural and Cellular Support

Micro-fragmented adipose tissue uses a small amount of the patient’s own fat tissue. The fat is usually collected from the abdomen, thigh, or side through a small harvesting procedure.

The collected tissue is cleaned and mechanically processed into tiny fragments. It is then injected into the damaged joint or soft-tissue area, often with imaging guidance.

Fat tissue contains more than fat cells. It also contains:

  • Small blood vessels
  • Structural matrix
  • Stromal cells
  • Signaling cells
  • Proteins involved in tissue support

MFAT keeps parts of this natural tissue structure instead of turning the sample into a simple liquid. The processed tissue may provide cushioning, structural support, and local biological signals.

MFAT is often discussed for larger or more complex problems, including:

  • Knee or hip joint damage
  • Cartilage defects
  • Osteoarthritis
  • Larger partial tears
  • Chronic joint inflammation
  • Injuries that have not responded to simpler treatments

A clinical comparison from Sports Medicine of the Rockies explains that PRP is generally less invasive and may be considered for earlier or milder soft-tissue injuries. MFAT requires a small fat harvest and may be discussed for larger joints or more complex tissue problems (Sports Medicine of the Rockies, 2026).

Early research has reported improvements in pain and function among some patients receiving MFAT for knee osteoarthritis. However, research is still developing. Treatment methods are not fully standardized, and results cannot be promised.

Patients must also understand the regulatory limits. The U.S. Food and Drug Administration warns that many regenerative medicine products marketed for orthopedic problems have not been approved to treat conditions such as osteoarthritis, tendonitis, disc disease, back pain, or joint pain. The exact status depends on the product, processing method, intended use, and federal requirements.

A qualified medical team should clearly explain the evidence, regulatory status, possible benefits, costs, risks, and other treatment options before MFAT is considered.

Epidural Spinal Injections Calm Inflamed Nerves

An epidural spinal injection places medication into the epidural space near irritated spinal nerves.

These injections may be considered when a herniated disc, spinal narrowing, or severe inflammation affects a nerve root. Nerve-root irritation may cause pain that travels from the neck into the shoulder or arm. It may also cause pain that travels from the lower back into the hip or leg.

A traditional epidural steroid injection usually contains a corticosteroid and a local anesthetic. Its main purpose is to reduce inflammation around the nerve.

For accuracy, a steroid epidural injection is better described as a targeted anti-inflammatory treatment than as a regenerative treatment. It does not rebuild a torn disc or repair damaged ligaments.

By lowering nerve inflammation, an epidural injection may help a patient:

  • Sleep with less pain
  • Stand and walk more comfortably
  • Reduce severe arm or leg symptoms
  • Participate in physical rehabilitation
  • Use fewer strong pain medicines
  • Return to basic daily activities

Current evidence suggests that epidural steroid injections may provide limited, mainly short-term improvement in pain and disability for some people with cervical or lumbar radiculopathy. The injections do not consistently prevent surgery or repair the damaged spinal structure (Armon et al., 2025).

Some clinics also discuss epidural injections containing platelet preparations or other biological products. These uses should not be presented as proven replacements for standard epidural treatment. Evidence is limited, and some biological products used for spinal conditions may be investigational or unapproved.

Patients should receive a clear explanation of what will be injected, why it is being used, the available evidence, possible risks, regulatory concerns, and standard alternatives.

Choosing the Correct Treatment

No single injection is right for every personal injury. A torn tendon is different from an irritated nerve. A mild ligament sprain is different from a large cartilage defect.

Before recommending a treatment, the clinical team may consider:

  • The exact injured tissue
  • Whether the injury is new or chronic
  • The size and grade of a tear
  • MRI, ultrasound, or X-ray findings
  • Numbness, weakness, or nerve symptoms
  • Previous treatments and results
  • Current medications
  • Diabetes, heart disease, or other conditions
  • The patient’s work and activity needs

PRP may be considered for a stubborn tendon, muscle, or ligament injury. A platelet-fibrin product may be selected when a fibrin scaffold and slower release of signals are desired.

MFAT may be discussed for more advanced joint or cartilage damage. An epidural injection may be considered when nerve inflammation is stopping the patient from sleeping, walking, or participating in rehabilitation.

Surgery may still be necessary for a complete tendon rupture, major instability, severe fracture, progressive muscle weakness, spinal cord compression, or another serious condition.

Integrating Chiropractic Care and Medical Oversight

Injury Medical Clinic PA in El Paso, Texas, uses a multidisciplinary model that combines chiropractic care, medical evaluation, functional medicine, personal injury care, and rehabilitation.

Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, focuses on chiropractic care, musculoskeletal evaluation, functional medicine, and injury rehabilitation.

His published clinical observations emphasize that patients often need both mechanical care and tissue-focused support. An injection may improve the healing environment, but the patient may still need better joint movement, stronger stabilizing muscles, improved spinal mechanics, and a gradual return to normal activity.

Clinic materials explain that treatment may include:

  • Chiropractic adjustments or mobilization
  • Soft-tissue treatment
  • Spinal decompression when appropriate
  • Corrective exercise
  • Strength and balance training
  • Functional medicine support
  • Nutrition guidance
  • Diagnostic imaging
  • Medical or surgical referrals

This approach focuses on restoring function rather than only lowering a pain score. Dr. Jimenez’s professional materials list his chiropractic, advanced-practice nursing, functional medicine, and injury-care qualifications.

Medical Direction From Dr. Maria Cardenas

Clinic materials identify Dr. Maria Guadalupe Cardenas, MD, as a board-certified internal medicine physician who serves as medical director and collaborative physician at Injury Medical Clinic PA.

Those materials list:

  • NPI #1164426749
  • Texas medical license #J2933
  • More than 40 years of internal medicine experience
  • Board certification in internal medicine

Dr. Cardenas works with Dr. Jimenez as part of the clinic’s medically integrated model. Her role provides medical direction and helps the team review medications, laboratory findings, chronic health conditions, procedure risks, and medical concerns that may affect treatment.

Dr. Jimenez directs chiropractic and rehabilitation strategies within his professional scope. Dr. Cardenas provides internal medicine experience and medical oversight. Clinic materials describe this collaboration as part of the practice’s integrated care structure.

This type of multidisciplinary setup is used in many integrative and injury-focused clinics. It allows a medical physician, chiropractor, advanced-practice provider, and rehabilitation team to contribute different skills to one coordinated plan.

Documenting Meaningful Recovery

Personal injury documentation should show more than the number of office visits. Strong clinical records may include:

  • The injury history
  • Examination findings
  • Imaging results
  • Functional limitations
  • The reason for each treatment
  • Changes in pain and movement
  • Strength and range-of-motion measurements
  • Response to rehabilitation
  • Referrals and future recommendations

When regenerative or image-guided treatments are used, the records should explain why the procedure was medically reasonable and what tissue was being treated.

Follow-up examinations can show whether the patient is walking better, lifting more safely, sleeping longer, or returning to work. This creates a clearer picture of tissue-level and functional recovery.

The records may help an attorney, insurer, or other reviewer understand the injury and treatment process. However, good documentation must remain objective and medically accurate.

A Clear Path Toward Personal Injury Recovery

PRP, PFP, MFAT, and epidural spinal injections do not work in the same way.

PRP concentrates the patient’s platelets and growth factors. PFP creates a fibrin framework that may hold biological signals near the injury for a longer period. MFAT supplies a small amount of the patient’s own supportive fat tissue and natural cellular environment.

Traditional epidural steroid injections mainly reduce inflammation around an irritated spinal nerve. This may make it easier for the patient to walk, sleep, and participate in rehabilitation, but it does not directly rebuild damaged tissue.

The goal is not to select the newest procedure. The goal is to choose the safest and most reasonable treatment for the diagnosed injury.

For people with whiplash, a torn tendon, a herniated disc, or another personal injury, a coordinated team can determine whether the next step should include chiropractic care, rehabilitation, functional medicine, an image-guided injection, a specialist referral, or surgery.

Natural Healing: Chiropractic Care for Injury Recovery | El Paso, Tx (2023)

References

Armon, C., et al. (2025). Epidural steroids for cervical and lumbar radicular pain and spinal stenosis: A systematic review summary. Neurology.

El Paso Chiropractor Blog. (2026a). Integrative chiropractic and regenerative medicine in El Paso: A modern path for spine, joint, and injury recovery.

El Paso Chiropractor Blog. (2026b). Regenerative and integrative care for sciatica: PRP, PFP, mFAT, epidurals, and chiropractic support.

Health Coach Clinic. (2026). Regenerative medicine options for spinal health.

Jimenez, A. (2026a). Regenerative therapies for fitness and recovery insights.

Jimenez, A. (2026b). Clinical observations and integrative injury care resources.

Jimenez, A. (n.d.). Dr. Alexander Jimenez professional profile.

Malanga, G. A., et al. (2019). Microfragmented adipose injections in the treatment of knee osteoarthritis. International Orthopaedics, 43, 501–506.

Miron, R. J., Fujioka-Kobayashi, M., Hernandez, M., Kandalam, U., Zhang, Y., Ghanaati, S., & Choukroun, J. (2017). Injectable platelet-rich fibrin: Opportunities in regenerative dentistry. Clinical Oral Investigations, 21, 2619–2627.

Personal Injury Doctor Group. (2026). Regenerative therapies for fitness and recovery.

Sciatica Pain and Treatment Clinic. (2026). Regenerative and integrative therapies for pain relief.

Setayesh, K., Villarreal, A., Gottschalk, A., Tokish, J. M., & Choate, W. S. (2018). Treatment of muscle injuries with platelet-rich plasma: A review of the literature. Current Reviews in Musculoskeletal Medicine, 11(4), 635–642.

Sports Medicine of the Rockies. (2026). Comparing PRP, BMAC, and MFAT: Choosing the right regenerative treatment.

U.S. Food and Drug Administration. (2021). Important patient and consumer information about regenerative medicine therapies.

YouTube. (n.d.). Platelet-rich plasma treatment for injured tendons, muscles, ligaments, and joints.

Medical Disclaimer: This article is intended for educational purposes. It does not replace an examination, diagnosis, or treatment plan from a qualified healthcare professional. Results vary, and not every treatment is appropriate for every patient.

Restorative Injection Therapy Effectiveness for Muscle Pain

Explore restorative injection therapy musculoskeletal pain relief techniques that can aid in recovery and improve mobility.

Abstract

Welcome to our educational deep dive into the world of advanced regenerative medicine. I am Dr. Alex Jimenez, and I am thrilled to guide you through the intricate and fascinating landscape of cellular repair and tissue regeneration. In this comprehensive post, we will explore the physiological underpinnings of musculoskeletal injuries, focusing on conditions like Achilles tendonitis, and discuss cutting-edge treatment modalities that go beyond conventional approaches. We will dissect the science behind prolotherapy, examining how solutions like dextrose can trigger the body’s innate healing cascades. We’ll also delve into the synergistic potential of combining these therapies with other regenerative techniques, such as platelet-rich plasma (PRP) and stem cell therapies, to amplify healing outcomes.

A central theme of our discussion will be the importance of an integrative and multidisciplinary approach to patient care. Here at Injury Medical Clinic, we embody this philosophy through our collaborative partnership. I work alongside Dr. Maria Guadalupe Cardenas, a highly experienced board-certified internist who serves as our Medical Director. This partnership allows us to blend the best of chiropractic care, functional medicine, and conventional medical oversight to create personalized, evidence-based treatment plans. We will explore how this integrated model, which includes chiropractic adjustments, rehabilitation, nutritional guidance, and advanced regenerative injections, provides a holistic framework for treating complex injuries and promoting long-term wellness. Join me as we uncover the latest research from leading experts and translate it into practical, clinical applications that are transforming patient care.

Our Integrated Approach: A Fusion of Chiropractic, Medical, and Functional Medicine

At Injury Medical Clinic, our philosophy is built on a foundation of collaboration and integration. We believe that the most effective patient care arises from a multidisciplinary team that can view health and injury through multiple expert lenses. This is precisely the environment we have cultivated here in El Paso, Texas.

I am Dr. Alex Jimenez, and my background is extensive, spanning chiropractic (DC), advanced practice nursing (APRN, FNP-BC), and certified functional medicine (CFMP, IFMCP). This diverse training allows me to approach patient care from a holistic perspective, understanding not just the biomechanical aspects of an injury but also the systemic, cellular, and metabolic factors that influence healing and overall well-being.

Integrative Peptides for Hair Restoration and Health

However, the cornerstone of our practice is our collaborative relationship with Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a distinguished internist with over 40 years of experience and is board-certified in Internal Medicine. She serves as our Medical Director and Collaborative Physician, a structure that is becoming a gold standard in integrative and injury care clinics. Her NPI is #1164426749, and her Texas MD License is #J2933.

This partnership is not merely a formality; it is an active, dynamic collaboration that benefits every patient who walks through our doors. Here’s how it works:

  • Medical Oversight and Direction: Cardenas provides essential medical oversight for our practice. This is particularly crucial when we incorporate advanced procedures like regenerative injections (e.g., prolotherapy, PRP). Her expertise ensures that these treatments are administered safely, with proper diagnostic evaluation and consideration of the patient’s overall medical history. She reviews patient cases, consults on complex conditions, and ensures that our protocols adhere to the highest medical standards.
  • Comprehensive Diagnostics: While I may use functional and biomechanical assessments to diagnose a musculoskeletal issue, Dr. Cardenas’s internal medicine background allows us to integrate conventional medical diagnostics. This can include ordering and interpreting blood work, imaging studies (MRI, CT scans), and assessing for underlying medical conditions (like diabetes, autoimmune disorders, or cardiovascular issues) that could impact a patient’s healing capacity.
  • Synergistic Treatment Planning: A patient with chronic low back pain, for example, receives a multifaceted evaluation. I perform a thorough chiropractic and biomechanical assessment to identify spinal misalignments (subluxations), muscle imbalances, and faulty movement patterns. Simultaneously, under Dr. CCardenas’sdirection, we might investigate inflammatory markers through blood tests or use diagnostic imaging to rule out pathologies like disc herniations or spinal stenosis. The treatment plan then becomes a fusion of our expertise: I will provide chiropractic adjustments to restore spinal alignment and nerve function, while we may also recommend functional medicine interventions to address systemic inflammation and, if medically necessary, regenerative injections overseen by Dr. Cardenas to repair damaged ligamentous or disc tissue.
  • A Safety Net for Holistic Care: The presence of a medical doctor on our team provides a crucial safety net. It allows us to confidently manage a wide spectrum of patient needs, from a straightforward personal injury case to a complex chronic pain patient with multiple comorbidities. It bridges the gap between the “alternative” and “conventional” medical worlds, offering patients the best of both.

Our services reflect this integrated model, encompassing:

  • Chiropractic Care: Focused on spinal health, nervous system function, and biomechanics.
  • Functional Medicine: Investigating the root causes of disease and dysfunction.
  • Personal Injury and Rehabilitation: Comprehensive care for accidents and injuries.
  • Medical Oversight: Ensuring patient safety and comprehensive diagnostic workups.
  • Regenerative Medicine: Utilizing the body’s own healing mechanisms to repair tissue.

This collaborative framework ensures that we are not just treating symptoms; we are addressing the whole person—structurally, biochemically, and medically. This synergy allows us to take on complex cases and guide our patients on a true journey to healing and optimal function.

The Challenge of Tendinopathies: A Deeper Look at Achilles Tendonitis

One of the most common and frustrating conditions we treat in our clinic is Achilles tendonitis, or more accurately, Achilles tendinopathy. Understanding the distinction is crucial for effective treatment. “Tendonitis” implies a predominantly inflammatory process (-itis means inflammation). For many years, we believed that tendon pain was primarily caused by inflammation. However, modern research, including histological studies of chronic tendon tissue, has revealed a different story.

Leading researchers in the field have shown that in chronic cases, the problem is not active inflammation but rather a degenerative process called tendinosis. This is a state of cellular breakdown and disorganization within the tendon. Instead of the neat, parallel, and robust collagen fibers that give a healthy tendon its incredible tensile strength, we see:

  • Collagen Disarray: The fibers become tangled, disorganized, and weakened.
  • Angiofibroblastic Hyperplasia: A pathological process characterized by an abnormal ingrowth of new, dysfunctional blood vessels (neo-vascularization) and an increase in immature fibroblast-like cells. These new vessels are leaky, weak, and often accompanied by nerve endings that contribute to pain.
  • Mucoid Degeneration: The accumulation of a gel-like substance that further disrupts the tendon’s structure and integrity.
  • Paucity of Inflammatory Cells: A noticeable lack of the inflammatory cells (like neutrophils and macrophages) that you would expect to see in an acute injury.

This is a failed healing response. The body has attempted to repair the initial micro-trauma but has failed to complete the process, resulting in a structurally compromised, weak, and painful tendon. This is why traditional anti-inflammatory treatments, such as long-term use of NSAIDs (Non-Steroidal Anti-Inflammatory Drugs) or corticosteroid injections, often fail in the long run and can even be detrimental. Corticosteroids, in particular, can inhibit collagen synthesis and further weaken the tendon, increasing the risk of a catastrophic rupture.

The Role of Mechanical Load and Immobilization

So, what drives this degenerative process? It’s often a cycle of overuse and inadequate recovery. For a truck driver, for example, the repetitive action of pressing the pedals, especially the clutch, places a constant, low-grade eccentric load on the Achilles tendon. An athlete might experience this from repetitive jumping or running. This chronic overloading, without sufficient time for the tendon cells (tenocytes) to repair the micro-damage, initiates the degenerative cascade of tendinosis.

Now, let’s consider the treatment. When a patient presents with significant Achilles tendinopathy, especially if we are considering a regenerative intervention like prolotherapy, managing the mechanical load on that tendon becomes paramount. The tendon needs a protected environment to heal. This is where immobilization, often with a walking boot, becomes a critical component of the initial treatment phase.

My clinical protocol, developed from evidence-based practices and years of observation, is clear on this. If we are embarking on a regenerative treatment plan for Achilles tendinosis, the patient must be compliant with offloading the tendon.

  • Why the Boot is Non-Negotiable: The goal of our regenerative injections is to restart the healing cascade. We are intentionally creating a controlled, localized inflammatory response to signal the body to bring in growth factors, fibroblasts, and other reparative cells. If the patient continues to place excessive strain on the tendon by walking, running, or working without support, they are essentially counteracting the treatment. The newly forming collagen fibers are delicate and can be easily disrupted or torn, sabotaging the entire healing process.
  • Initial Immobilization Protocol: For a patient undergoing prolotherapy for Achilles tendinosis, I typically require them to wear a walking boot for at least the first week following the injection. This provides strict immobilization and allows the initial, crucial phases of inflammation and proliferation to occur without mechanical disruption.
  • Progressive Weaning: After the first week, the protocol can be adjusted based on the patient’s progress and the severity of the condition. They might be allowed to remove the boot for short periods while at rest but must wear it when ambulating. As they return for subsequent treatments (often spaced several weeks apart to allow for tissue remodeling), we reassess. The goal is to gradually reintroduce load to the tendon in a controlled manner, as mechanical stimulation is eventually necessary to guide the proper alignment of new collagen fibers. This is where our integrated rehabilitation comes in, with specific eccentric loading exercises introduced at the appropriate time.

This structured approach of “protect, then progressively load” is fundamental. Without patient compliance with immobilization, the chances of a successful outcome from even the most advanced regenerative therapies are significantly diminished. It is a partnership: we provide the biological stimulus for healing, and the patient provides the optimal mechanical environment for that healing to take place.

Prolotherapy: Reigniting the Body’s Natural Healing Cascade

Now, let’s dive into the core of one of our key regenerative therapies: prolotherapy. The term is short for “proliferative therapy,” and its name perfectly describes its function—it stimulates the proliferation and regeneration of new, healthy tissue.

You asked, “What’s Prolo?” The answer is both simple and profoundly elegant. At its most fundamental level, prolotherapy involves injecting a mild irritant solution into a damaged area, such as a weakened ligament or a degenerated tendon, to trigger a localized, controlled healing response intentionally.

The Science of Dextrose Prolotherapy

The most commonly used and extensively studied prolotherapy agent is hypertonic dextrose. This is a simple sugar solution, but its concentration is key. We typically use a 50% dextrose solution, which we then mix with a local anesthetic, usually 2% lidocaine, for patient comfort during the injection.

Here is the physiological journey that occurs when we inject this solution into, for example, the enthesis of the Achilles tendon (the point where it inserts into the heel bone):

  1. Cellular Dehydration and Osmotic Shock: The hypertonic (highly concentrated) dextrose solution creates a significant osmotic gradient. The fluid inside the local cells (tenocytes, fibroblasts) is less concentrated than the injected solution. Through osmosis, water is rapidly drawn out of these cells, causing them to shrink and become dehydrated. The body perceives this cellular stress as a mild injury.
  2. Triggering the Inflammatory Cascade: This controlled “injury” is the magic key. It kickstarts the body’s natural, three-stage wound healing cascade—the very same process that was stalled in the chronic tendinosis state.
    • Phase 1: The Inflammatory Phase (First 1-3 days): The cellular stress and dehydration signal the release of a host of inflammatory mediators and chemotactic agents from local platelets, mast cells, and other cells. This is like sounding an alarm. Platelets arrive and degranulate, releasing crucial growth factors such as Platelet-Derived Growth Factor (PDGF), Transforming Growth Factor-Beta (TGF-β), Epidermal Growth Factor (EGF), and Vascular Endothelial Growth Factor (VEGF). These growth factors are the project managers of the healing process. They call in the “clean-up crew” (macrophages) to clear out degenerated tissue and the “construction crew” (fibroblasts) to start rebuilding.
    • Phase 2: The Proliferative Phase (Day 3 to ~6 weeks): This is where the real rebuilding begins. Guided by the growth factors, fibroblasts migrate to the area. They begin to proliferate and, most importantly, synthesize and lay down new Type III collagen. This is a relatively weak and disorganized “scaffolding” collagen, but it’s the essential first step in rebuilding the tendon’s matrix. Angiogenesis (the formation of new blood vessels) also occurs, bringing a fresh supply of oxygen and nutrients to the healing tissue.
    • Phase 3: The Remodeling Phase (Week 6 to 12+ months): This is the longest and arguably most important phase. The initial, weak Type III collagen is gradually replaced by the much stronger, more organized Type I collagen—the primary structural component of a healthy tendon. This process requires a careful balance of rest and controlled mechanical stress. This is where our chiropractic and physical rehabilitation programs become critical. Specific, gentle loading exercises (like eccentric heel drops for Achilles tendinosis) help guide the alignment of new collagen fibers along lines of tension, resulting in a tendon that is not only repaired but also strong, resilient, and functional.
5 Things You Need to Know About Ligamentous Injuries Before They Get Worse

Why Prolotherapy Works for Chronic Pain

The power of prolotherapy lies in its ability to address the root cause of many chronic musculoskeletal pain conditions: ligamentous laxity and tendinosis. Ligaments are the “stabilizers” of our joints. When they are injured or stretched (a sprain), they often do not heal back to their original tightness, leading to joint instability. This instability forces the surrounding muscles to work overtime to stabilize the joint, leading to chronic muscle spasm, fatigue, and pain. It can also cause abnormal wear and tear on the joint cartilage, leading to osteoarthritis.

Prolotherapy, by strengthening and tightening these weakened ligaments and repairing degenerated tendons, restores stability to the joint. This breaks the vicious cycle of instability, muscle spasm, and pain. It is not a pain-masking treatment; it is a restorative and curative therapy that corrects the underlying mechanical problem.

As a clinician with extensive experience in both chiropractic and functional medicine, I see prolotherapy as a perfect bridge. Chiropractic adjustments are excellent at restoring proper joint mechanics and nerve function, but if the ligaments supporting the joint are weak, the joint may not “hold” the adjustment. Prolotherapy strengthens those very ligaments, creating a stable foundation upon which chiropractic care and rehabilitation can build lasting results. This is the essence of our integrative approach—using the right tools in the right sequence to rebuild the patient from the ground up.

The Injection Procedure: Precision and Technique

When we prepare for the injection, precision is everything. Let’s imagine we are treating the Achilles tendon.

  • Patient Positioning: The patient is positioned comfortably, typically lying prone with their foot hanging off the edge of the table to allow easy access to the entire length of the tendon and its insertion point on the calcaneus (heel bone).
  • Sterile Preparation: The entire area is meticulously cleaned with an antiseptic solution like chlorhexidine or Betadine to minimize the risk of infection.
  • The “Peppering” Technique: We don’t just do one large injection. The goal is to stimulate a broad area of tissue. We use a technique called “peppering,” where the needle is inserted and then fanned out to make multiple small deposits of the prolotherapy solution throughout the degenerated portion of the tendon and, critically, at the enthesis (the fibrocartilaginous junction where the tendon inserts into the bone). The enthesis is a common site of pathology and pain, and it is rich in proprioceptive nerve endings and has a poor blood supply, making it notoriously slow to heal on its own.
  • Mixing the Solution: In the syringe, we draw up the 50% dextrose and the 2% lidocaine. The lidocaine serves two purposes: it provides immediate anesthesia to make the procedure more comfortable, and it also contributes to the initial inflammatory signal, as local anesthetics can have a mild irritant effect on cells. The final mixture is tailored to the specific tissue and patient.

This procedure, when performed by a skilled practitioner, is safe and remarkably effective. It harnesses the body’s own powerful, innate healing intelligence and directs it to the precise area where it is needed most. It is a cornerstone of regenerative medicine and a powerful tool in our arsenal against chronic musculoskeletal pain.

Expanding the Regenerative Toolkit: PRP and Stem Cells

While dextrose prolotherapy is a powerful and foundational treatment, it is part of a broader spectrum of orthobiologics—substances derived from the body that can help injuries heal. Two other key players in this field are Platelet-Rich Plasma (PRP) and mesenchymal stem cells (MSCs). Understanding how these therapies relate to and build upon the principles of prolotherapy is essential for creating a truly customized treatment plan.

The central concept connecting all these therapies is stimulating the body’s healing cascade. They all work by delivering a concentrated dose of the biological signals needed for tissue repair. The primary difference lies in the potency and composition of the “signal” being delivered.

Platelet-Rich Plasma (PRP): Concentrating the Body’s First Responders

If dextrose prolotherapy is like sending a general alarm to call in the body’s healing factors, PRP is like delivering the healing factors themselves directly to the site in a highly concentrated form.

  • What is PRP? Platelets, or thrombocytes, are small, anuclear cell fragments in our blood. While their most famous role is in blood clotting, they are also miniature powerhouses of healing. Their cytoplasm is packed with alpha granules, which are tiny storage sacs filled with a vast array of potent growth factors. These are the very same growth factors (PDGF, TGF-β, VEGF, etc.) that are released during the initial inflammatory phase of healing triggered by prolotherapy. PRP therapy involves concentrating these platelets from the patient’s own blood and injecting them into the injured area.
  • The PRP Procedure:
    1. Blood Draw: The process is simple and safe. We draw a small amount of the patient’s blood, just like a standard lab test, into a special tube containing an anticoagulant.
    2. Centrifugation: This tube is then placed in a centrifuge, a machine that spins at high speed. The spinning separates the blood into its different components based on density. The heavier red blood cells fall to the bottom, the lighter plasma (the liquid portion of blood) and platelets rise to the top, and a thin layer in between, called the “buffy coat,” is where the platelets and white blood cells are most concentrated.
    3. Extraction and Injection: We carefully extract this platelet-rich layer, which can have a platelet concentration 3 to 10 times greater than that of normal blood. This golden-colored liquid, the PRP, is then immediately injected into the patient’s injured tendon, ligament, or joint using the same sterile, precise techniques (like ultrasound guidance) as prolotherapy.
  1. PRP vs. Prolotherapy: When to Use Which?
    • Prolotherapy is often my first-line treatment for more diffuse conditions like generalized ligamentous laxity or mild to moderate tendinosis. It is cost-effective, has a long track record of safety, and is excellent at “waking up” the healing process over a broad area. It’s like tilling the soil and adding a general fertilizer.
    • PRP is a more potent, targeted therapy. I often reserve it for more significant injuries, such as partial tendon tears, moderate to severe tendinosis, or cases where prolotherapy has not yielded a complete response. It is also particularly effective for intra-articular (in-joint) conditions like osteoarthritis, as it provides a concentrated bath of anti-inflammatory and regenerative growth factors directly to the damaged cartilage and synovium. Think of PRP as a specialized, high-potency fertilizer applied directly to the root of a struggling plant.

From a clinical standpoint, the combination of our services works synergistically. A patient might receive a chiropractic adjustment to align the pelvis and sacroiliac joints, followed by prolotherapy to the sacroiliac ligaments to provide long-term stability, and then a PRP injection into a specific torn ligament or degenerated disc identified on an MRI. This multi-layered approach addresses the problem from every angle: mechanical, structural, and biological.

Mesenchymal Stem Cells (MSCs): The Master Coordinators of Repair

If PRP delivers the project managers (growth factors), stem cell therapy delivers the master architects and a fresh construction crew. This represents the most advanced frontier of regenerative medicine currently in clinical use.

  • What are MSCs? Mesenchymal stem cells are multipotent stromal cells that can differentiate into a variety of cell types, including osteoblasts (bone cells), chondrocytes (cartilage cells), myocytes (muscle cells), and adipocytes (fat cells). However, their primary therapeutic action in orthopedics is not necessarily by differentiating into new tissue themselves. Instead, they act as powerful “orchestrators” of the healing environment through a paracrine effect.
  • The Paracrine Effect: When injected into an injured area, MSCs release a powerful cocktail of trophic (growth-promoting), anti-inflammatory, and immunomodulatory factors. They essentially assess the local environment and secrete the specific molecules needed to:
    • Potently suppress inflammation: They can calm an overly aggressive inflammatory response that might be damaging tissue.
    • Inhibit apoptosis (cell death): They protect existing healthy cells from dying off in the harsh environment of an injury.
    • Promote angiogenesis: They stimulate the formation of new, healthy blood vessels.
    • Recruit native stem cells: They send out signals that call the body’s own resident stem cells to the site of injury to participate in the repair.
    • Modulate the immune system: They prevent the immune system from attacking the healing tissue.
  • Sources of MSCs: In clinical practice, MSCs are typically harvested from the patient’s own body (autologous). The two most common sources are:
    1. Bone Marrow Aspirate Concentrate (BMAC): This involves a minimally invasive procedure, usually done under local anesthesia, where a needle is used to draw bone marrow from the iliac crest (the back of the hip bone). The aspirate is then centrifuged to concentrate the stem cells and other regenerative cells. BMAC is a rich source of MSCs and hematopoietic stem cells (which form blood cells), as well as a full complement of growth factors similar to PRP.
    2. Adipose-Derived Stem Cells (ADSCs): This involves a mini-liposuction procedure, where a small amount of fat tissue is harvested, typically from the abdomen or flank. The fat is then processed to isolate the stromal vascular fraction (SVF), which is extremely rich in ADSCs. Adipose tissue is a particularly dense source of MSCs, containing hundreds of times more stem cells per gram than bone marrow.
  1. Clinical Application: Stem cell therapy is typically reserved for the most severe cases: significant partial or full-thickness tendon tears, advanced osteoarthritis, or degenerative disc disease, where the goal is not only to stop degeneration but to achieve significant structural regeneration.

In our integrative clinic, a decision to use stem cell therapy would be made after a comprehensive evaluation involving both Dr. Cardena and mes. We would review advanced imaging (MRI), assess the patient’s overall health and comorbidities, and have a thorough discussion about the risks, benefits, and realistic expectations. The procedure itself would be performed under the highest medical standards, often utilizing imaging guidance (ultrasound or fluoroscopy) to ensure precise placement of these precious cells.

The journey from prolotherapy to PRP to stem cells is a journey of increasing biological potency. By having all these tools at our disposal, we can tailor the regenerative stimulus to the exact needs of the patient and the specific nature of their injury, embodying the true meaning of personalized, evidence-based medicine.

The Foundational Role of Chiropractic Care in Musculoskeletal Healing

While advanced regenerative injections like prolotherapy and PRP are powerful tools for stimulating tissue repair at a cellular level, they are not a magic bullet. True, lasting healing requires a holistic approach that addresses the entire kinetic chain—the interconnected system of bones, joints, muscles, and nerves that governs how we move. This is where chiropractic care serves as the indispensable foundation of our treatment paradigm.

At its core, chiropractic philosophy is rooted in the principle that the body has an innate intelligence (innate wisdom) to heal itself. The nervous system, housed within the spinal column, is the master control system that coordinates this healing. When the spine is misaligned, a condition chiropractors call a vertebral subluxation, it can interfere with the normal transmission of nerve signals. This not only causes local pain and muscle spasm but can also disrupt the function of the very tissues and organs that those nerves supply, impeding the body’s ability to heal and regulate itself.

Biomechanics: The “Why” Behind the Injury

Before we even consider an injection, my first step as a chiropractor is to perform a thorough biomechanical analysis. Why did this patient develop Achilles tendinosis in the first place? It’s rarely just an isolated problem in the tendon itself. The answer often lies “upstream” in the kinetic chain.

  • Case Example: The Achilles Tendon: A patient presents with right-sided Achilles pain. A conventional approach might focus on the ankle. My chiropractic and functional movement assessment, however, might reveal:
    • A Pelvic Tilt: The patient’s right ilium may be rotated posteriorly, causing a functional leg length discrepancy. This makes the right leg effectively “shorter,” altering the way their foot strikes the ground with every step.
    • Overpronation: This pelvic imbalance can lead the foot to roll inward (overpronate) to compensate excessively. Overpronation places a “whipping” or torsional strain on the Achilles tendon, creating micro-trauma with every step.
    • Sacroiliac Joint Dysfunction: The underlying cause of the pelvic tilt could be a fixation or misalignment in the sacroiliac (SI) joint.
    • Lumbar Spine Subluxation: The SI joint dysfunction might, in turn, be a compensation for a subluxation in the lower lumbar spine (e.g., L4/L5), potentially irritating the nerve roots that contribute to the sciatic nerve, which controls the muscles of the lower leg.

You can see how the pain in the ankle is just the “symptom” of a cascade of biomechanical failures. Simply injecting the Achilles tendon without correcting these underlying structural faults is like patching a crack in a wall without fixing the crumbling foundation. The crack will inevitably return.

The Chiropractic Adjustment: Restoring Neuromechanical Function

The primary tool I use to correct these faults is the chiropractic adjustment. This is a specific, gentle, and controlled force applied to a joint to restore its proper motion and alignment.

  • Restoring Joint Mobility: The adjustment breaks up adhesions and releases fixations in the joints of the spine, pelvis, and extremities (including the foot and ankle). By restoring normal movement to the SI joint and lumbar vertebrae, we can correct the pelvic tilt and leg length discrepancy.
  • Normalizing Nerve Function: By correcting the subluxation, we remove the interference from the nervous system. This has several profound effects:
    • Pain Reduction: It reduces the direct irritation of nerve roots and mechanoreceptors in the joint capsule, providing immediate pain relief.
    • Muscle Relaxation: It resets the nerve signals to the surrounding muscles, breaking the cycle of chronic muscle spasm and guarding that contributes to pain and dysfunction. For our Achilles patient, this means the tight calf muscles (gastrocnemius and soleus) that are constantly pulling on the tendon can finally relax.
    • Improved Proprioception: Proprioception is the body’s sense of its position in space, managed by nerve endings in our joints and muscles. An adjustment “re-calibrates” these signals, improving balance, coordination, and neuromuscular control. This is crucial for preventing re-injury.
  • Facilitating Systemic Healing: By optimizing nervous system function, we are ensuring that the brain can effectively coordinate the healing process throughout the body. The signals to release anti-inflammatory cytokines, to direct blood flow, and to activate the cellular repair mechanisms we stimulate with prolotherapy are all transmitted and managed by the nervous system. A well-adjusted spine ensures this communication network is free of static and interference.

Integrating Adjustments with Regenerative Therapies

In our clinic, chiropractic adjustments and regenerative injections are not separate treatments; they are two parts of a single, integrated plan.

  1. Preparation: Before a regenerative procedure, I will often perform a series of adjustments. The goal is to create a biomechanically neutral and stable environment. By aligning the pelvis, spine, and foot/ankle complex before we inject, we ensure that the tendon or ligament we are treating is not under abnormal stress during the initial, critical phase of healing.
  2. During the Healing Process: Following an injection, gentle, specific adjustments continue to be a key part of the protocol. We avoid aggressive manipulation of the treated joint itself, but we continue to adjust adjacent areas to maintain overall alignment. This prevents compensatory patterns from developing while the treated area is healing. For instance, while the patient is in a walking boot for their Achilles, we will regularly adjust their pelvis and lumbar spine to counteract the gait changes and stresses imposed by the boot.
  3. Long-Term Stabilization: Once the ligaments and tendons are strengthened by prolotherapy or PRP, the chiropractic adjustments become even more effective. A stable, regenerated ligamentous system can now “hold” the adjustment, preventing the recurrence of subluxations and ensuring long-term biomechanical integrity.

This synergy between restoring structure (chiropractic) and regenerating tissue (prolotherapy/PRP), all under the watchful medical oversight of Dr. Cardenas, is the hallmark of our practice. We are not just chasing pain; we are rebuilding the patient’s entire neuromusculoskeletal system to be stronger, more stable, and more resilient than it was before the injury.

Clinical Pearls and Advanced Considerations

Drawing upon years of clinical practice and a deep dive into the scientific literature, we integrate several nuanced concepts and advanced protocols into our patient care plans. These “clinical pearls” often make the difference between a good outcome and a great one, reflecting a sophisticated understanding of human physiology and the art of personalized medicine.

The Importance of a Comprehensive Diagnostic Workup

Before any needle touches the skin, a thorough and accurate diagnosis is the bedrock of our approach. This goes far beyond just identifying the painful spot.

  • History is Paramount: The patient’s story tells us so much. I spend a significant amount of time listening. When did the pain start? What was the mechanism of injury? What makes it better or worse? Are there patterns to the pain throughout the day? A truck driver’s Achilles pain will have a different mechanical origin story than a marathon runner’s. This narrative guides our physical exam.
  • Physical Examination: This is a hands-on, multi-system evaluation.
    • Palpation: We palpate not just the site of pain but the entire kinetic chain. For Achilles pain, this means feeling the texture and tenderness of the tendon, the calf muscles, the hamstring attachments, the gluteal muscles, the sacroiliac ligaments, and the paraspinal muscles of the lumbar spine. Tendinosis often feels nodular, thickened, and exquisitely tender.
    • Range of Motion Testing: We assess both active and passive range of motion in all related joints to identify restrictions.
    • Orthopedic and Neurological Testing: Specific tests (like Thompson’s test to rule out an Achilles rupture) are crucial. We also check reflexes, sensation, and muscle strength to assess for any neurological compromise.
  • Diagnostic Imaging:
    • Musculoskeletal Ultrasound (MSKUS): This is one of the most valuable tools in my office. With diagnostic ultrasound, I can visualize the tendon in real-time. I can see the disorganized fibers, the thickening, the neovascularity of tendinosis, and the precise location of any partial tears. It is also an invaluable tool for guiding our injections, allowing us to place the needle with millimeter accuracy directly into the pathological tissue, while avoiding sensitive structures like nerves and blood vessels. This is a significant advantage over “blind” injections.
    • MRI: For more complex cases, or to evaluate intra-articular structures like cartilage, menisci, or the spinal discs, an MRI is the gold standard. The decision to order an MRI is often made in consultation with Dr. Cardenas, ensuring it is medically appropriate.

Functional Medicine: Addressing Systemic Barriers to Healing

A musculoskeletal injury does not happen in a vacuum. The body’s ability to mount an effective healing response is profoundly influenced by its overall systemic health. This is where my functional medicine training becomes critical. We look for and address factors that may be sabotaging the healing process from the inside out.

  • Nutritional Status: Tissue repair is an energy-intensive process that requires specific building blocks. We assess for and correct deficiencies in key nutrients:
    • Vitamin C: Essential for collagen synthesis.
    • Zinc and Copper: Co-factors for enzymes involved in cross-linking collagen fibers.
    • Amino Acids: Especially proline, lysine, and glycine, which are the primary amino acids that make up collagen. We may recommend a high-quality collagen or specific amino acid supplement.
    • Protein Intake: Patients need adequate protein to fuel tissue regeneration.
  • Systemic Inflammation: While we want to induce localized inflammation with prolotherapy, chronic, systemic inflammation is detrimental to healing. It creates a “pro-degenerative” environment throughout the body. We use advanced blood tests (like hs-CRP, ESR, and cytokine panels) to assess a patient’s inflammatory status. We then use targeted nutritional and lifestyle interventions to lower systemic inflammation:
  • Anti-Inflammatory Diet: Emphasizing whole foods, omega-3 fatty acids (from fish oil), and phytonutrients (from colorful fruits and vegetables), while removing pro-inflammatory foods like processed sugar, industrial seed oils, and refined carbohydrates.
  • Gut Health: A leaky gut (intestinal permeability) is a major driver of systemic inflammation. We may incorporate protocols to heal the gut lining.
  • Metabolic Health: Conditions like insulin resistance and diabetes are catastrophic for tendon health. High blood sugar leads to the formation of Advanced Glycation End-products (AGEs). These AGEs cross-link with collagen fibers, making them brittle, stiff, and prone to injury. They also impair blood flow and cellular function. For any patient with a chronic tendinopathy, screening for metabolic dysfunction is non-negotiable. Managing blood sugar through diet, exercise, and targeted supplements is often a prerequisite for a successful outcome with regenerative therapies.
  • Hormonal Balance: Hormones like thyroid hormone, cortisol, and sex hormones play a role in tissue metabolism and repair. An imbalance, such as hypothyroidism or chronic high cortisol from stress, can significantly slow down healing.

By integrating these functional medicine principles, we ensure that the “soil” (the patient’s systemic environment) is fertile and ready to support the “seed” of regeneration that we plant with our injections.

The Post-Injection Protocol: A Roadmap to Recovery

The treatment does not end when the patient leaves the clinic after their injection. The post-procedure period is just as important as the procedure itself. Each patient receives a detailed, written protocol that outlines what to expect and what to do.

  • Managing Post-Injection Soreness: We explain that it is normal and, in fact, desirable to experience some soreness, stiffness, and swelling for a few days after the injection. This is a sign that the desired inflammatory healing cascade has been successfully initiated.
  • STRICT AVOIDANCE of Anti-Inflammatories: This is a crucial point. We instruct patients to avoid all NSAIDs (like ibuprofen, naproxen) and ice for at least two weeks, and preferably throughout the entire course of treatment. These agents block the very inflammatory pathways (specifically the prostaglandin pathway) that we are trying to stimulate. Taking them is like calling the fire department to put out the controlled burn we just started. For pain management, we recommend acetaminophen (Tylenol), which is a pain reliever but not a potent anti-inflammatory, or natural anti-inflammatory support that works on different pathways, like curcumin or boswellia, after the initial acute phase.
  • Activity Modification and Rehabilitation: The protocol provides a week-by-week guide to activity.
    • Week 1 (Protection Phase): As discussed, this often involves immobilization in a boot or sling. The focus is on relative rest and protecting the healing tissue. Gentle, pain-free range of motion is encouraged to prevent stiffness.
    • Weeks 2-6 (Proliferation/Early Remodeling): We begin to introduce gentle, controlled stress. For the Achilles, this is when we would start isometric exercises (contracting the muscle without moving the joint) and then progress to very light eccentric exercises. Eccentric loading (lengthening the muscle-tendon unit under tension) has been shown in numerous studies to be the most effective stimulus for promoting healthy collagen remodeling in tendons.
    • Week 6+ (Remodeling and Strengthening): We gradually increase the intensity and complexity of the exercises, progressing towards functional movements that mimic the patient’s daily activities or sport. This is a collaborative process involving myself, the patient, and sometimes our dedicated rehabilitation staff.

This structured, phased approach ensures that we apply the right type of mechanical stress at the right time, guiding healing tissue to mature into a strong, resilient, and fully functional structure. It is this meticulous attention to detail, from the initial diagnosis to the final stages of rehabilitation, that defines a truly comprehensive and successful regenerative medicine program.

References

SEO Tags: Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, Integrative Medicine, Chiropractic Care, El Paso TX, Prolotherapy, Achilles Tendonitis, Tendinosis, Regenerative Medicine, Platelet-Rich Plasma, PRP, Stem Cell Therapy, Functional Medicine, Musculoskeletal Injury, Chronic Pain, Biomechanics, Vertebral Subluxation, Chiropractic Adjustment, Personal Injury Care, Rehabilitation, Dextrose Prolotherapy, Ligament Laxity, Joint Instability, Holistic Healthcare

Integrative PRP and Peptide Care Benefits for Patients

Integrative PRP and Peptide Care Benefits for Patients

Integrative PRP and Peptide Care: How Evidence-Based Protocols, Chiropractic Integration, and Medical Oversight Enhance Outcomes

Abstract

In this educational post, I present a clear, patient-centered journey through modern platelet-rich plasma (PRP) handling, gel-separator technique, scalp and joint applications, peptide adjuncts, and how we integrate these with chiropractic care, functional medicine, rehabilitation, and personal injury services. I explain why precise tube handling matters physiologically, how air pockets and gel contact affect plasma integrity, and why patients feel transient tension-like sensations during scalp procedures.

I outline our multidisciplinary model at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, collaborate with our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), whose extensive internal medicine experience ensures rigorous medical oversight. I highlight practical protocols, clinical observations from our sciatica and musculoskeletal programs, and evidence-based rationale linking PRP and peptide therapy to tissue repair, nociception modulation, and neuromuscular function—showing exactly how integrative chiropractic care fits into comprehensive treatment pathways.

Integrative PRP and Peptide Care Benefits for Patients

Introduction: A Practical Journey Through PRP, Peptides, and Integrative Care

I often start by demystifying the hands-on steps that make biologic therapies successful. In our clinic, patients see us prepare PRP tubes, discuss gel separators, and decide how best to use PRP across different sites—ankle, knee, hip, scalp, and even in cosmetic adjuncts. This transparency builds trust and helps patients understand why small details—like avoiding gel contact or managing an air pocket—can meaningfully influence outcomes. The short-lived scalp “tightness” many feel isn’t random; it reflects local tissue signaling, transient nociceptive input, and pressure dynamics that normalize quickly. When we add carefully selected peptides and massage-based delivery, comfort improves, and local circulation enhances the biologic activity at the treatment site.

At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), our multidisciplinary setup is the backbone of safety and efficacy. I lead the chiropractic and functional medicine integration, while Dr. Maria Guadalupe Cardenas, MD—our Medical Director and Collaborative Physician—provides medical direction and internal medicine oversight. Together, we align PRP, peptides, chiropractic adjustments, rehabilitative exercise, and personal injury protocols under evidence-based methods, ensuring patients receive comprehensive, coordinated care.

PRP Fundamentals: Why Gel Separators, Air Pockets, and Spin Parameters Matter

  • Key concept: A gel separator sits between red blood cells and plasma after centrifugation. If the draw needle or transfer tip touches the gel, non-plasma components can mix upward, reducing platelet purity and forcing a re-spin to restore separation.
  • Physiological rationale: PRP efficacy depends on platelet concentration and integrity. Platelets carry alpha granules rich in growth factors—PDGF, TGF-β, VEGF, EGF—that signal angiogenesis, fibroblast activation, and extracellular matrix repair. Diluting PRP with residual red cells or leukocytes changes the cytokine milieu and can increase inflammatory noise, which may alter outcomes in sensitive tissues.

Technique notes I emphasize:

  • Maintain tip control near the source, avoid contacting the gel, and keep air pockets small but present where recommended to prevent vacuum lock and facilitate even transfer.
  • Use validated spin speeds and durations appropriate to the kit’s design; over-spinning can cause platelet activation in the tube, premature degranulation, and reduced bioactivity on delivery.
  • For multi-site plans (e.g., ankle, knee, hip, scalp), allocate full tubes per target based on dosing guidance and patient-specific goals (pain reduction, tendon healing, hair follicle support), ensuring consistency across sessions.

Clinical observation: When handling tubes, my team prefers a controlled transfer technique that protects the plasma interface. Patients often ask why we are meticulous—because even a “tiny tip” gel contact can force a re-spin and delay care. The better the separation, the better the bioactive payload.

Patient Sensations: Understanding the Transient “Tension” After Scalp PRP

Many patients describe a brief tightness or tension-like headache in the scalp immediately after PRP, resolving in minutes. Here’s why:

  • Local mechanoreceptor and nociceptor activation: Needle microtrauma and volume expansion stimulate transient pain fibers (A-delta and C fibers). This brief signaling is part of normal local tissue response.
  • Microvascular dynamics: PRP introduces volume and bioactive factors that modulate vasodilation and endothelial signaling. The pressure change can feel like a vice that quickly subsides as homeostasis returns.
  • Inflammatory micro-priming: Controlled, short-lived inflammation invites macrophage and fibroblast activity, enhancing regenerative signaling without prolonged discomfort.

Clinical tip: Gentle scalp massage post-application can improve comfort, encourage lymphatic flow, and support even distribution of PRP and peptides across microchannels created by microneedling.

Peptides Added to PRP: Why Combination Therapy Can Enhance Outcomes

We often add peptides following PRP—particularly in hair restoration and skin support—because certain peptides can:

  • Promote angiogenesis and collagen remodeling (e.g., copper peptide GHK-Cu).
  • Support follicular cycling, keratinocyte health, and dermal extracellular matrix integrity.
  • Modulate inflammatory signaling to fine-tune repair without blunting the regenerative cascade.

Physiologic rationale:

  • PRP supplies growth factors; peptides can provide receptor-level nudges that make cellular responses more coherent. Together, they create a synergistic microenvironment: PRP initiates, peptides guide and sustain.
  • Massage-driven delivery increases local perfusion and dispersion, potentially optimizing bioavailability across treated microchannels.

Clinical observation: Patients report that peptide adjuncts make sessions more comfortable and “feel pleasant,” reinforcing adherence and overall satisfaction. When we open a site with PRP (e.g., scalp), peptides become a biologic “finisher,” reinforcing ECM remodeling and trophic support.

Cosmeceutical Carriers: Stabilizing PRP in Topical Systems

Some patients use a PRP-compatible carrier cream—such as specialized formulations designed to hold PRP for cosmetic use—to extend localized benefits after in-clinic procedures. The rationale:

  • A stable carrier matrix may maintain PRP components for short-term topical application post-microneedling, supporting barrier repair and hydration while the skin is most receptive.
  • While topical PRP is distinct from injectable efficacy, post-procedure microchannels can facilitate superficial delivery of bioactive constituents, complementing clinical PRP injections.

We ensure patients understand the difference between injectable PRP (primary driver of outcomes) and topical adjuncts (supportive, comfort-focused). The carrier must be formulated to preserve PRP integrity for its intended short-term use.

Multidisciplinary Model: Internal Medicine Oversight and Chiropractic Integration

Our team-based approach is core to patient safety and efficacy:

  • Medical Oversight: Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), serves as the Medical Director and Collaborative Physician at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic). With over 40 years as an internist, Dr. Cardenas provides comprehensive medical governance—reviewing labs, contraindications, medications, and systemic risk factors (e.g., diabetes, hypertension, anticoagulation).
  • Chiropractic Integration: I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, coordinate integrative chiropractic care with PRP and peptide therapy. Chiropractic adjustments address joint mechanics, spinal alignment, and neuromuscular coordination, which can improve perfusion and tissue loading patterns—helping PRP-treated tissues heal under more favorable biomechanical conditions.
  • Functional Medicine: We evaluate metabolic drivers of impaired healing (e.g., insulin resistance, micronutrient deficiencies, gut-derived inflammation) and implement targeted nutrition, sleep, stress, and movement plans that enhance cellular repair capacity.
  • Rehabilitation: Our rehab team builds graded exercise plans, proprioceptive training, and tendon-loading protocols to align mechanical stress with the biologic repair timeline triggered by PRP.
  • Personal Injury Care: For trauma cases, we layer diagnostics, case documentation, and coordinated interventions—ensuring medico-legal clarity and consistent functional gains across tissues affected by injury.

How Integrative Chiropractic Care Fits: Biomechanics Meets Biology

  • Restoring Kinematics: Adjustments and mobilization aim to normalize arthrokinematics, reduce facet joint irritation, and improve paraspinal muscle activation. Proper motion reduces maladaptive loading that can sabotage PRP gains in connected chains (e.g., knee PRP benefits are greater when hip and lumbar mechanics are optimized).
  • Neurophysiology: Spinal manipulation can modulate segmental inhibition, influence descending pain pathways, and normalize muscle spindle feedback. Reduced nociceptive noise may improve motor control, facilitating better rehab mechanics as tissues remodel post-PRP.
  • Circulatory Support: By improving thoracolumbar and pelvic mechanics, venous and lymphatic return can improve regionally, potentially assisting clearance of inflammatory byproducts while PRP-driven repair unfolds.

Clinical observations from our sciatica program

Drawing from observations, I’ve seen patients with lumbar radiculopathy and piriformis-related sciatica respond better when PRP targeting tendinous or ligamentous contributors is integrated with:

  • Targeted chiropractic adjustments to reduce foraminal irritation and improve pelvic alignment.
  • Gluteal activation and core stabilization to normalize lumbopelvic mechanics.
  • Anti-inflammatory nutrition and sleep optimization to support neuroimmune balance.

This blend helps downshift central sensitization while PRP addresses local tissue deficits—resulting in more durable functional gains.

Evidence-Based Methods: Linking Protocols to Outcomes

  • PRP Composition: Platelet concentration and leukocyte content should be matched to indication—e.g., leukocyte-poor PRP for intra-articular environments to limit synovial irritation, versus leukocyte-rich PRP for tendon conditions where targeted inflammation can assist remodeling (Fitzpatrick et al., 2017; Andia & Maffulli, 2018).
  • Hair Restoration: PRP is associated with increased hair density and shaft thickness through follicular stem cell activation and improved vascular supply (Gentile & Garcovich, 2020).
  • Musculoskeletal Repair: PRP demonstrates benefits in patellar tendinopathy, lateral epicondylitis, and some knee osteoarthritis cohorts, especially when dosing and frequency are standardized and paired with structured rehab (Laudy et al., 2015; Filardo et al., 2015).
  • Peptide Adjuncts: Peptides such as GHK-Cu have been shown to support skin regeneration, angiogenesis, and collagen synthesis, making them logical adjuncts post-microneedling and after PRP (Pickart & Margolina, 2018).
  • Integrative Model: Combining biologics, chiropractic, and functional medicine under medical oversight reduces fragmentation of care, improves risk management, and supports behavioral adherence—key determinants of outcomes in complex musculoskeletal and hair restoration pathways.

Patient Communication: Making Complex Care Easy to Understand

I prefer simple explanations:

  • “We keep the tip off the gel so your PRP stays pure.”
  • “A little scalp tightness is normal and fades quickly.”
  • “We add peptides to guide the repair that PRP starts.”
  • “Chiropractic and rehab align your mechanics so the biology can succeed.”
  • “Dr. Cardenas reviews your medical background to keep you safe and optimized.”

Practical Protocol Flow: From Draw to Delivery

  • Pre-assessment: Medical screening by Dr. Cardenas and functional review by me—medications, labs, lifestyle risks, and mechanical contributors.
  • Collection and spin: Strict kit instructions, controlled centrifugation, avoiding gel contact, confirming layer purity.
  • Site planning: Allocate full tubes per joint or scalp region as indicated. For microneedling, reserve a portion for topical carrier application when appropriate.
  • Adjunct selection: Choose peptides based on target tissue; consider topical carriers post-microneedling for comfort and barrier support.
  • Chiropractic alignment: Sequence adjustments to normalize kinematics before or after biologic delivery depending on the site and patient tolerance.
  • Rehab progression: Begin with pain-modulated loading, progress to eccentric and isometric strategies, transition to functional patterns that match the patient’s goals.
  • Follow-up: Re-assess pain, function, and tissue quality; refine dosing and integrate lifestyle changes for sustained improvement.

Why This Integrative Strategy Works

  • Systems thinking: We match biologic repair (PRP + peptides) with mechanical coherence (chiropractic + rehab) and metabolic readiness (functional medicine) under solid medical oversight. This reduces conflicting inputs and enhances tissue signaling.
  • Timing: We respect repair timelines—initial inflammation, proliferation, remodeling—so loading and care dosages are synchronized with cellular events.
  • Personalization: We tailor protocols to patient uniqueness—comorbidities, activity demands, and goals—reducing variance and increasing consistency.

Closing Perspective

Our goal is to make advanced care feel intuitive. When patients watch us handle tubes carefully, understand why scalp tightness fades quickly, and see how peptides and massage enhance comfort, they appreciate that precision isn’t a luxury—it’s a necessity. With Dr. Cardenas’s medical direction and our integrative chiropractic, functional medicine, and rehab systems, we deliver coordinated, evidence-based care designed to help tissues heal and patients thrive.

Fighting Inflammation Naturally *Chiropractic Care* | El Paso, Tx (2023)

References

PRP Therapy Results on Plantar Fasciitis on the Achilles Tendon

Find out how PRP therapy can be a game changer for plantar fasciitis and Achilles tendon pain management on the feet.

Abstract

In this educational overview, I, Dr. Alex Jimenez, will guide you through a paradigm shift in understanding and treating chronic heel pain, commonly diagnosed as plantar fasciitis. For years, the standard approach has focused on directly treating the plantar fascia itself—often with painful injections and limited long-term success. However, groundbreaking clinical insights and emerging research now point to a different culprit: the Achilles tendon and the gastrocnemius-soleus complex. We will explore the biomechanical and physiological reasons why dysfunction in the calf and Achilles leads to the painful micro-tears in the plantar fascia. This post details an innovative, evidence-based injection protocol targeting the Achilles tendon, developed through clinical collaboration and supported by research. We will discuss the specific techniques, the rationale behind them, and how this approach integrates seamlessly into a comprehensive, multidisciplinary care model. This model, which we practice at our clinic, combines advanced regenerative medicine with the foundational principles of chiropractic care, medical oversight, functional medicine, and rehabilitation to achieve lasting relief and restore function. We will also introduce the vital collaborative role of Dr. Maria Guadalupe Cardenas, MD, our distinguished Medical Director, whose expertise in internal medicine provides essential medical oversight for our integrative patient care protocols.

A Message from Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST

Hello, and welcome. I am Dr. Alex Jimenez, and I am honored to share with you some of the latest, most effective strategies for managing chronic heel pain. With a deep background in chiropractic, functional medicine, and as a board-certified Family Nurse Practitioner, my mission has always been to find the root cause of my patients’ suffering and provide solutions that are not just palliative but truly corrective.

Here at Injury Medical Clinic PA in El Paso, Texas, we have cultivated a unique, multidisciplinary environment. Our strength lies in our collaborative team approach. I work hand-in-hand with Dr. Maria Guadalupe Cardenas, MD, our esteemed Medical Director and Collaborative Physician. Dr. Cardenas is Board Certified in Internal Medicine and brings over four decades of invaluable experience to our practice. Her role is crucial; she provides the essential medical direction and oversight that allows us to safely and effectively integrate advanced procedures, like the ones we’ll discuss today, with our core services of chiropractic care, rehabilitation, and functional medicine. This synergy ensures that our patients receive a comprehensive, safe, and holistic treatment plan tailored to their specific needs, whether they are recovering from a personal injury or dealing with a chronic condition.

What you are about to read is the culmination of years of clinical practice, collaboration with leading orthopedic surgeons, and a relentless pursuit of better outcomes for patients told their heel pain is something they have to “live with.” Let’s embark on this journey together and redefine how we approach plantar fasciitis.

Rethinking Plantar Fasciitis: The True Origin of Heel Pain

For decades, the medical community has approached plantar fasciitis with the assumption that the problem lies solely within the plantar fascia itself—the thick band of tissue that runs across the bottom of the foot, connecting the heel bone to the toes. This has led to treatments aimed directly at this structure: steroid injections, aggressive stretching, and even surgery. While these methods can provide temporary relief, they often fail to address the underlying cause, leading to high rates of recurrence and, in some cases, further damage, such as fat pad atrophy.

My clinical observations, supported by the work of innovative researchers, have led me to a different conclusion: in most cases of chronic, non-traumatic heel pain, the plantar fascia is the victim, not the culprit. The true problem originates higher up the kinetic chain, specifically within the gastrocnemius-soleus complex (your calf muscles) and its connection to the heel via the Achilles tendon.

The Biomechanical Connection: How Calf Tightness Damages the Foot

To understand this concept, we need to think of the lower leg and foot as an interconnected system.

  • The Windlass Mechanism: The plantar fascia plays a crucial role in the normal biomechanics of walking through what is known as the windlass mechanism. As you push off your toes, the fascia tightens, elevating the arch, stiffening the foot, and creating a rigid lever for efficient propulsion.
  • The Role of the Achilles: The Achilles tendon, the strongest and thickest tendon in the body, connects the powerful calf muscles to the heel bone (calcaneus). It is responsible for plantarflexion (pointing your foot down).
  • The Tug-of-War: An imbalance in this system creates a pathological “tug-of-war” on the calcaneus. When the gastrocnemius and soleus muscles are chronically tight, a condition often stemming from tendinosis (a degenerative state of the tendon), they exert a constant, excessive pulling force on the back of the heel through the Achilles tendon.

Think about what happens overnight. As you sleep, your calf muscles are in a relaxed, shortened state, and your foot naturally falls into a position of plantarflexion. This allows the tight Achilles tendon to pull on the heel, which in turn keeps the plantar fascia in a shortened, slackened state for hours.

Then, your alarm goes off. You stand up, and your entire body weight is suddenly forced onto your foot. This action violently stretches the plantar fascia, which has been in a contracted state all night. This abrupt, forceful stretch is what causes the characteristic stabbing pain of the first few steps in the morning. These are not just feelings of stiffness; they are the result of micro-tears occurring in the fascia at its insertion point on the heel. Day after day, this cycle of nocturnal shortening followed by abrupt morning stretching perpetuates a state of chronic injury, inflammation, and degeneration in the plantar fascia. The body tries to heal, but it is re-injured every single morning.

This is why treatments focused only on the plantar fascia fail. An injection into the fascia might calm the inflammation, but it does nothing to release the relentless tension from the Achilles tendon. We are simply treating the symptom while ignoring the disease. The real solution lies in addressing the Achilles tendinosis and the associated tightness in the gastrocnemius-soleus complex. By releasing this tension, we allow the plantar fascia the biomechanical freedom it needs to heal naturally.

A Revolutionary Treatment Protocol: Targeting the Achilles Tendon

Based on this understanding, a new treatment protocol has been developed—one that I, along with my orthopedic colleagues, have refined over the past decade with remarkable success. This technique was born from a collaborative discussion with an orthopedic surgeon, Dr. Roman, who was frustrated with the poor outcomes of traditional plantar fascia treatments, including fat pad replacement surgeries. Over a series of conversations (and a few Moscow Mules on bar napkins, as the story goes), we mapped out a logical, anatomy-based approach. We hypothesized that if we could treat the tendinosis in the Achilles, we could resolve the downstream problem in the plantar fascia. The clinical results that followed have been nothing short of transformative.

The protocol involves a series of targeted injections into the Achilles tendon itself, rather than the exquisitely sensitive bottom of the foot. The goal is to stimulate a healing response within the degenerated tendon tissue, improve its flexibility, and reduce the chronic tension on the calcaneus.

Identifying the Injection Sites: A Precise, Palpation-Based Approach

Precision is key to this procedure. We don’t just inject randomly; we use careful anatomical landmarks and palpation to identify the exact points of dysfunction.

1. The Mid-Substance Achilles Tendon Injection

The primary target is the “watershed” area of the Achilles tendon, a region approximately 2-6 cm above its insertion on the heel. This area has a relatively poor blood supply, making it susceptible to degeneration (tendinosis) and slow to heal.

  • Patient Positioning: The patient lies face down (prone) on the treatment table with their feet hanging off the edge. This position allows the calf muscles to relax and provides clear access to the Achilles tendon.
  • Locating the Bifurcation: To find the precise entry point, I have the patient gently push their foot against my leg to engage the calf muscles. I then run my thumb superiorly (upward) along the Achilles tendon. I am feeling for a specific landmark: the musculotendinous junction, where the fibers of the gastrocnemius muscle begin to merge into the tendon. This junction often feels like a subtle “bifurcation” or split. This is a critical area of tension and is often tender to the touch. Once I identify this spot, the patient can relax their leg.
  • The Entry Point: This palpable bifurcation becomes our entry point. It represents the upper boundary of the tendinopathic zone we intend to treat.

2. The Achilles Tendon Insertion Injections

The second area of focus is the enthesis—the point where the Achilles tendon inserts directly onto the calcaneus (heel bone). This area is also subject to immense stress and is a common site of degenerative change and pain.

  • Palpation is Key: With the patient’s foot relaxed, I palpate the very bottom of the Achilles tendon where it fans out and attaches to the bone. This area often feeBoneropey” or fibrotic.
  • Identifying Maximum Tenderness: I apply gentle pressure to both the medial (inner) and lateral (outer) sides of the insertion. I ask the patient, “Is it more tender on the inside or the outside?” Most patients report significantly more tenderness on the medial side, which corresponds to the area of greatest mechanical strain.
  • Marking the Sites: The points of maximum tenderness on the medial and lateral aspects of the insertion become our secondary injection targets.

The Injection Technique: A Step-by-Step Guide

With our landmarks identified, we can proceed with the injections. This demonstration uses a biologic allograft solution, but the technique is similar for Platelet-Rich Plasma (PRP) or prolotherapy. The key is to deliver the healing substance accurately into the degenerated tendon tissue.

Procedure for the Mid-Substance Injection

  1. Preparation: The area is thoroughly cleaned with an antiseptic solution. We use a 5 cc syringe, which, for this protocol, is split between the primary site and the insertion sites.
  2. Needle Entry: Using a 1.5-inch needle, I enter the skin at the pre-identified bifurcation point. The bevel of the needle should be pointed up. I advance the needle perpendicularly through the skin and subcutaneous tissue, about halfway in.
  3. Angling Down into the Tendon: This is the most crucial step. Once the needle is about halfway in, I change the angle, dropping it down so it runs parallel to the tendon fibers. I then advance the needle deeper into the core of the tendon.
  4. Feeling the Tissue Change: As the needle enters the tendon, there is a distinct change in tactile sensation. It goes from the soft, yielding feel of subcutaneous fat to a much firmer, denser, almost “gritty” feel. This confirms that we are inside the tendon sheath and within the substance of the tendon itself. This proprioceptive feedback is essential for accurate placement.
  5. Injection: Once I’m confident in the placement, I slowly and gently inject the solution (in this case, 1- 2.5 cc, depending on the total volume available). The goal is to bathe the degenerated fibers in the regenerative substance.

Procedure for the Insertion Site Injections

  1. Angled Approach: For the insertion points on the heel, the approach is different. I come in at an angle, directing the needle toward the point of maximum tenderness on the bone where the tendon attaches.
  2. Contacting the Bone: I advance the needle until I gently make contact with the periosteum (the outer surface of the bone).
  3. Aspiration (A CritBone Safety Step): Before injecting, I aspirate by pulling back on the plunger. This is a non-negotiable safety check. If blood flashes into the hub of the syringe, it means the needle tip is inside a blood vessel. Injecting into a vessel, especially if the solution contains an anesthetic like lidocaine, can cause serious systemic complications. If a flash occurs, I withdraw the needle, clear it, and find a new trajectory.
  4. Injection: If the aspiration is clear (no blood return), I proceed to inject a small amount (e.g., 0.5 cc) of the solution directly onto the enthesis. This is repeated for both the medial and lateral insertion points.

Why This Technique Works: The Physiology of Healing

Whether using PRP, prolotherapy, or other biologic allografts, the underlying principle is the same: we are kick-starting the body’s own healing cascade in a tissue that has become stuck in a degenerative, non-healing state.

  • PRP (Platelet-Rich Plasma): PRP is a concentration of platelets from the patient’s own blood. Platelets are the first responders to injury. When injected into the degenerated tendon, they release a host of powerful growth factors (e.g., PDGF, TGF-β, VEGF). These signaling molecules orchestrate the healing process by:
    • Attracting stem cells to the site of injury.
    • Stimulating the formation of new blood vessels (angiogenesis), which improves nutrient delivery and waste removal.
    • Promoting the synthesis of new, healthy collagen fibers, which are the building blocks of the tendon.
  • Prolotherapy: Prolotherapy solutions, typically containing dextrose (a sugar), work by creating a controlled, localized inflammatory response. This “therapeutic inflammation” essentially tricks the body into recognizing the old, chronic injury as a new, acute one. This re-ignites the healing cascade (inflammation -> proliferation -> remodeling) that had previously stalled. While effective, prolotherapy is generally less potent than PRP and may require more treatment sessions (e.g., 6-8 weekly or bi-weekly treatments) to achieve comparable results.

By targeting the Achilles tendon with these regenerative techniques, we are not just masking pain; we are fundamentally changing the tissue at a cellular level. We are transforming a weak, degenerated, and tight tendon into a stronger, more flexible, and healthier one. This, in turn, eliminates abnormal tensile forces on the plantar fascia, allowing it to heal.

Integrating Chiropractic Care for Comprehensive Recovery

While this injection protocol is a powerful tool, it is most effective when integrated into a comprehensive rehabilitation program. This is where the principles of chiropractic and functional medicine become indispensable. As a chiropractor, my focus extends beyond the injection site to the entire musculoskeletal system.

Chiropractic care plays a pivotal role in post-procedure recovery and long-term prevention. The goal is to correct the underlying biomechanical faults that may have contributed to the development of Achilles tendinosis in the first place.

Restoring Proper Joint Mechanics

  • Foot and Ankle Adjustments: After an injury and a period of altered gait (limping), the 26 bones of the foot and ankle can become misaligned and restricted. I perform specific chiropractic adjustments to the subtalar joint, talonavicular joint, and other intertarsal joints. Restoring proper mobility in these joints is critical for re-establishing the foot’s natural shock-absorbing capabilities and ensuring the windlass mechanism functions correctly.
  • Knee, Hip, and Sacroiliac Adjustments: The kinetic chain is a two-way street. A problem in the foot can cause compensations that lead to dysfunction in the knee, hip, and pelvis. Conversely, a primary misalignment in the sacroiliac joint or lumbar spine can alter a person’s gait, placing abnormal stress on the foot and ankle. A full-spine and extremity assessment is crucial. By ensuring the entire kinetic chain is moving freely and in alignment, we reduce compensatory stress on the healing Achilles tendon and plantar fascia.

Rehabilitation and Patient Education

The recovery process doesn’t end in the clinic. Active patient participation is essential.

  • The Post-Injection Boot: Immediately following the procedure, patients are typically placed in a walking boot for a few days. The purpose of the boot is to immobilize the ankle and offload the newly treated tendon, protecting it from excessive strain during the initial, critical phase of inflammation and healing.
  • Controlled Stretching: After about three days, the patient can begin a gentle and controlled calf stretching program. This must be done correctly. The goal is not to aggressively stretch the foot but to apply a long-duration, low-load stretch to the gastrocnemius and soleus muscles. This helps to remodel the new collagen fibers in the tendon in a lengthened, more functional alignment.
  • Strengthening Exercises: As healing progresses, we introduce eccentric strengthening exercises for the calf muscles. Eccentric contractions (where the muscle lengthens under load, such as slowly lowering your heels off a step) are particularly effective for treating tendinopathies. These exercises stimulate collagen production and improve the tensile strength of the tendon.
  • Gait Analysis and Orthotics: We assess the patient’s walking and running patterns to identify any persistent biomechanical flaws, such as overpronation. In some cases, custom-molded orthotics may be recommended to provide appropriate arch support and correct foot posture, preventing future recurrence.

This integrative approach is the hallmark of our practice. The targeted regenerative injection, performed under the medical direction of Dr. Cardenas, addresses the pathology at the cellular level. The chiropractic adjustments restore the foundational biomechanical framework. And the guided rehabilitation program rebuilds strength and function. It’s this synergy that leads to lasting results.

Conclusion: A New Hope for Heel Pain Sufferers

The traditional approach to plantar fasciitis has left countless individuals in a cycle of pain, frustration, and disability. The paradigm shift toward treating the Achilles tendon as the primary driver of the condition offers a new, more effective path forward. This anatomy-driven, evidence-based protocol, which I have seen succeed time and time again in my clinical practice over the last decade, represents a significant advancement in the management of chronic heel pain.

By understanding that the plantar fascia is often the “victim” of dysfunction higher up the kinetic chain, we can redirect our therapeutic efforts to the root cause: Achilles tendinosis. Through precise, regenerative injections aimed at healing the tendon, we can release the chronic tension that damages the foot.

When this powerful intervention is combined with holistic chiropractic care to restore biomechanical integrity and a structured rehabilitation program to rebuild strength, we create an environment where the body can truly heal itself. This integrative model, championed by our collaborative team at Injury Medical Clinic PA, provides a comprehensive solution that not only alleviates pain but restores function and offers a genuine opportunity for a pain-free life. If you have been struggling with chronic heel pain, know that there is hope and there are better options available.

References and Further Reading

  1. Ahmad, J., & Jones, K. J. (2014). Insertional Achilles Tendinopathy. JBJS Reviews, 2(12), e3. https://doi.org/10.2106/JBJS.RVW.N.00032
  2. Carcia, C. R., Martin, R. L., Houck, J., & Wukich, D. K. (2010). Achilles Pain, Plantar Fasciitis, and Related Pathology. Journal of Orthopaedic & Sports Physical Therapy, 40(9), A1-A26. https://doi.org/10.2519/jospt.2010.0305
  3. Cheung, J. T., An, K. N., & Zhang, M. (2006). Consequences of partial and total plantar fascia release: a finite element study. Foot & Ankle International, 27(2), 125-132. https://doi.org/10.1177/107110070602700208
  4. de Vos, R. J., Weir, A., van Schie, H. T., Bierma-Zeinstra, S. M., Verhaar, J. A., Weinans, H., & Tol, J. L. (2010). Platelet-rich plasma injection for chronic Achilles tendinopathy: a randomized controlled trial. JAMA, 303(2), 144-149. https://doi.org/10.1001/jama.2009.1986
  5. Martin, R. L., Davenport, T. E., Reischl, S. F., McPoil, T. G., Matheson, J. W., Wukich, D. K., … & Godges, J. J. (2014). Heel pain—plantar fasciitis: revisión 2014. Journal of Orthopaedic & Sports Physical Therapy, 44(11), A1-A33. https://doi.org/10.2519/jospt.2014.0303
  6. Rabago, D., & Nourani, B. (2017). Prolotherapy for Musculoskeletal Pain. PM&R: The Journal of Injury, Function, and Rehabilitation, 9(9S), S230-S238. https://doi.org/10.1016/j.pmrj.2017.06.012
  7. Sampson, S., Gerhardt, M., & Mandelbaum, B. (2008). Platelet-rich plasma injection grafts for musculoskeletal injuries: a review. Current Reviews in Musculoskeletal Medicine, 1(3-4), 165–174. https://doi.org/10.1007/s12178-008-9032-5
  8. Young, C. C., Rutherford, D. S., & Niedfeldt, M. W. (2001). Treatment of plantar fasciitis. American Family Physician, 63(3), 467-474. https://www.aafp.org/pubs/afp/issues/2001/0201/p467.html

SEO Tags: Plantar Fasciitis Treatment, Heel Pain Relief, Achilles Tendinosis, Dr. Alex Jimenez, Dr. Maria Cardenas, Integrative Chiropractic Care El Paso, PRP for Achilles, Prolotherapy for Heel Pain, Regenerative Medicine, Functional Medicine, Chronic Heel Pain, Calf Tightness and Foot Pain, Biomechanics of the Foot, Non-Surgical Heel Pain Solution, Injury Medical Clinic, El Paso Chiropractor, Musculoskeletal Health, Windlass Mechanism, Tendinopathy Treatment, Personal Injury Care

Integrative Peptides for Hair Restoration and Health

Integrative Peptides for Hair Restoration and Health

Evidence-Based Integrative Peptides, Hair Restoration, Weight Optimization, and Chiropractic Care: A Practical, Patient-Centered Guide From My Clinic in El Paso, Texas

Abstract

In this educational post, I walk you through a clear, first-person journey across modern, evidence-based strategies that we use in my clinic for musculoskeletal healing, skin and hair restoration, metabolic health, and sexual wellness. I explain the differences between peptides and bioregulators, the physiology behind repair and regeneration, and why delivery systems are relevant for bioavailability. We review current findings on agents such as BPC-157, GHK-Cu, GLP-1/GIP agonists, mitochondrial exercise mimetics, PRP microneedling, exosomes, and topical aesthetics like SNAP-8, and I explain how these fit safely within our multidisciplinary model. And we look at how integrative chiropractic care complements peptide signaling and regenerative procedures by optimizing biomechanics, autonomic balance, and adherence.

Integrative Peptides for Hair Restoration and Health

About Our Multidisciplinary Team and Care Model in El Paso, Texas

I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. At Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, we operate a collaborative, integrative model common in injury and functional care clinics: an MD provides medical direction alongside a chiropractor.

  • Medical direction and collaboration: Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933) serves as our medical director and collaborative physician. With over 40 years of internal medicine experience, Dr. Cardenas provides medical oversight, safety review, protocol alignment, and governance of prescription-based therapies.
  • Integrative chiropractic care: I lead musculoskeletal diagnostics, spinal and extremity adjustments, neuromuscular rehabilitation, and functional medicine protocols that address sleep, stress, nutrition, and inflammation.
  • Coordinated services: We integrate chiropractic care, internal medicine oversight, functional medicine, personal injury care, rehabilitation, and regenerative adjuncts (PRP, exosomes, body-contouring lasers, topical peptides) in patient-centered pathways.

Why Integrative Chiropractic Care Belongs in Regenerative and Metabolic Programs

I view chiropractic care as the mechanical foundation that allows biochemical tools to work optimally. Pain and dysfunctional mechanics alter autonomic tone, perfusion, and inflammatory signaling, which in turn can blunt the benefits of peptides or PRP. By restoring joint motion, neuromuscular control, and breathing mechanics, we create a hospitable environment for repair.

  • Biomechanics and perfusion: Precise adjustments and soft-tissue work improve mechanotransduction, guiding fibroblasts, tenocytes, and chondrocytes to lay down well-organized collagen while enhancing regional microcirculation (Wang, 2006).
  • Autonomic regulation: Reducing sympathetic overdrive with cervicothoracic modulation and breathwork supports vasomotor balance, skin barrier function, and scalp microenvironment for hair growth (Sicurella et al., 2019).
  • Pain modulation and adherence: Lower pain improves sleep quality, exercise adherence, and consistent dosing of peptide/topical regimens—a key driver of outcomes.

From my clinical observations reported at sciatica.clinic and on my professional LinkedIn profile, patients integrating chiropractic care into metabolic, hair, and skin protocols show stronger adherence, better functional capacity, and faster recovery trajectories, particularly in radicular pain and postural strain pathways.

Understanding Peptides and Bioregulators: Size, Signaling, and Clinical Meaning

I teach patients and clinicians to distinguish between peptides and bioregulators because size and structure shape biology.

  • Key distinctions
    • Peptides: Typically 2–40 amino acids in the U.S. literature (up to 50 in some European sources).
    • Bioregulators: Ultra-short chains (often 2–4 amino acids) capable of entering cells and sometimes the nucleus to influence transcription.
  • Mechanisms of action
    • Peptides often bind cell-surface receptors, triggering cascades like MAPK, PI3K/Akt, cAMP/PKA to modulate regeneration and homeostasis (Fosgerau & Hoffmann, 2015; Lau & Dunn, 2018).
    • Bioregulators may alter gene expression and epigenetic patterns for tissue-specific adaptation (Khavinson & Linkova, 2016).
  • Endogenous versus exogenous
    • GHK-Cu is an endogenous copper tripeptide found in plasma and saliva that supports antimicrobial defense, angiogenesis, and extracellular matrix remodeling (Pickart & Margolina, 2018).
    • BPC-157 is derived from gastric peptides, synthesized for purity and dosing, and studied preclinically for endothelial protection and nitric oxide pathway modulation (Sikiric et al., 2018).

Why this matters clinically: In musculoskeletal repair, receptor signaling and transcriptional nudges complement graded mechanical loading and neuromuscular reeducation. Cellular cues are necessary but insufficient without proper biomechanics; chiropractic adjustments align those mechanical inputs.

Safety, Unknowns, and Risk Interpretation

We proceed with caution, transparency, and oversight.

  • Lock-and-key specificity: Peptides tend to be more targeted than many small molecules, limiting off-target effects, but risk relates to receptor distribution and downstream signaling (Kumar & Purohit, 2018).
  • The meaning of “unknown”: When regulators label risks as unknown, it signals insufficient human RCTs rather than proof of safety or harm. We distinguish biological plausibility and preclinical data from clinical proof, using shared decision-making and MD oversight.
  • Historical context: Peptide therapeutics date back to insulin in 1922; modern pipelines include hundreds of peptide drugs (Fosgerau & Hoffmann, 2015; Lau & Dunn, 2018).

Our safeguards:

  • Thorough inclusion/exclusion criteria and medical screening.
  • Chain-of-custody, documentation, and third-party testing for purity and contaminants.
  • Slow titration, symptom tracking, and route alignment with regulatory status and scope.
  • Close MD oversight for off-label or adjunctive uses.

The Physiology of Repair: Why Peptide Science Fits Integrative Chiropractic

After injury, tissues progress through hemostasis, inflammation, proliferation, and remodeling. Proper joint alignment and neuromuscular control optimize mechanotransduction, directing cellular repair and collagen orientation (Wang, 2006).

  • GHK-Cu enhances ECM turnover and angiogenesis, supporting dermal and musculoskeletal remodeling (Pickart & Margolina, 2018).
  • BPC-157 influences endothelial protection and NO signaling; preclinical models suggest tendon/ligament support (Sikiric et al., 2018).
  • Our roles: I restore biomechanical efficiency; Dr. Cardenas stabilizes systemic contributors (glycemic control, vascular health, inflammation). Together, we align mechanical inputs and biochemical signaling.

Delivery Matters: Oral, Topical, and Transdermal Strategies

Peptides face gastric proteolysis and mucosal barriers. We match delivery to the molecule and the target.

  • Oral delivery
    • Enteric coatings bypass gastric acid to release in the small intestine (Shen et al., 2015).
    • Trehalose stabilization and lyophilization can preserve structure.
    • Permeation enhancers used judiciously may transiently increase paracellular transport (Maher et al., 2019).
  • Topical and cosmetic routes
    • GHK-Cu is well supported in topical/dermocosmetic contexts. We avoid parenteral routes for non–FDA-approved indications and leverage skin-delivery or oral strategies where appropriate (Pickart & Margolina, 2018).
  • Transdermal adjuncts for PRP/exosomes
    • Iontophoresis and electroporation help drive actives through the stratum corneum when needling is limited, complementing PRP microneedling and post-procedure recovery (Fabbrocini et al., 2019; Singh et al., 2020).

Spotlight on Key Peptides and Bioregulators We Use

  • Musculoskeletal support: BPC-157 and GHK-Cu
    • Proposed actions: endothelial protection, NO modulation, collagen synthesis, ECM alignment.
    • Clinical pairing: graded loading, eccentric programming, chiropractic adjustments, and modalities like shockwave or laser for tendon/ligament repair.
  • Mitochondrial exercise mimetics
    • Tools targeting NAD+ pools, AMPK, PGC-1α aim to boost ATP synthesis, biogenesis, and oxidative resilience (Lautenschlager et al., 2021).
    • We use these as bridges for deconditioned or metabolically burdened patients, not replacements for real exercise. Mechanotransduction from training is irreplaceable.
  • Neurocognitive bioregulators
    • Short-chain bioregulators investigated for neurogenesis, myelin support, and sleep/circadian balance (Khavinson & Linkova, 2012).
    • Agents like semax/selank are discussed in the literature for attention, mood, and anxiolysis with intranasal routes (Perevalova et al., 2023; Dolotov et al., 2010). We screen psychiatric history, drug interactions, and sleep considerations.
  • GLP-1/GIP-based metabolic support
    • GLP-1 RAs improve glycemic control, appetite, and weight outcomes with cardiometabolic benefits (Wilding et al., 2021).
    • We titrate doses conservatively to minimize GI side effects and preserve lean mass, pairing therapy with resistance training, adequate protein intake, and mitochondrial support.
    • Dual agonists (e.g., tirzepatide) and emerging triple agonists are considered within evolving evidence for enhanced adiposity and energy expenditure control (Jastreboff et al., 2022; Shao et al., 2023).

Aesthetic Skin Rejuvenation: PRP Microneedling, PDRN, and Topical Peptides

Patients value clear timelines and visible milestones. We combine immediate cosmetic effects with biologically durable changes.

  • PRP microneedling creates microchannels; platelets release PDGF, VEGF, and TGF-β, stimulating fibroblasts, collagen I/III deposition, angiogenesis, and controlled remodeling (Fabbrocini et al., 2019; Singh et al., 2020).
  • PDRN formulations, inspired by nucleic acid trophic signaling, support dermal repair and collagen synthesis post-procedure.
  • Topical neuromodulators like SNAP-8 (Acetyl Octapeptide-3) can smooth fine lines by modulating SNARE-mediated neurotransmitter release in expression lines, offering immediate visual improvements while deeper remodeling proceeds (Alves & Campos, 2020).

Hair Restoration: Physiology, PRP/Exosomes, and Copper Peptides

Hair cycling moves through telogen, anagen, and catagen phases. Our protocols aim to shorten telogen and extend anagen.

  • PRP and exosomes: Growth factors and vesicles modulate dermal papilla signaling and pathways like Wnt/β-catenin, accelerating anagen re-entry and improving density over weeks (Gupta & Carviel, 2019; Zhao et al., 2020).
  • GHK-Cu derivatives: Copper peptides support angiogenesis, anti-inflammatory balance, and matrix integrity; clinically, patients report stronger shafts and improved scalp health (Pickart & Margolina, 2018).
  • Clinical timing: Early sprouts can appear in 2–4 weeks after injections. We schedule 2–3 rounds over 6–9 months for meaningful density and caliber changes, often reducing the need for transplantation when adherence is high.

Metabolic Weight Optimization: GLP/GIP Strategies, Amylin Synergy, and Rehab

We design tiered strategies and keep doses low but effective to reduce side effects.

  • Tiered approach
    • Good: weekly semaglutide.
    • Better: weekly tirzepatide (GLP-1/GIP dual agonist).
    • Best: emerging triple agonists under investigation.
  • Why weekly in-clinic injections
    • Safety: Sterile reconstitution and site rotation lower risk.
    • Compliance: Real-time titration and side-effect mitigation.
    • Adjuncts: Red light panels for incremental skin tightening and coordinated rehab for lean mass preservation.
  • Layering levers
    • Amylin agonists (e.g., cagrilintide/pramlintide profiles) improve satiety and can match high-dose GLP efficacy through mechanism diversification (Smith & Finan, 2023).
    • Lipotropics and mitochondrial supports (e.g., MitoQ, SS-31-like approaches) improve fatty acid transport and oxidative capacity (Murphy & Smith, 2020; Szeto, 2014).
  • Chiropractic fit
    • Adjustments reduce pain barriers; neuromuscular reeducation reinforces safe movement patterns for resistance training—the strongest tool to protect lean mass during a caloric deficit.

Regulatory Pathways, Safety Infrastructure, and Ethical Access

We adhere to U.S. frameworks for cosmetics and supplements while distinguishing FDA-approved medications.

  • MOCRA (cosmetics) and DSHEA (dietary supplements) define non-drug pathways when disease claims are avoided (U.S. FDA, 2022; U.S. FDA, 2023).
  • We emphasize third-party testing, lot documentation, and chain of custody.
  • For self-injection scenarios, we use a competency checklist, first-dose in-office supervision, and pre-metered syringes to protect patients and staff.
  • We provide WADA disclosures for athletes, tailored informed consents for each route, and ongoing lab monitoring (e.g., A1c, fasting insulin, lipids, hs-CRP, CMP) under Dr. Cardenas’s oversight.

Clinical Observations From Practice: Radicular Pain and Desk-Athlete Strain

From my sciatica practice observations at sciatica.clinic and professional case narratives on LinkedIn:

  • Sciatica pathways: L4–S1 radicular patterns often present with hip abductor weakness and thoracolumbar junction stiffness. After restoring hip hinge mechanics and lumbar motion, nerve mechanosensitivity declines; with improved microcirculation and sensible loading, endothelial-supportive adjuncts correlate with faster return to walking tolerance and better sleep.
  • Desk-athlete syndrome: Cervicothoracic dysfunction, forward-head posture, and scapular dyskinesis benefit from joint mobilization, deep neck flexor training, and posterior-chain reconditioning. When elasticity or fascial glide lags, ECM-supportive peptides plus hydration and collagen-rich nutrition accelerate perceived recovery and resilience.

Take-Home Principles for Patients and Clinicians

  • Peptides and bioregulators are tools, not cures: They amplify innate repair when paired with sleep, nutrition, and graded loading.
  • Chiropractic meets cell biology: Adjustments restore mechanical inputs; peptides refine the biochemical milieu, together creating durable tissue change.
  • Medical oversight matters: With Dr. Cardenas directing medical aspects, we ensure appropriate screening, dosing, and monitoring—especially for metabolic and neurocognitive applications.
  • Evidence evolves: Where data are robust (e.g., GLP-1 RAs), we follow best practice. Where evidence is emerging, we proceed cautiously, transparently, and with informed consent.
LLT Laser Therapy for Periphearl Neuropathy  |  El Paso, TX (2019)

References

Regenerative Medicine and Recovery for Musculoskeletal Health

Regenerative medicine for musculoskeletal health offers groundbreaking treatments for injury recovery and maintaining joint function.

Abstract

I am Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. In this comprehensive educational post, I guide you through an integrated, evidence-based journey that unites cutting-edge regenerative medicine, integrative chiropractic care, and functional medicine within a medically directed, multidisciplinary clinic. Drawing on landmark research and clinical trials, I translate complex biology into clear, actionable concepts: how mesenchymal stem cells (MSCs) and secretomes/exosomes modulate inflammation, promote tissue repair, and remodel fibrosis; why umbilical cord tissue and menstrual-derived stem cells possess unique youthful, antifibrotic signatures; how paracrine signaling and microRNA rapidly downshift inflammatory cascades; and how clinical protocols—from joint injections to pelvic floor neuromuscular rehabilitation, long COVID care, and personal injury recovery—are designed and delivered safely.

This post also details our integrative, team-based model at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where I collaborate with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI 1164426749; Texas MD License J2933), our Medical Director and Collaborative Physician. Together, we unify chiropractic care, medical oversight, functional medicine, rehabilitation, personal injury documentation, allergy testing and immunotherapy, and noninvasive pelvic floor therapies. Across sections, I present my clinical observations from Sciatica Clinic and my professional platform, connecting physiology to protocols and protocols to outcomes. The integrated narrative includes APA-7 in-text citations and a hyperlinked reference list, with bold highlights and SEO-optimized titles.

Integrative Regenerative Medicine and Interdisciplinary Care in El Paso: Who We Are and How We Work

I practice at Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, in El Paso, Texas. Our clinic is deliberately built as a multidisciplinary, medically directed environment because modern musculoskeletal and systemic conditions rarely live in silos.

  • Medical Direction: Dr. Maria Guadalupe Cardenas, MD, a board-certified internist with over 40 years of experience (NPI 1164426749; Texas MD License J2933), serves as our Medical Director and Collaborative Physician. Her internal medicine governance ensures safety, diagnostic clarity, and alignment with evidence-based medical standards.
  • My Role: I am Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. I provide integrative chiropractic care, functional medicine evaluation, regenerative protocol design, and rehabilitation planning. My chiropractic lens focuses on biomechanics, neuromuscular timing, autonomic tone, and functional restoration.
  • Team Integration:
    • Chiropractic: Precise spinal and extremity adjustments, soft tissue strategies, neuromuscular re-education, corrective exercise, ergonomic coaching.
    • Internal Medicine Oversight: Risk stratification, comorbidity management (diabetes, cardiovascular disease, autoimmune disorders), medication safety, imaging decisions, and escalation pathways.
    • Functional Medicine: Anti-inflammatory nutrition, gut–immune–brain axis modulation, sleep and stress strategies, metabolic optimization.
    • Regenerative Medicine: Orthobiologics (HCT/Ps), exosome/secretome-based support, injection strategies, dosing, safety protocols.
    • Personal Injury: Objective documentation, imaging correlation, impairment ratings, coordinated conservative rehabilitation, and medico-legal clarity.
    • Rehabilitation: Phased strengthening, mobility restoration, proprioceptive retraining, gait and return-to-function plans.
    • Ancillary Programs: Pelvic floor neuromuscular rehabilitation (HIFEM-based), allergy testing and immunotherapy (SCIT/SLIT), ultrasound-guided procedures, photobiomodulation, shockwave therapy, PEMF.

Why a multidisciplinary model? Because patients present with layers: joint pain plus metabolic inflammation; spine dysfunction plus sleep disruption; pelvic floor weakness plus low back pain; sciatica plus anxiety after trauma; allergic triggers plus cervicogenic headaches. The integrated structure lets us address physiology from multiple angles—mechanics, chemistry, and context—to accelerate recovery and protect long-term function.

A New Era in Regenerative Medicine: From Symptom Suppression to Biological Repair

Why Traditional Approaches Often Fall Short

Conventional musculoskeletal care has often relied on NSAIDs and corticosteroid injections to control pain and inflammation. While these may offer short-term relief, they can be catabolic, impair tendon integrity, accelerate cartilage breakdown, and suppress the body’s innate healing response (Caplan, 2007; Caplan & Correa, 2011). Long-term NSAID use also carries risks: gastrointestinal bleeding, renal compromise, and increased cardiovascular events. Clinically, we view these as bridging tools rather than destinations—used judiciously to reduce acute pain while preparing for restorative interventions.

Regenerative Medicine and Orthobiologics

Regenerative medicine, especially HCT/Ps and orthobiologics, seeks to change the local environment of injured tissues—from a chronic inflammatory, catabolic state to an immunomodulated, pro-repair, pro-resolution milieu. The therapeutic mechanisms include:

  • Reducing pro-inflammatory cytokines such as TNF-α and IL-1β to calm destructive signaling (Tögel et al., 2005).
  • Shifting immune phenotypes from M1 macrophages (pro-inflammatory) to M2 macrophages (pro-resolving) to enable tissue repair (Caplan & Correa, 2011).
  • Neurotrophic support to soothe irritated nerves and reduce neurogenic inflammation; microRNA within exosomes can quickly modulate pain-associated pathways.
  • Paracrine signaling (secretome): stem cell products act like chief supervisors, secreting growth factors, cytokines, chemokines, mRNA, and microRNA to recruit and instruct local repair cells to proliferate and differentiate appropriately (Pittenger et al., 1999).

In our clinic, we emphasize precise anatomic targeting, dose integrity, and environmental preparation (functional medicine-driven anti-inflammatory support, sleep optimization, glycemic stability) to improve responsiveness.

The Five Stages of Biological Regeneration: Setting Realistic Timelines and Expectations

Regeneration unfolds across months, not days. I counsel patients to celebrate early relief but respect the biology:

  • Stage 1: Inflammation and Signaling (weeks 0–3)
  • Anti-inflammatory molecules quiet the area while paracrine signals recruit native repair cells. Patients often feel better quickly—this is the immunomodulatory effect (Tögel et al., 2005).
  • Stage 2: Proliferation (weeks 2–6)
  • Recruited cells multiply, increasing the local workforce.
  • Stage 3: Differentiation (weeks 6–12)
  • Cells specialize into chondrocytes, tenocytes, or osteoblasts depending on local cues (Pittenger et al., 1999).
  • Stage 4: Tissue Formation (months 3–6)
  • New collagen and matrix are laid down but initially weak and disorganized.
  • Stage 5: Remodeling and Maturation (months 6–12+)
  • Angiogenesis (VEGF-driven), collagen alignment and cross-linking strengthen tissue to endure physiologic loads.

Clinically, I remind patients: early pain relief is not structural completion. Resist overloading too soon—avoid the “break your stitches” error.

Aging, MSC Decline, and the Rationale for “Younger” Donor Sources

Dr. Arnold Caplan’s seminal data demonstrated that bone marrow MSCs decline dramatically with age—approximately 1 in 10,000 cells at birth; 1 in 100,000 in adolescence; 1 in 250,000 by the 30s; 1 in 400,000 by the 50s; and 1 in 2,000,000 by the 80s (Caplan, 2007). Fewer cells with more senescent signaling reduce repair efficiency.

This is why umbilical cord tissue and perinatal MSCs (e.g., Wharton’s jelly) are compelling: they are epigenetically young, immunoprivileged, and rich in growth factors and exosomes. They bring robust paracrine medicine to older tissues lacking cellular vigor. Ethical sourcing standards—full-term, healthy births with informed consent—mitigate concerns and align with current regulatory frameworks.

What’s Inside Umbilical Cord-Derived Products: The Regenerative “Elixir”

Key bioactive components include:

  • Medicinal Signaling Cells (MSCs): Orchestrators that modulate immune responses and direct local repair (Caplan & Correa, 2011).
  • Growth Factors: VEGF, PDGF, TGF-β to drive angiogenesis, proliferation, and collagen synthesis (Pittenger et al., 1999).
  • High-molecular-weight hyaluronic acid: Immediate lubrication, shock absorption, and stimulation of synovial HA production—beneficial in osteoarthritic joints.
  • mRNA/microRNA: Genetic instructions and short regulatory strands that disrupt inflammatory transcripts and pivot the molecular environment toward resolution.
  • Cytokines/Chemokines: Anti-inflammatory balance plus homing signals for repair cell recruitment.

We emphasize that regenerative biologics are not panaceas for all disease; they are powerful tools for musculoskeletal, fibrosis, and localized inflammatory conditions under careful medical direction.

The Power of Exosomes and Secretomes: Fast, A-Cellular Signal Delivery

Exosomes are nanometer-sized extracellular vesicles carrying proteins, mRNA, and microRNA from parent cells. Clinically important traits:

  • Rapid anti-inflammatory modulation: MicroRNA inserts into inflammatory transcript workflows—creating “junk code” that halts cytokine production quickly.
  • A-cellular safety: Exosomes do not replicate—reducing theoretical risks associated with live-cell therapies.
  • Small size: They can cross barriers such as the blood–brain barrier, making them valuable in CNS

We often combine cellular products for long-term structural regeneration with exosome-rich products for rapid symptom reduction and immune recalibration.

Integrative Chiropractic Care: Biomechanical Foundation for Durable Outcomes

Regeneration thrives in stable, well-aligned, efficiently loaded joints. My chiropractic role includes:

  • Spinal alignment: Normalizing segmental motion, reducing aberrant load transfer, and improving nerve and autonomic tone.
  • Joint mobilization: Restoring range in peripheral joints to prevent micro-shear that perpetuates catabolic signaling.
  • Soft tissue techniques: ART, Graston, myofascial release to reestablish glide, break adhesions, and improve mechanotransduction.
  • Rehabilitative exercise: Phased programs that retrain movement patterns, strengthen stabilizers, and improve proprioception.

Biomechanics plus biologics is additive: correct the hinges and heal the tissue. Under medical oversight, we time adjustments around regenerative procedures—often allowing several weeks before direct manipulation of treated areas.

Clinical Decision Frameworks: Imaging, Red Flags, and Targeted Injections

Imaging escalation follows red flag pathways:

  • Indications for MRI (with/without contrast):
  • Unexplained weight loss, persistent fevers, night sweats
  • History of malignancy prone to bone metastasis
  • Severe, unremitting pain at rest or night
  • Progressive neurological deficits
  • Infection suspicion (elevated inflammatory markers, immunosuppression)
  • (Bloem et al., 2019; ACR Appropriateness Criteria)

Ultrasound is invaluable for dynamic tendon assessments, surface ligament visualization, bursal, and guided injections—cost-effective, radiation-free, and excellent for procedural precision (Jacobson, 2018).

Diagnostic anesthetic tests (e.g., lidocaine at ligament entheses) clarify pain generators before committing to regenerative dosing. We document dosages, sites, responses, and adverse events while accounting for anticoagulants and medication interactions under internal medicine guidance.

Joint-Specific Strategies: Shoulder, Elbow, Knee, Hip, Ankle

Shoulder: Restore the Soccer-Ball-on-a-Head Mechanic

We combine palpation of SC/AC joints, biceps tendon, rotator cuff insertions with orthopedics (Hawkins-Kennedy, Empty Can, resisted rotations, O’Brien’s). Injections follow a comprehensive map—not just intra-articular—prioritizing primary lesions and peritendinous support. A young athlete may need small targeted volumes; an older patient often requires a larger dose to overcome entrenched inflammation and degenerative changes.

Elbow: Treat the Annular Ligament and Common Extensors

Chronic lateral epicondylitis often hides annular ligament laxity; treat both the common extensor tendon and the annular ligament. Pronating the forearm protects the radial nerve corridor; on the medial side, safeguard the ulnar nerve and identify subluxation risks with arm position.

Knee: The Medial Compartment’s Hidden Players

Examine and treat MCL laxity, pes anserine bursitis/tendinopathy, and patellofemoral tracking. Ultrasound guidance improves precision. Combine intra-articular HA when indicated with periligamentous support. Post-TKA pain is often extra-articular—MCL/LCL micro-laxity, hamstring tendinopathy, pes bursitis, IT band friction, proximal tibiofibular joint dysfunction—treat around hardware while documenting safe needle paths.

Hip: Dose Integrity and Polyaxial Reality

The hip is weight-bearing and multi-planar, so underdosing fails. Use concentrated doses without over-distending the capsule. Treat intra-articular space plus capsular ligaments and peri-tendinous structures. In avascular necrosis, aim to rekindle angiogenesis and halt collapse—target injections under ultrasound and counsel realistic expectations.

Ankle and Morton’s Neuroma: Mechanics First

Ankle ligaments and tendons are accessible and respond well to regenerative injections. Morton’s neuroma requires calming the nerve plus restoring transverse metatarsal ligament stiffness to reduce interdigital compression—the mechanical root cause.

Spine Strategy: SI Joint, Iliolumbar Ligament, and Facet Targets

Low back pain frequently involves lumbopelvic stability deficits:

  • Palpate iliolumbar and SI ligaments; use provocation tests (Gaenslen’s, compression/distraction, thigh thrust).
  • Stabilize with chiropractic adjustments, thoracolumbar fascia work, and gluteal/core strengthening.
  • Perifacet injections deliver regenerative medicines near joint capsules—exosomes act like a smoke grenade that finds inflammation without requiring exact intra-capsular placement.

Cervical spine: do not inject above C2 due to vertebral artery risks; focus on perifacet injections from C2/3 down. Treat superior nuchal line muscle/fascial attachments for cervicogenic headaches—safe, bone-backed terrain.

Safety Protocols: Anticoagulants, Anti-Inflammatory Agents, Cancer History, Chemotherapy

  • Anticoagulants: Hold when safe and appropriate under prescribing physician’s guidance; weigh bleeding risk vs clot risk. Superficial injections may proceed with caution; deeper procedures often require a washout period.
  • NSAIDs/supplements: Stop NSAIDs; hold blood-thinning supplements (curcumin, high-dose omega-3s, ashwagandha) pre-procedure. Oral CBD is paused; topical forms carry less concern.
  • Cancer: For cell-based therapies, we often prefer patients to be cancer-free for ≥5 years; PRP can be considered sooner with imaging verification of no metastasis.
  • Chemotherapy: Ideally, wait ≥2 weeks before and ≥2 weeks after chemo sessions; minimum 1 week post-chemo if clinically necessary.

Internal medicine oversight ensures risk stratification, consent, and safe timing.

Exosomes, Secretomes, and Long COVID: Lessons from ARDS and CNS Delivery

Double-masked randomized trials in severe ARDS and compelling MSC safety data in H7N9 cohorts have shown survival improvements and strong tolerability while CRP plummets (Lanzoni et al., 2021). Because exosomes cross the blood–brain barrier readily, they can modulate neuroinflammation, address brain fog, headaches, and autonomic dysfunction seen in long COVID. Our approach integrates IV and nebulized exosomes, guided by medical direction, with rehabilitative strategies and autonomic balance via chiropractic care.

MicroRNA: Genetic”“Shortcodes” for Rapid Anti-Inflammation

Historically dismissed as “junk,” microRNAs (miRNAs) regulate gene expression. In pain and inflammation, miRNAs can insert into the transcript code, garble messages, and halt cytokine production—explaining the swift pain relief patients report after exosome-rich treatments. We often pair live MSCs (long-term structural regeneration) with exosome supplementation (rapid signal delivery).

Menstrual-Derived Stem Cells and Secretome Therapeutics: Scarless Healing Lessons

The endometrium regenerates monthly without fibrosis. Menstrual-derived stem cells (MSCs/ERCs) show:

  • High proliferative capacity (rapid doubling times)
  • Karyotypic stability through expansions
  • Youthful transcriptional signatures (OCT4, SSEA-4, c-Kit)
  • Active telomerase, resisting replicative senescence

Their secretome skews toward TGF-β3 (anti-scarring), HGF, and prominent MMP activity (e.g., MMP-3, MMP-10) that remodels aberrant collagen. Preclinical and early clinical signals across intrauterine adhesions, ovarian stromal repair, lung ARDS, liver fibrosis, skin/corneal repair, and neurology suggest multi-node antifibrotic and pro-resolution potency (Evans et al., 2019; Cuenca et al., 2018).

Clinical logic: Single-target antifibrotic drugs often underperform amid redundant networks (YAP/TAZ, integrins, LOX/LOXL2, CTGF). A secretome retunes the orchestra—macrophage polarization, pro-resolving mediators, elastogenesis, MMP-driven matrix clean-up, and angiogenesis—to break the stiffness loop.

Fibrosis: Why Mechanotransduction and Stiffness Must Be Addressed Systemically and Locally

Fibrosis is a maladaptive wound-healing program marked by myofibroblast activation, stiff ECM, and feedback via mechanotransduction (integrins, YAP/TAZ, FAK, Rho/ROCK) (Dupont et al., 2011). Clinically, we must:

  • Reduce stiffness signals biomechanically (chiropractic alignment, soft tissue mobilization, posture, load management).
  • Shift immune tone (functional medicine anti-inflammatory diets, sleep, autonomic balance).
  • Deliver secretome or exosome support to recalibrate matrix synthesis, break pathological cross-links, and enhance elastin.

Secretome-informed strategies are considered under medical guidance, often paired with functional prehabilitation, metabolic stabilization, and rehabilitation to maintain gains.

Pelvic Floor Neuromuscular Rehabilitation: Supramaximal Contractions via HIFEM

Many men and women suffer silent pelvic floor dysfunction—incontinence, sexual dysfunction, pelvic heaviness, low back pain. Kegels often fail due to execution errors, muscle imbalance, or insufficient intensity. High-intensity focused electromagnetic (HIFEM) therapy:

  • Induces supramaximal contractions by bypassing voluntary limits, forcing deep remodeling (hypertrophy, hyperplasia).
  • Sessions (~28 minutes) deliver thousands of perfect-form contractions with built-in lactic acid clearance patterns.
  • Patients remain fully clothed, with no downtime.

Our integrated pathway:

  • Screening by Dr. Cardenas (contraindications: electronic implants, metallic pelvic devices, pregnancy, recent surgeries).
  • Chiropractic evaluation for lumbopelvic mechanics; address SI joint alignment, thoracolumbar fascia, and gluteal chains.
  • Phased protocols: Typically six sessions (twice weekly for three weeks), plus corrective exercise and functional medicine support for hormones and inflammation.

Outcome: Restored continence and core stability, reduced low back strain, improved athletic function. Maintenance sessions sustain gains.

Allergy Testing and Immunotherapy (SCIT/SLIT): Weekly Clinic Rhythm with Medical Oversight

Many of our patients benefit from an in-office allergy program integrated into their weekly chiropractic visits.

  • Percutaneous scratch testing: Timed 15 minutes; results in ~5 minutes; typically covered by many insurers.
  • SCIT (subcutaneous immunotherapy): 3–5-year protocols, in-clinic monitoring.
  • SLIT (sublingual immunotherapy): At-home convenience, strong safety in low-risk populations; internal medicine oversight manages indications, contraindications, and escalation protocols.

Physiology: Immunotherapy retrains immunity—tilting away from Th2 dominance, increasing Treg activity, reducing specific IgE, and elevating blocking IgG4—leading to fewer symptoms and less medication reliance over time (Agache et al., 2019; Canonica et al., 2014).

Chiropractic complements airway health via thoracic mobility, diaphragm function, and autonomic modulation; functional medicine reduces systemic inflammatory load and supports gut barrier integrity.

Personal Injury Integration: Whiplash, Central Sensitization, and Proprioceptive Recovery

Whiplash-associated disorders induce rapid capsular ligament strains, subfailure injuries, and mechanoreceptor disruption—driving instability and altered motion patterns (Bogduk, 2011). The biochemical cascade (prostaglandins, bradykinin, histamine, Substance P, CGRP) lowers nociceptor thresholds and can progress to central sensitization via glutamate/NMDA pathways.

Our integrated approach:

  • Internal medicine screens for red flags, oversees short-term pharmacology when necessary.
  • Chiropractic adjustments re-normalize segmental motion and gate pain via A-beta input and descending inhibition (Pickar, 2002; Coronado et al., 2012).
  • Functional medicine cools systemic inflammation (omega-3s, curcumin, sleep, anti-inflammatory diets), supports mitochondrial repair (CoQ10, ALA, L-carnitine) to power collagen synthesis.
  • Rehabilitation restores proprioception (PNF), core control (DNS principles), and kinetic chain integration.
  • Documentation: Impairment ratings (AOMSI via CRMA), neurological testing, and validated outcomes for medico-legal accuracy (Rondinelli et al., 2008).

Functional Medicine: Anti-Inflammatory Nutrition, Sleep, and Glycemic Control

Healing capacity depends on nutrition, sleep, glycemic stability, and stress physiology. We emphasize:

  • Anti-inflammatory diets: Mediterranean-style patterns, omega-3s, polyphenol-rich foods (Calder, 2020).
  • Protein sufficiency: 1.2–1.6 g/kg/day during rehab phases to support collagen and muscle repair—adjusted for renal status.
  • Micronutrients: Vitamin D, magnesium, zinc, vitamin C, B vitamins to support nerves, immune function, and tissue synthesis.
  • Sleep optimization: Enhances glymphatic clearance (Nedergaard, 2013; Plog & Nedergaard, 2018).
  • Gut–immune balance**: Address SIBO/SIFO, repair intestinal permeability, reduce LPS burden to downshift neuroinflammation (Pimentel et al., 2020; Erdogan & Rao, 2015).

Glymphatic System and Neuroinflammation: Brain Health Essentials

The glymphatic system clears metabolic waste (amyloid-beta, tau) primarily during sleep, driven by AQP4 on astrocytic end-feet and arterial pulsatility (Nedergaard, 2013; Plog & Nedergaard, 2018). Dysfunction increases neuroinflammation—microglial activation and cytokine storm—and correlates with cognitive symptoms, headaches, and mood changes.

We support brain health via:

  • Sleep hygiene and aerobic exercise to amplify pulsatility.
  • Cervical alignment strategies to normalize CSF hydrodynamics.
  • Anti-inflammatory nutrition and omega-3s (SPMs).
  • Autonomic balance: Chiropractic care tilts toward parasympathetic tone; the vagus nerve’s cholinergic anti-inflammatory pathway reduces cytokine signaling.

Mast Cell Activation Syndrome (MCAS): Soothe, Stabilize, Solve

MCAS is characterized by hyper-reactive mast cells that degranulate excessively—driving hives, GI upset, tachycardia, dizziness, headaches, brain fog, fatigue (Afrin et al., 2017; Skaper et al., 2018). Our three-step model:

  • Soothe: H1/H2 blockers, quercetin, vitamin C; symptom relief.
  • Stabilize: Cromolyn sodium, PEA, luteolin; low-histamine diet; DAO enzyme support for histamine intolerance.
  • Solve: Gut repair (5R model), treat SIBO/SIFO, reduce toxin load, autonomic balance with chiropractic care.

Internal medicine oversight coordinates medications, screens comorbidities, and monitors contraindications.

SIBO/SIFO: Migrating Motor Complex and Location Matters

SIBO (hydrogen-, methane-, hydrogen sulfide-dominant) and SIFO (Candida) are overgrowths in the small intestine, driving bloating, pain, malabsorption, leaky gut, and systemic inflammation (Pimentel et al., 2020; Erdogan & Rao, 2015).

Our phased approach:

  • Weed: Prescription antibiotics (rifaximin ± neomycin/metronidazole) or herbal antimicrobials (berberine, oregano oil, allicin, neem, caprylic acid).
  • Seed & Feed: Gut lining repair (L-glutamine, zinc carnosine), cautious probiotic reintroduction, prebiotics as tolerated.
  • Maintain: Stimulate migrating motor complex (MMC) with prokinetics (pharmaceutical or ginger/artichoke extract/5-HTP), optimize stomach acid, address adhesions, ensure ileocecal valve competence.

Chiropractic supports vagal tone, balances sympathetic overdrive, and normalizes lumbar/pelvic mechanics that influence GI motility.

Evidence-Based Chiropractic: Conservative First-Line Care for Spine Pain

Guidelines from the American College of Physicians and major systematic reviews emphasize noninvasive, conservative care for low back pain, including spinal manipulation, exercise, multimodal rehabilitation, and cognitive and lifestyle strategies (Qaseem et al., 2017; Colter et al., 2018; Paige et al., 2017; Bussières et al., 2018; Hayden et al., 2021).

Chiropractic adjustments modulate mechanoreceptors, reduce muscle guarding, influence descending inhibitory pathways, and restore mobility—making active rehabilitation more effective.

Clinical Observations and Patient Journeys

From my practice and Sciatica Clinic:

  • Sciatica: Iliolumbar and SI ligament contributions recur; when stabilized, maintenance visit frequency drops and exercise adherence rises.
  • Knee pain with clean X-rays: Ultrasound often reveals pes anserine bursitis or MCL thickening; targeted treatments yield faster relief than intra-articular-only strategies.
  • Rotator cuff partial tears: Scapular mechanics plus injections and posterior capsule work produce durable improvements over 8–12 weeks.

I also emphasize clear care plans, reassessment, and patient education. Clinical certainty is built on listening, examination, diagnostics, guideline-informed reasoning, and knowing when to refer.

More clinical narratives and ongoing cases:

Leadership, Communication, and Accountability in Care Delivery

Patients seek certainty, not sales. They need to know:

  • What is wrong, why it hurts, how we will help, and how progress will be measured.
  • The difference between short-term relief and long-term functional restoration.

Our systems incorporate:

  • Better questions (e.g., patient-centered visioning for outcomes).
  • Better offers (A/B plan options).
  • Better leadership (clear clinical direction, trained team).
  • Better accountability (on-time scheduling, adherence, reassessments).

We design care maps showing how chiropractic, medical oversight, functional medicine, rehab, and regenerative strategies interact.

Practical Protocol Highlights: Dosing, Targeting, and Outcome Tracking

  • Dose integrity: Do not dilute limited biologics across too many sites. Prioritize the dominant pain generator.
  • Targeting: Use ultrasound/fluoroscopy for accuracy; save images in the record.
  • Outcome tracking: WOMAC, Oswestry, NDI, pain scales, range-of-motion, strength metrics at 2, 6, 12, 24 weeks.
  • Staged care: Address areas sequentially to maintain dose strength and evaluate responsiveness.

Bringing It All Together: A Patient Journey Example

  • Day 1: Intake, red flag screening, functional metrics, chiropractic exam, medical review by Dr. Cardenas; imaging/ultrasound as indicated.
  • Week 1–2: Calming phase—diagnostic anesthetic tests, initial adjustments to reduce guarding, anti-inflammatory nutritional support.
  • Week 2–6: Regenerative procedure with exosome support if appropriate; rehabilitative progression; sleep and stress strategies; weekly follow-ups.
  • Week 6–12: Strength and endurance phases; gait retraining; nerve mobility as indicated; monitor outcomes and adjust care plan.
  • Month 3–6: Advanced functional tasks; return-to-work/sport planning; maintenance schedules; allergy or pelvic floor programs as needed.
  • Month 6–12: Remodeling phase monitoring; possible booster doses; long-term self-care programming.

Conclusion: Hope, Honesty, and Integrated Excellence

Our mission is to deliver patient-centered, evidence-based care that addresses the whole person. By integrating chiropractic precision, internal medicine oversight, functional medicine, rehabilitation, and regenerative strategies, we provide a safer, clearer, and faster path to function. We do not promise what biology cannot deliver; we do stabilize viable structures, support antifibrotic and pro-resolving pathways, and coordinate surgical care when indicated. The integrative model is not just better medicine—it is better patient experience and better long-term outcomes.

References

SEO tags: integrative chiropractic care, regenerative medicine, mesenchymal stem cells, exosomes, secretome therapy, anti-inflammatory nutrition, pelvic floor rehabilitation, HIFEM supramaximal contractions, allergy testing immunotherapy, SCIT SLIT, long COVID exosomes, glymphatic system sleep, neuroinflammation microglia, mast cell activation syndrome, SIBO SIFO prokinetics, iliolumbar ligament sacroiliac joint, perifacet injections, ultrasound-guided procedures, lumbopelvic stability, personal injury whiplash, central sensitization, biomechanical mechanotransduction, fibrosis antifibrotic secretome, endometrium scarless healing, TGF-beta3 elastin MMP3, internal medicine oversight, Dr Maria Guadalupe Cardenas, Dr Alex Jimenez DC APRN FNP-BC, Injury Medical Clinic PA El Paso, Mission Plaza Injury Medical Clinic, Sciatica Clinic observations, evidence-based spine care

Treating Erectile Dysfunction Through Regenerative Methods

Treating Erectile Dysfunction Through Regenerative Methods

A Comprehensive Guide to Men’s Health: Understanding and Treating Erectile Dysfunction and Low Testosterone

Abstract

Erectile Dysfunction (ED) is a prevalent and multifaceted condition that significantly impacts a man’s quality of life and often serves as a crucial early indicator of underlying cardiovascular disease. Its prevalence increases with age, affecting an estimated 150 million men globally. The causes of ED are diverse, ranging from vasculogenic (related to blood flow), neurogenic (nerve-related), and hormonal to psychogenic factors. While traditional treatments like PDE5 inhibitors (e.g., Viagra, Cialis) offer symptomatic relief, they are often accompanied by side effects and the phenomenon of tachyphylaxis, where effectiveness diminishes over time. This post explores the latest findings in men’s health, focusing on regenerative and restorative therapies that address the root causes of ED. We will delve into innovative treatments such as Extracorporeal Shockwave Therapy (ESWT) and Platelet-Rich Plasma (PRP), which stimulate the body’s natural healing mechanisms to improve blood flow and regenerate tissue. Furthermore, we will examine the critical role of testosterone in male vitality and sexual function, discussing the diagnosis and management of hypogonadism (low testosterone). I will outline the importance of a comprehensive hormonal evaluation before embarking on peptide therapies or other treatments, ensuring a foundation for optimal outcomes. This guide aims to provide a clear, evidence-based journey through modern approaches to men’s health, integrating these advanced therapies within a holistic and personalized care model.

Treating Erectile Dysfunction Through Regenerative Methods


A Multidisciplinary Approach to Men’s Health at Injury Medical Clinic

At Injury Medical Clinic PA, located in El Paso, Texas, we have cultivated a unique and powerful multidisciplinary environment dedicated to comprehensive patient care. Our practice is built on the principle of collaboration, bringing together diverse medical and therapeutic disciplines under one roof to provide a truly integrated treatment experience. As a Doctor of Chiropractic (DC) and a board-certified Family Nurse Practitioner (APRN, FNP-BC), I have always believed in looking at the whole person, not just isolated symptoms. This philosophy is the cornerstone of our clinic.

A pivotal part of our collaborative team is our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is Board Certified in Internal Medicine and brings over 40 years of invaluable experience as an internist to our practice (NPI #1164426749, Texas MD License #J2933). Her profound expertise provides the essential medical oversight that allows us to safely and effectively integrate a wide range of therapies. This model, where a Medical Doctor provides direction alongside a chiropractor and other specialists, is common in forward-thinking integrative and injury care clinics, and it ensures our patients receive the highest standard of care.

Our team synergistically combines:

  • Chiropractic Care (Dr. Alex Jimenez): Focusing on musculoskeletal alignment, nervous system function, and the body’s innate ability to heal.
  • Medical Oversight (Dr. Maria Cardenas): Providing diagnostic expertise, managing complex medical conditions, and ensuring all treatments are medically sound and appropriate.
  • Functional Medicine: Investigating the root causes of disease by looking at genetics, environment, and lifestyle factors.
  • Personal Injury Care & Rehabilitation: Offering specialized protocols for recovery from accidents and injuries.
  • Advanced Regenerative Therapies: Utilizing cutting-edge treatments like shockwave therapy, PRP, and peptide therapy to restore function and promote healing.

This integrated framework allows us to create highly personalized treatment plans. When a patient presents with a complex issue like erectile dysfunction, we don’t just offer a single solution. We conduct a thorough evaluation that includes a chiropractic assessment of spinal and pelvic alignment (which can affect nerve function to the pelvic region), a medical workup supervised by Dr. Cardenas to rule out cardiovascular or endocrine issues, and a functional medicine analysis to explore hormonal balance and lifestyle factors. This holistic approach ensures we are not just treating symptoms but are truly addressing the underlying cause of the condition, leading to more sustainable and meaningful results for our patients.


Understanding Erectile Dysfunction: More Than Just a Symptom

When I begin a discussion on men’s health, I often find a mix of apprehension and curiosity in the room. A topic like Erectile Dysfunction (ED) can be difficult for many men to talk about, yet it is an incredibly common and important health issue. I want to assure you that this is a safe and educational space to explore this topic. When I recently asked a room full of people to raise their hands if they or their partner had experienced ED, it was telling that many women raised their hands. This highlights that ED is a condition that affects not just the individual but also their relationships and loved ones.

ED is formally defined as the persistent inability to attain or maintain an erection sufficient for satisfactory sexual performance. Beyond the immediate impact on sexual function, it profoundly affects a man’s quality of life, self-esteem, and intimate relationships. However, one of the most critical points I want to emphasize is this: ED is often the first sign of underlying cardiovascular disease.

If you take nothing else away from this post, please remember this: when a patient comes to my office and says, “Doc, I’m having trouble with erections, what can you do for me besides the blue pill?” my first thought isn’t just about sexual function. My first thought is about their heart. ED and cardiovascular disease share the same root cause in many cases: endothelial dysfunction, which is the damage to the inner lining of blood vessels. The penile arteries are much smaller than the coronary arteries of the heart. This means they are often the first to show signs of blockage or damage from conditions like atherosclerosis (the hardening and narrowing of arteries). This makes ED a “canary in the coal mine” for future, more serious cardiovascular events like a heart attack or stroke. Therefore, a thorough investigation for cardiovascular risk factors is a non-negotiable part of our evaluation for any man presenting with ED.

The Staggering Prevalence of Erectile Dysfunction

The numbers surrounding ED are truly astonishing and underscore why this is a public health concern we must address openly. It is a condition that increases significantly with age.

  • Globally, over 150 million men were affected by ED as of 2025, and this number is steadily rising.
  • Age is a primary factor. While it can affect men at any age, the prevalence climbs with each passing decade.
  • Hormonal changes, particularly declining testosterone levels, are a contributing factor. It’s important to clarify that low testosterone doesn’t directly cause ED in most cases, but it significantly contributes to reduced libido and can worsen existing erectile problems.

The Multifactorial Etiology of ED

To effectively treat ED, we must first understand its complex web of causes. It’s rarely a single-issue problem.

  • Vasculogenic (Most Common): This refers to problems with blood flow. Atherosclerosis is the chief culprit here. Plaque buildup in the arteries restricts blood flow to the penis, making it difficult to achieve an erection. This is also linked to impaired nitric oxide (NO) signaling. Nitric oxide is a crucial molecule that tells the smooth muscles in the penile arteries to relax, allowing blood to rush in and create an erection. When endothelial cells are damaged, they produce less NO, disrupting this entire process. This is precisely why regenerative therapies that improve blood flow, like shockwave therapy, can be so effective.
  • Neurogenic: Erections are controlled by a complex interplay of nerve signals from the brain, spinal cord, and pelvic region. Conditions like diabetes (which causes diabetic neuropathy), multiple sclerosis, spinal cord injuries, or nerve damage from pelvic surgery (e.g., radical prostatectomy) can interrupt these signals.
  • Hormonal: As mentioned, low testosterone (hypogonadism) is a significant contributor, primarily by reducing sexual desire (libido). We will explore this in-depth later, as optimizing hormone levels is a foundational step in treating many men with ED.
  • Psychogenic: The mind and body are inextricably linked. Depression, anxiety, stress, and relationship issues can all have a profound negative impact on sexual function. The psychological burden of ED can also create a vicious cycle of performance anxiety, further worsening the problem.
  • Drug-Induced (Very Common): This is likely the second most common cause after vasculogenic issues. A vast number of common medications can cause or worsen ED. These include:
    • Nearly all classes of blood pressure medications (beta-blockers, diuretics).
    • Antidepressants, especially SSRIs (Selective Serotonin Reuptake Inhibitors).
    • Antipsychotics.
    • Opioids and other narcotics.
  • Iatrogenic: This means the condition is caused by a medical treatment. Pelvic surgery, particularly for prostate or bladder cancer, and radiation therapy to the pelvic region can damage the delicate nerves and blood vessels essential for erectile function.

The Limitations of Traditional Therapies

For decades, the primary treatment for ED has been PDE5 inhibitors, the class of drugs that includes sildenafil (Viagra), tadalafil (Cialis), and vardenafil (Levitra). These drugs work by enhancing the effects of nitric oxide. They block the enzyme phosphodiesterase type 5 (PDE5), which normally breaks down cGMP, a molecule that promotes vasodilation. By blocking PDE5, these drugs allow cGMP to accumulate, leading to more sustained relaxation of the smooth muscles and improved blood flow.

While these pills have helped millions of men, they are not a perfect solution. They are a symptomatic treatment, not a cure. They do nothing to address the underlying atherosclerosis, nerve damage, or hormonal imbalances.

Furthermore, they come with notable drawbacks:

  • Side Effects: Common side effects include headaches, flushing, nasal congestion, indigestion, and visual disturbances.
  • Tachyphylaxis: This is a significant issue I see in my practice. Tachyphylaxis is a phenomenon where the body develops a rapid tolerance to a drug, requiring higher and higher doses to achieve the same effect. A patient might come in and say, “Doc, the Viagra worked great for a few months, but now I have to take 100mg, and even that’s not working as well. I’m trying 150mg.” They are chasing a diminishing return. This happens very, very quickly with PDE5 inhibitors for many men.

This is where our journey into regenerative medicine begins. We have better options that go beyond simply managing symptoms. We can offer therapies that aim to restore and regenerate the natural function of the erectile tissues.


Regenerative Solutions: Extracorporeal Shockwave Therapy (ESWT)

This brings us to one of the most exciting and promising treatments for ED: Extracorporeal Shockwave Therapy (ESWT). This is a non-invasive therapy that uses high-frequency, low-intensity acoustic waves to stimulate the body’s own healing processes within the penile tissue. It is a cornerstone of our restorative approach to men’s health.

How Shockwave Therapy Restores Erectile Function

The science behind ESWT is elegant and powerful. The acoustic waves are delivered to the penile shaft and crus (the base of the penis) using a specialized wand. These waves generate a force that creates what we call controlled microtrauma in the tissue.

Now, the word “trauma” might sound alarming, but this is a key concept in regenerative medicine. I often tell my patients, “Inflammation, in the right context, is good. I love inflammation. What I don’t like is chronic, uncontrolled hyperinflammation.” This controlled microtrauma triggers a localized, acute inflammatory response. This is the body’s natural “call to action.”

This process mobilizes the body’s entire repair crew to come to the area and restore it. Specifically, the shockwaves cause a cascade of biological effects:

  1. Stimulation of Angiogenic Factors: The microtrauma upregulates the release of powerful growth factors, most notably Vascular Endothelial Growth Factor (VEGF). VEGF is the master signal for angiogenesis, which is the formation of new blood vessels.
  2. Neovascularization: In response to VEGF and other signals, the body begins to build new, healthy blood vessels (capillaries) within the corpus cavernosum—the sponge-like erectile chambers of the penis. This process directly counteracts the effects of vasculogenic ED by improving the blood supply.
  3. Improved Endothelial Function: The therapy also helps to regenerate and repair the endothelium, the inner lining of existing blood vessels. A healthier endothelium means better production of nitric oxide (NO), leading to improved vasodilation and stronger, more spontaneous erections.
  4. Recruitment of Stem Cells: The inflammatory signals also attract the body’s own resident stem cells to the area, further promoting tissue repair and regeneration.

In essence, shockwave therapy is not a band-aid. It is a regenerative modality that aims to physically reverse the underlying pathology of vasculogenic ED. It opens up old, clogged pathways and builds new ones, fundamentally improving blood flow to the penis. The evidence for its efficacy is robust, with numerous studies available on platforms like PubMed demonstrating significant improvements in erectile function, especially for men with mild to moderate vasculogenic ED (Gruenwald et al., 2012; Kitrey et al., 2016).

This therapy can be administered right in the office. For men who may feel uncomfortable with in-office treatments, technology has advanced to the point where there are now effective at-home devices. For instance, we might discuss a handheld device—we call ours the EDX—which is a more affordable alternative to well-known brands like The Phoenix. This allows patients to continue and perpetuate the benefits of their in-office treatments in the privacy of their homes. These devices are also versatile and can be used for other musculoskeletal conditions like plantar fasciitis.


Regenerative Solutions: Platelet-Rich Plasma (PRP) Therapy

Another powerful tool in our regenerative arsenal is Platelet-Rich Plasma (PRP) Therapy. This therapy harnesses the healing power of a patient’s own blood to rejuvenate tissues. When used for ED, it is often referred to as the “P-Shot.”

The Mechanism of PRP in Tissue Regeneration

So, how does it work? The process is straightforward but scientifically profound.

  1. Blood Draw: We start by drawing a small amount of the patient’s own blood, just like a standard lab test.
  2. Centrifugation: The blood is placed in a centrifuge, a machine that spins at high speed to separate the blood components. This process concentrates the platelets into a small volume of plasma. This resulting platelet-rich plasma contains 5 to 10 times the concentration of growth factors found in normal blood.
  3. Injection: This “liquid gold” is then carefully and strategically injected into specific areas of the penis, including the corpus cavernosum.

Once injected, the concentrated platelets are activated and release a symphony of growth factors. These are the same signaling proteins that your body uses to heal a cut or a broken bone. Key growth factors include:

  • Platelet-Derived Growth Factor (PDGF): Stimulates cell growth, replication, and angiogenesis.
  • Transforming Growth Factor-Beta (TGF-β): Promotes tissue matrix formation and cell differentiation.
  • Vascular Endothelial Growth Factor (VEGF): As with shockwave therapy, this is crucial for forming new blood vessels.
  • Epidermal Growth Factor (EGF): Stimulates cell growth and differentiation.
  • Fibroblast Growth Factor (FGF): Important for tissue repair and cell proliferation.

The combined effect of these growth factors is a powerful stimulus for tissue regeneration, angiogenesis (new blood vessel formation), and nerve regeneration. Research, particularly in diabetic and post-prostatectomy animal models—two of the most challenging patient populations to treat—has shown that PRP can improve smooth muscle content in the corpus cavernosum and promote the regeneration of damaged nerves (Ding et al., 2019). The goal is to repair and rejuvenate the fundamental structures needed for a healthy erection: the blood vessels, nerves, and smooth muscle tissue.

The Synergistic Power of Combination Therapy

In our clinic, we have observed that the most profound results often come from combining therapies. Shockwave therapy and PRP work together with a powerful synergistic effect.

Think of it this way:

  • Shockwave therapy (ESWT) acts like the “tiller” in a garden. It breaks up the old, compacted soil (fibrotic tissue and plaque), aerates it, and prepares the environment for new growth. It creates the microtrauma and inflammatory signals that call for repair.
  • PRP therapy acts like the “fertilizer and seeds.” It delivers a highly concentrated dose of the growth factors and regenerative cells needed to build new structures in the prepared environment.

By using ESWT first to “prime” the tissue and then following up with PRP, you get more out of both treatments. If you are a practitioner who performs injections, this combination is a game-changer. Even for non-injectors, offering shockwave therapy alone provides a fantastic regenerative option.

Both of these therapies are minimally invasive. Patients may experience some minor local discomfort or bruising at the injection site with PRP, but there are no serious systemic side effects associated with either treatment, which stands in stark contrast to the potential side effects of oral medications.

The ultimate message here is that when traditional therapies fail or are not well-tolerated, we have real, evidence-based answers. With shockwave therapy and PRP, we are not just treating symptoms; we are treating the underlying cause of the problem.


Addressing a Common Question: Post-Prostatectomy and Cancer Patients

A question that frequently comes up is regarding patients who have undergone treatment for prostate cancer. For example, a man who has had a radical prostatectomy (surgical removal of the prostate), radiation therapy, and perhaps subsequent hormone therapy. Are these men still candidates for regenerative treatments like ESWT, PRP, and peptides?

The answer is a resounding yes, absolutely. In fact, this is one of the most important patient populations we can help. These treatments are often the only hope for restoring natural erectile function after the nerves and blood vessels have been damaged by surgery or radiation.

However, there are important considerations regarding the timing of these treatments, especially concerning cancer. For many years, the standard dogma was to wait a full five years after cancer treatment was completed before starting any therapy that could potentially stimulate tissue growth, including testosterone replacement. The fear was promoting a recurrence of the cancer.

Fortunately, the guidelines are evolving based on new evidence. The American Urological Association (AUA) has updated its stance. The consensus is now shifting towards a much shorter window. Instead of the rigid five-year rule, we are now looking at a one- to two-year window after the completion of treatment. So, if a man has finished his radical prostatectomy and any subsequent therapies, and his PSA levels are stable and undetectable, we can confidently begin regenerative therapies like ESWT, PRP, and even certain peptides after one to two years. This is a monumental shift that allows us to help these men regain their quality of life much sooner.


The Foundational Role of Hormones: The Testosterone Connection

Now, I’m going to take this discussion to the next level. I have had countless conversations with patients and practitioners who are excited about the world of peptides and regenerative medicine. They might say, “Doc, I tried these peptides, but they don’t seem to be working,” or “I’m ready to start, what should I take?”

Before embarking on any peptide journey or advanced regenerative protocol, I must stress this: you have to check the hormones first.

I am a huge advocate for peptides; they are a revolutionary field of medicine. But they are not magic bullets that work in a vacuum. They work within the body’s existing biochemical environment. If that environment is fundamentally out of balance, the peptides will not be able to perform their function effectively. You must ensure that the foundational systems—thyroid, adrenal (cortisol), and especially sex hormones like testosterone and estrogen—are optimized.

I have seen it time and time again in my practice. A man comes in with ED, fatigue, and low libido, asking for the latest peptide or regenerative treatment. We run a simple blood test, and the results are earth-shattering: his testosterone is in the basement. By simply addressing this foundational hormonal deficiency, we can unlock the potential for all other therapies to work in the most efficacious manner.

The Physiology of Testosterone Production

Let’s do a quick review of how testosterone is made. It’s a beautifully orchestrated system known as the Hypothalamic-Pituitary-Gonadal (HPG) Axis:

  1. The hypothalamus in the brain releases Gonadotropin-Releasing Hormone (GnRH).
  2. GnRH travels to the pituitary gland and tells it to release two key hormones: Luteinizing Hormone (LH) and Follicle-Stimulating Hormone (FSH).
  3. LH travels through the bloodstream down to the testicles and stimulates the Leydig cells to produce and release testosterone.
  4. FSH stimulates the Sertoli cells in the testicles, which are responsible for sperm production (spermatogenesis).

The Epidemic of Low Testosterone (Hypogonadism)

Low testosterone is incredibly common, and its prevalence mirrors that of ED. It is estimated that nearly 30 million men affected by ED also have low testosterone. The levels naturally decline with age, beginning around age 30-40 and decreasing by about 1-2% per year.


I use a simple “rule of 10” to help remember the trend:

  • At age 40, about 40% of men have low testosterone.
  • At age 50, about 50% of men have low testosterone.
  • At age 60, about 60% of men have low testosterone.
  • By age 70, a staggering 70% of men have clinically low testosterone levels.

This makes it an easy thing to keep in the back of your mind. When a man in his 50s or 60s presents with relevant symptoms, there’s a very high probability that low testosterone is part of the clinical picture.

Symptoms and Signs of Low Testosterone

The symptoms of low testosterone are often insidious and can be mistaken for the normal aging process. It’s crucial to listen for these clues:

  • Decreased libido (sex drive): This is often the most prominent and specific symptom.
  • Erectile dysfunction: While not the direct cause, low T worsens ED and blunts the response to other treatments.
  • Fatigue and decreased energy levels.
  • Depressed mood and irritability.
  • Poor memory and “brain fog.”
  • Decreased muscle mass and strength.
  • Increased body fat, especially around the waist.
  • Diminished body and facial hair.
  • Delayed ejaculation.

On physical exam, we look for:

  • Gynecomastia: Development of breast tissue in men. This is due to an imbalance between testosterone and estrogen.
  • Small, soft testes.
  • Large waist circumference: Obesity is a major factor.

The Critical Link Between Obesity and Low Testosterone

I want to spend a moment on the connection between obesity and testosterone because it’s a trap many clinicians fall into. Over 50% of heavier men exhibit low testosterone. However, you might send them for a standard testosterone blood test, and it comes back “normal.” How can this be?

The answer lies in a protein called Sex Hormone-Binding Globulin (SHBG). SHBG is like a taxi for hormones; it binds to testosterone in the bloodstream, rendering it inactive. Only the “free” or unbound testosterone is biologically active and can exert its effects on tissues.

Heavier individuals, particularly those with insulin resistance, tend to have lower levels of SHBG. When SHBG is low, a larger percentage of the total testosterone is “free.” This can make the total testosterone level appear normal on a lab report, even when the man is clinically hypogonadal and symptomatic.

This is a critical takeaway: In a heavier patient, you must order not only a total testosterone level but also a free testosterone level and an SHBG level. The free testosterone will often reveal the true deficiency.

The Broader Health Implications of Low Testosterone

Low testosterone is not just about sex and muscles. It is associated with a host of serious chronic diseases:

  • Type 2 Diabetes: Higher testosterone levels are associated with a lower risk of developing diabetes. Testosterone improves insulin sensitivity.
  • Sleep Apnea: This is a two-way street. Low testosterone can contribute to obesity, which worsens sleep apnea. Conversely, when you give a man testosterone replacement therapy (TRT), you must be cautious if he has underlying sleep apnea. Testosterone can relax the muscles in the upper airway, potentially making the apnea worse. Always screen for sleep apnea in heavier patients before starting TRT.
  • Cardiovascular Disease: Low T is linked to hypertension and hyperlipidemia.
  • COPD and Kidney Disease.
  • Rheumatoid Arthritis: Interestingly, low testosterone has been shown to elevate the risk of developing this autoimmune condition.

Diagnosing Hypogonadism: A Step-by-Step Guide

Diagnosing low testosterone requires a careful and systematic approach. It’s not just about a number on a lab report.

  1. Clinical Suspicion: It starts with the patient’s symptoms and a thorough history and physical exam. To help overcome the barrier of men being hesitant to discuss these issues, we use validated questionnaires in our office.
    • The ADAM (Androgen Deficiency in Aging Males) questionnaire is a simple screening tool. The two most important questions are: “Do you have a decrease in libido?” and “Are your erections less strong?” This questionnaire has an 88% sensitivity for detecting low testosterone.
    • The SHIM (Sexual Health Inventory for Men) questionnaire is another excellent tool that is highly specific for identifying men with low testosterone and ED.
  2. Laboratory Testing:
    • Timing is Everything: Testosterone levels are highest in the morning. Therefore, you must always draw the labs first thing in the morning, ideally before 8 or 9 a.m.
    • Confirm the Result: A single low reading is not enough for a diagnosis. The AUA guidelines recommend getting at least two separate morning samples and using the lower of the two values for diagnosis.
    • The Diagnostic Threshold: The generally accepted cutoff for hypogonadism is a total testosterone level of less than 300 ng/dL, in the presence of associated symptoms. I cannot stress this enough: we treat the patient, not the number. A man with a level of 250 ng/dL who feels fantastic and has no symptoms does not require treatment. A man with a level of 350 ng/dL who has severe symptoms may be a candidate for therapy.
  3. Differentiating the Cause (Primary vs. Secondary Hypogonadism):
    • Once you’ve confirmed low testosterone, the next step is to check a Luteinizing Hormone (LH) level. This tells you where the problem is.
    • Primary Hypogonadism: This means the problem is in the testicles. The testicles are failing to produce testosterone despite the pituitary gland’s signals. In this case, you will see low testosterone and a high LH. The pituitary is “shouting” at the testicles to work, but they can’t respond.
    • Secondary Hypogonadism: This means the problem is in the brain (hypothalamus or pituitary). The testicles are fine, but they aren’t receiving the signal to produce testosterone. In this case, you will see low testosterone and a low or inappropriately normal LH.
  4. Further Workup for Secondary Hypogonadism:
    • If you find a combination of low testosterone and low LH, it is crucial to check a prolactin level. An elevated prolactin level can suggest a prolactinoma, a benign tumor of the pituitary gland that can suppress the HPG axis. These are more common than you might think and require referral to an endocrinologist.
    • Also, check an estradiol (estrogen) level, especially if the patient has gynecomastia. For optimal health, a man needs a healthy ratio of testosterone to estradiol, typically around 20:1. When testosterone levels drop, this ratio can fall to 15:1 or even 10:1, leading to estrogen-dominant symptoms.

Guidelines for Testosterone Replacement Therapy (TRT)

Once a diagnosis is made, the primary goal of TRT is to reduce symptoms, not to chase a specific number on a lab report. The therapeutic benefits extend far beyond sexual function, including improved bone density, better glucose control in diabetics, increased lean muscle mass, and fat loss.

  • Treatment Goal: The “utopian” target range for total testosterone is typically between 450 and 600 ng/dL. In reality, it can be challenging to keep levels in this narrow range, and they often fluctuate. The key is to find the lowest effective dose that alleviates the patient’s symptoms. It’s not uncommon for levels to reach 800 or 900 ng/dL, which is generally safe as long as other markers are monitored. We want to avoid supra-physiological levels (well over 1,000 ng/dL).
  • Contraindications and Cautions:
    • Active Prostate Cancer: TRT is generally contraindicated in men with active, untreated prostate cancer. However, as discussed, men who have been successfully treated for prostate cancer can often start TRT after a 1-2 year waiting period.
    • Recent Cardiac Event: You should not initiate TRT within three to six months of a major cardiac event like a heart attack or severe arrhythmia without first consulting the patient’s cardiologist.
    • Severe Benign Prostatic Hyperplasia (BPH): Men with severe lower urinary tract symptoms may see them worsen on TRT.
    • Erythrocytosis: An elevated red blood cell count.
  • Monitoring During Therapy: This is absolutely critical for safety.
    • Hematocrit: Testosterone stimulates the bone marrow to produce red blood cells. This can lead to erythrocytosis or polycythemia, a condition where the blood becomes too thick, increasing the risk of blood clots, stroke, and heart attack. You must monitor the complete blood count (CBC) and hematocrit regularly. If the hematocrit rises above 54%, the dose needs to be lowered, or the patient may need to donate blood (therapeutic phlebotomy).
    • Prostate-Specific Antigen (PSA): We monitor PSA levels to screen for any changes in the prostate.
    • Symptom Improvement: Regular follow-ups are essential to ensure the therapy is working and to make dose adjustments as needed.

It’s important to remember that TRT is not a primary treatment for ED. Its main effect is on libido. However, by restoring libido and creating a more favorable hormonal environment, it significantly enhances the response to other ED treatments like PDE5 inhibitors, shockwave therapy, and PRP. For men experiencing tachyphylaxis with Viagra or Cialis, optimizing their testosterone can often make those drugs effective again at lower doses.


Peptide Therapies for Men’s Health and Sexual Function

With a solid hormonal foundation in place, we can now intelligently incorporate advanced peptide therapies to further enhance sexual function, vitality, and overall well-being. Peptides are short chains of amino acids that act as signaling molecules in the body, directing cells to perform specific functions.

Gonadotropin-Based Peptides for Natural Testosterone Support

For men who want to increase their testosterone levels without shutting down their body’s own production (which is what happens with exogenous testosterone), or for those concerned about fertility, gonadotropin-based peptides are an excellent option.

  • Human Chorionic Gonadotropin (hCG): hCG is a peptide that mimics the action of Luteinizing Hormone (LH). It directly stimulates the Leydig cells in the testicles to produce more of the man’s own endogenous testosterone. This is a great strategy for “restarting” the HPG axis. It’s also used in combination with TRT to prevent testicular atrophy and maintain fertility. Potential side effects include an increase in estradiol (as testosterone is aromatized into estrogen), oily skin, and water retention.
  • Gonadorelin: This is a synthetic version of Gonadotropin-Releasing Hormone (GnRH). It works upstream by stimulating the pituitary gland to release its own LH and FSH. This encourages a more natural, pulsatile production of testosterone and also supports sperm production (via FSH stimulating the Sertoli cells). It is an excellent choice for men on TRT who wish to maintain fertility.

Peptides for Libido, Erection Quality, and Overall Vitality

  • PT-141 (Bremelanotide): This is a unique and powerful peptide specifically approved for low libido in women, but it is highly effective in men as well. It works centrally in the brain on melanocortin receptors to directly increase sexual desire. Importantly, its mechanism of action is independent of the nitric oxide pathway. This makes it an excellent option for men who do not respond well to PDE5 inhibitors. It can improve libido, enhance sexual desire, and improve erectile quality. The primary side effect is nausea, which affects about 40% of users, especially women. The key is to start with a very low dose and titrate up slowly.
  • CJC-1295/Ipamorelin: This is a popular combination peptide that stimulates the body’s own production and release of Growth Hormone (GH). CJC-1295 is a Growth Hormone-Releasing Hormone (GHRH) analog, while Ipamorelin is a ghrelin mimetic (a secretagogue). They work synergistically to create a strong, natural, pulsatile release of GH from the pituitary gland. While not a direct treatment for ED, the downstream effects of optimized GH levels include improved sleep quality, fat loss (especially visceral fat), enhanced muscle recovery, and a significant boost in energy and sexual vitality.
  • BPC-157 and TB-500 (The “Wolverine Stack”): This is our go-to combination for systemic tissue repair and regeneration.
    • BPC-157 (Body Protection Compound): This peptide is a phenomenal healing agent that seems to repair almost every tissue in the body. For sexual health, its most relevant properties are its ability to stimulate angiogenesis (new blood vessel growth) and modulate nitric oxide signaling, both of which are crucial for erectile function.
    • TB-500 (Thymosin Beta-4): This peptide is the perfect partner to BPC-157. If BPC-157 is the “general contractor” bringing all the materials (growth factors, cells) to the construction site, TB-500 is the “master engineer” organizing everything and directing the cellular processes of repair and regeneration.

Using these two together can help repair the micro-damage in the blood vessels and tissues of the penis, supporting the effects of treatments like shockwave therapy and PRP.

Intelligent Combination Protocols

The real art of functional and regenerative medicine lies in combining these therapies for a synergistic effect.

  • For Testosterone Support Without Fertility Issues: Combining TRT with low-dose hCG can maintain testicular size and function while providing stable testosterone levels.
  • For Enhanced Libido and Erection Quality: Combining a PDE5 inhibitor (like Cialis) with PT-141 can be incredibly effective, as they work on two different pathways (nitric oxide and central melanocortin receptors, respectively).
  • For Anti-Aging and Sexual Vitality: A protocol using CJC-1295/Ipamorelin can improve overall health, body composition, and energy, which naturally translates to better sexual function.

By layering these sophisticated therapies on top of a solid foundation of optimized hormones and a healthy lifestyle, we can create truly transformative results for our patients.


A Final Word on the Future of Men’s Health

We have journeyed through the complexities of erectile dysfunction, the foundational importance of testosterone, and the exciting frontier of regenerative medicine with shockwave therapy, PRP, and peptides. The message I want to leave you with is one of hope and empowerment.

The days of viewing ED as an inevitable consequence of aging or simply handing out a prescription for a blue pill are over. We now understand that ED is a critical health marker, often signaling deeper cardiovascular issues. We have a full toolbox of modern, evidence-based therapies that can do more than just manage symptoms—they can restore function, regenerate tissue, and address the root causes of the problem.

By taking an integrated, whole-person approach, conducting thorough evaluations, and personalizing treatment plans, we can help men not only regain their sexual confidence but also improve their overall health and vitality. The result is happier, healthier patients who are empowered to live their lives to the fullest. And when you create happy patients, they become your greatest advocates, sharing their success stories and helping countless others find their way to better health. Ultimately, this is why we do what we do, and it is the key to building a successful and fulfilling practice.

Unlocking Vitality: Chiropractic Wisdom and the Science of Functional Healing | El Paso, Tx (2024)

References

  • Ding, X., Li, S., Wang, X., Wang, Z., Gao, Y., Chen, S., & Li, Z. (2019). The role of platelet-rich plasma in the treatment of erectile dysfunction: An overview. Sexual Medicine Reviews, 7(2), 320–328. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6342907/
  • Gruenwald, I., Appel, B., & Vardi, Y. (2012). Low-intensity extracorporeal shock wave therapy—a novel effective and curative treatment for erectile dysfunction. The Journal of Sexual Medicine, 9(1), 259–264. https://pubmed.ncbi.nlm.nih.gov/22423129/
  • Kitrey, N. D., Gruenwald, I., Appel, B., Shechter, A., Massarwi, O., & Vardi, Y. (2016). Penile low intensity shock wave treatment is able to shift PDE5i nonresponders to responders: A long-term follow-up study. The Journal of Urology, 195(6), 1864–1868. https://pubmed.ncbi.nlm.nih.gov/27197779/
  • Rastrelli, G., & Maggi, M. (2017). Erectile dysfunction in men with testosterone deficiency. Sexual Medicine Reviews, 5(2), 214–228. https://pubmed.ncbi.nlm.nih.gov/27889396/

Regenerative Medicine for Health Restoration in Integrative Care

Discover the role of regenerative medicine with integrative care in modern healthcare and its benefits for patient recovery and wellness.

Educational Abstract: Muse Stem Cells, Integrative Chiropractic Care, and Multidisciplinary Regenerative Strategies

In this educational post, I summarize the latest discourse around Muse stem cells—multilineage-differentiating, stress-enduring cells—and explore how these findings may interface with integrative chiropractic care, functional medicine, personal injury care, and rehabilitation. I highlight the physiology behind Muse cell homing, stress endurance, and pluripotent activity across all three germ layers, with attention to safety, dosing, and manufacturing considerations. I also explain our multidisciplinary model in El Paso, Texas, where I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, collaborate with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine) (NPI #1164426749, Texas MD License #J2933), who serves as Medical Director and Collaborative Physician at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic). Together, we integrate chiropractic care and medical oversight with functional medicine and rehabilitation protocols to deliver evidence-guided, patient-centered results. Clinical observations from my practice and published literature are combined to create a practical framework for care.

Muse Stem Cells: What I’m Seeing and Why It Matters

Over the past year, I have been closely tracking the emergence of Muse stem cells—cells that are identified by the SSEA-3 surface marker and selected under lethal stress conditions. In conversations with colleagues nationwide, I’ve heard a consistent theme after patient treatments: “Godsend.” While anecdotes never substitute for rigorous evidence, the convergence of enthusiastic clinical feedback with a growing peer-reviewed literature caught my attention.

The narrative from the field is that conventional mesenchymal stem cells (MSCs) can deliver musculoskeletal relief. Still, Muse cells may extend capabilities beyond the mesoderm, demonstrating potential across the ectoderm, mesoderm, and endoderm. As a clinician who blends chiropractic, functional medicine, and rehabilitative strategies, I’m most interested in how any regenerative technology can fit safely within a structured, medically supervised, integrative framework.

The key takeaways below are grounded in published research on Muse biology and stem cell trafficking principles, tempered by caution around claims that outpace validation. Where appropriate, I provide APA-7 citations and a reference list to support readers in exploring the literature further.

Physiological Foundations: Size, Homing, Stress Endurance, and Differentiation

  • Cell Size and Pulmonary First-Pass Effect
    • Muse cells have been reported to measure approximately 8–15 micrometers, smaller than many standard MSCs (~15–25 micrometers). The rationale offered is that smaller cells may be less subject to pulmonary trapping during intravenous delivery, improving systemic distribution.
    • Physiologically, IV-administered cells encounter the lung microvasculature first; larger cells often lodge in pulmonary capillaries, reducing delivery to distal targets. While smaller size can improve transit, actual target engraftment depends on receptor-mediated homing, local microenvironment, and survival under stress (Fischer et al., 2019).
  • Targeted Homing via Receptors and Chemotactic Gradients
    • Muse cells reportedly express S1P2 receptors, enabling chemotaxis toward sphingosine-1-phosphate (S1P) gradients released by injured tissues. Many injured stromal cells also release stromal cell-derived factor-1 (SDF-1/CXCL12), which can attract progenitors via CXCR4 axes (Fischer et al., 2019; Estrada et al., 2013).
    • Clinically, this suggests the biology itself can guide cell migration without external targeting technologies, but robust homing depends on receptor expression consistency, gradient strength, vascular integrity, and immune context.
  • Stress Endurance and Survival in Hostile Microenvironments
    • Muse cells are described as stress-enduring, isolated under heat and glass-induced stress, selecting for cells that resist hypoxia, oxidative stress, and proteolytic enzymes. This is physiologically meaningful: post-injury tissues feature low oxygen tension, high reactive oxygen species, and inflammatory proteases that can kill less resilient cells (Kurose et al., 2013).
    • Enhanced survival may extend the therapeutic window for paracrine signaling and potential cell fate conversion in target tissues.
  • Pluripotency Across All Three Germ Layers
    • Muse cells are characterized as pluripotent within adult tissues, capable of differentiating into lineages spanning ectoderm (e.g., neural, skin), mesoderm (e.g., muscle, bone), and endoderm (e.g., liver). They are identified by SSEA-3 positivity and comet-like differentiation behavior in stress contexts (Kurose et al., 2013; Wakao et al., 2014).
    • Reported mechanisms include direct tissue replacement, wherein Muse cells sense local transcription factors, adopt lineage-specific programs, and replace damaged cells—a claim that requires careful clinical confirmation in humans to define consistency, durability, and safety.
  • Paracrine Signaling from a Stress-Selected Parent Cell
    • Like MSCs, Muse cells release anti-inflammatory cytokines, growth factors, and exosomes/secretomes. Their stress-selected origin may produce a distinct signal profile that dampens apoptosis, stabilizes microvasculature, and modulates immune reactivity (Caplan & Dennis, 2006; Vizoso et al., 2017). For pain patients, improved paracrine signaling can reduce neuroinflammation and facilitate local repair.

Why use each mechanism therapeutically:

  • Smaller size and homing increase the odds that IV-delivered cells reach the injury site.
  • Stress endurance increases survival long enough to signal and potentially integrate.
  • Pluripotency expands tissue applications theoretically beyond musculoskeletal-only targets.
  • Paracrine signaling addresses the biochemical milieu that drives pain and degeneration.

Evidence Snapshot: What’s Established and What Requires Caution

  • Preclinical and Early Clinical Signals
    • Muse cells have been studied in animal models of cardiac injury, stroke, and liver disease, with reports of engraftment and functional improvement (Wakao et al., 2014; Jiang et al., 2016).
    • There are human pilot studies and early-phase trials in select indications, but scale, long-term outcomes, and standardized manufacturing across centers vary (Fujita et al., 2015; Kurose et al., 2013).
  • Manufacturing and Verification
    • Muse cells are identified via SSEA-3 and stress-selection protocols. Batches reported as SSEA-3 verified may reflect higher purity, but clinicians must demand Certificates of Analysis, tracking, sterility data, and independent validation of markers and functional assays (FDA, 2024; ISCT, 2019).
  • Dosing, Dilution, and Inflammation
    • Pure Muse formulations may produce excess inflammation due to robust activity. A buffered approach using MSCs with ~20% Muse content has been suggested to temper cytokine surges. Predilution is posited to reduce dosing error and minimize adverse events.
    • Clinically, we treat such products like high-potency biologics: low-and-slow titration, careful monitoring, and co-managed anti-inflammatory support as needed (Caplan & Dennis, 2006).
  • Extraordinary Claims (e.g., Biological Age Reversal)
    • Reports of multi-organ epigenetic age reduction after IV Muse plus exosomes and cord blood plasma (the “golden bag”) are intriguing but require peer-reviewed corroboration with transparent biomarker panels, reproducible methodology, and independent replication before broad clinical adoption (Levine, 2013; Horvath, 2013). We approach such claims with enthusiasm and caution.

Integrative Chiropractic Care: Where Musculoskeletal Recovery Meets Regeneration

As a chiropractor and nurse practitioner operating in an integrative model, I anchor care in the biomechanics and biochemistry of pain:

  • Chiropractic Adjustments and Neuro-Muscular Reeducation
    • Precision spinal and extremity adjustments restore joint kinematics, reduce nociceptive input, and normalize proprioceptive signaling to the CNS. Improved segmental motion reduces local hypoxia and metabolic waste, creating a better microenvironment for any regenerative intervention to function (Bialosky et al., 2009).
    • Post-adjustment stabilization via targeted exercises reconditions motor patterns, lowering reinjury risk and supporting tendon-ligament remodeling.
  • Functional Medicine Synergy
    • We address glycemic variability, mitochondrial health, and inflammatory drivers (e.g., gut dysbiosis, micronutrient deficits). Optimizing omega-3:omega-6 balance, vitamin D, magnesium, and polyphenols can enhance paracrine responsiveness and blunt excess cytokine activity following cell therapy (Calder, 2015).
    • Personalized sleep and stress interventions normalize HPA axis function, further improving tissue repair dynamics.
  • Rehabilitation and Bio-Scaffolding
    • Progressive eccentric loading, fascia mobilization, and neuromuscular cuing shape collagen alignment and mechanotransduction—the mechanical signals cells use to decide fate and function (Wang et al., 2009). If Muse or MSCs are used, scaffolded joint environments (e.g., Wharton’s Jelly gel) may hold cells in place to amplify local remodeling.
  • Medical Oversight for Safety and Outcomes
    • With Maria Guadalupe Cardenas, MD, we ensure proper indication selection, evaluate for contraindications, and provide pharmacologic and diagnostic support. This is especially crucial when using any biologic with paracrine potency.

Our Multidisciplinary Model in El Paso, Texas

  • Team Structure
    • I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, lead integrative chiropractic and functional medicine services at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas.
    • Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine) (NPI #1164426749, Texas MD License #J2933) serves as the Medical Director and Collaborative Physician, providing medical oversight typical of multidisciplinary injury and integrative clinics.
  • Workflow and Safety
    • Intake includes medical history, medication reconciliation, imaging if needed, and functional assessments.
    • If regenerative options are considered, Dr. Cardenas and I co-review labs (CBC, CMP, CRP), autoimmune screens if indicated, and discuss informed consent, risk-benefit, and adjunctive rehabilitation.
    • We track outcomes using pain scales, functional metrics (e.g., Oswestry, LEFS), and, when appropriate, biomarker panels.
  • Clinical Observations
    • At sciatica.clinic and in my LinkedIn clinical updates, I’ve noted that patients combining mechanical correction (adjustments, decompression), metabolic stabilization (nutrition, sleep, stress), and targeted rehabilitation often outperform those pursuing single-modality care. The promise of Muse cells—if validated—would be to fit within this triad, not replace it:
      • Reduce local inflammation via paracrine signaling.
      • Potentially contribute to tissue-specific repair in complex injuries.
      • Benefit from optimized biomechanics that reduce recurrent microtrauma.

Links:

Practical Protocol Considerations: Reasoning and Rationale

  • Patient Selection
    • Indications: refractory tendinopathies, degenerative joint pain, post-injury states with persistent deficits, and select neurological or systemic conditions only under medical supervision.
    • Contraindications: active infection, uncontrolled autoimmune activity, malignancy considerations, pregnancy, and any condition flagged by medical review.
  • Delivery Strategy
    • Local injections for focal musculoskeletal lesions may be considered in conjunction with bio-scaffolding to maintain residency.
    • Intravenous approaches require careful dose, dilution, and monitoring for inflammatory reactions. Where strong responses are expected, buffered formulations (e.g., MSC plus ~20% Muse content) may reduce cytokine surges.
  • Adjunctive Care
    • Prehabilitation: reduce systemic inflammation, optimize nutrient status, assess sleep quality.
    • Post-intervention: staged loading protocols, manual therapy for fascia, nerve gliding where appropriate, and gait retraining to optimize mechanotransduction.
  • Monitoring
    • Short-term: vitals, inflammation markers, pain/function scales.
    • Medium-term: imaging when indicated, functional performance tests, return-to-activity progression.
    • Documentation: maintain batch verification, SSEA-3 reports, and sterile processing data for traceability.
  • Avoiding Pitfalls
    • Do not rely solely on biologics to correct issues driven by poor biomechanics or unaddressed metabolic inflammation.
    • Be wary of non-diluted, non-verified products, and ensure patient expectations match current evidence.
Discovering the Benefits of Chiropractic Care | El Paso, Tx (2023)

Where Integrative Chiropractic Fits: The Bridge Between Structure and Biology

  • Why combine integrative chiropractic with regenerative care?
    • Adjustments and soft tissue work optimize joint mechanics, reducing shear and compressive stress that can derail cell-driven repair.
    • Functional medicine stabilizes systemic drivers of inflammation (glucose spikes, gut permeability, micronutrient deficiencies) that influence cell survival and repair signals.
    • Rehabilitation turns initial biological gains into durable functional improvements through graded exposure and neuromuscular consolidation.
  • Outcome Logic
    • Cells cannot succeed in a biomechanically hostile joint.
    • Pain reduction through paracrine effects must be matched with movement quality to sustain benefits.
    • Medical oversight ensures safety, manages reactions, and integrates pharmacologic support when needed.

A Realistic, Evidence-Guided Path Forward

The conversation around Muse stem cells is exciting, and early data suggest unique biology—SSEA-3 positive selection, stress endurance, pluripotency, and enhanced homing. As a clinician, I remain cautiously optimistic: we integrate promising tools with rigorous protocols, transparent verification, and a whole-person care model.

If Muse cells continue to prove safe and effective across controlled trials, they may become a valuable adjunct for complex musculoskeletal and possibly multisystem conditions. Meanwhile, our clinic’s integrated model—chiropractic, functional medicine, rehabilitation, and medical oversight—provides a stable platform to evaluate and responsibly incorporate emerging therapies.

Key Points Recap

  • Muse cells are described as stress-enduring, SSEA-3 positive, smaller than many MSCs, with potential pluripotent activity.
  • Homing mechanisms (S1P2, SDF-1/CXCL12) and paracrine signaling underpin their proposed efficacy.
  • Buffered dosing and predilution aim to reduce inflammatory reactions; batch verification is essential.
  • Our integrative team in El Paso—combining chiropractic, internal medicine oversight, functional medicine, and rehabilitation—creates a safe, effective framework for considering regenerative options.
  • Extraordinary claims (e.g., age reversal) demand peer-reviewed replication and standardized methodology before routine clinical adoption.

References

SEO tags: Muse stem cells, SSEA-3 marker, stress-enduring stem cells, pluripotent adult stem cells, regenerative medicine, integrative chiropractic, functional medicine, injury medical clinic, El Paso chiropractic, Dr. Maria Guadalupe Cardenas MD, Dr. Alex Jimenez DC, bio-scaffolding, Wharton’s Jelly, paracrine signaling, S1P2 receptor, SDF-1 CXCL12, pulmonary trapping, musculoskeletal rehabilitation, epigenetic age, multidisciplinary clinic, personal injury care